
Childhood Eczema: Do Steroids and Dupixent Affect Growth?
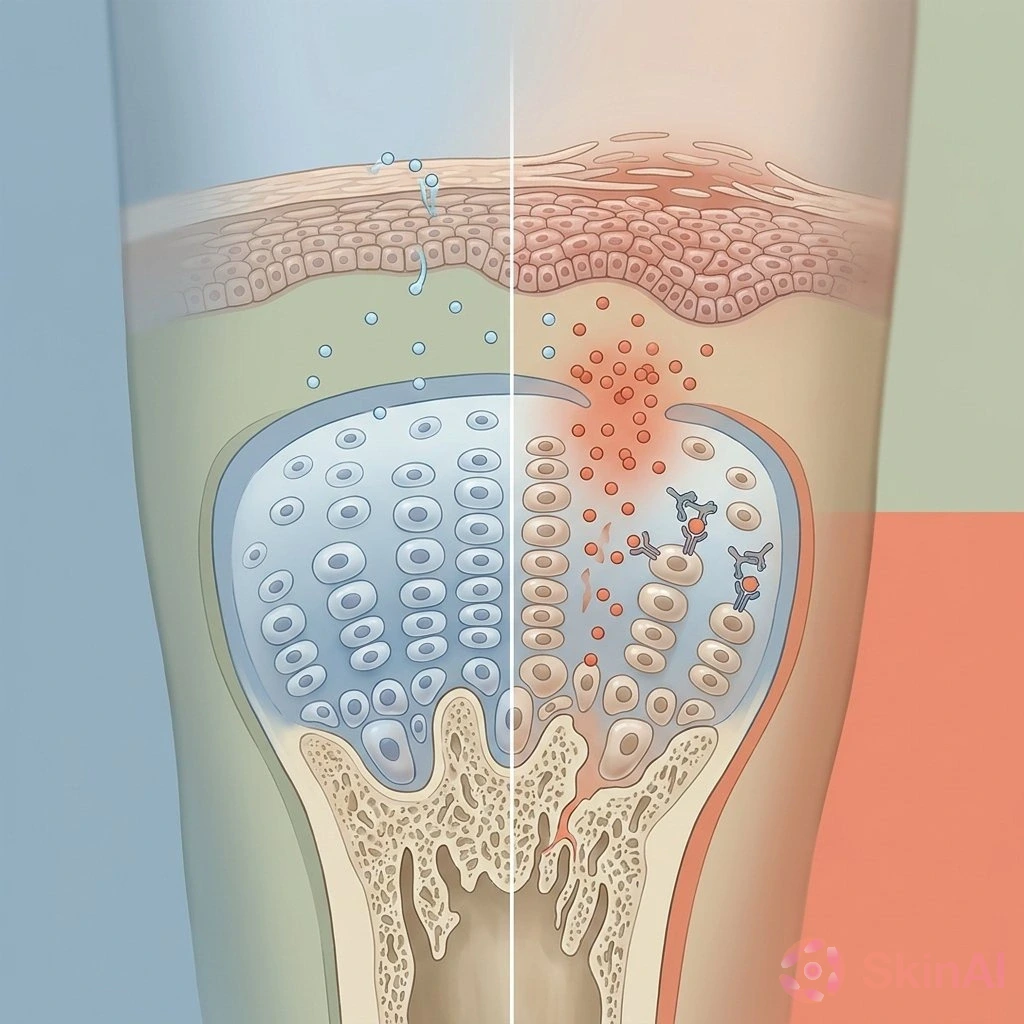
Atopic Dermatitis and Growth in Children: What the Research Shows
When a child has atopic dermatitis, a common type of eczema, families often focus on relieving itchy skin and preventing flare-ups. But for children with more severe symptoms, there may be other concerns too, including how the condition and its treatment could affect growth over time.
Research is beginning to explore whether controlling eczema and reducing its effects on sleep and daily life might be linked to changes in children’s growth. Scientists are also looking at whether long-term use of steroid creams plays a role.
In the second installment of the Dermatology Times Expert Perspectives series, “Beyond the Skin: Sleep, Steroids, and Growth in Children With Atopic Dermatitis,” dermatologist Lisa Swanson, MD, discusses emerging research on these questions, including studies of the medicine dupilumab (Dupixent). The findings are not conclusive, but they offer a starting point for broader conversations about caring for children with eczema. (Source: Dermatology Times, Expert Perspectives)
Why both eczema and its treatment matter
Steroid creams and ointments, also called topical corticosteroids, are an important part of eczema care for many children. They help calm skin inflammation, relieve itching, and manage flare-ups.
When prescribed and used appropriately, these medicines are generally considered safe. Still, some families worry about what might happen if a child needs them for a long time.
Some of the medicine can pass through the skin and into the body. This is more likely with stronger steroids, use over large areas, prolonged treatment, or application to skin whose protective barrier is damaged.
Too much exposure can raise concerns about suppression of the hypothalamic-pituitary-adrenal axis. This is the body’s system for making and regulating certain hormones, including cortisol. Excessive steroid exposure may also have other effects throughout the body.
At the same time, eczema that is not well controlled can mean ongoing inflammation, disrupted sleep, and a significant burden on a child’s daily life. These factors may also be relevant when considering growth.
That makes it difficult to know whether a difference in growth is related to steroid exposure, the underlying eczema, or a combination of factors. In the Expert Perspectives discussion, Swanson considers how to address families’ concerns about steroid use while also emphasizing the importance of controlling the disease. (Source: Dermatology Times, Expert Perspectives)
What a study found about dupilumab and height
Dupilumab is a biologic medicine, a treatment that targets specific parts of the immune system involved in inflammation. Researchers have studied whether treatment with dupilumab is associated with changes in growth among children with severe atopic dermatitis.
A 2026 analysis by Irvine and colleagues looked again at data from a clinical trial comparing dupilumab with a placebo, an inactive treatment. The researchers examined changes in children’s height percentiles, including in a group whose starting height was below the 40th percentile. (Source: Irvine and colleagues, 2026 post hoc analysis)
A height percentile shows how a child’s height compares with that of other children of the same age and sex. For example, being at the 40th percentile means a child is taller than about 40% of children in that comparison group. A change in percentile is not the same thing as a change in height measured in inches or centimeters.
Among children who started below the 40th percentile, those receiving dupilumab had greater odds of moving up at least 5 percentile points by week 16 than those receiving placebo. The reported unadjusted odds ratio was 2.5. This compares the odds in the two groups; it does not mean that children grew 2.5 times as much.
The researchers also considered two measures of steroid cream use. After accounting for the total amount of topical corticosteroid used, the odds ratio was 3.1. After accounting for the number of days without steroid cream use, it was 2.9. The association remained when these measured aspects of steroid exposure were considered. (Source: Irvine and colleagues, 2026 post hoc analysis)
There is an important limitation: This was a post hoc analysis, meaning the researchers examined the data after the original trial had been conducted. The findings are exploratory and do not prove that dupilumab directly makes children grow taller. They also cannot fully separate the effect of the medicine from any possible effect of better eczema control.
What happened during longer follow-up?
The researchers also looked at an extension of the trial. Children who had received placebo for the first 16 weeks then started dupilumab. In this part of the study, everyone knew which treatment the children were receiving, a design known as an open-label extension.
Researchers observed changes in height percentiles and a marker of bone formation in children who switched from placebo to dupilumab. These changes were similar to those seen in children who had received dupilumab throughout the treatment period. (Source: Irvine and colleagues, 2026 post hoc analysis)
Among children whose starting height was below the 40th percentile:
- Of those who switched from placebo to dupilumab, 40.4% moved up at least 5 height percentile points between weeks 16 and 52.
- Of those who received dupilumab continuously, 50.7% moved up at least 5 height percentile points during the same period.
These findings suggest that favorable changes in growth-related measures may also occur when children start dupilumab after an initial period without it. But because this part of the study was open-label and the analysis was exploratory, it cannot establish the best time to start treatment for growth outcomes.
Researchers continue to consider whether earlier, sustained control of severe eczema could affect broader aspects of development, especially in children whose height is already tracking at a lower percentile.
What a bone formation marker can and cannot tell us
Along with height, researchers have studied bone alkaline phosphatase, or BALP, in children receiving dupilumab. BALP is made by bone-forming cells and can provide clues about bone formation activity.
Interpreting BALP in children is not straightforward. Levels naturally change as children grow and move through different stages of development. A change in BALP does not, by itself, show that a child has stronger bones, greater bone density, or better long-term bone health.
The possible connection between dupilumab, eczema control, and bone formation is not yet fully understood. Researchers have suggested that less itching and better sleep could contribute to favorable growth-related changes. But the post hoc analysis did not directly measure sleep, so it cannot show whether sleep played a part. (Source: Irvine and colleagues, 2026 post hoc analysis)
What other studies have found
Clinical trials can help researchers compare treatments, while observational studies look at patterns among people receiving care in everyday settings. Both can add useful information, though they answer different kinds of questions.
In a 2025 study using the TriNetX health data network, Chen and colleagues looked back at records of children with atopic dermatitis and compared them with similar children without the condition. Children with eczema had a 15% higher relative risk of having a height below the fifth percentile. The reported relative risk was 1.15, with a 95% confidence interval of 1.12 to 1.18, a range reflecting the uncertainty around that estimate. (Source: Chen and colleagues, 2025 TriNetX retrospective cohort analysis)
This finding points to an association, not proof that eczema itself causes reduced growth. Because the researchers looked back at existing records, the study could not establish the cause of the height differences.
Another study looked at 47 children in Italy who were between 6 months and 5 years old and received dupilumab. Researchers found no negative effect on growth over 52 weeks. That is reassuring, but the study was small and observational, so its findings may not apply to every child. (Source: Italian multicenter retrospective study of 47 children)
Together, these studies suggest that growth is worth considering as part of eczema care. Larger studies that follow children over longer periods are still needed.
What this means for families
For children with moderate to severe eczema, treatment discussions may include more than what the skin looks like. A child’s growth pattern, sleep, ongoing inflammation, and exposure to steroid creams can all be part of the conversation.
The current evidence does not establish that dupilumab should be prescribed specifically to increase height or improve bone density. Treatment decisions depend on factors such as a child’s age, eczema severity, previous treatment response, and individual circumstances.
Families with questions about growth, steroid use, or treatment options should discuss them with their child’s doctor or dermatologist. A professional can also assess new or worsening skin changes, pain, bleeding, possible signs of infection, or any symptoms that cause concern.
This article is for information only and is not a substitute for advice from a qualified health professional.
Sources
- Dermatology Times. Expert Perspectives, “Beyond the Skin: Sleep, Steroids, and Growth in Children With Atopic Dermatitis,” second installment featuring Lisa Swanson, MD.
- Irvine and colleagues. 2026 post hoc analysis of height percentile changes and growth-related measures in children receiving dupilumab or placebo.
- Chen and colleagues. 2025 TriNetX retrospective cohort analysis of height in children with atopic dermatitis.
- Italian multicenter retrospective study of dupilumab and growth in 47 children aged 6 months to 5 years.