
Molluscum Contagiosum (ICD-10: B08) ⚠️
Molluscum Contagiosum: A Common Viral Skin Condition
Overview
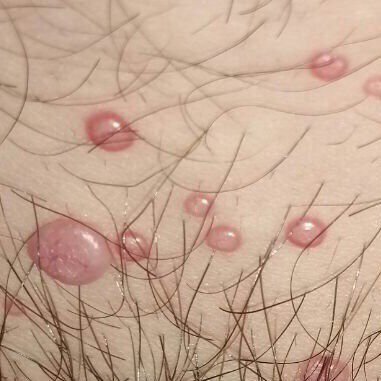
Molluscum contagiosum (MC) is a benign viral skin infection caused by the molluscum contagiosum virus (MCV), a member of the Poxviridae family. The disease manifests as small, raised, dome-shaped lesions that often have a central dimple or umbilication. Though harmless in most cases, MC is contagious and can spread through direct contact or contaminated objects, making it a public health concern in settings like schools, gyms, and swimming pools.
MC most commonly affects children and adolescents, but it can also appear in adults—particularly those with weakened immune systems or chronic skin conditions. While the lesions are generally painless and self-limiting, they may cause cosmetic concern, itching, and social discomfort, prompting individuals to seek treatment.
The infection is self-limiting and resolves without treatment within 6 to 12 months in most immunocompetent individuals, which is why observation alone is an appropriate choice for many healthy patients. Treatment is decided case by case, weighing the risk of autoinoculation and transmission to others against the fact that lesions are harmless and will clear on their own.
Predisposing Factors and Routes of Transmission
The primary cause of molluscum contagiosum is direct inoculation of the virus into the skin. The virus can be transmitted through skin-to-skin contact or via contact with contaminated objects such as towels, clothing, or shared bathwater. Common methods of transmission include:
- Childhood contact: Shared toys, towels, gym mats, or swimming pool environments;
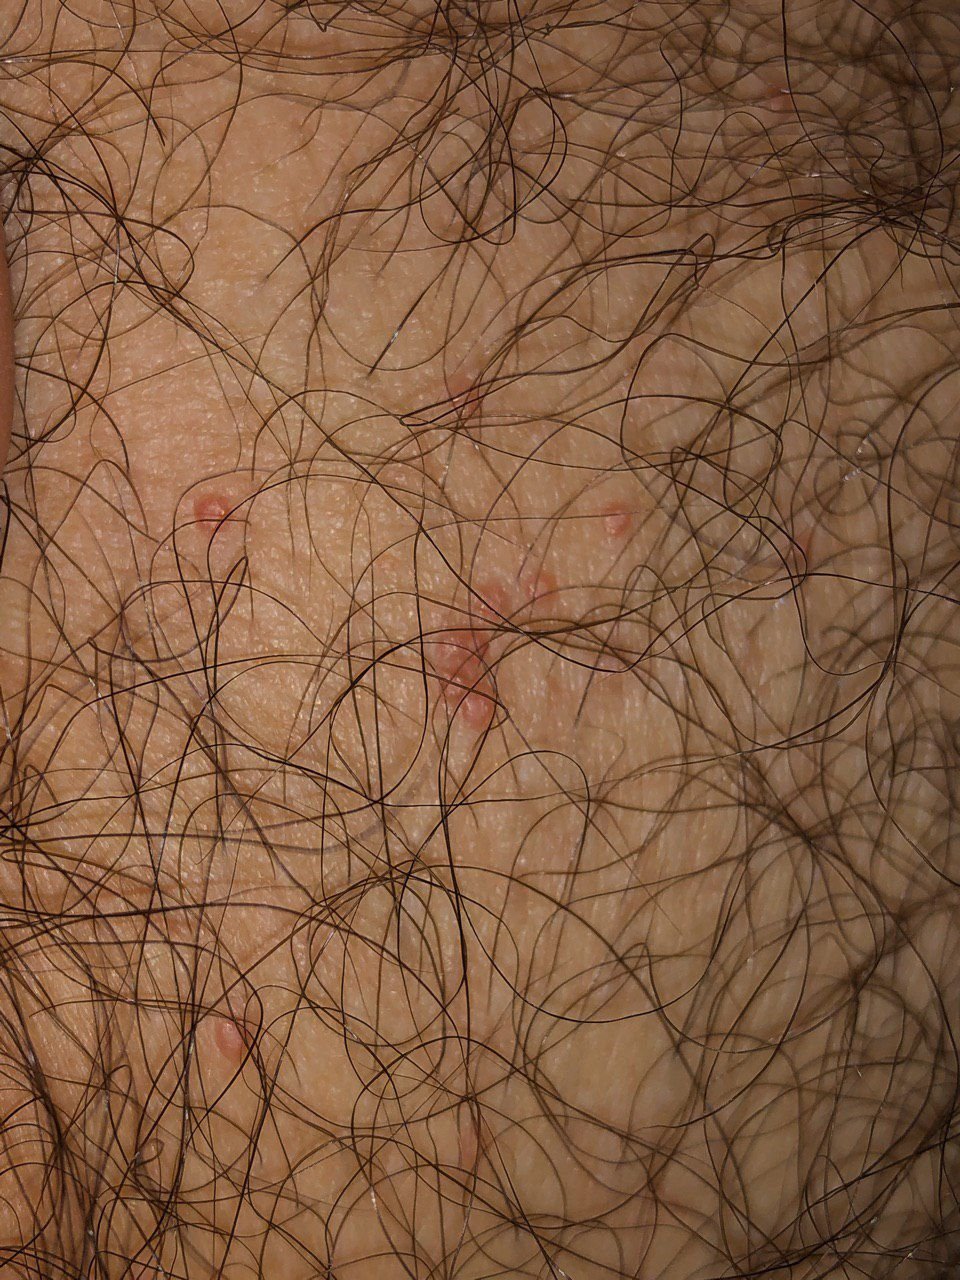
- Sexual transmission: In adults, MC may be transmitted during close physical or sexual contact, with lesions typically appearing in the genital or pubic regions;
- Autoinoculation: Scratching or rubbing lesions can spread the virus to other parts of the body.
Factors that increase the risk of molluscum contagiosum include:
- Weakened immune system: HIV/AIDS, cancer, or use of immunosuppressive medications;
- Living or sleeping in crowded conditions, which increases close skin contact;
- Chronic skin conditions: Atopic dermatitis and eczema may facilitate viral entry through compromised skin barriers;
- Frequent exposure to communal spaces (e.g., public pools, locker rooms, daycare centers).
In children, lesions are often found on the face and extremities, while in adults, genital and lower abdominal regions are more commonly affected due to the mode of transmission.
Diagnosis of Molluscum Contagiosum
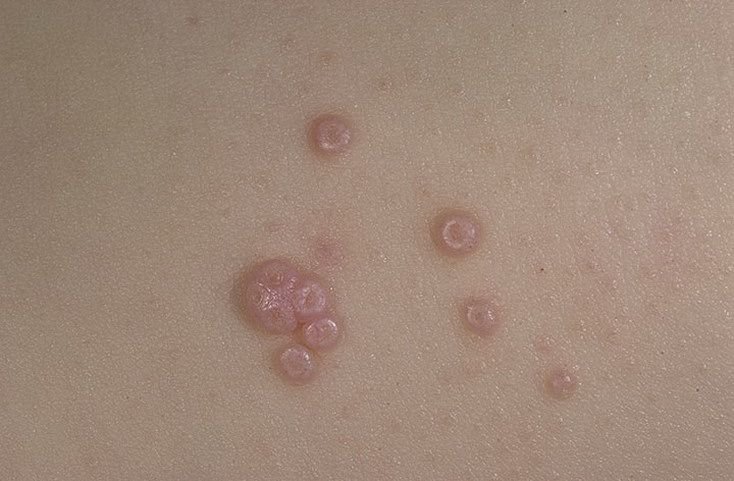
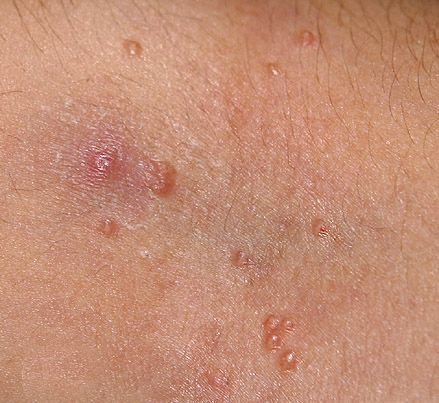
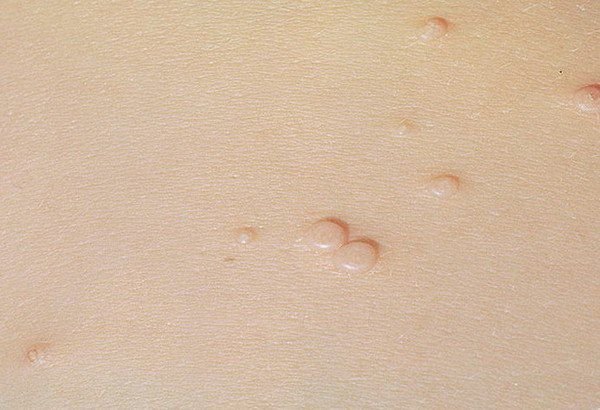
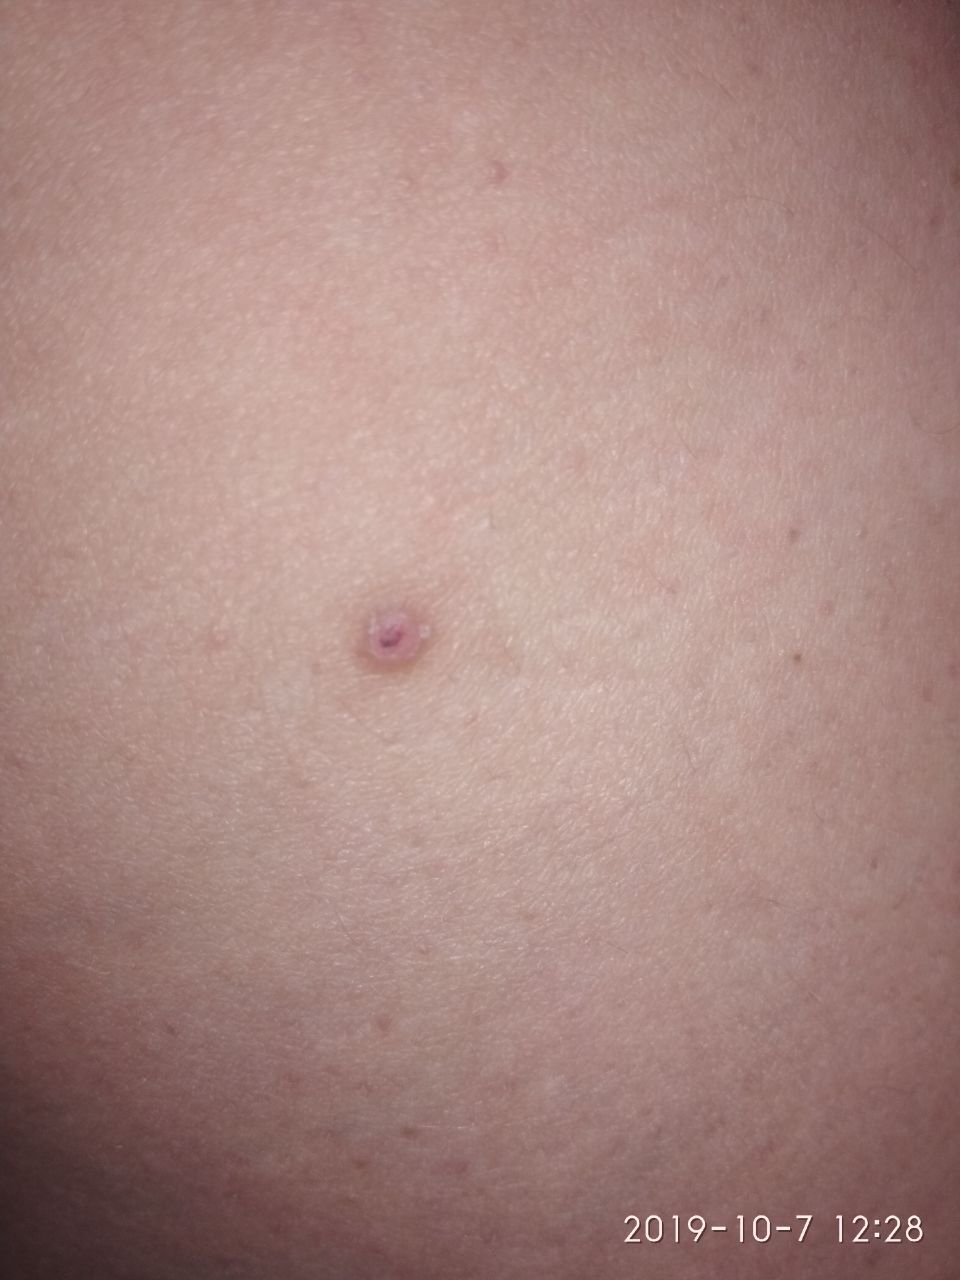
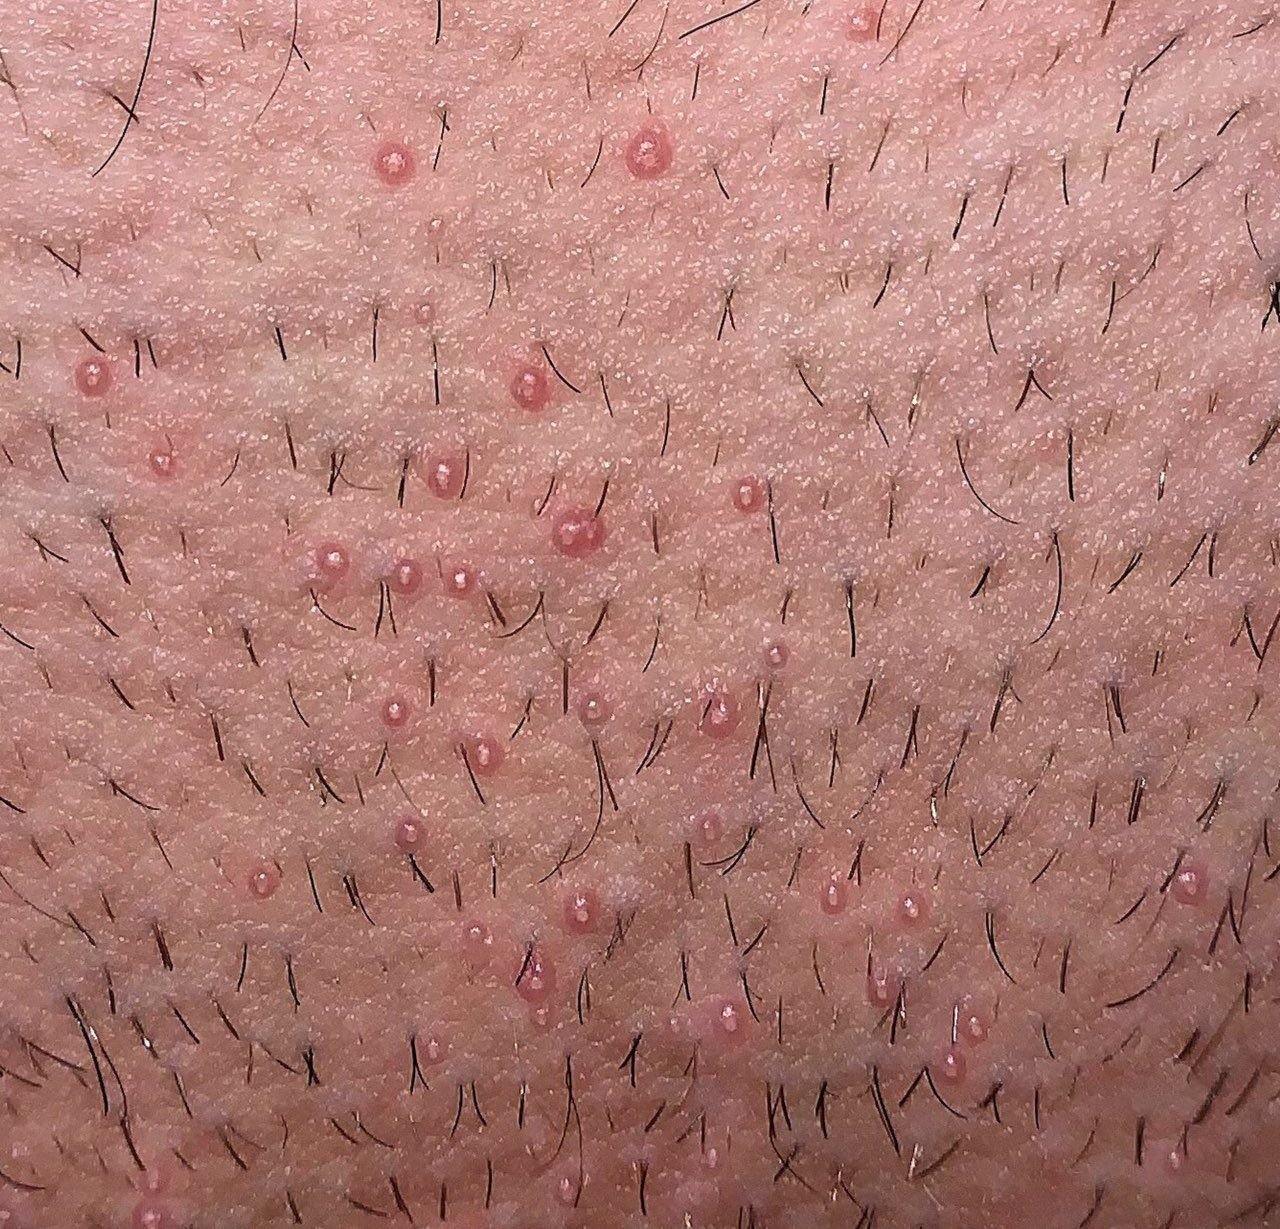
The diagnosis of MC is usually made clinically through physical examination. The lesions are visually distinctive—small, firm, pink or skin-colored papules with a characteristic central umbilication. Diagnosis is straightforward in most typical cases.
However, additional diagnostic steps may be required in atypical or immunocompromised patients, especially when lesions resemble other neoplasms. These include:
- Dermatoscopy: Visualizes round or oval-shaped whitish lesions with a central keratin core and cerebriform structures;
- Biopsy and histopathology: Reserved for atypical lesions or genuine diagnostic uncertainty — not for lesions that simply persist, since persistence is part of the natural course. Histology reveals large eosinophilic cytoplasmic inclusion bodies (molluscum bodies) within keratinocytes;
- PCR testing or viral culture: Rarely used due to the benign nature of the condition, but possible in research or severe cases.
Symptoms: Clinical Presentation of MC
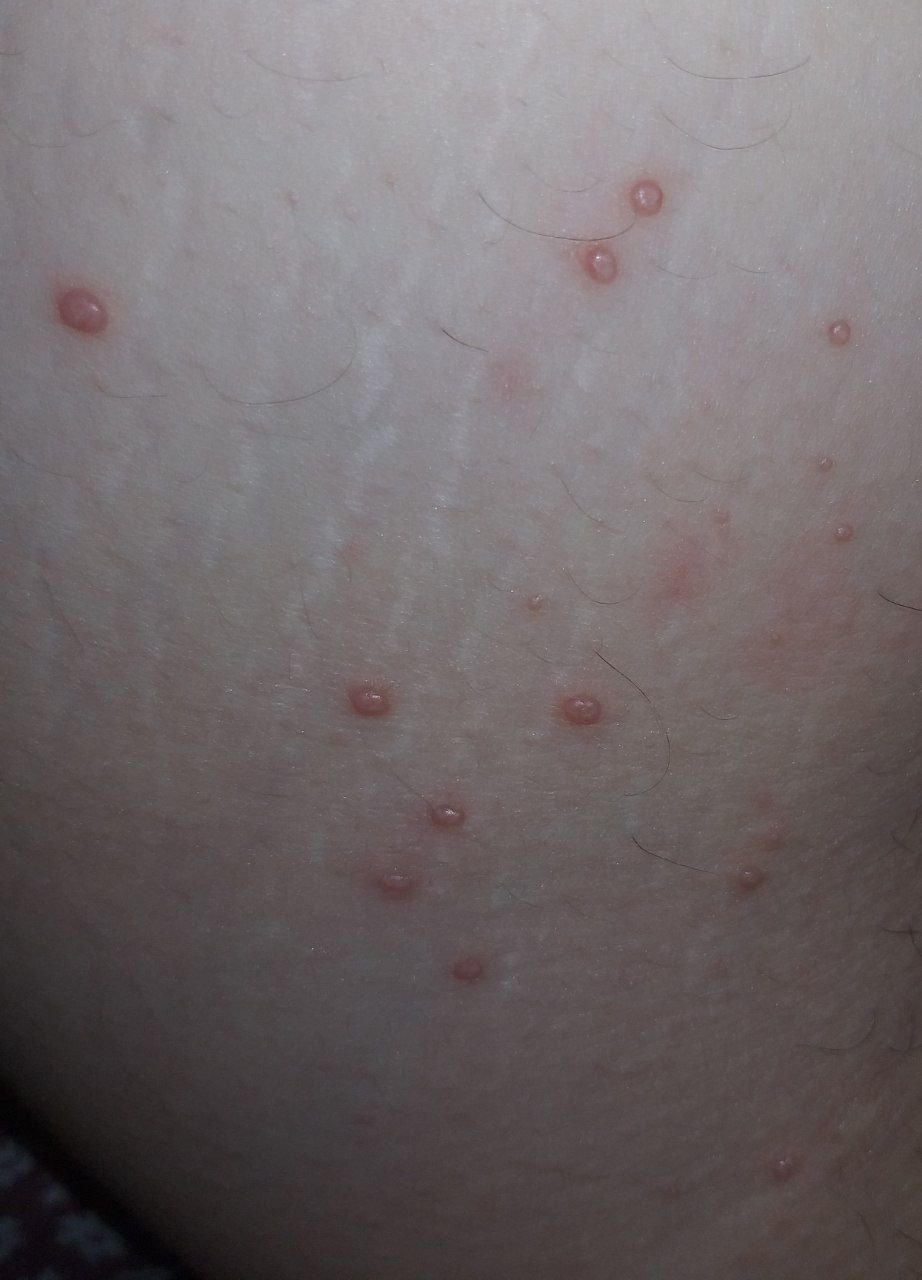
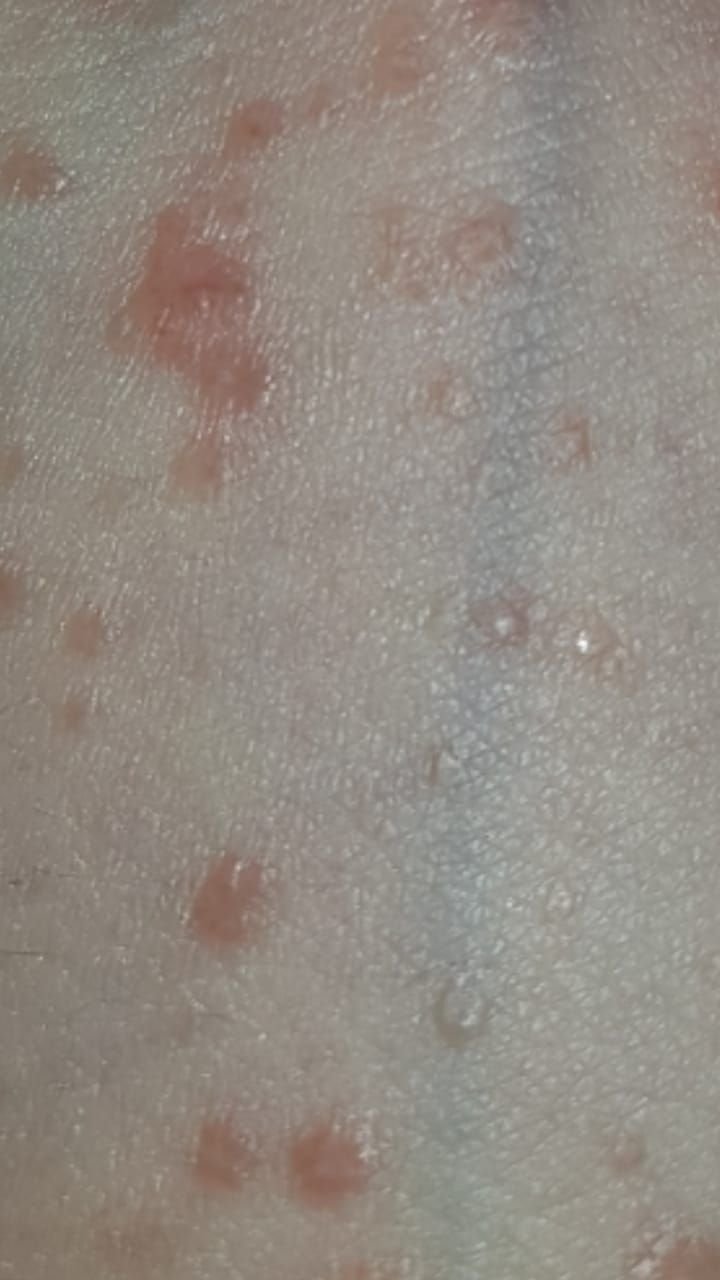
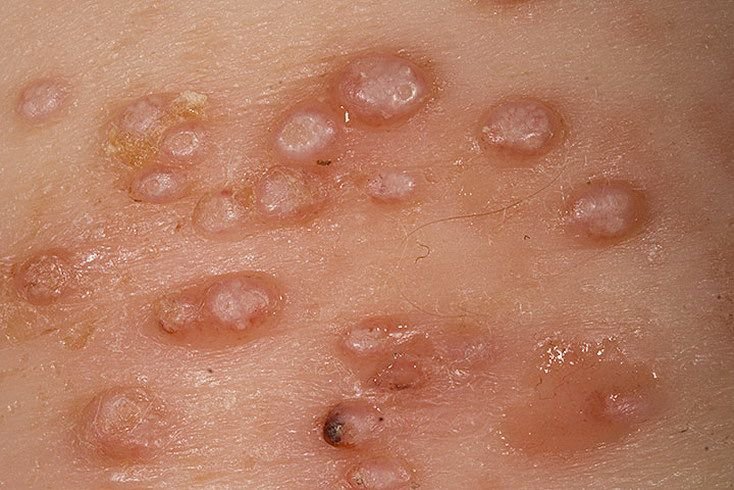
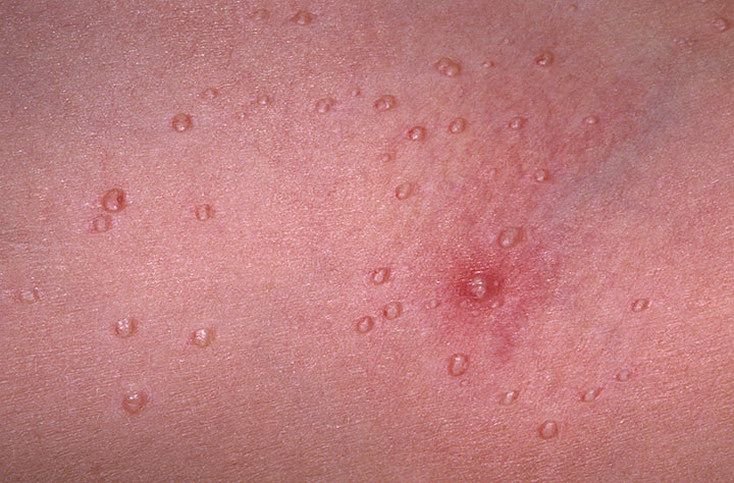
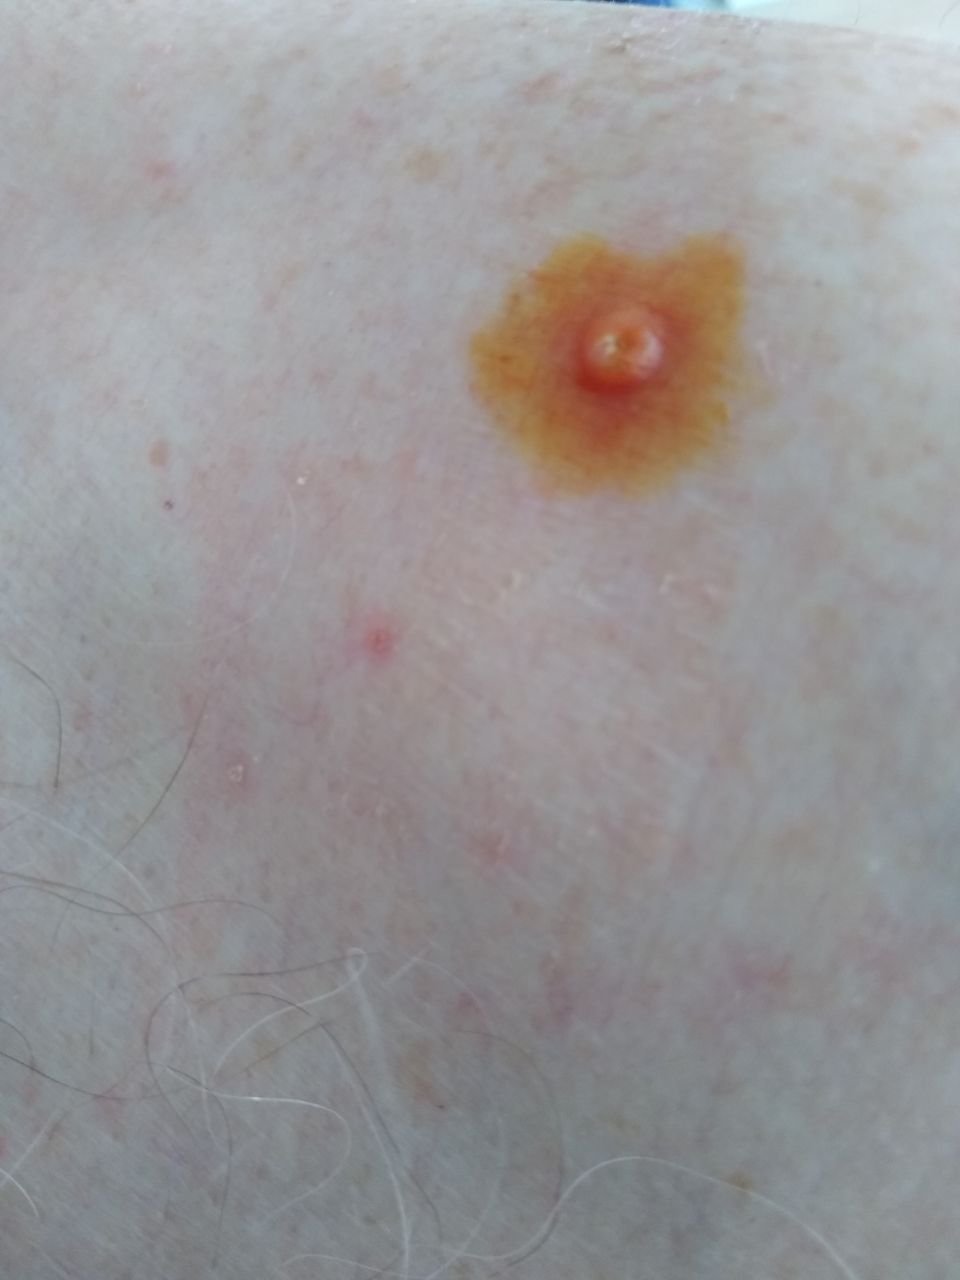
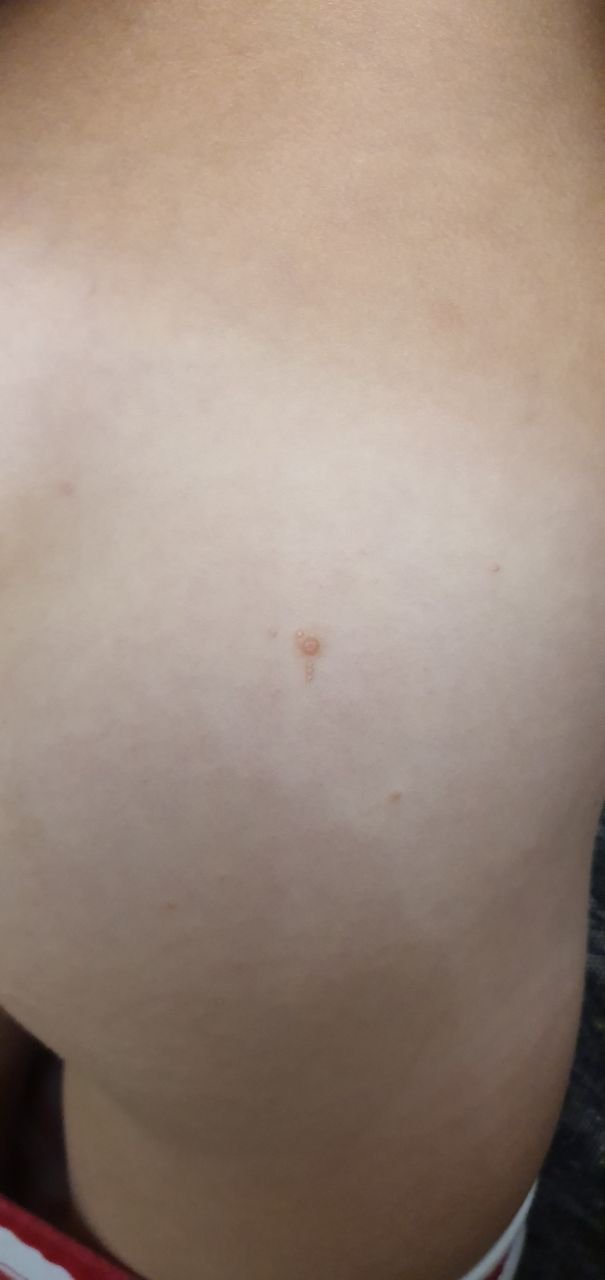
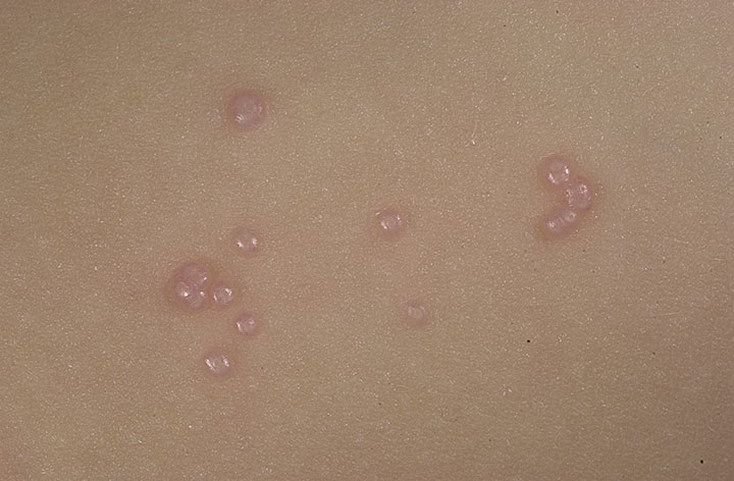
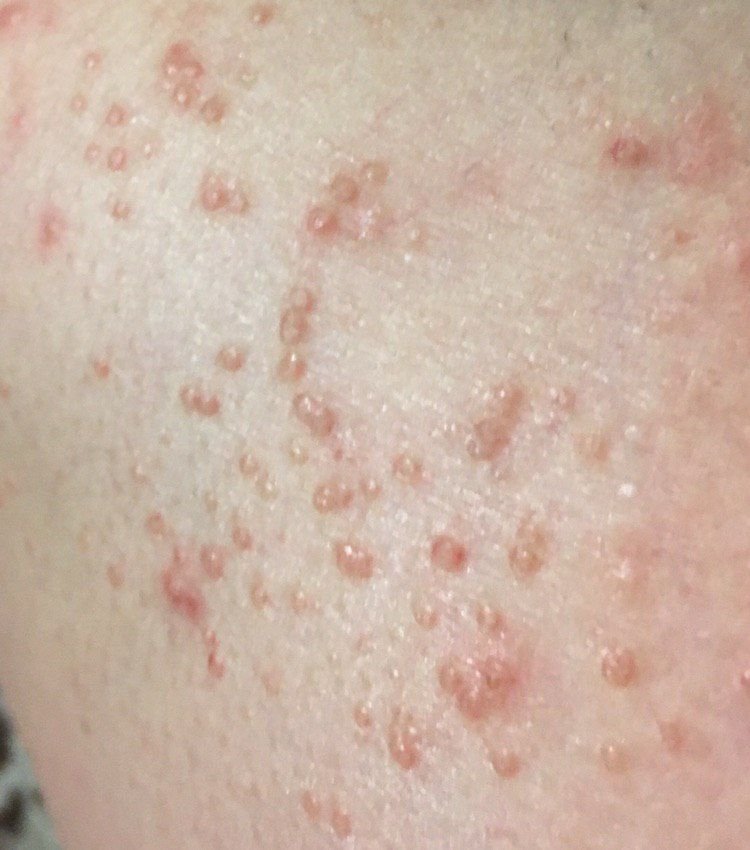
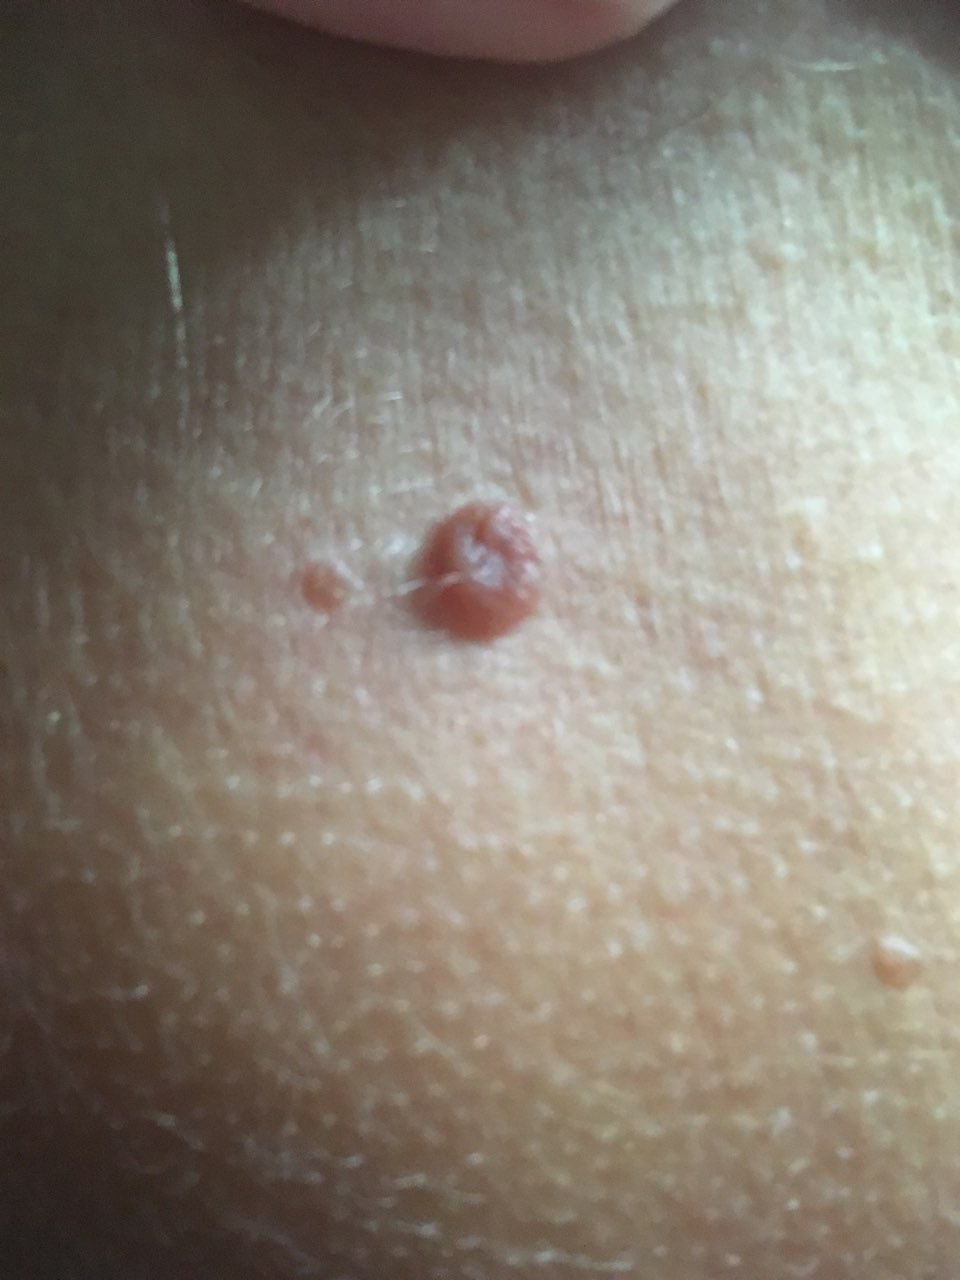
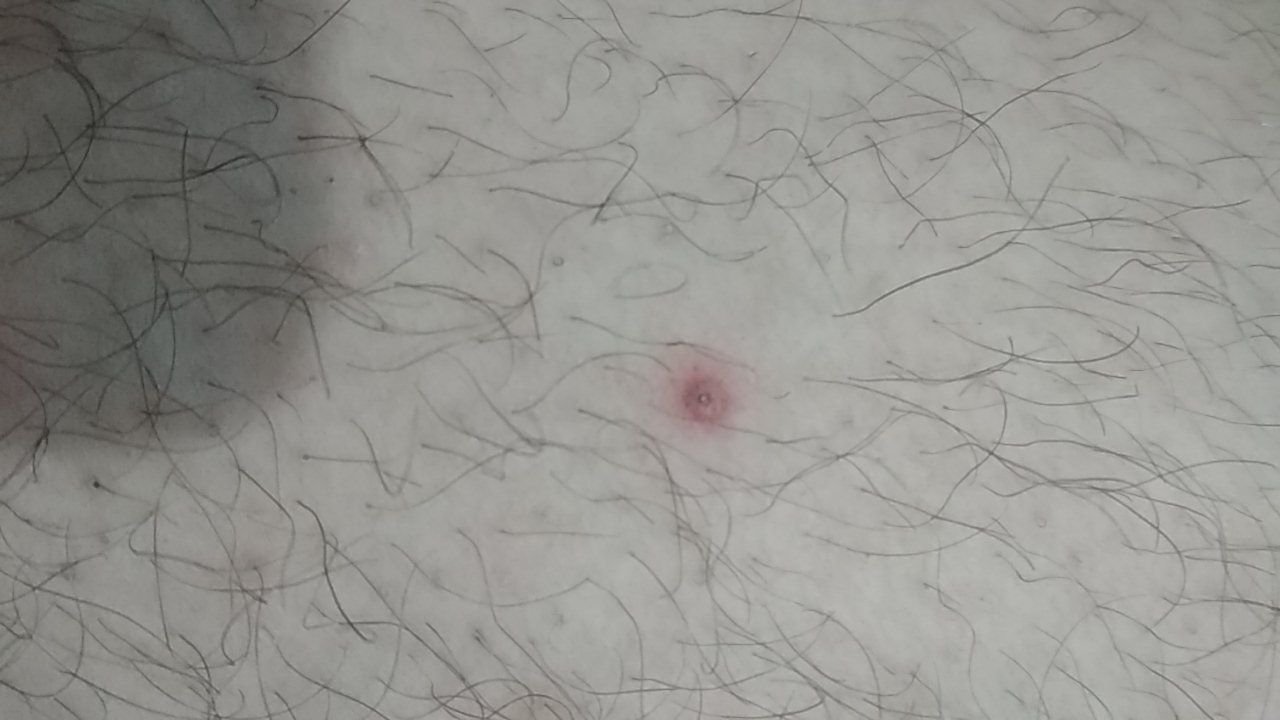
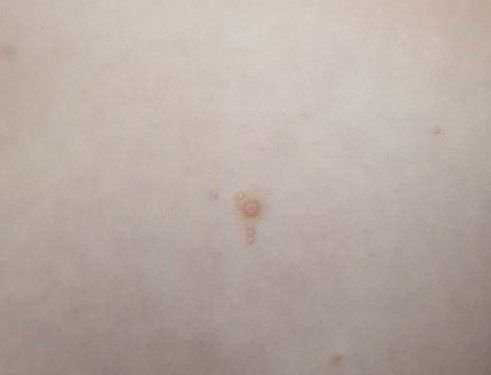
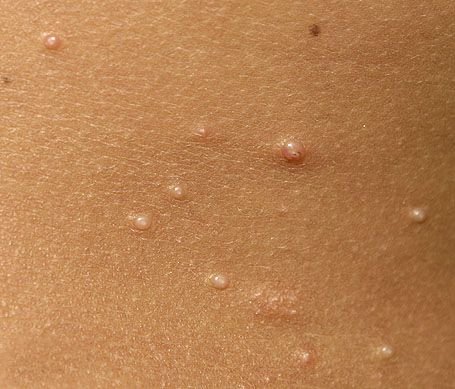
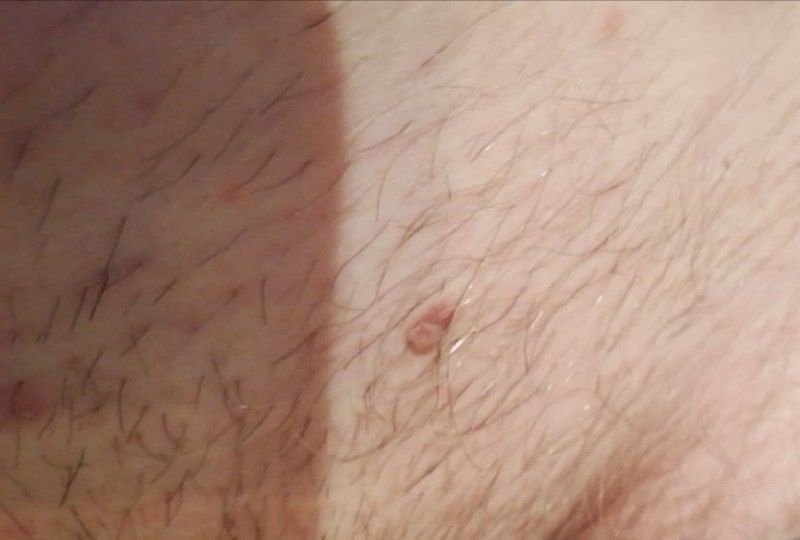
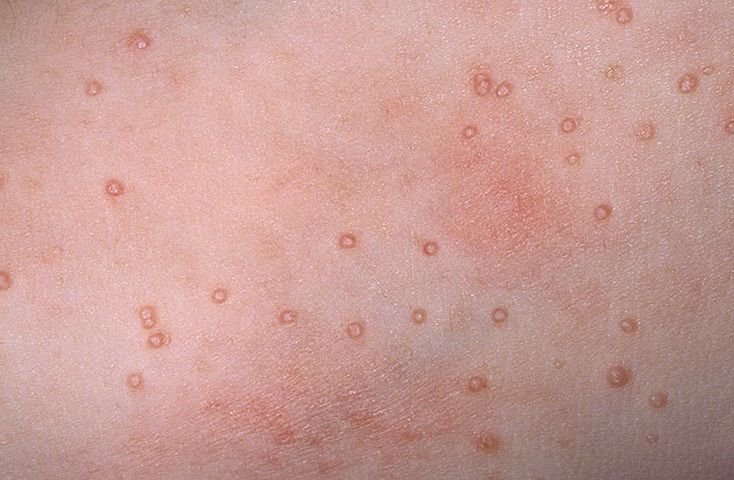
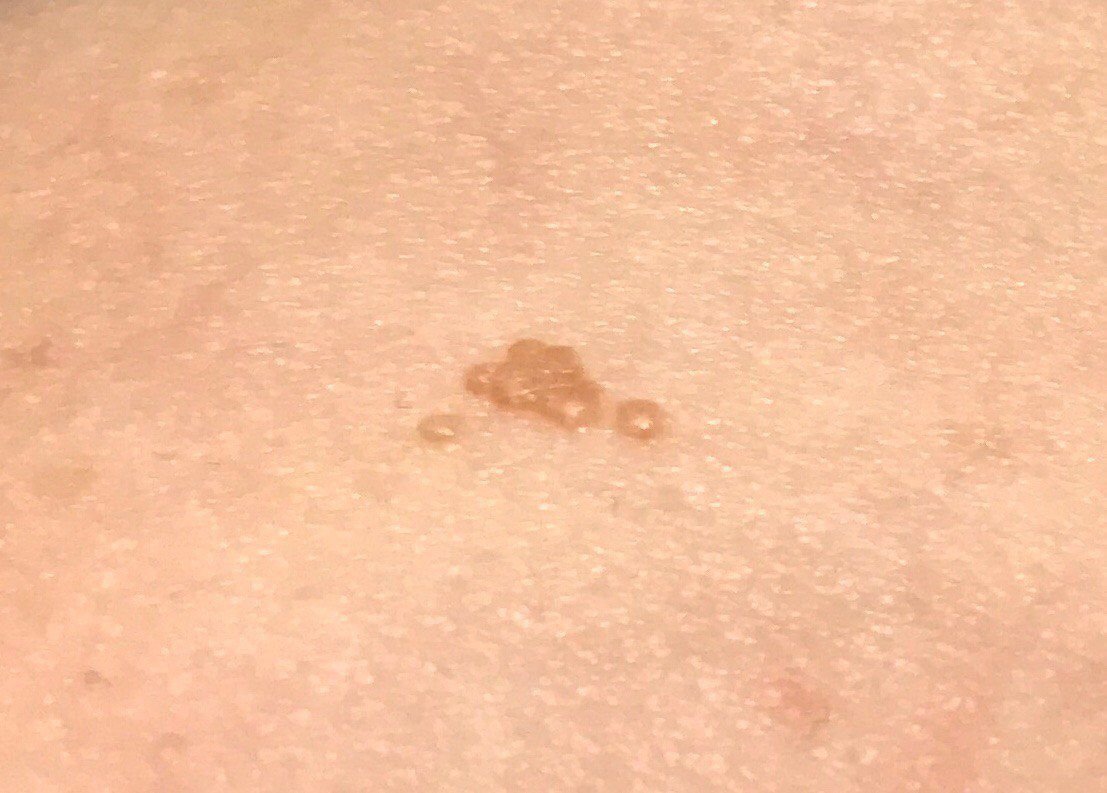
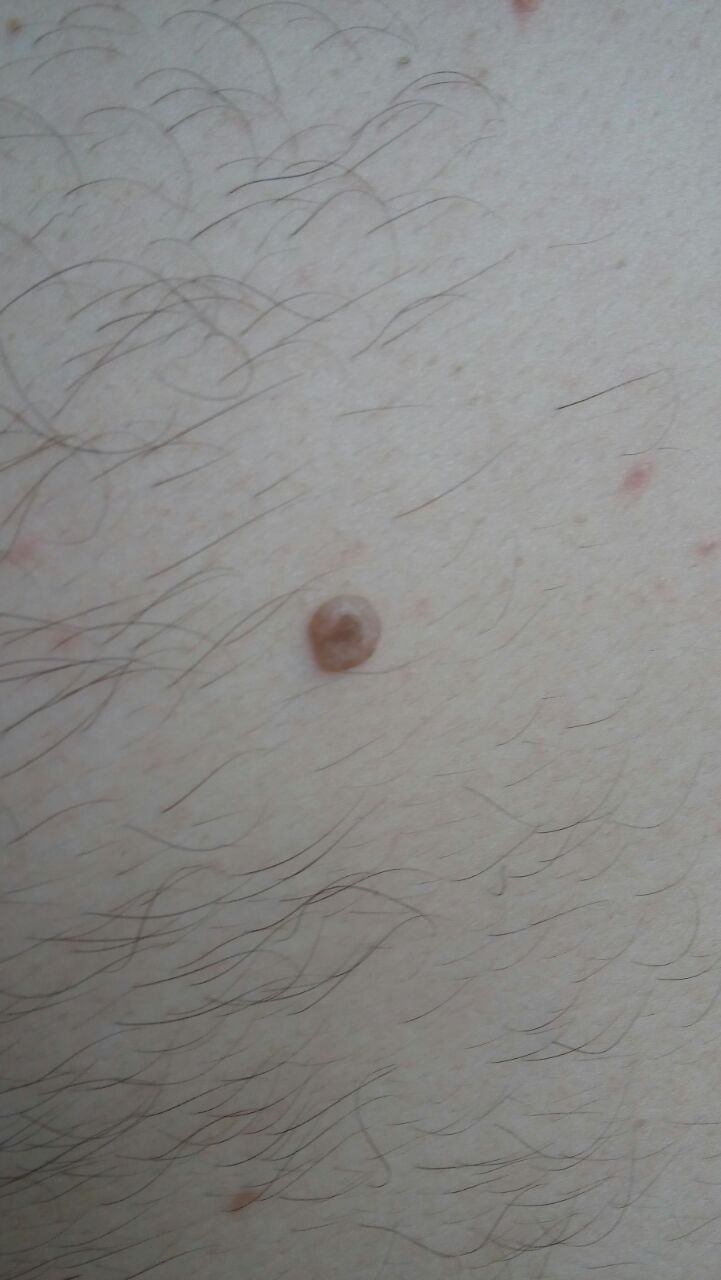
Molluscum contagiosum appears as one or more round, dome-shaped papules measuring 2–5 mm in diameter. Each lesion has a central depression or dimple and may contain a waxy, white core. When squeezed, the lesion may extrude a soft, cheese-like material composed of viral particles and cellular debris.
Key clinical features include:
- Color: Skin-toned, pink, or pearly white;
- Surface: Smooth and shiny, without scales or crusts;
- Umbilicated center: Often filled with a whitish keratin plug;
- Itching or irritation: May be present, especially during the healing phase or in individuals with sensitive skin;
- Location: In children—face, trunk, arms, and legs; in adults—lower abdomen, groin, genitals, and thighs;
- Number of lesions: Can range from a few to several dozen; confluent clusters may form if left untreated.
Lesions are typically asymptomatic but may cause psychosocial distress due to visibility and contagiousness. In some cases, secondary bacterial infection can occur following scratching or trauma.
Dermatoscopic Description of Molluscum Contagiosum
Dermatoscopy provides detailed visualization of molluscum contagiosum lesions, especially useful when the clinical presentation is ambiguous or the diagnosis needs confirmation.
Typical dermatoscopic findings include:
- Milky-white round or oval-shaped structures with well-defined edges;
- Central amorphous area representing keratin plug (polyglobular yellow-white core);
- Cerebriform or lobulated inner pattern within the lesion;
- Peripheral radial lines of dotted or sinuous nature (crown-like pattern) surrounding the center.
These features distinguish MC from viral warts, nevi, and skin tumors and help guide treatment decisions in unclear or atypical presentations.
Differential Diagnosis
Several benign and malignant skin lesions may mimic molluscum contagiosum. It is important to rule out the following conditions:
- Viral warts (verrucae): Typically lack central umbilication and have a rougher, keratotic surface;
- Papillomatous nevus: More pigmented and textured compared to MC;
- Nevus sebaceous: Usually presents in infancy or early childhood, commonly on the scalp;
- Dermatofibroma: Firm, pigmented lesions with dimple sign and without central core;
- Keratoacanthoma: Rapidly growing dome-shaped nodule, often with a central keratin plug, seen in older individuals;
- Basal cell carcinoma (nodular): Pearly nodule with telangiectasia and possible ulceration;
- Amelanotic melanoma: Non-pigmented, irregular nodules with rapid growth, requiring histopathological confirmation.
Risks and Clinical Relevance
From an oncological perspective, molluscum contagiosum is non-malignant and does not increase the risk of cancer. The virus remains confined to the superficial epidermis and does not invade internal organs.
However, certain clinical concerns include:
- Contagiousness: Easy transmission to others through skin contact or contaminated surfaces;
- Cosmetic burden: Especially when lesions are numerous or located on the face or genitals;
- Risk of autoinoculation: Spreading to other body parts via scratching or trauma;
- Secondary bacterial infection: Particularly in excoriated or inflamed lesions;
- Immunodeficiency association: Extensive or persistent MC may signal underlying immune suppression.
Rapid increase in size, change in consistency, or development of subjective symptoms such as pain may require biopsy to rule out malignancy or other dermatoses.
Tactics: When and Why to Seek Medical Help
Because molluscum clears on its own, there is no need to treat every case. Clinical diagnosis is usually sufficient, and watchful waiting is a reasonable plan for uncomplicated lesions in healthy children. Treatment is considered individually — for genital lesions, extensive or widespread disease, complications, or where the lesions cause significant distress. Patients should seek evaluation from a dermatologist when:
- Lesions are increasing in number or size;
- There is trauma, bleeding, or signs of infection in or around lesions;
- Lesions are located in sensitive areas (face, genitals, eyelids);
- The individual is immunocompromised or has chronic skin conditions.
Where lesions are left to resolve on their own, no special tracking is needed: routine photographic documentation and skin mapping are not required for uncomplicated molluscum. A lesion that changes in an unexpected way is a reason to be seen again.
Treatment of Molluscum Contagiosum
Where treatment is chosen, the method depends on the patient’s age, immune status, the site and number of lesions, what is available locally, and the patient’s preference. No single approach is clearly superior, and all carry some risk of discomfort or pigment change. Options include:
- Cantharidin: Applied in the clinic to blister the lesion; widely used in children because it is not painful at the time of application;
- Cryotherapy: Application of liquid nitrogen to freeze and destroy lesions, usually over several visits;
- Curettage: Physical removal of the lesion core, often with topical anaesthetic;
- Potassium hydroxide solution: A topical option that can be applied at home under medical direction;
- Laser or electrocoagulation: Selected cases, generally where other methods have failed or lesions are extensive.
Imiquimod is not recommended for molluscum contagiosum: controlled trials in children did not show it to be of benefit, despite its earlier widespread use.
In rare cases, surgical excision and histological analysis are required when lesions are atypical or present a diagnostic dilemma.
Self-removal is contraindicated due to the risk of autoinoculation, scarring, bleeding, and secondary infections. Clinical resolution is usually defined as clearance of all visible lesions, but recurrence and autoinoculation can occur; follow-up is recommended.
Prevention of Molluscum Contagiosum
Preventive measures focus on minimizing skin trauma, maintaining hygiene, and protecting against viral spread in communal environments.
Key strategies include:
- Avoiding direct skin contact with another person’s lesions;
- Not scratching, picking or squeezing lesions, which is the main way the infection spreads to new areas of one’s own skin;
- Hand hygiene, particularly after touching or treating a lesion;
- Covering lesions with clothing or a dressing where this is practical, especially for contact sports or swimming;
- Not sharing towels, flannels, razors or clothing while lesions are present;
- Barrier protection during intimate contact when lesions are present in the genital area, bearing in mind that condoms may not give full protection, since lesions on skin they do not cover can still transmit the infection.
With early diagnosis, appropriate removal techniques, and patient education, molluscum contagiosum can be effectively managed and the risk of spread or recurrence significantly reduced.

Copyright concern about an image on this page? Write to mail@skinai.pro. Images may not be reused without permission unless an open licence is stated on this page.

Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)