
Wart Plane (ICD-10: B07) ⚠️
Plane Wart (Flat Wart, Verruca Plana): Viral Skin Lesion with Benign Course
Overview
Plane warts, also known as flat warts or verruca plana, are benign epithelial tumors of viral origin caused by the human papillomavirus (HPV). These lesions are most frequently seen in children, adolescents, and young adults, and are characterized by their small size, flattened surface, multiplicity, and ability to resolve spontaneously in some cases—especially in younger individuals.
Despite being considered harmless, plane warts can cause significant cosmetic discomfort due to their location, which often includes exposed skin areas such as the face and hands. Moreover, warts can be resistant to treatment and may increase in number, leading to a need for medical intervention.
Predisposing Factors and Transmission
The causative agent of plane warts is HPV, usually of low oncogenic risk (e.g., types 3, 10, 28). However, while HPV infects a large portion of the population, not everyone develops visible lesions. This suggests that the manifestation of warts depends on individual susceptibility and immune status.
Factors that increase the risk of developing flat warts include:
- Exposure to HPV through direct skin contact with someone who has warts, or through shared items and surfaces;
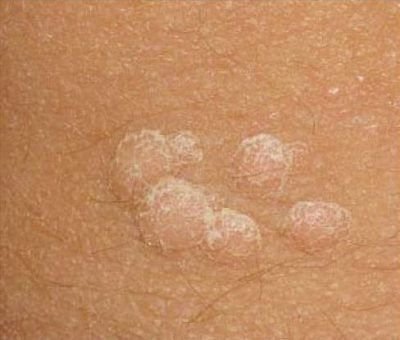
- Skin trauma: Micro-injuries let the virus in, which is why flat warts so often appear in a line along a scratch or across an area that has been shaved — the Koebner phenomenon;
- Autoinoculation: Scratching or shaving over existing lesions spreads them to neighbouring skin, and is the usual reason they multiply;
- Immunosuppression: HIV infection, cancer treatment, immunosuppressive drugs or organ transplantation make flat warts more numerous and much harder to clear;
- Pediatric population: Due to high rates of close physical interaction.
Transmission occurs through direct contact with infected skin or contaminated objects, and the virus can spread to adjacent areas through autoinoculation.
Diagnosis of Flat Warts
The diagnosis of plane warts is mainly clinical, relying on visual inspection of the skin. These lesions have a characteristic appearance, allowing experienced dermatologists to make a diagnosis during a physical exam.
Additional tools may be used in complex or atypical cases:
- Dermatoscopy: Helps visualize subtle vascular and keratinization patterns typical of plane warts;
- HPV typing: Not required for diagnosis or treatment of plane warts, including recurrent ones;
- Skin biopsy: Performed when malignancy is suspected or the lesion does not respond to standard therapy. Histological examination reveals acanthosis, hyperkeratosis, and koilocytosis.
Symptoms and Clinical Features
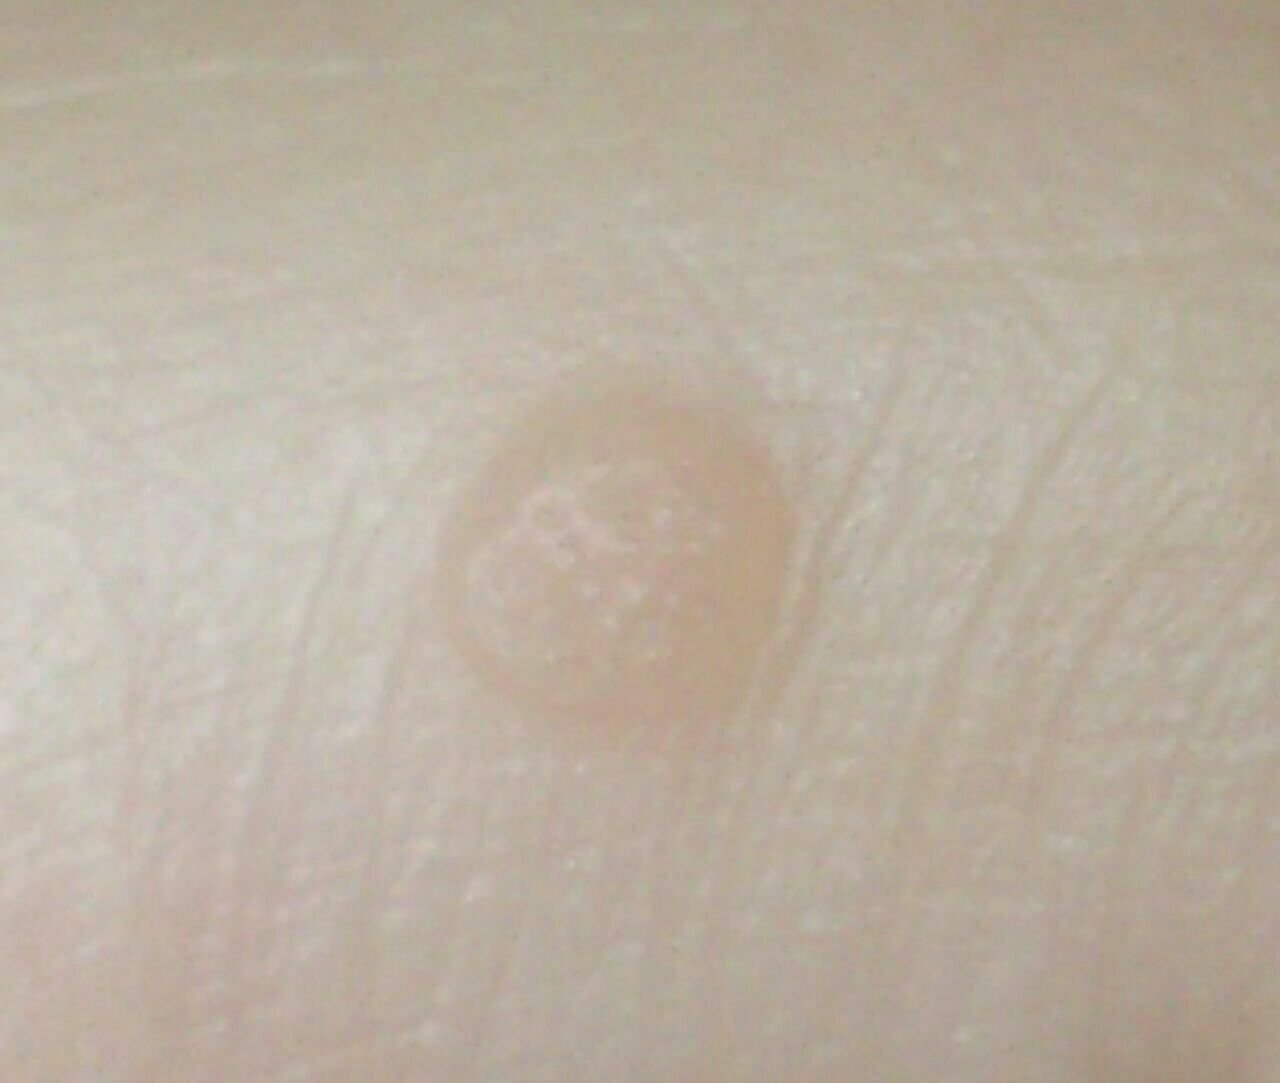
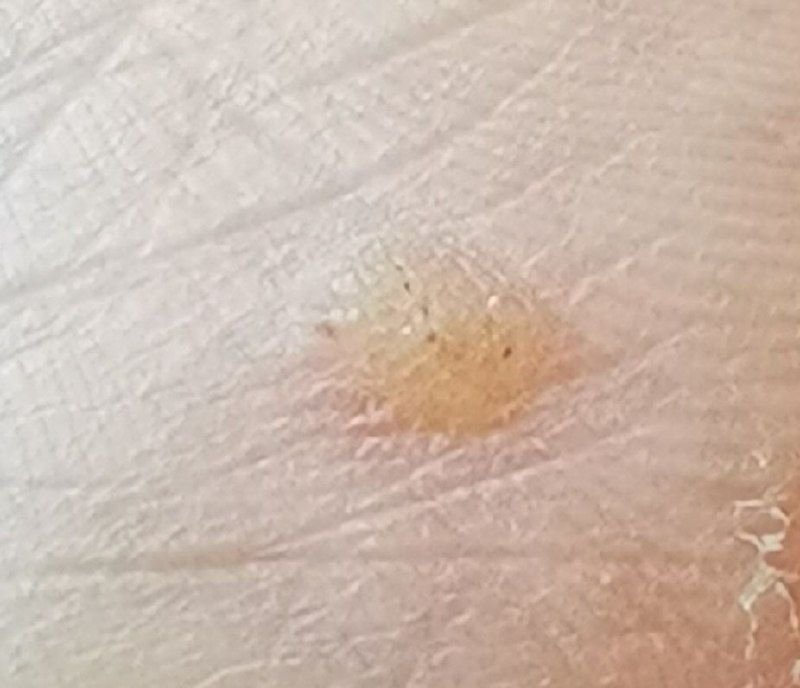
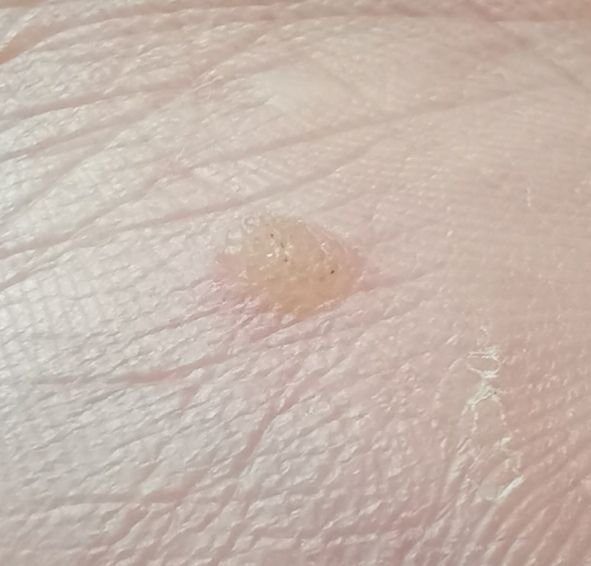
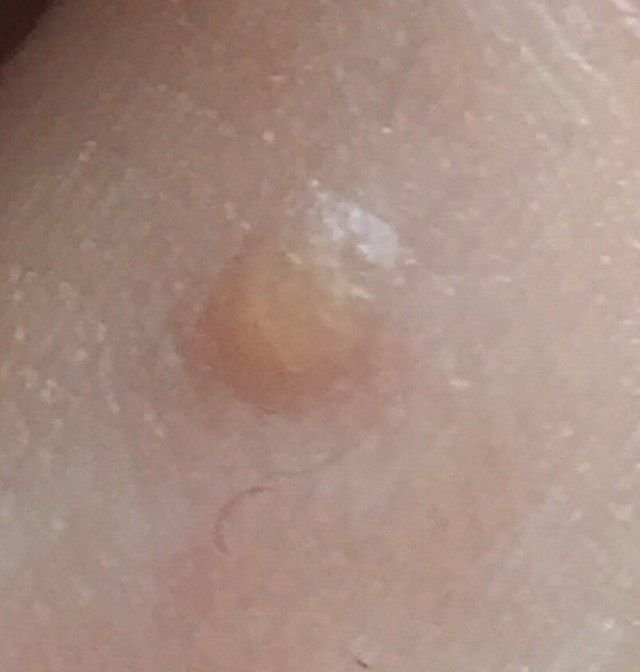
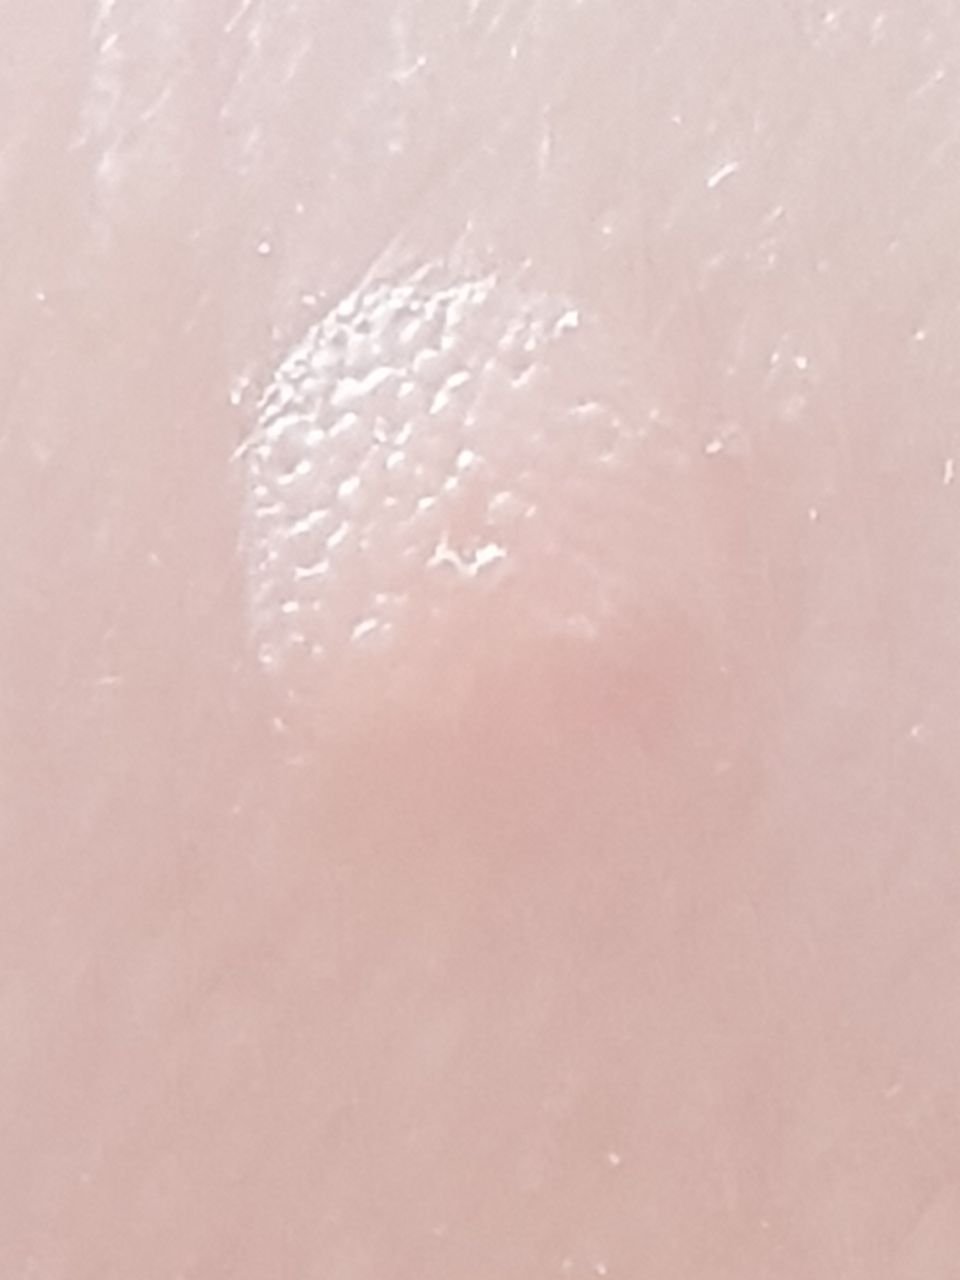
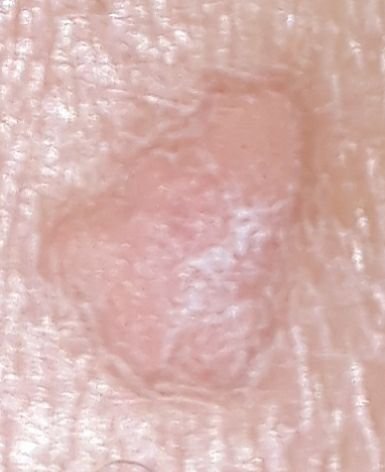
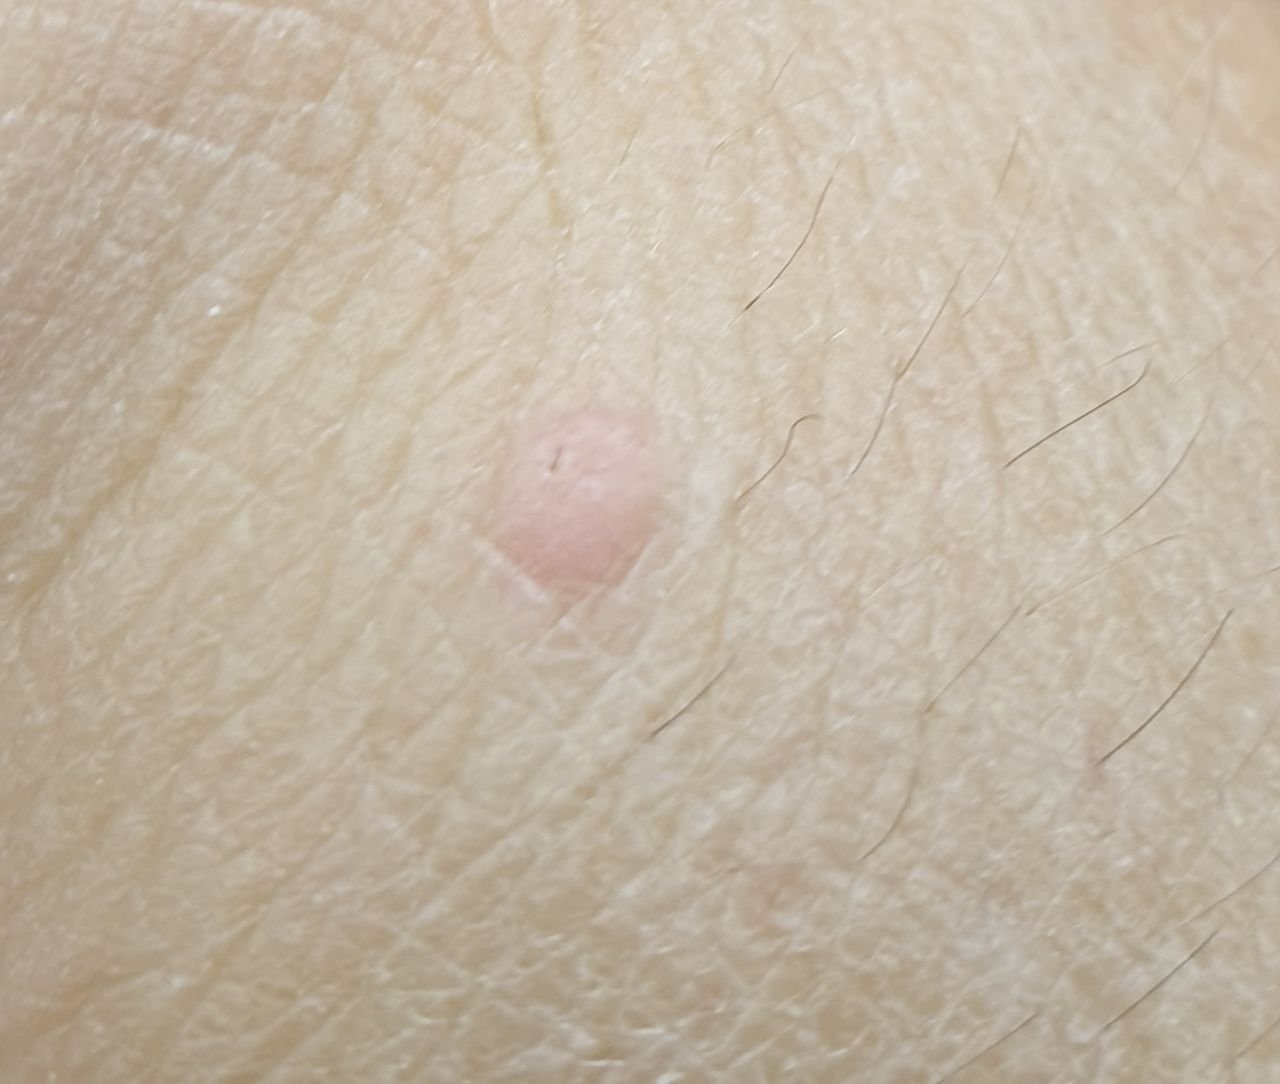
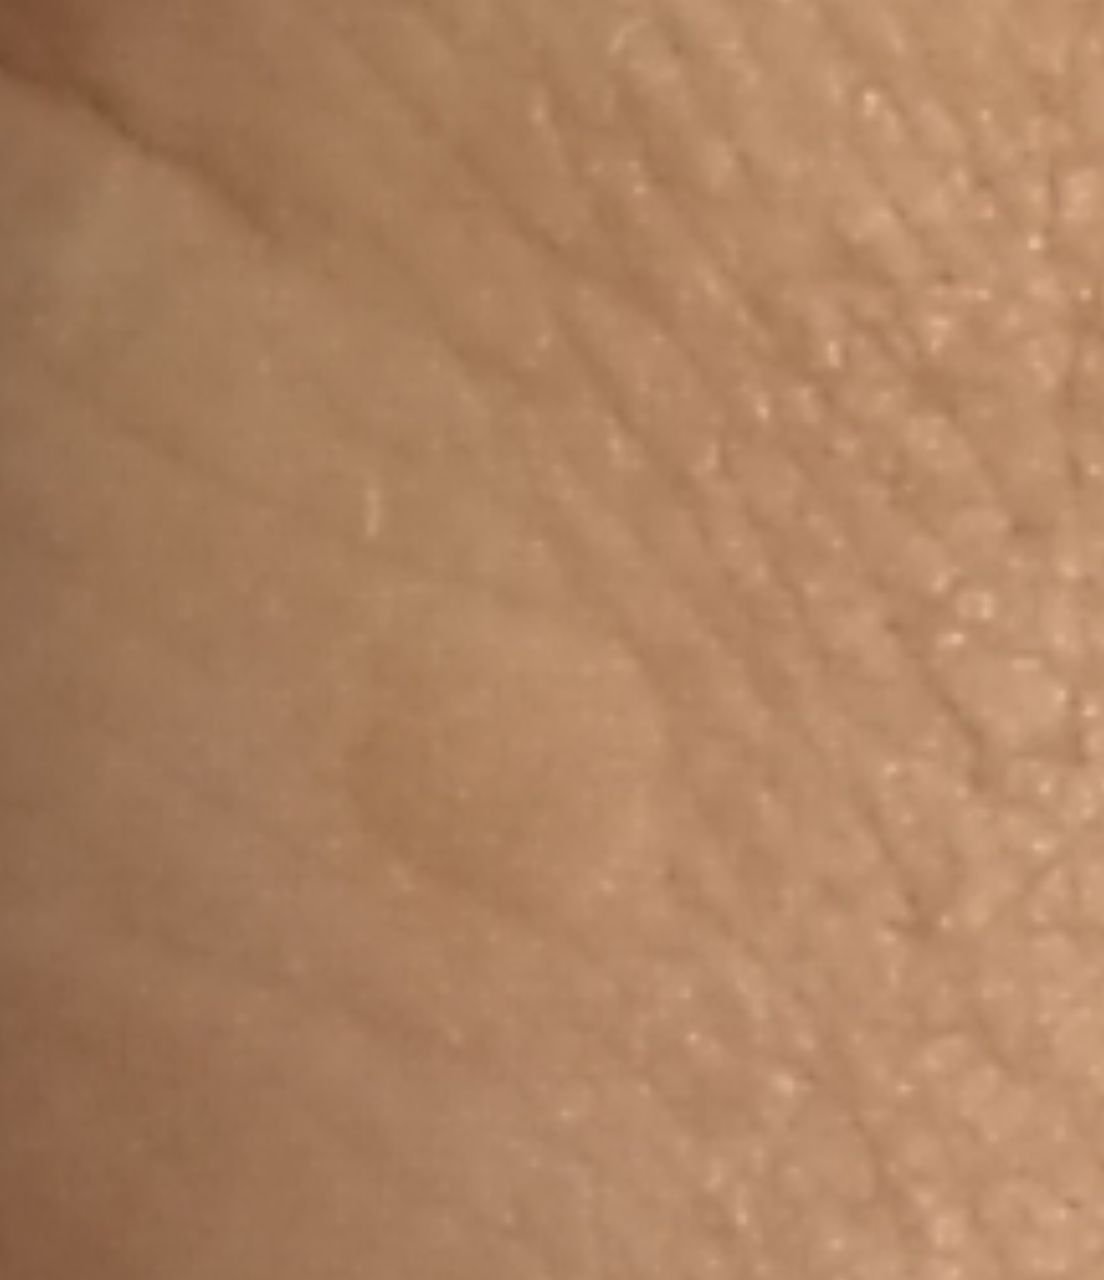
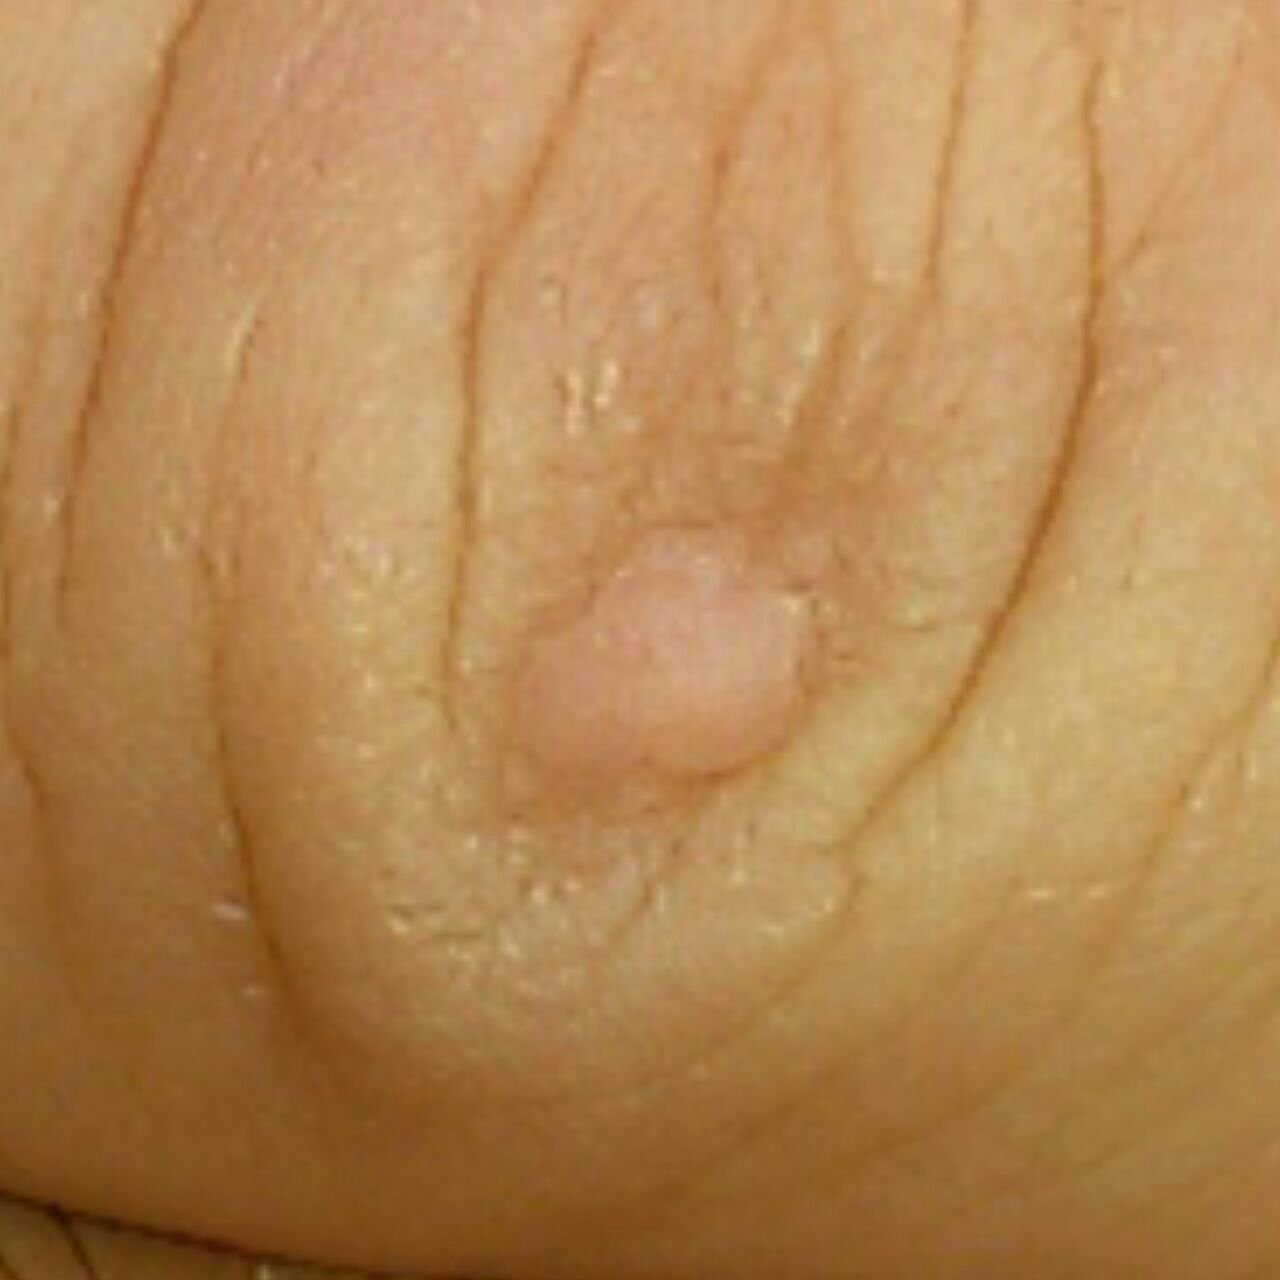
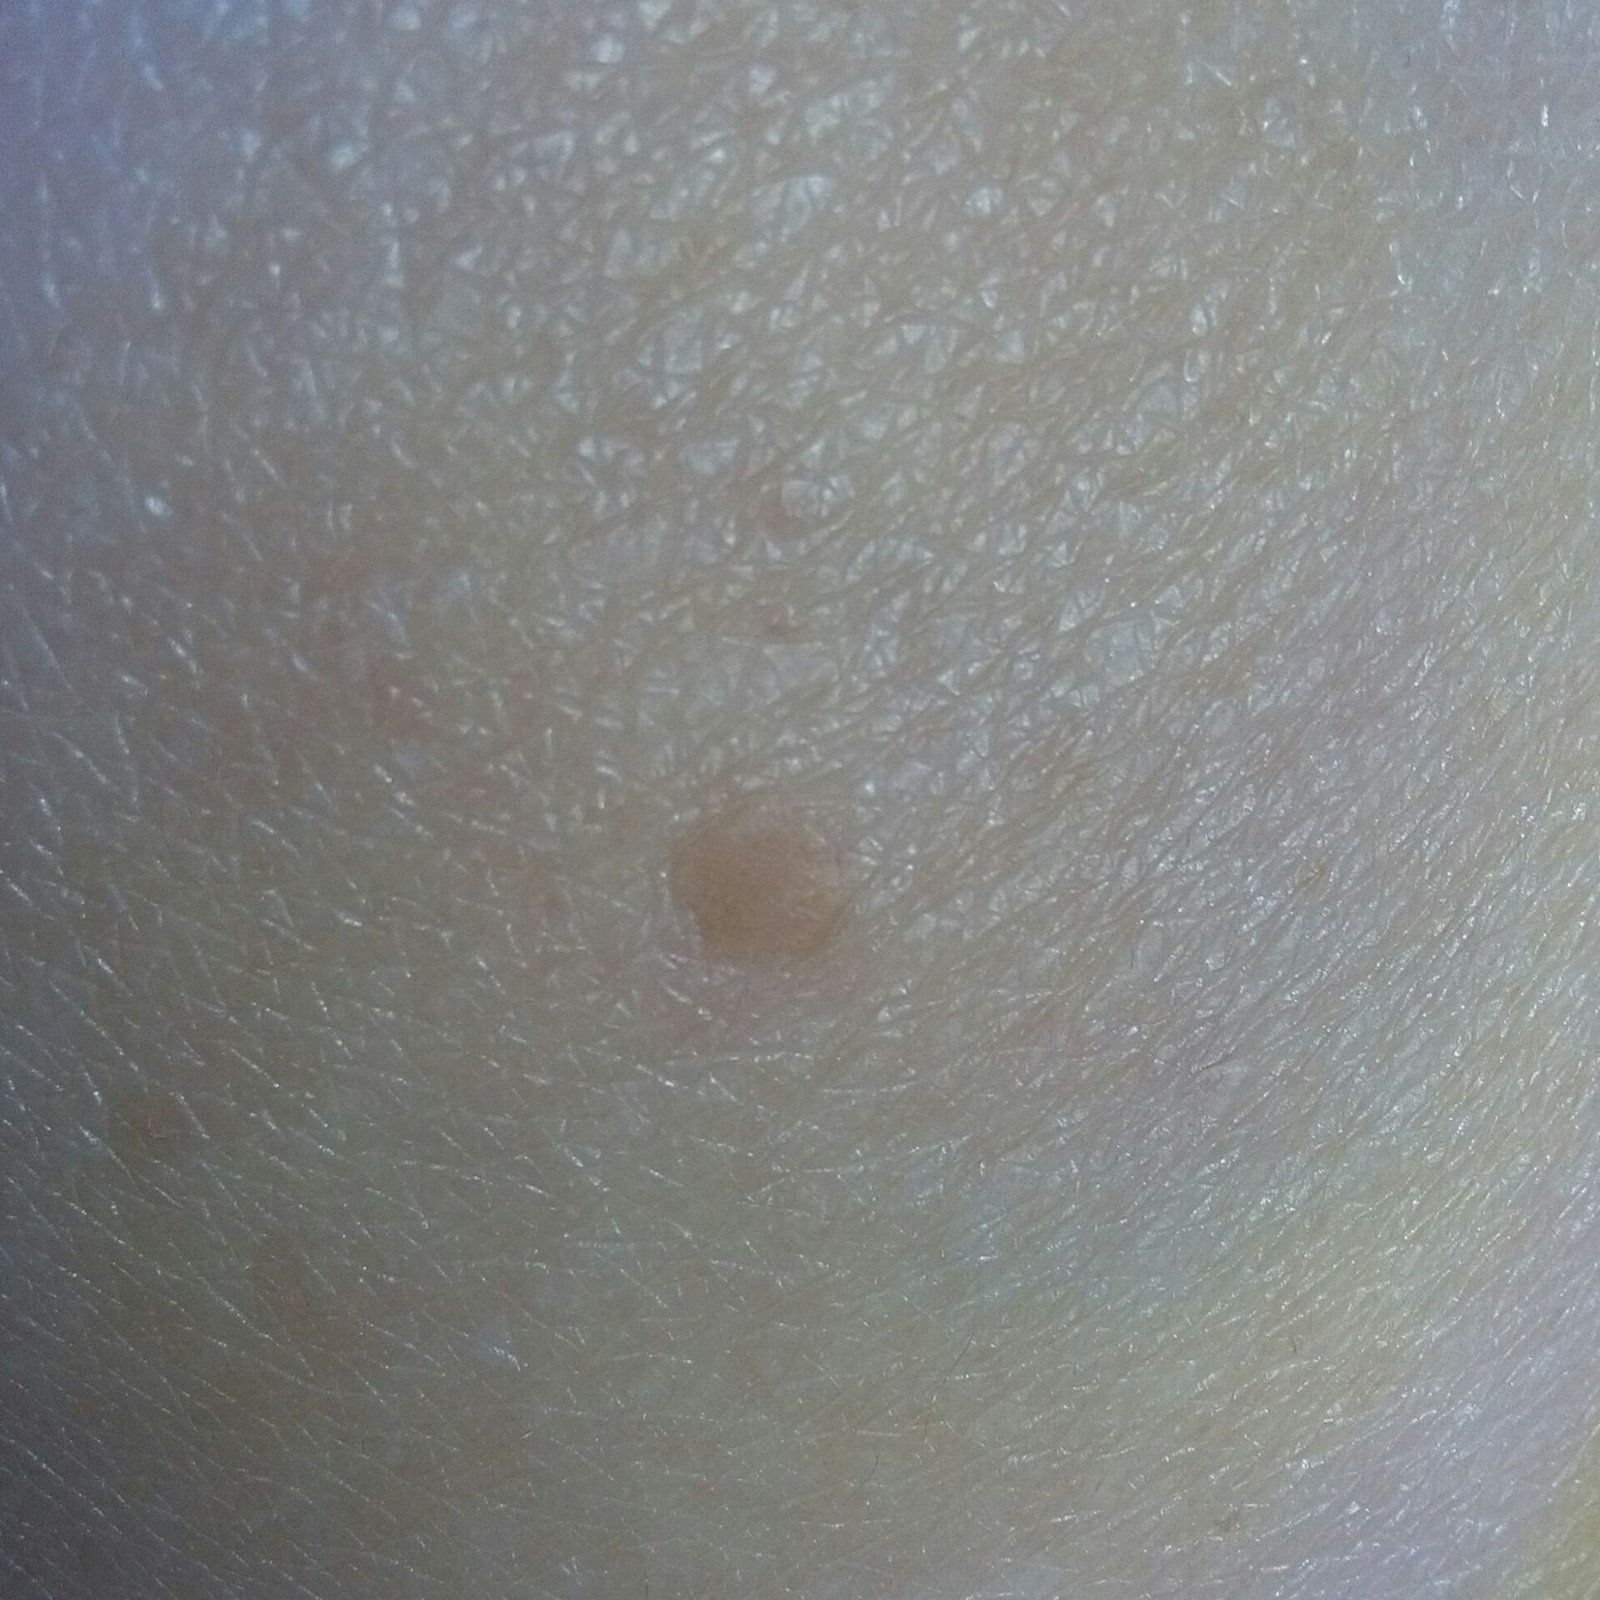
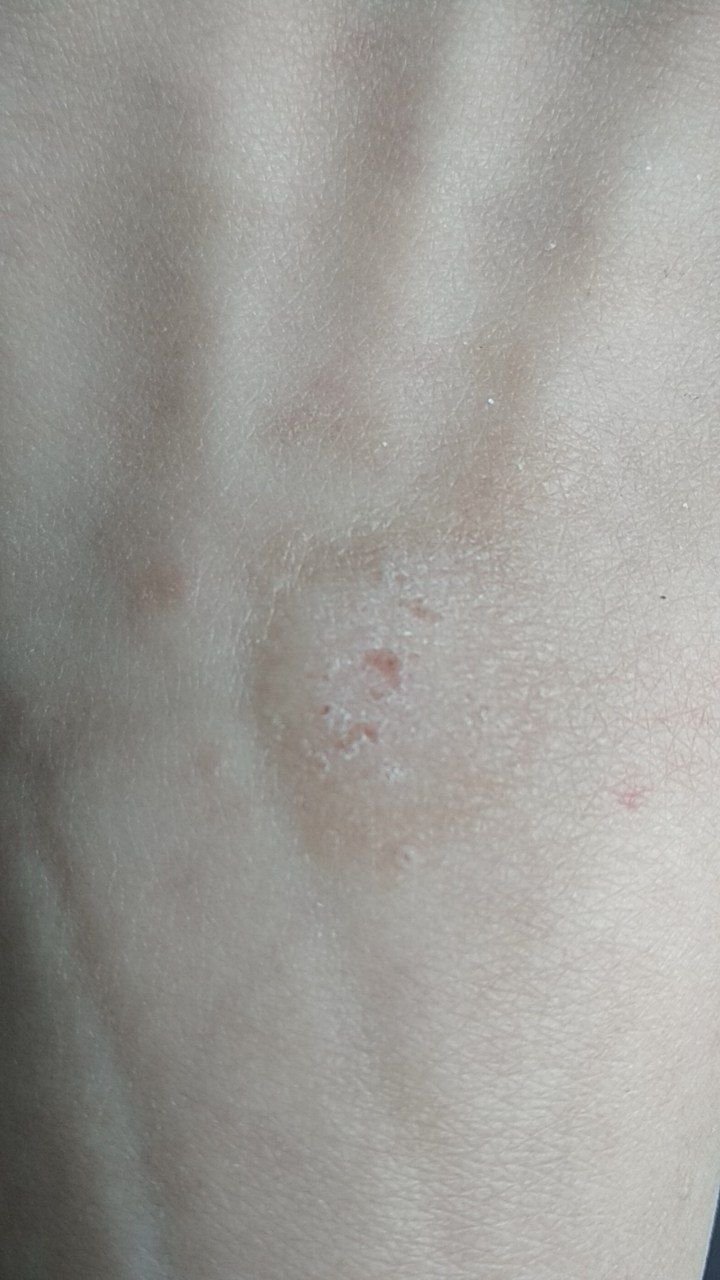
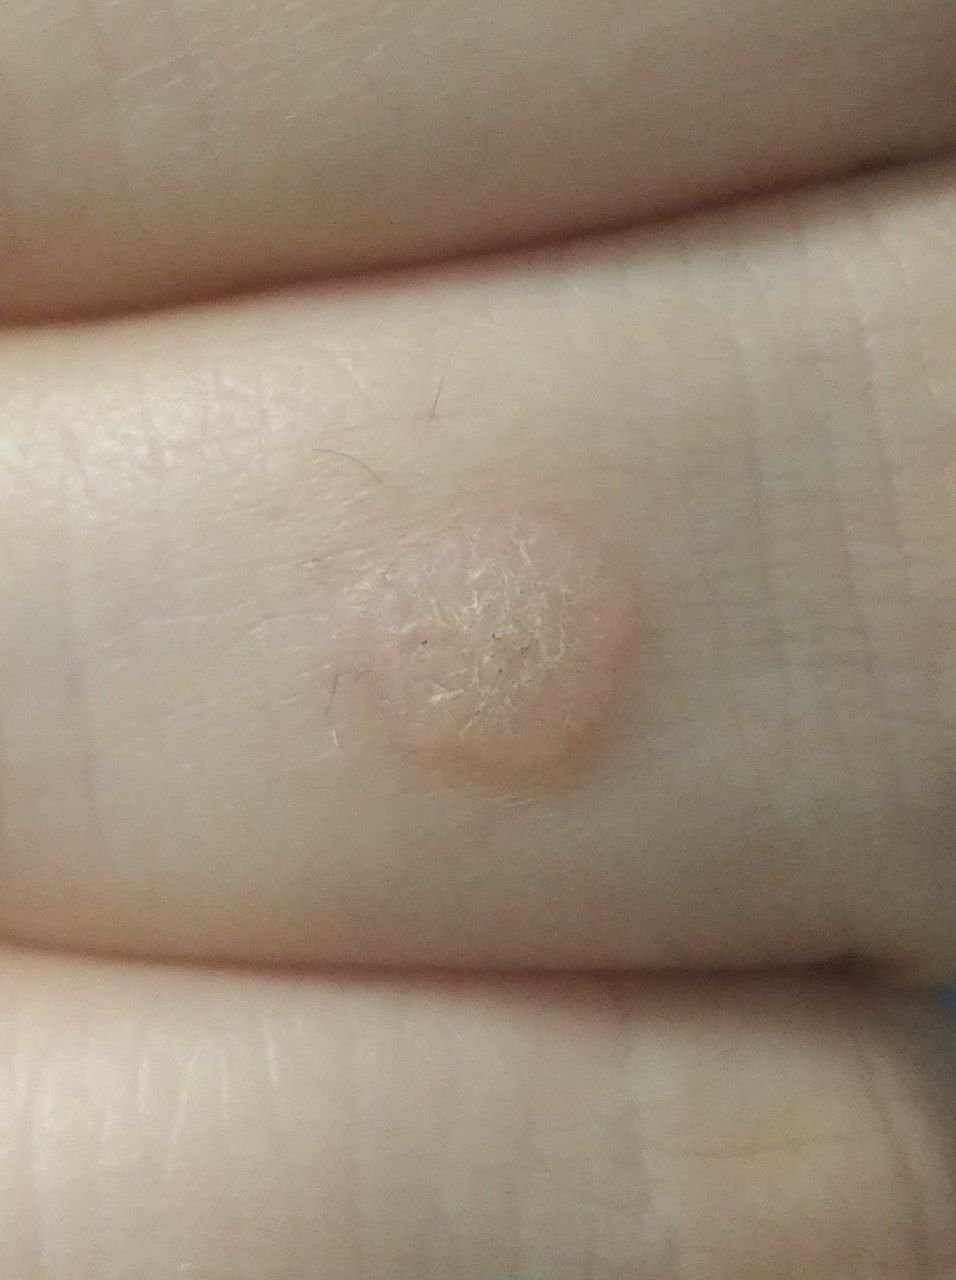
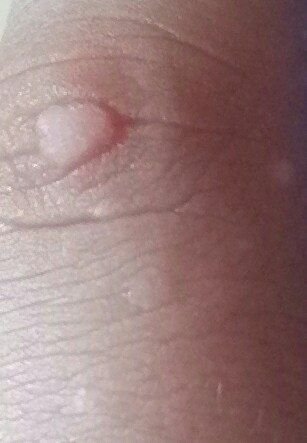
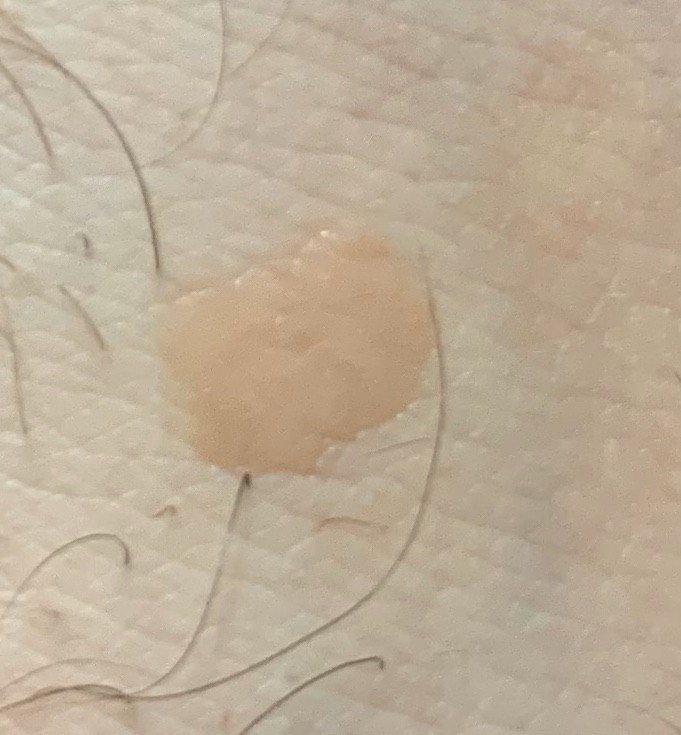
Flat warts present as small, slightly elevated lesions with a smooth, flattened surface. They often occur in clusters or linear patterns due to the Koebner phenomenon (appearance of new lesions after trauma). Their color ranges from skin-colored to pale brown or grayish, depending on the degree of keratinization and sun exposure.
Key clinical features include:
- Size: Typically 2–5 mm in diameter and 1–2 mm in height;
- Texture: Soft, smooth, and slightly velvety to the touch;
- Margins: Clearly defined, often with a subtle corolla of elevated skin around the edge;
- Hair growth: Usually absent on the lesion itself;
- Location: Commonly seen on the face, forehead, cheeks, chin, back of hands, forearms, and shins;
- Symptoms: Asymptomatic in most cases; rarely, mild tingling or irritation on pressure may occur.
Dermatoscopic Description
Dermatoscopy can aid in distinguishing flat warts from other papular dermatoses. In the case of plane warts, the following structures are often observed:
- A regularly distributed pattern of tiny dotted vessels over a lightly pigmented, finely granular surface, with little keratin build-up;
- Absence of the dense “frogspawn” pattern seen in common warts, which helps separate the two;
- No pigment network, which distinguishes a flat wart from a melanocytic lesion.
Dermoscopy is an adjunct here, not a definitive test: the diagnosis of plane warts rests on their clinical appearance — small, smooth, flat-topped papules, usually numerous and grouped on the face or the backs of the hands. Dermoscopy helps mainly in separating them from early basal cell carcinoma, seborrheic keratosis and pigmented lesions.
Differential Diagnosis
Flat warts must be differentiated from a variety of benign and malignant skin lesions that can mimic their appearance. Accurate diagnosis is particularly important for atypical or resistant cases. The differential diagnosis includes:
- Papillomatous nevus: More irregular and pigmented than flat warts, often congenital in origin;
- Nevus sebaceous: Typically yellowish, waxy plaques found on the scalp or face in childhood;
- Halo nevus: Pigmented nevus with surrounding depigmented area, usually without keratinization;
- Dermatofibroma: Firm, brownish nodules that dimple inward when pinched;
- Common warts (verruca vulgaris): More raised and keratinized, often with rough surface and black dots;
- Plantar wart: Found on soles of the feet, deeper and often painful;
- Molluscum contagiosum: Dome-shaped lesions with central umbilication, softer on palpation;
- Nodular basal cell carcinoma: Slow-growing pearly nodule, may ulcerate or bleed;
- Amelanotic melanoma: Rare and non-pigmented malignant lesion, requires biopsy if suspected.
Risks and Clinical Relevance
Flat warts are considered oncologically safe and carry a negligible risk of malignancy. Nonetheless, patients should be educated to monitor for signs of transformation, especially in lesions that change in:
- Size (rapid or disproportionate growth);
- Color (darkening, irregular pigmentation);
- Texture (ulceration or excessive keratinization);
- Symptoms (onset of pain, bleeding, or inflammation).
Additional risks include:
- Cosmetic impact: Particularly in facial or visible locations;
- Trauma-related complications: On areas exposed to friction or mechanical irritation (e.g., hands, wrists);
- Autoinoculation: New lesions may form on adjacent skin through scratching or shaving;
- HPV carriage: Indicates a compromised immune defense or increased viral load, especially in cases of widespread lesions.
Tactics: Clinical Management and Monitoring
If flat warts are asymptomatic and not cosmetically disturbing, dermatologists may recommend dynamic observation with periodic re-evaluation—especially in children and adolescents, where spontaneous resolution is common.
However, a dermatologic consultation is warranted in the following scenarios:
- Lesions are multiplying or merging into clusters;
- There are changes in appearance or texture;
- Warts are traumatized or inflamed;
- There is significant aesthetic or psychological concern;
- The patient is immunocompromised or has chronic skin disorders.
Plane warts do not call for a fixed schedule of examinations, and routine photographic documentation or skin mapping is not needed. What matters is being seen again if a lesion changes in a way that does not fit a wart.
Treatment of Flat Warts
Treatment aims to eliminate visible lesions, prevent recurrence, and avoid complications. Minimally invasive methods are preferred, especially for facial or cosmetically sensitive areas.
Common treatment methods include:
- Observation: Appropriate for many cases, and the first thing to consider. Plane warts commonly clear on their own, particularly in children and adolescents, and doing nothing avoids the scarring and pigment change that treatment on the face can cause;
- Topical retinoids: May be considered for facial lesions, applied over weeks under medical supervision, with the expected irritation explained in advance;
- Topical salicylic acid: An option on the hands, used with more caution than on thicker skin elsewhere;
- Cryotherapy and other destructive methods: Require real caution on the face, where they can leave pale or dark marks and scars that outlast the warts themselves. Light treatment over several sessions is preferred to aggressive freezing;
- Laser, radiofrequency or electrocoagulation: Not routine treatments for flat warts. They carry the same risk of pigmentary change and scarring, and are reserved for selected resistant cases;
- Surgical excision: Reserved for atypical lesions or cases with diagnostic uncertainty, followed by histopathological examination.
Self-removal is discouraged due to the risk of bleeding, infection, scarring, and viral dissemination. All procedures should be performed in sterile conditions by qualified professionals.
Prevention of Plane Warts
Prevention of verruca plana relies on minimizing exposure to HPV, maintaining healthy skin, and supporting immune function.
- Do not shave over lesions. Shaving across a flat wart is one of the most reliable ways to spread it along the shaved area, and is the usual explanation for a line of new warts on the face or legs;
- Avoid scratching or picking lesions, which carries the virus to adjacent skin;
- Do not share razors or towels, and keep personal care items personal;
- Protect the skin from minor injury, and treat existing skin conditions, since intact skin is the main defence against infection;
- See a clinician if a lesion changes in a way that does not fit a wart — rather than on a fixed schedule.
With early identification, proper management, and education, most flat warts can be treated successfully—preventing cosmetic issues and reducing the spread of HPV within the population.






Copyright concern about an image on this page? Write to mail@skinai.pro. Images may not be reused without permission unless an open licence is stated on this page.

Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)