Melanoma (ICD-10: C43) 🚨
Melanoma: A Highly Aggressive and Potentially Lethal Form of Skin Cancer
Melanoma is a serious and extremely aggressive type of malignant tumor that originates in specialized skin cells known as melanocytes. These cells are responsible for the production of melanin—the natural pigment that determines the color of our skin, eyes, and hair. Unlike some other skin-related cells, melanocytes are not confined to the surface of the skin. They are also found in deeper anatomical regions, including mucous membranes (such as those in the mouth, nasal passages, and genitals) as well as the retina of the eye. Because of this widespread distribution, melanoma can develop in various locations across the body. This includes not only the skin but also internal surfaces such as the eyes, the genital area, the rectum, and even soft connective tissues. However, the vast majority—about 95%—of all diagnosed melanoma cases are found on the skin, making cutaneous melanoma the most prevalent form of the disease.
What Makes Melanoma So Aggressive and Life-Threatening
The dangerous reputation of melanoma comes from its unique biological behavior. Unlike many other skin tumors, melanoma is known for its ability to relapse repeatedly and to spread—often rapidly—to distant organs in the body. This metastatic spread, or metastasis, means that melanoma can move far beyond its original site and invade critical systems such as the lungs, liver, brain, and bones. Melanoma cells can migrate through the lymphatic system (lymphogenous route) or via the bloodstream (hematogenous route), further increasing the potential for widespread dissemination. One of the key factors influencing the speed and severity of melanoma progression is the state of the body’s immune system, particularly its innate ability to recognize and destroy abnormal or cancerous cells. When this natural antitumor defense is compromised, melanoma may advance at a much faster pace, making early detection and intervention crucial.
Classification and Major Types of Melanoma
There are several clinically recognized types of melanoma, each with its own unique characteristics, prevalence, and typical outcomes. Understanding these subtypes helps in assessing prognosis and guiding treatment decisions:
- Superficial Spreading Melanoma: This form is the most frequently diagnosed and is more common in women. It tends to spread across the surface of the skin before penetrating deeper layers, which often allows for earlier detection and a relatively favorable prognosis. It accounts for approximately 70% of melanoma cases.
- Nodular Melanoma: More often found in men, this subtype grows vertically rather than spreading outward. It penetrates deeply into the skin very early, leading to a more serious clinical outlook. Representing around 15% of cases, it is associated with a higher risk of complications due to its invasive nature.
- Acrolentiginous or Subungual Melanoma: Seen more commonly in individuals with darker skin tones, this form often develops in areas not usually exposed to the sun, such as the soles of the feet, the palms of the hands, and under the nails. It accounts for about 10% of all melanoma diagnoses.
- Lentiginous Melanoma: This variant typically appears in older adults, particularly women, and is associated with age-related pigment changes such as lentigo or melanosis. Like the superficial spreading type, it grows slowly and is less likely to invade deeply in its early stages. It comprises approximately 5% of cases.
- Amelanotic (Pigmentless) Melanoma: A very rare and diagnostically challenging form of the disease, amelanotic melanoma lacks the typical dark pigmentation. Because of its subtle appearance, it is often mistaken for benign lesions or other conditions, which can delay diagnosis and treatment.
Predisposing Factors That Contribute to the Development of Melanoma
Melanoma can occur at any age, and its distribution across age groups depends a good deal on which subtype is in question. Risk does rise with cumulative sun exposure and with age, but that is a tendency rather than a rule, and melanoma in a young adult is not a rarity to be discounted. Older adults—particularly those above 60 years of age—are more likely to develop what are known as lentiginous forms of melanoma. These forms are often linked to long-term sun damage and appear against a background of age-related pigmentation disorders such as lentigo or melanosis, especially on areas of the body that have been chronically exposed to the sun, like the face and forearms.
The transformation of normal melanocytes into malignant melanoma cells is a complex biological process influenced by a wide array of internal and external factors. These factors act either individually or in combination, gradually damaging the DNA within melanocytes and disrupting normal cellular behavior. Over time, these altered cells may acquire the ability to multiply uncontrollably, evade the immune system, and invade surrounding tissues, eventually developing into melanoma.
Risk Factors That Can Elevate the Likelihood of Developing Melanoma
Although it is difficult to pinpoint a single, universal cause for melanoma, medical research has identified several contributing elements that are known to significantly increase the risk of its development. These risk factors do not act equally in all individuals, and the presence of one or more of them does not guarantee that melanoma will develop. However, their influence is substantial enough to warrant careful monitoring and preventive measures:
- Ultraviolet Radiation Exposure: Both natural ultraviolet (UV) rays from sunlight and artificial sources such as tanning beds or sunlamps can damage the DNA in skin cells. Chronic or intense UV exposure is one of the most well-established and avoidable risk factors for melanoma.
- Light Skin Phototypes (I–II): Individuals with fair or very light skin, who also tend to have light-colored eyes and hair, possess lower levels of melanin. This pigment normally provides some protection against UV rays. As a result, people with these phototypes are significantly more vulnerable to sunburns and skin damage.
- Eye and Hair Color: Blue, gray, or green eyes, as well as blond or red hair, are often associated with increased melanoma risk due to the genetic links with reduced melanin production.
- Frequent or Severe Sunburns: Recurrent sunburns, especially those acquired during childhood or adolescence (particularly before age 14), are considered particularly harmful. Such early skin damage can predispose individuals to melanoma later in life.
- Presence of Atypical or Multiple Moles: Dysplastic nevi, atypical moles, congenital nevi, or blue nevi—especially when present in large numbers—are recognized as significant risk indicators. Specific skin conditions such as Dubreuilh melanosis also increase susceptibility.
- Family History of Melanoma: Individuals with close relatives (such as parents or siblings) who have had melanoma are more likely to develop the condition themselves, suggesting a strong genetic component in some cases.
- Genetic Disorders Affecting Skin Repair: Conditions like xeroderma pigmentosum, which impair the skin’s ability to repair DNA damage, dramatically elevate melanoma risk.
- Personal History of Melanoma: Individuals who have previously been diagnosed and treated for melanoma are at increased risk of developing another, either at the same site or elsewhere on the body.
- Age Above 50: The likelihood of developing melanoma increases with age due to cumulative exposure to environmental stressors and the gradual decline in immune system efficiency.
While the presence of these risk factors does not automatically mean that melanoma will develop, awareness and preventive strategies, including regular skin checks and protective measures against UV exposure, can dramatically reduce the chances of malignancy.
Diagnostics: How Melanoma Is Identified and Confirmed
Diagnosing melanoma is a multi-step process that requires the combination of clinical expertise, specialized imaging tools, and laboratory analysis. The initial stage of diagnosis begins with a comprehensive clinical examination performed by a healthcare professional, typically a dermatologist or oncologist. During this examination, the medical specialist conducts a careful visual inspection of the suspicious lesion, paying close attention to its shape, color, size, and texture, as well as any noticeable changes over time.
One of the key diagnostic tools used in this process is dermatoscopy (also known as dermatoscopy or epiluminescence microscopy). This non-invasive technique utilizes a handheld device with magnification and light to provide a detailed view of the internal structure of pigmented lesions. Dermatoscopy allows physicians to detect subtle patterns, irregularities, and abnormalities that may not be visible to the naked eye, significantly improving the accuracy of early melanoma detection.
However, while dermatoscopy offers important clues, it does not provide a definitive diagnosis. The only way to confirm whether a lesion is malignant melanoma is through histological examination, also known as a biopsy. In this procedure, the suspicious area—or the entire lesion—is surgically removed under local anesthesia and sent to a pathology laboratory. A pathologist then analyzes the tissue sample under a microscope to determine whether cancerous cells are present, their level of atypia, the depth of skin invasion, and other critical histological features. This microscopic analysis is considered the gold standard in melanoma diagnosis.
Once melanoma is confirmed, what follows depends on the tumour rather than on a fixed protocol. Imaging — ultrasound, computed tomography (CT), magnetic resonance imaging (MRI) or positron emission tomography (PET) — is not required for every newly diagnosed melanoma. Which investigations are appropriate is decided by the stage of the tumour, the clinical findings and the patient’s symptoms; a thin, early melanoma generally needs none of them. Sentinel lymph-node biopsy is relevant for selected primary melanomas, where its result informs staging and treatment, rather than for all of them.
Overall, accurate and timely diagnosis is essential for improving outcomes in patients with melanoma. Early detection, supported by a combination of clinical evaluation, dermatoscopic imaging, and histopathological confirmation, remains the cornerstone of effective melanoma management and can significantly improve long-term survival rates.
Symptoms: How Melanoma Manifests Visually and Physically
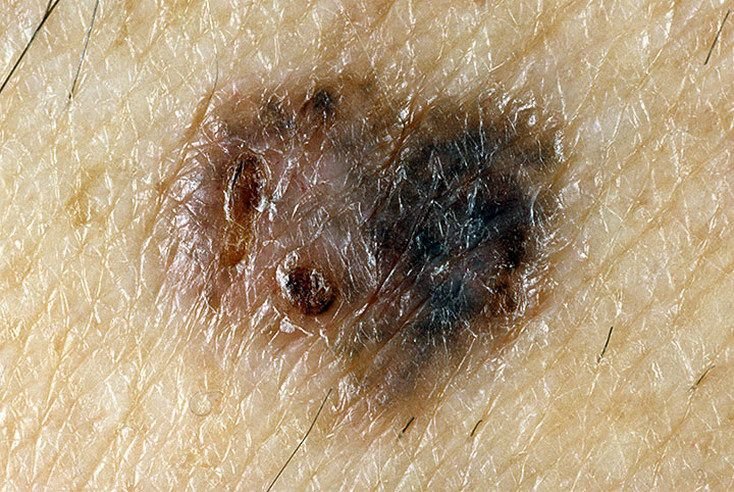
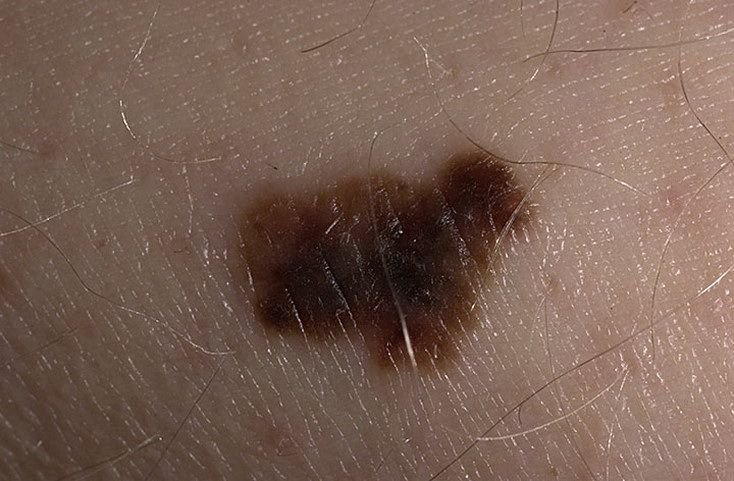
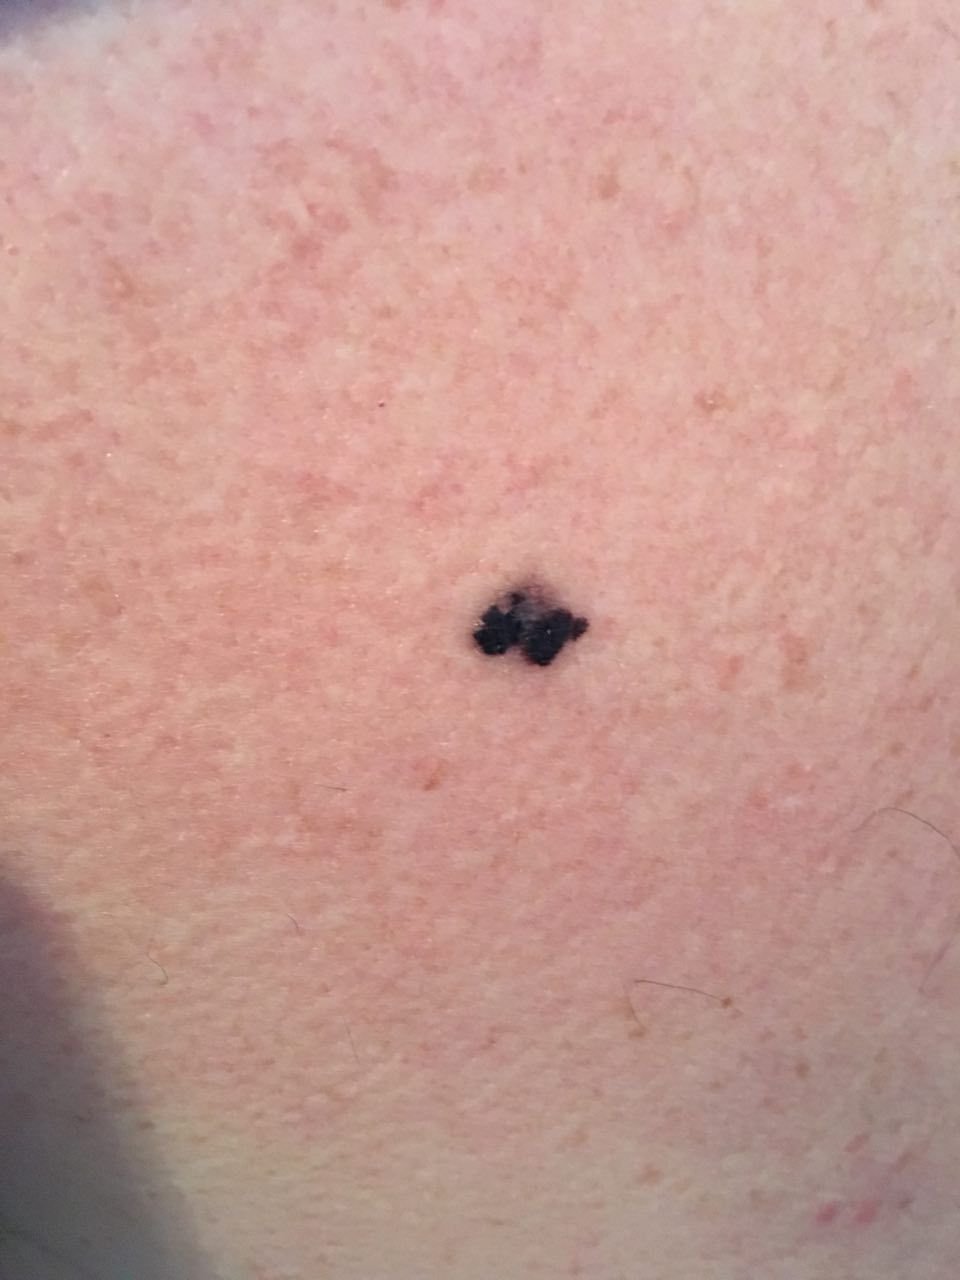
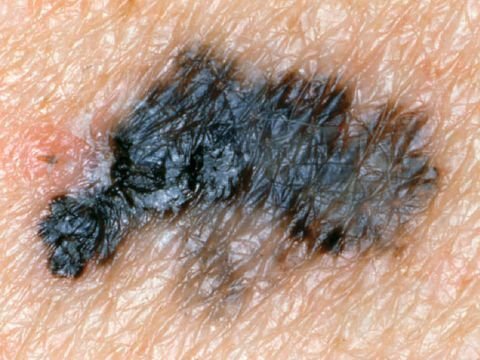
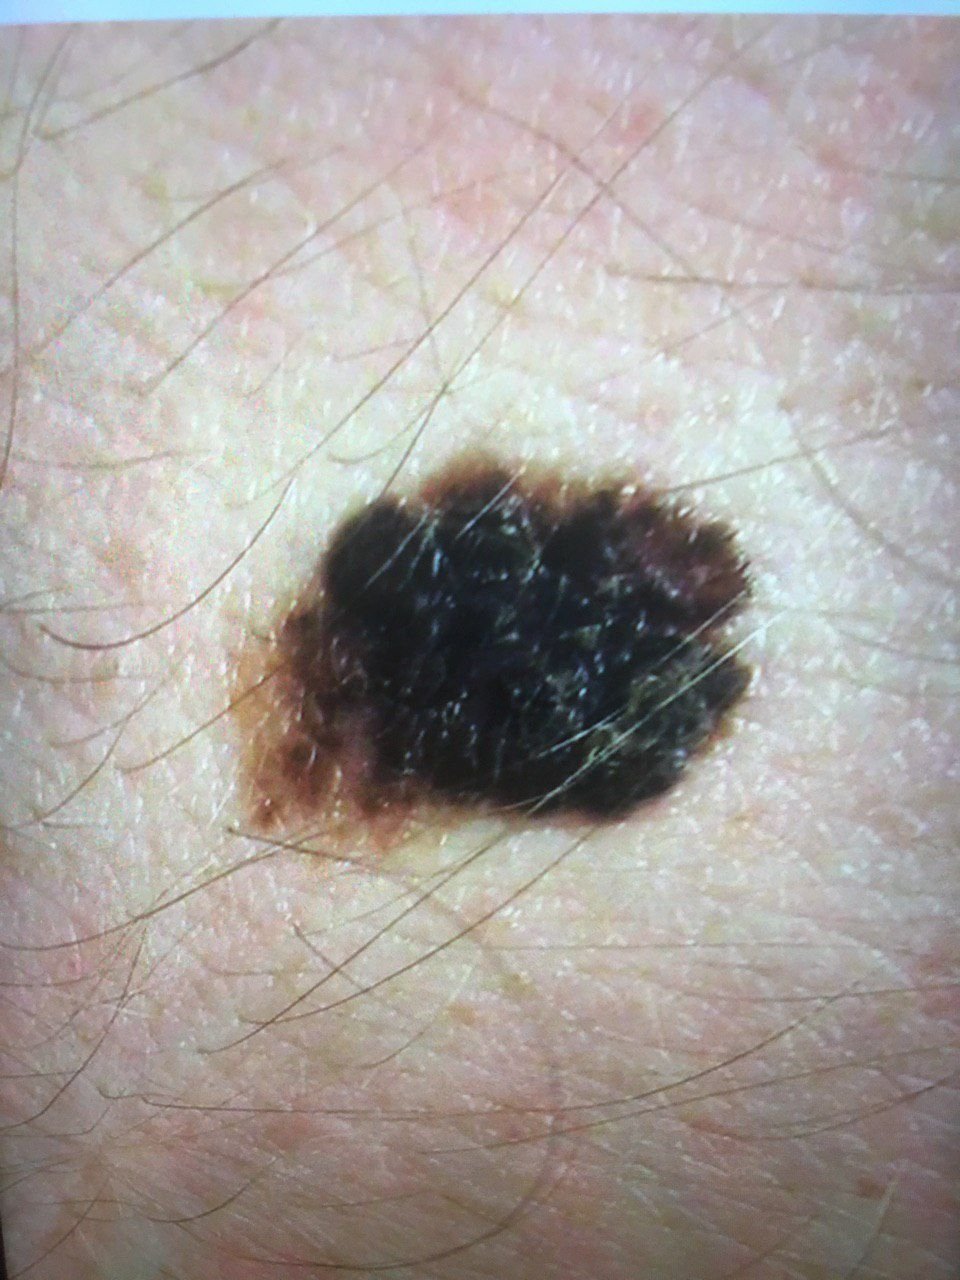
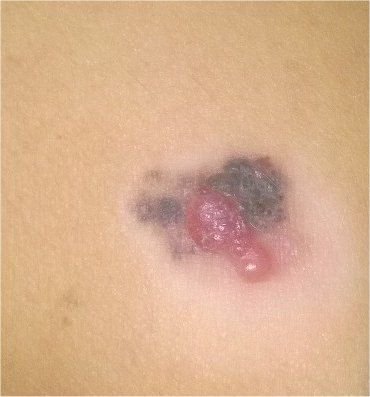
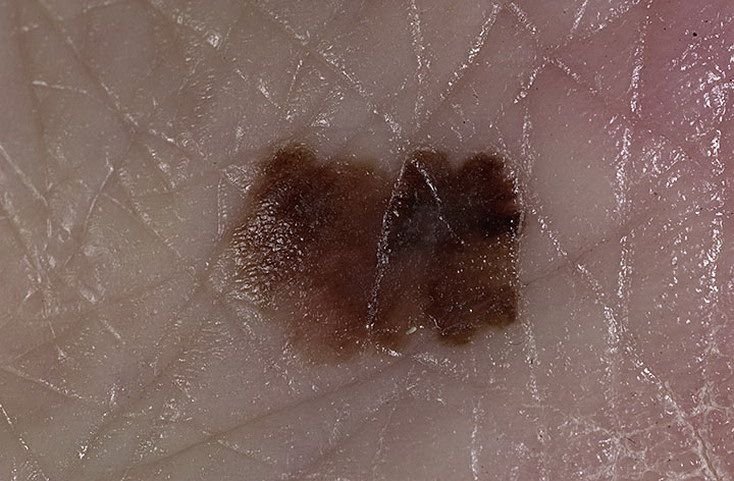
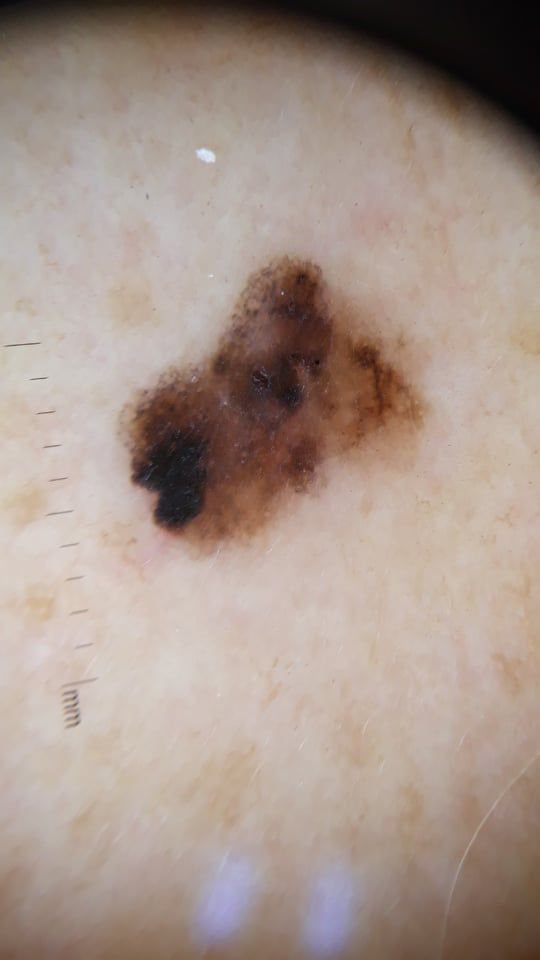
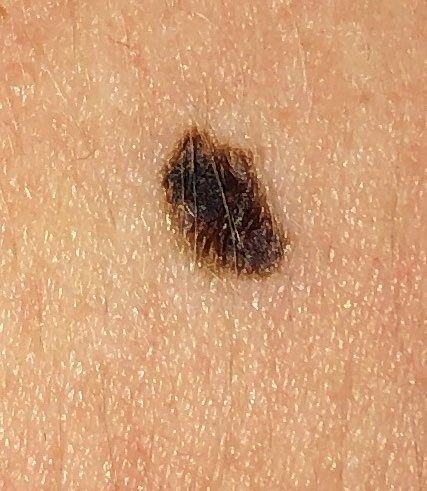
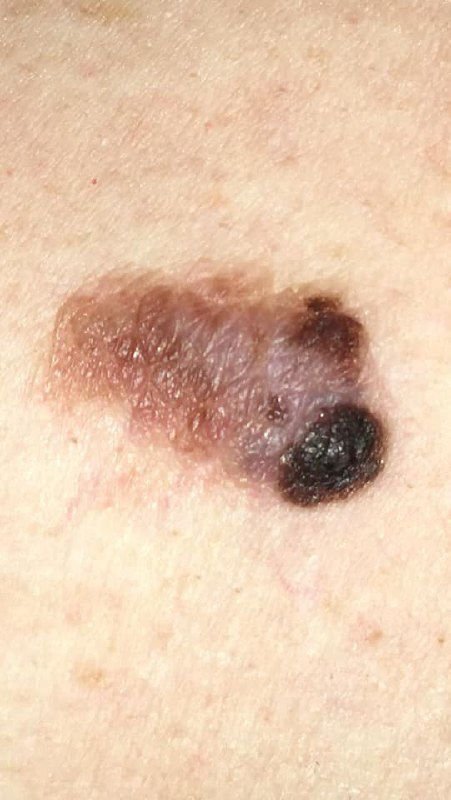
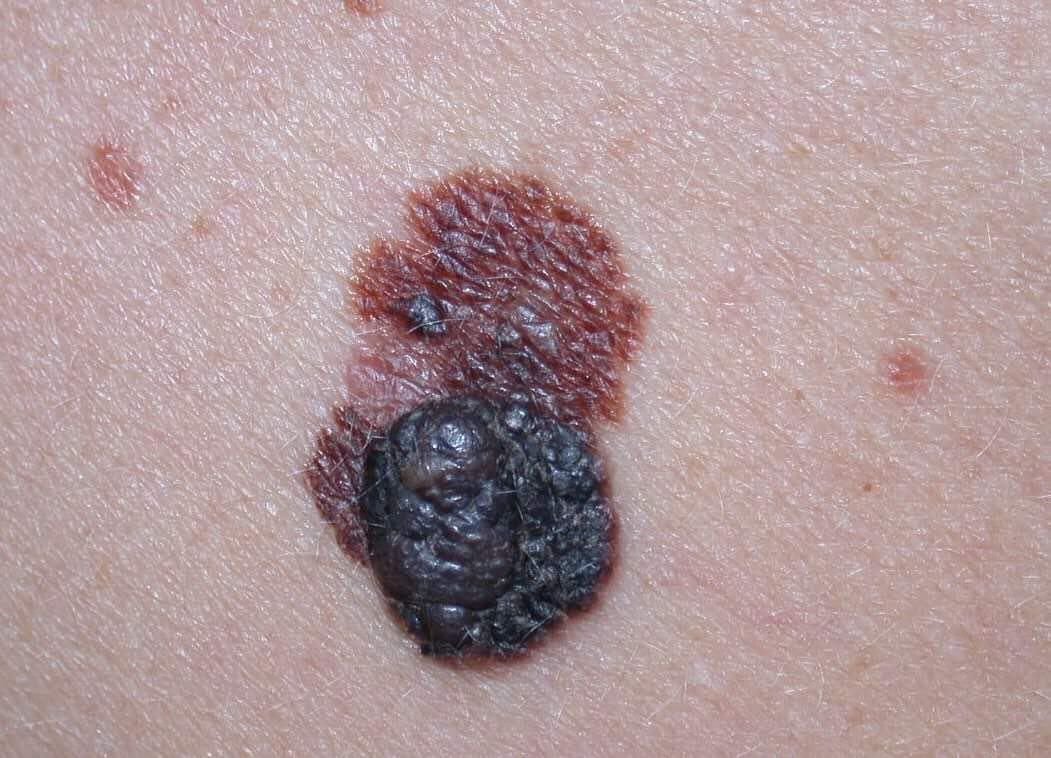
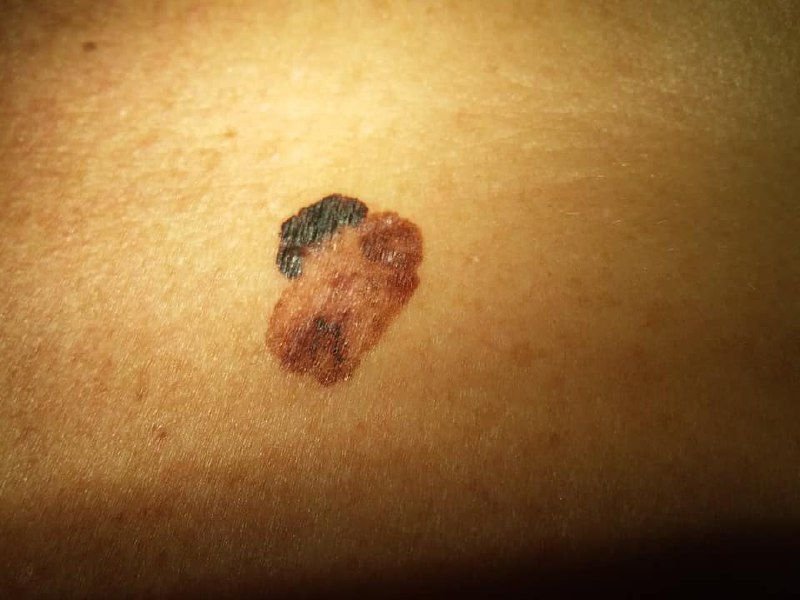
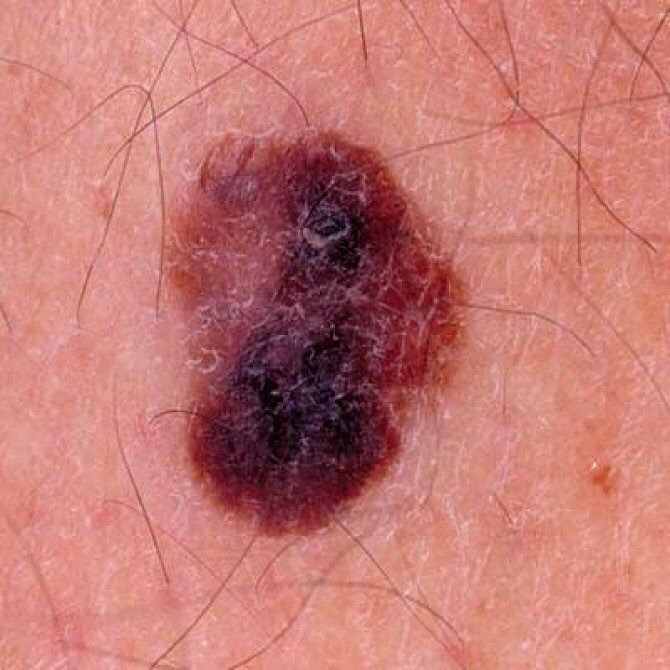
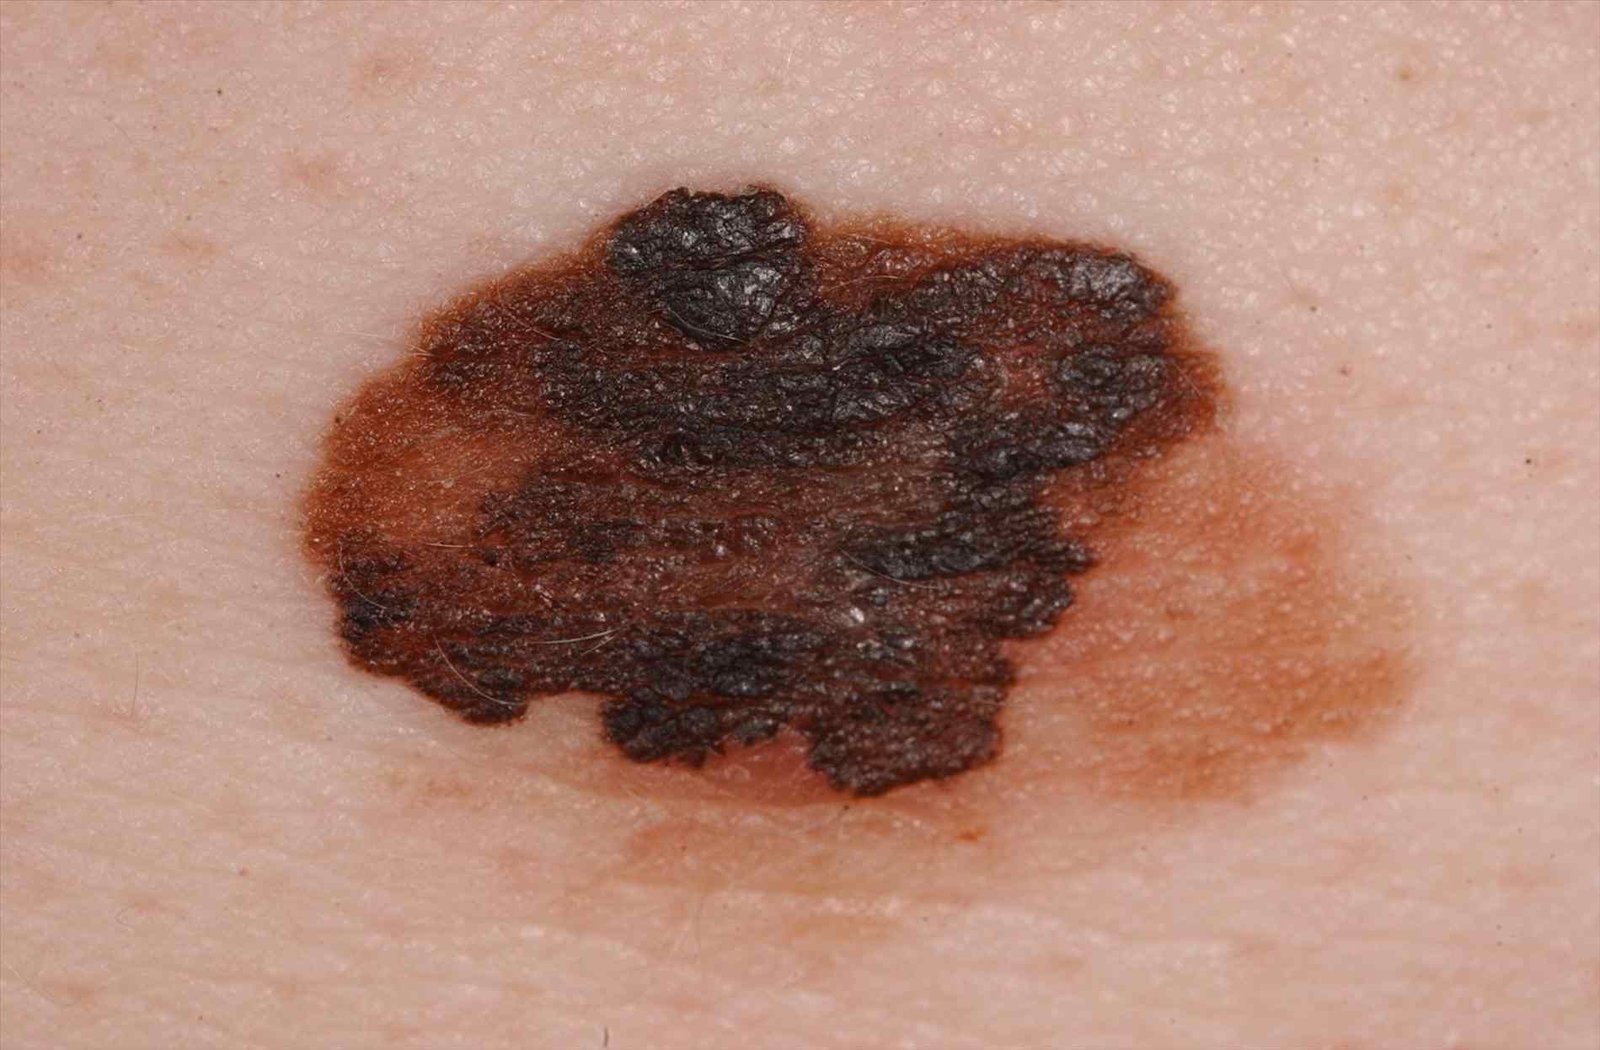
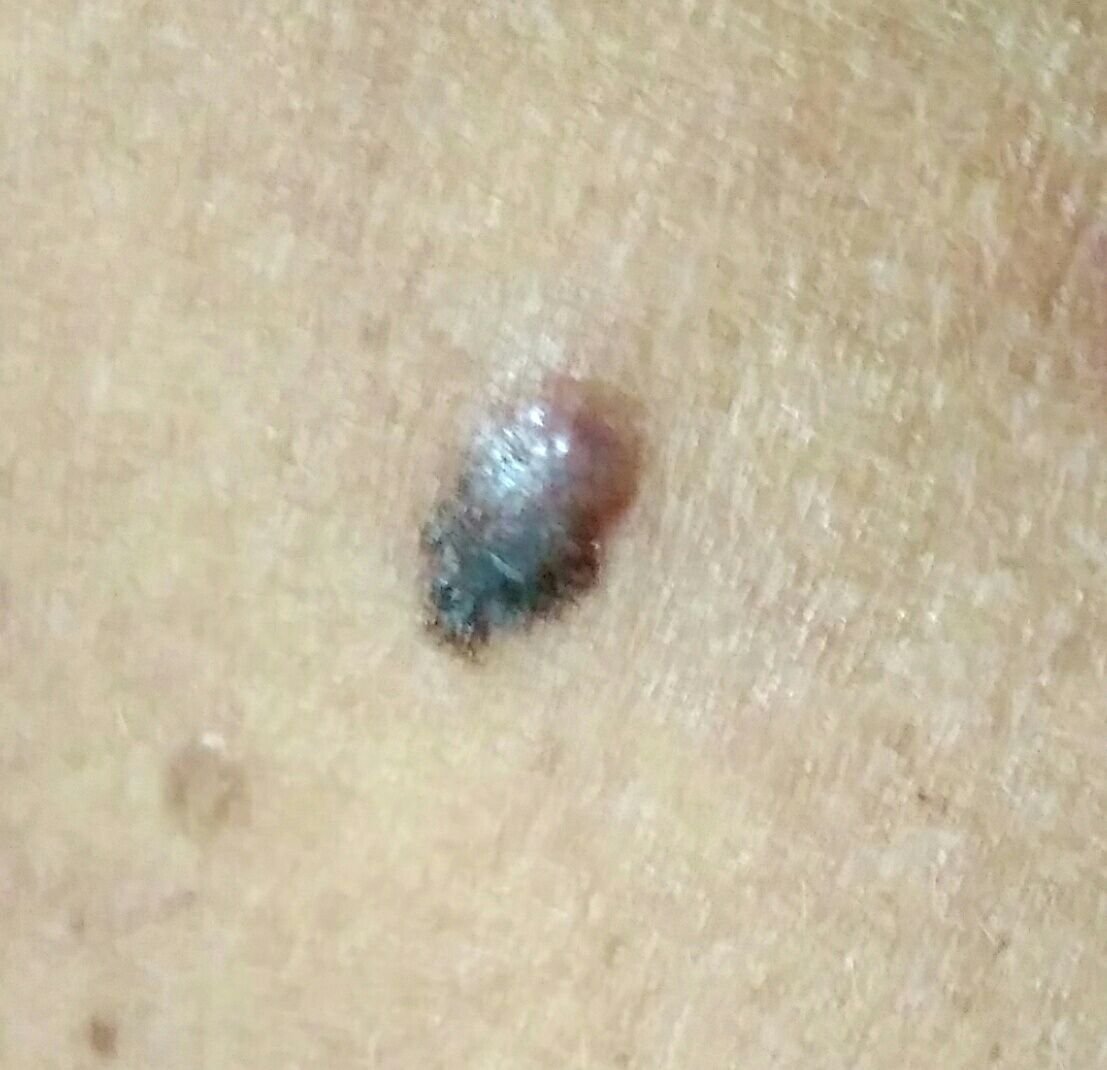
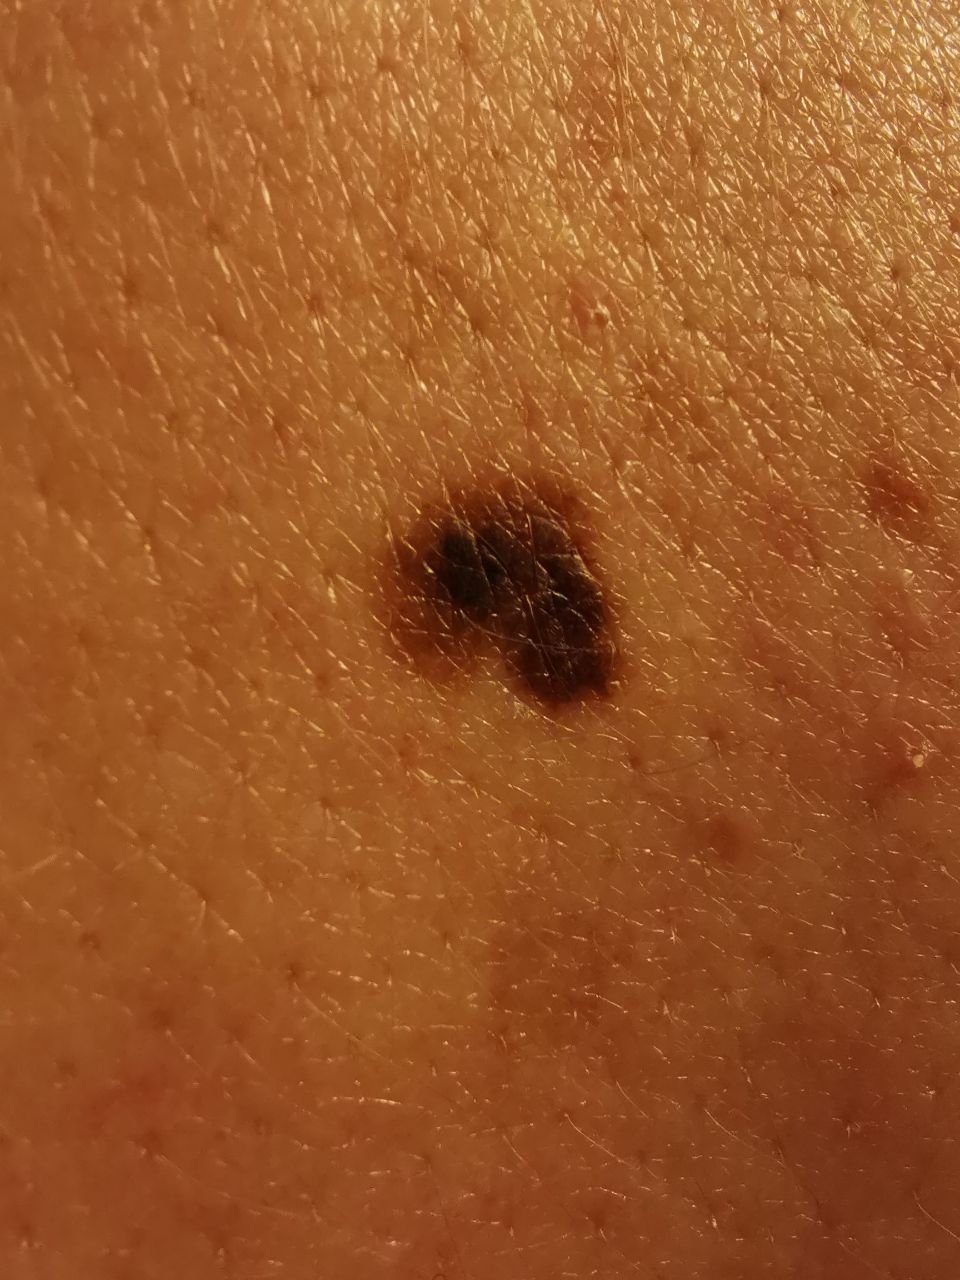
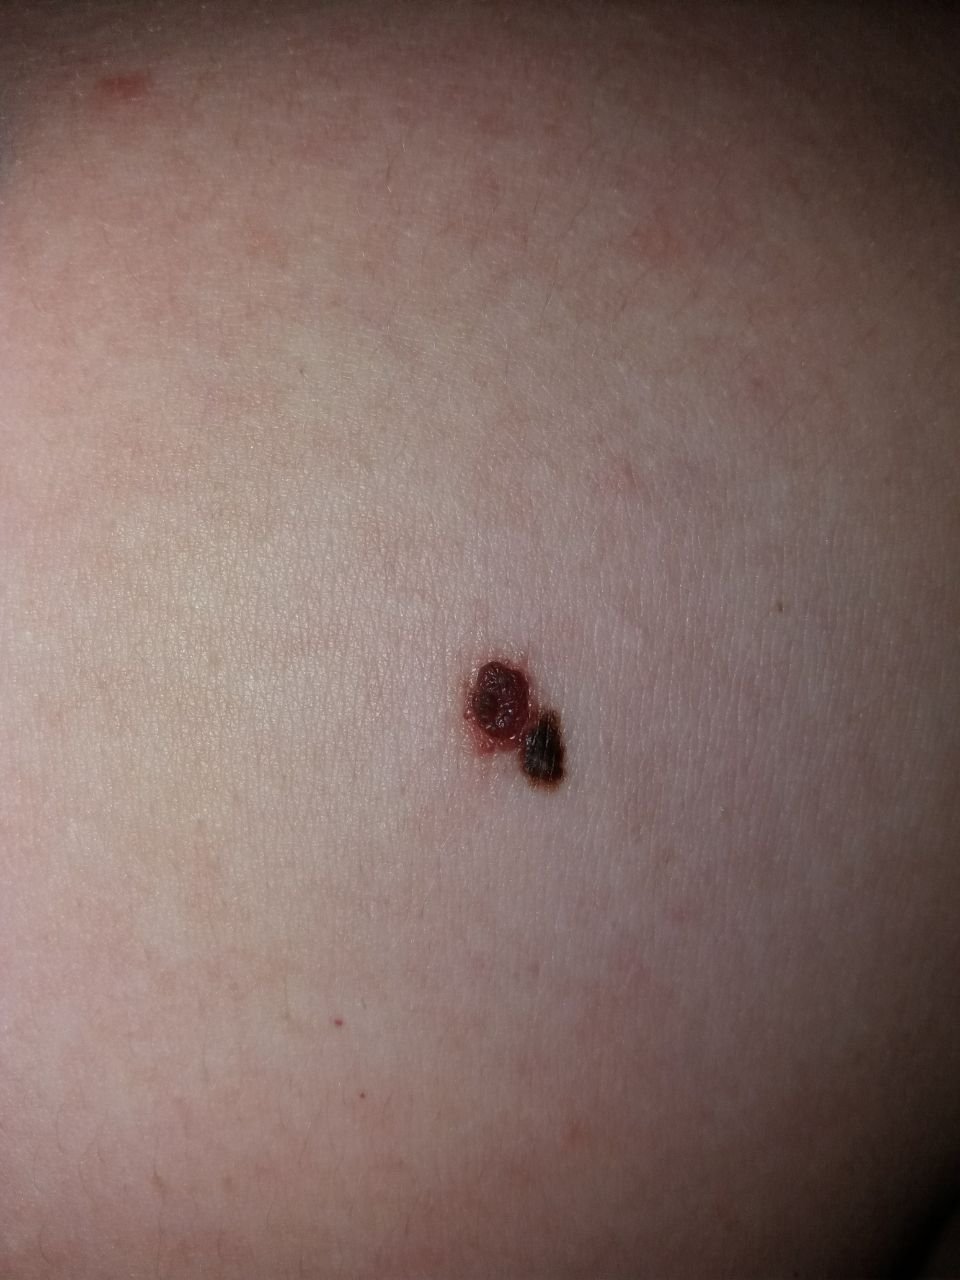
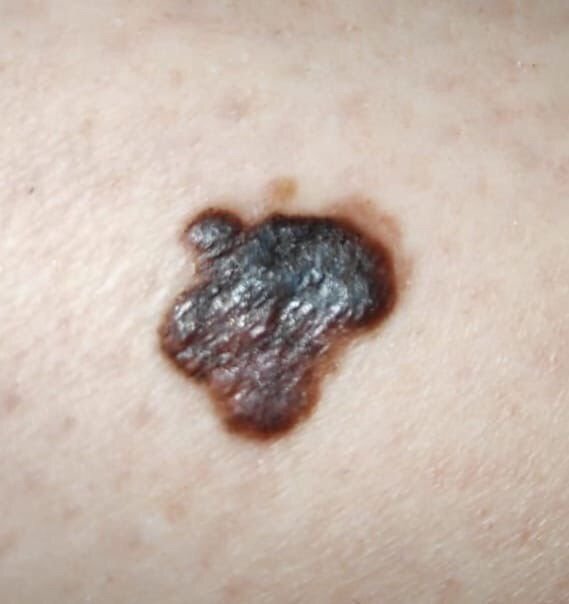
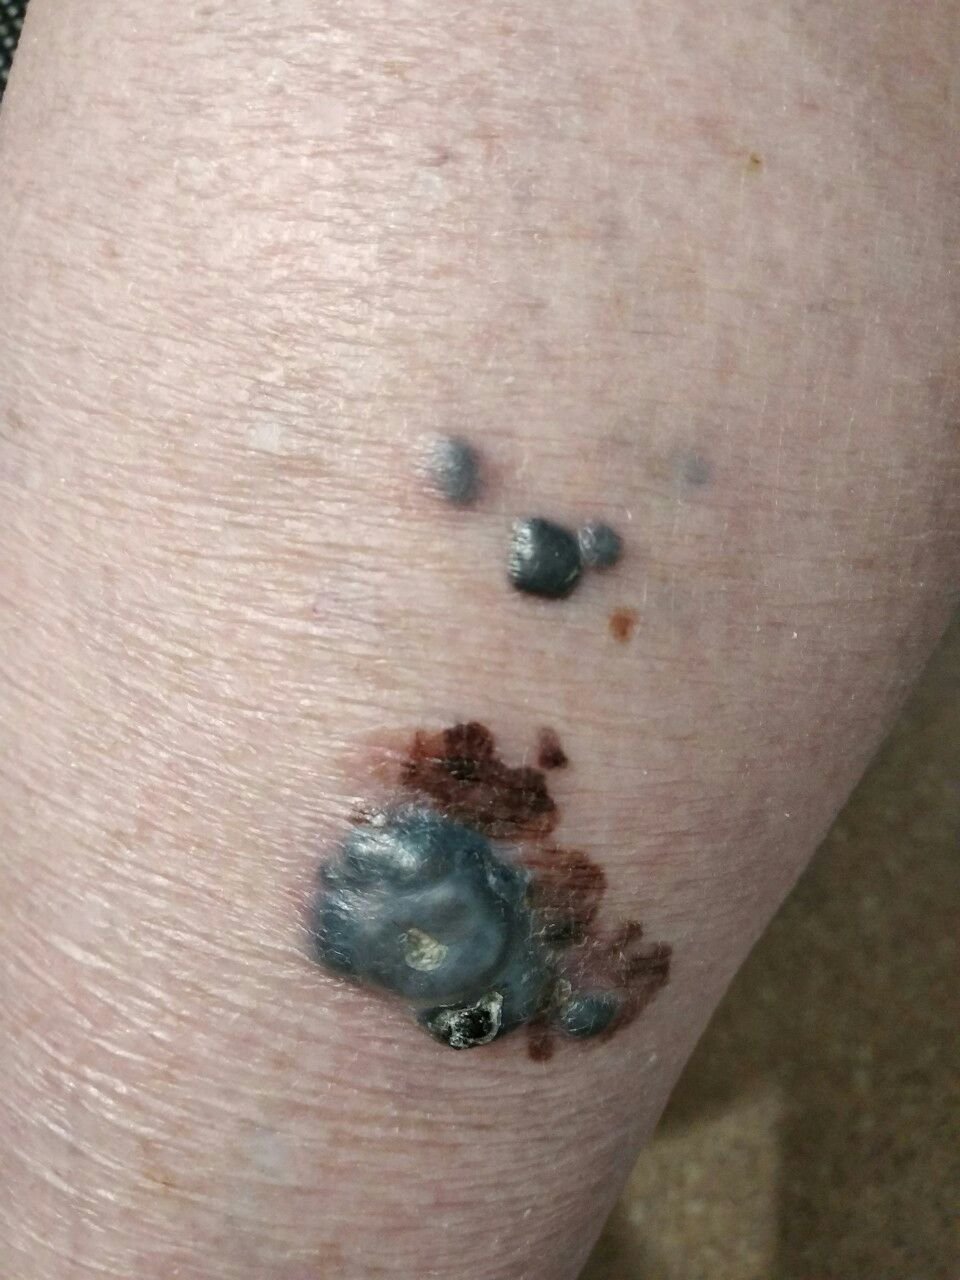
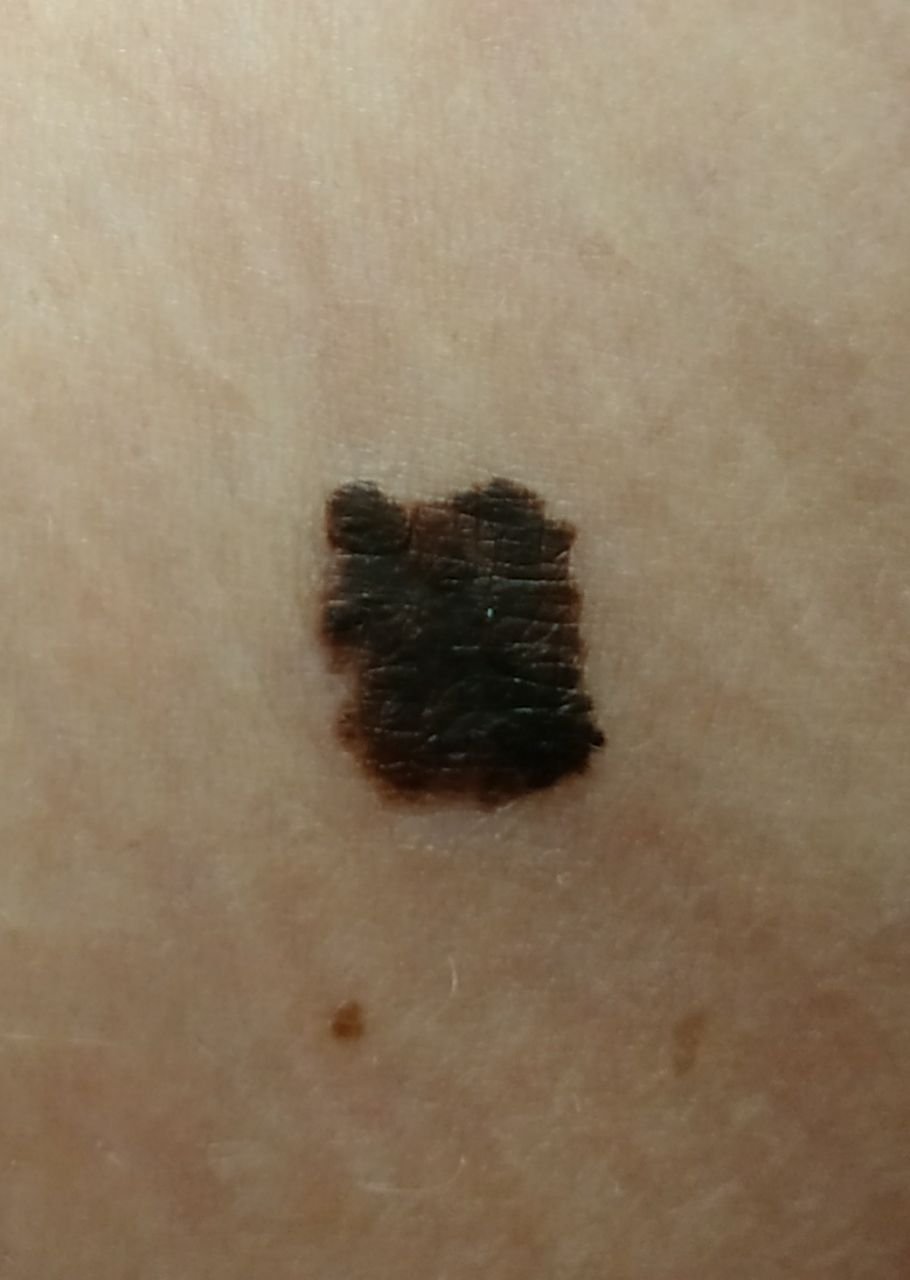
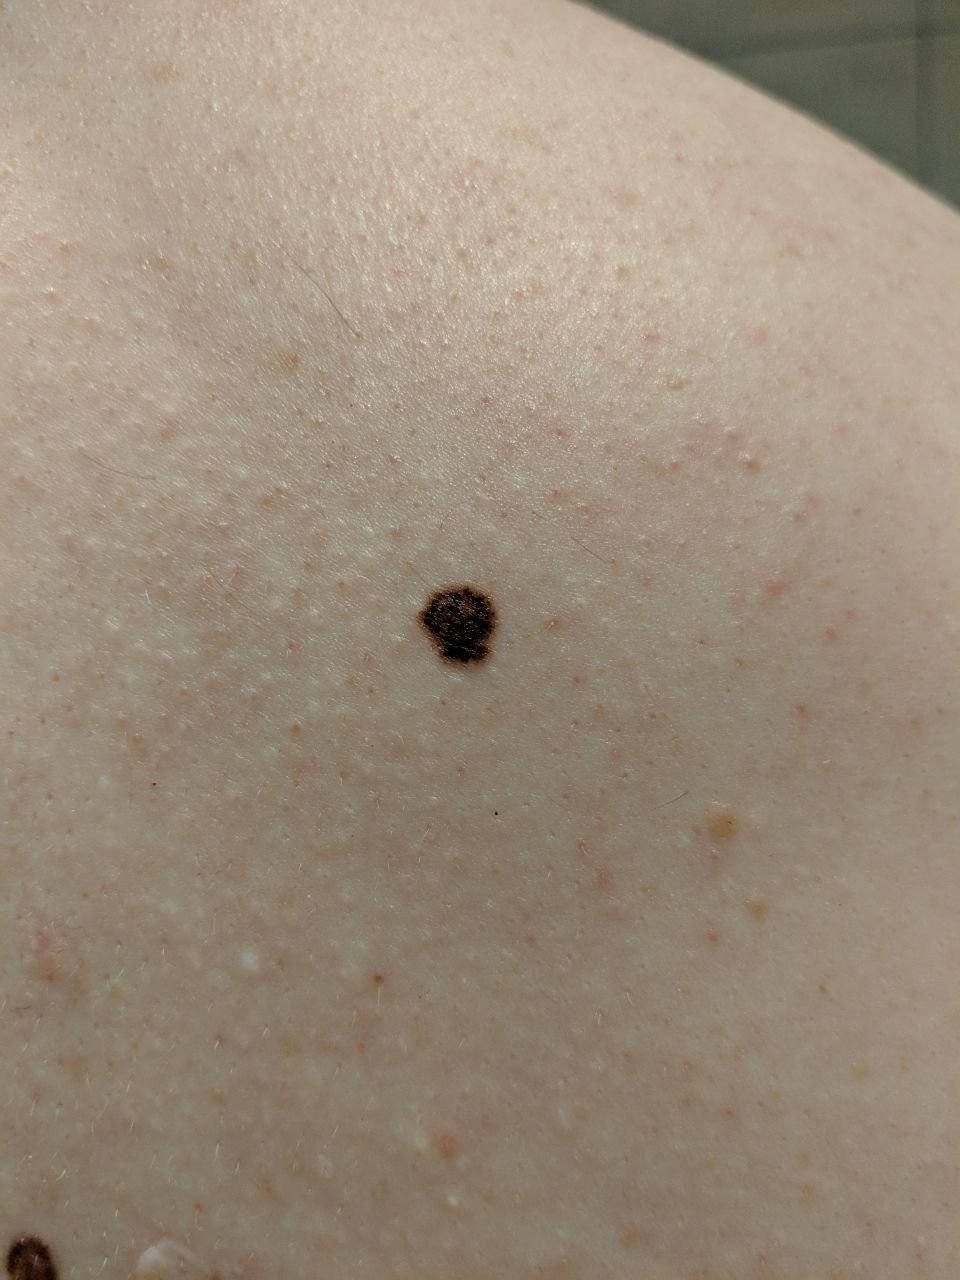
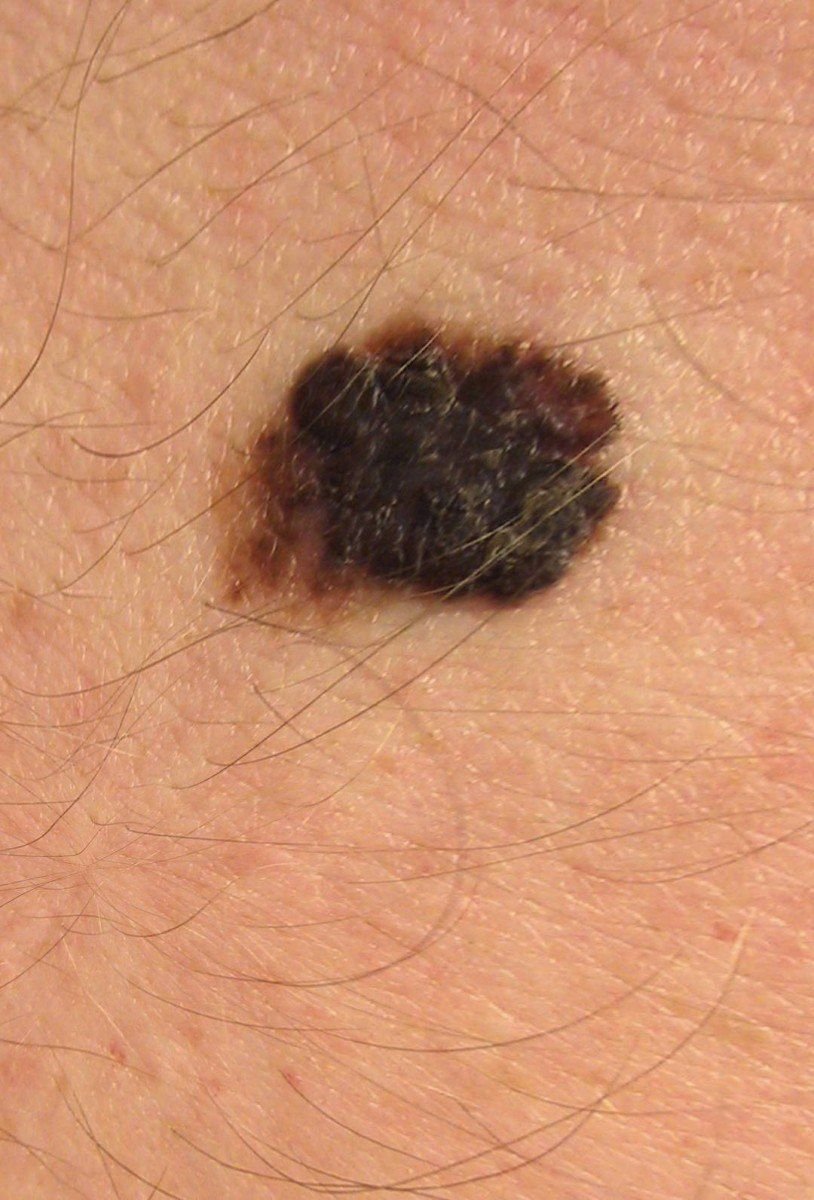
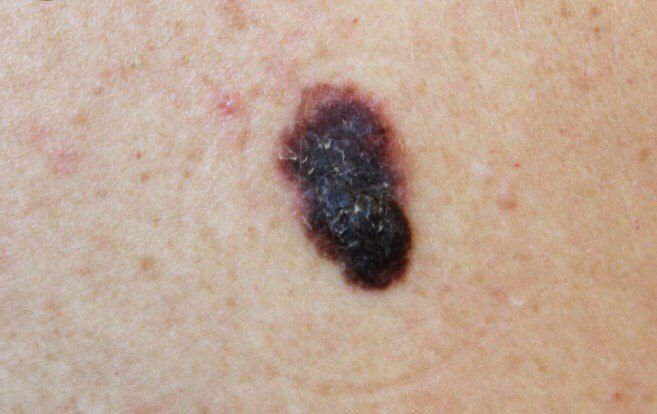
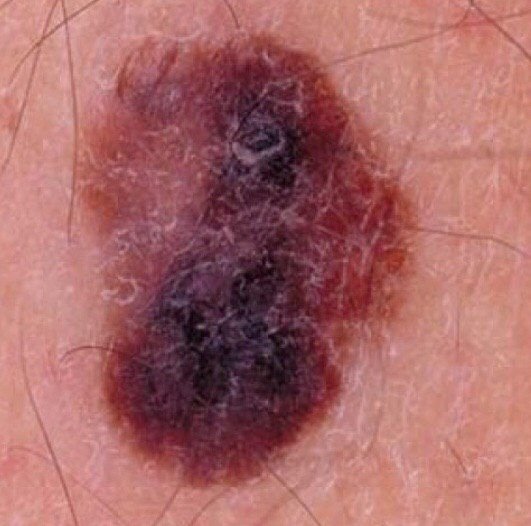
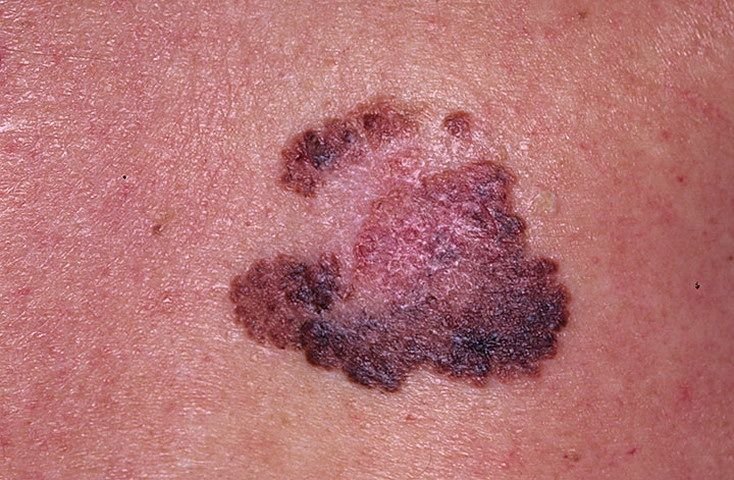
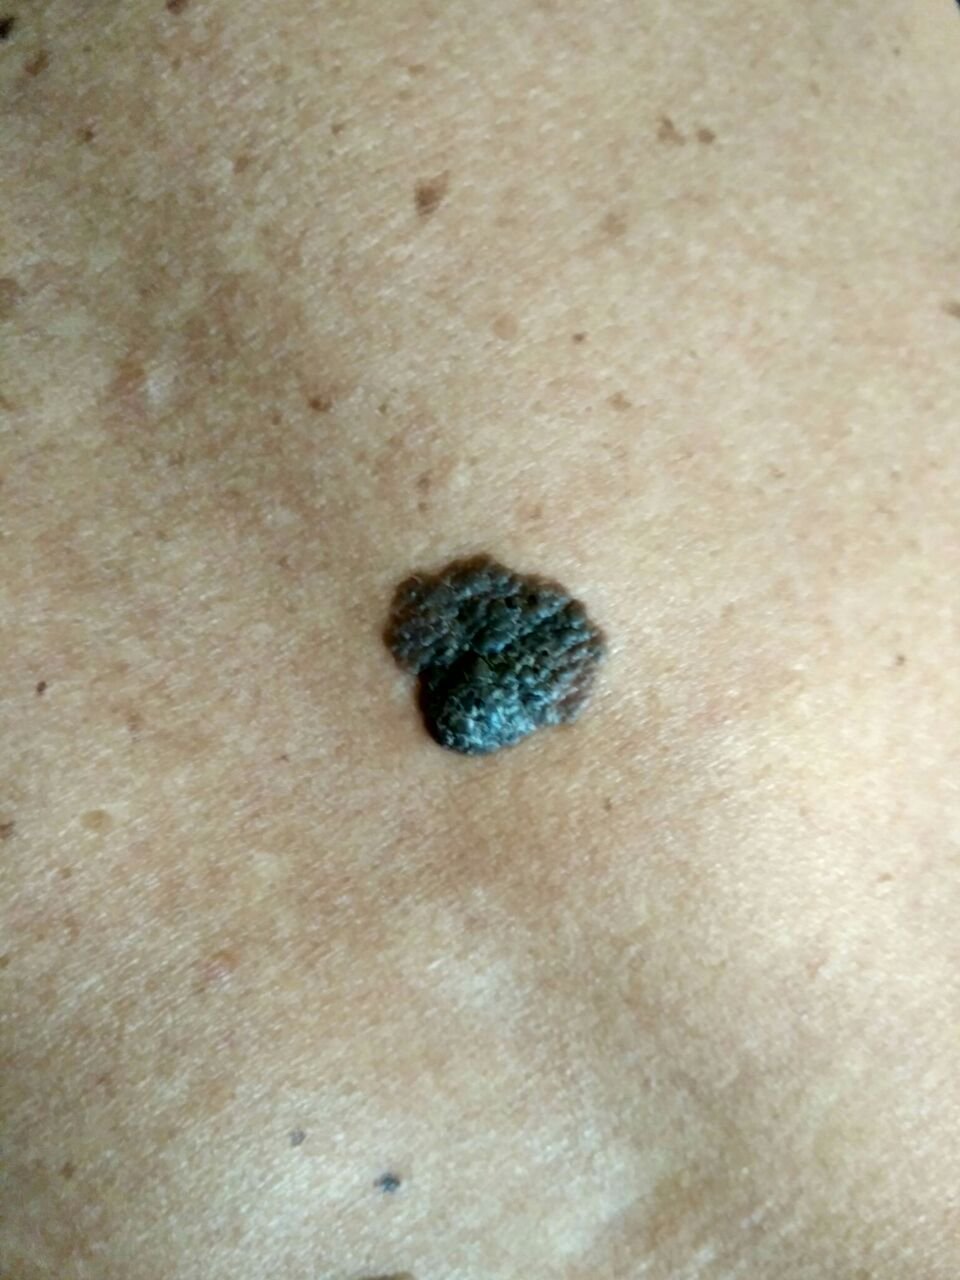
The clinical presentation of melanoma varies widely, but there are hallmark visual signs that can alert both patients and medical professionals to its presence. A melanoma lesion may appear as a flat or raised spot, or a combination of both, on the surface of the skin. These lesions often exhibit a multiform appearance and tend to differ in texture, color, and shape from normal skin or benign moles. In the earliest stages—designated as stage 0 (in situ) or stage I—the natural skin pattern may still be preserved. However, as the disease progresses, the surface often becomes smooth, uneven, or nodular, with features like ulceration, crusting, and even spontaneous bleeding becoming apparent.
To standardize the early detection of melanoma, the medical community uses the widely accepted ABCDE system (introduced by Friedman in 1985), which is designed to help evaluate suspicious pigmented skin lesions:
- A – Asymmetry: One half of the lesion does not match the other half in shape or size.
- B – Border: The edges of the lesion are irregular, notched, or blurred, especially in more advanced stages.
- C – Color: Uneven pigmentation with multiple shades of brown, black, or other colors like blue, pink, or white.
- D – Diameter: Melanomas are usually larger than 5–6 mm, although smaller lesions can still be dangerous.
- E – Evolving: The lesion changes over time in size, shape, surface texture, or symptoms such as itching or bleeding.
Additional warning signs that may accompany or develop later include the disappearance of hair from within the mole, new sensations like tingling or burning, hardening of the lesion, the appearance of satellite spots around the main tumor, and the enlargement of nearby lymph nodes. If several of these signs appear together, the lesion should be evaluated by a dermatologist promptly; melanoma cannot be reliably diagnosed by a fixed symptom count and requires clinical and histological assessment.
While melanoma can appear anywhere on the body, there are some gender- and age-related patterns. Women are more likely to develop melanoma on the lower limbs (legs), while men most commonly exhibit it on the torso. In older adults, facial melanomas are more prevalent, often due to cumulative sun exposure over the years.
Dermatoscopic Description: Microscopic Patterns of Malignancy
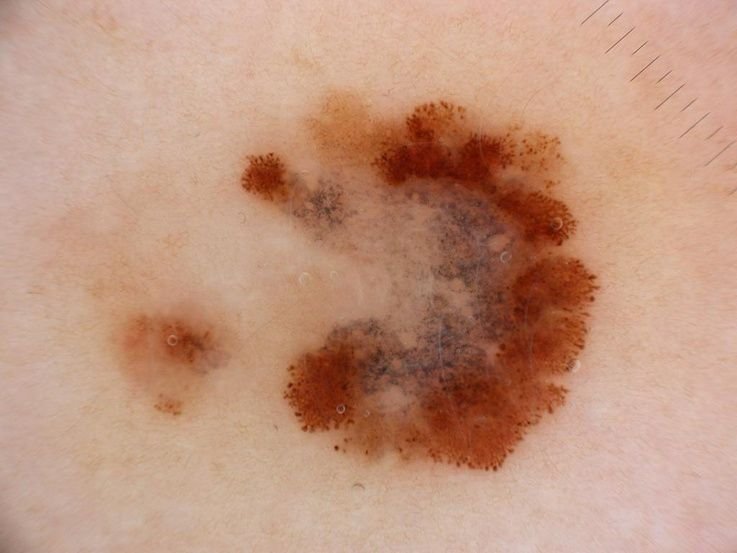
Dermatoscopy reveals highly specific visual patterns associated with melanoma, which can assist in distinguishing malignant lesions from benign ones. One of the key dermatoscopic findings is multicomponent structure—the presence of multiple overlapping visual characteristics within a single lesion.
Common dermatoscopic features of melanoma include:
- Atypical pigment network: Irregular pigmentation with varying intensity and distribution.
- Irregular streaks: Often appear as club-shaped or radiating structures on the periphery.
- Asymmetrically distributed globules and dots: These appear in uneven clusters within the lesion.
- Color asymmetry: Multiple hues, including black, brown, red, white, and blue, scattered throughout the lesion.
- Peripheral radial streaming: Light projections or radiations extending from the edge.
- Hypopigmentation and regression structures: Areas where pigment is lost or where scar-like tissue indicates tumor regression—a negative prognostic sign.
- Blue-white veil: Opaque bluish areas over a white base, often indicating deeper dermal invasion.
- Abnormal vascular patterns: Irregular blood vessels are commonly seen in aggressive forms of melanoma.
Differential Diagnosis: Conditions That May Resemble Melanoma
It is critically important to distinguish melanoma from other pigmented or vascular skin lesions, as misdiagnosis can lead to delayed treatment and worse outcomes. Conditions that may resemble melanoma include:
- Congenital dermal melanocytosis: Such as Mongolian spots, which are present at birth.
- Pigmented nevi: Including both simple and papillomatous types, which may mimic early melanoma features.
- Hemangiomas: Particularly those complicated by thrombosis that can alter their color and texture.
- Blue nevus: A deeply pigmented lesion that can appear alarming but is usually benign.
- Spitz nevus: Often seen in children and adolescents, but its resemblance to melanoma requires histological confirmation.
- Dysplastic nevi: Atypical moles that may evolve into melanoma or coexist with it.
- Lentigo: Age-related pigmented spots that require careful evaluation.
- Pigmented basal cell carcinoma: Another form of skin cancer that may display similar coloration and surface features.
Risks: Why Melanoma Is Considered One of the Deadliest Skin Cancers
Melanoma is widely recognized as one of the most aggressive and life-threatening types of skin cancer. Globally, the incidence of melanoma has been rising sharply, with the number of new cases doubling approximately every seven years. This alarming trend is primarily attributed to increasing exposure to ultraviolet (UV) radiation—both natural (from the sun) and artificial (from tanning beds)—and the tendency of people to travel more frequently to sunny regions, often without adequate sun protection.
Roughly half of all melanomas arise on skin that appears previously healthy, with no apparent pre-existing lesions. A minority of melanomas arise from a pre-existing pigmented lesion such as a mole; most arise de novo on previously normal skin. This dual origin complicates early detection and increases the risk of delayed diagnosis. While melanoma is about 10 times less common than other types of skin cancer (like basal or squamous cell carcinoma), it is responsible for the majority of skin cancer-related deaths. In fact, melanoma’s mortality rate is approximately 3.5 times higher than that of other malignant skin tumors.
Tactics: Clinical Strategy for Melanoma Management
When melanoma is suspected, it is crucial to consult a qualified oncologist or dermatologist without delay. The initial step involves thorough diagnostic evaluation, including clinical examination and biopsy. In cases where the diagnosis remains uncertain, a short-term observation period with frequent monitoring may be advised. However, more commonly, a complete excision of the suspicious lesion is performed, followed by histopathological analysis to confirm the diagnosis.
Once melanoma is confirmed, additional tests are carried out to determine whether the cancer has spread to nearby lymph nodes or distant organs. This staging process is essential for creating an individualized treatment plan and may involve imaging techniques such as CT scans, MRIs, or PET scans.
Treatment: Medical and Surgical Approaches
The cornerstone of melanoma treatment is surgical excision. Typically, this involves removing the tumor along with a margin of healthy skin to ensure complete eradication. The procedure is performed under local, regional, or general anesthesia depending on the tumor’s size and location.
Where a sentinel lymph node turns out to be involved, removing the rest of the nodes in that basin — a completion lymph-node dissection — is no longer done routinely. Surveillance of the basin, combined with systemic treatment, is the usual course, and the decision is an individual one.
For regional or distant disease, systemic treatment has changed substantially, and chemotherapy is no longer the mainstay. Two approaches carry the weight now: immune checkpoint inhibitors, which release the brakes the tumour puts on the immune system, and molecularly targeted therapy for tumours that carry a susceptible mutation, identified by testing the tumour tissue. Radiotherapy has a role in particular situations, such as brain or bone metastases, and palliative surgery can relieve symptoms. Which treatment applies, and in what order, is decided by an oncologist on the basis of the stage and the tumour’s mutation profile.
It is important to note that superficial or minimally invasive procedures like laser therapy or cryodestruction are not considered adequate treatments for melanoma, even in its earliest stages. Such methods may leave malignant cells behind, leading to recurrence or metastasis.
Prevention: How to Minimize the Risk of Developing Melanoma
Preventing melanoma begins with proactive and mindful care of the skin. Key preventive strategies include:
- Avoiding excessive sun exposure, especially during peak UV hours (10 AM to 4 PM);
- Using broad-spectrum sunscreen with SPF 30 or higher daily, even on cloudy days;
- Wearing protective clothing, hats, and sunglasses when outdoors;
- Avoiding artificial tanning devices, such as tanning beds and sunlamps;
- Being vigilant about skin changes, including new moles or evolving lesions;
- Seeking professional skin checks annually or as recommended based on individual risk factors.
In addition, individuals with a personal or family history of melanoma, or those with multiple atypical moles, should consider periodic dermatoscopic monitoring. Early recognition and prompt removal of potentially dangerous lesions remains the most effective way to prevent the progression of melanoma to advanced stages.