
Keratoacanthoma (ICD-10: D23) 🚨
Keratoacanthoma
Keratoacanthoma is a rapidly growing, non-pigmented skin tumour that resembles squamous cell carcinoma both clinically and under the microscope. Calling it benign understates the problem: it cannot be reliably distinguished from a well-differentiated squamous cell carcinoma on either basis, and for that reason it is generally managed as a low-grade squamous cell carcinoma rather than as a harmless growth. Despite its malignant-like features, keratoacanthoma frequently undergoes spontaneous regression within several months of its initial appearance. This tumor usually arises in adulthood, predominantly after the age of 35–40 years, and is more common in men than in women.
Predisposing Factors
While no definitive cause has been identified for keratoacanthoma, several contributing factors are believed to increase the risk of its development. These predisposing factors include:
- Excessive Sun Exposure: Chronic or intense exposure to ultraviolet radiation (natural or artificial) is a significant risk factor, particularly in fair-skinned individuals.
Diagnosis
Diagnosis of keratoacanthoma is based on thorough clinical evaluation, which includes physical inspection of the lesion and dermatoscopic examination. Due to its striking similarity to basal cell carcinoma and especially squamous cell carcinoma, a biopsy is performed. It is worth knowing what a biopsy can and cannot settle here: a superficial sample may be inadequate, because the features that separate keratoacanthoma from an invasive squamous cell carcinoma lie at the base and the edge of the lesion. Adequate sampling takes in the central keratin crater together with the lesion’s edge and depth; a shallow shave can miss an invasive tumour altogether.
Clinical Presentation
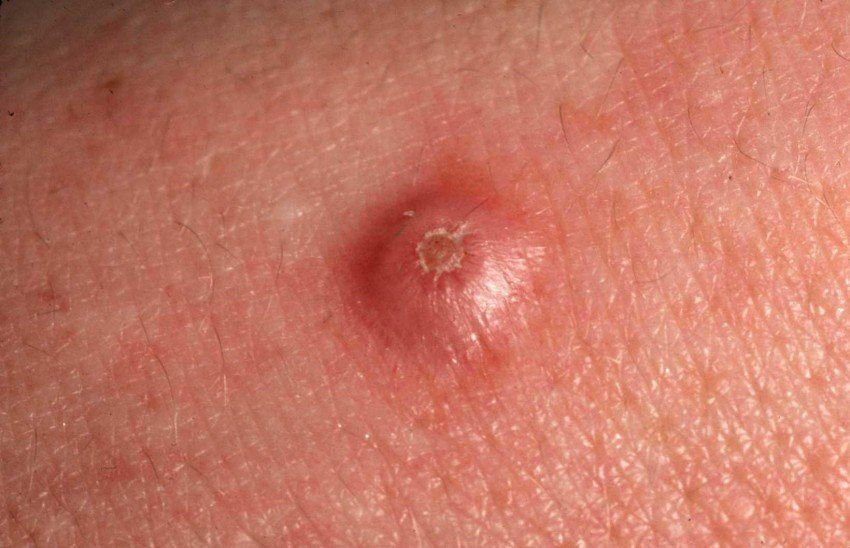
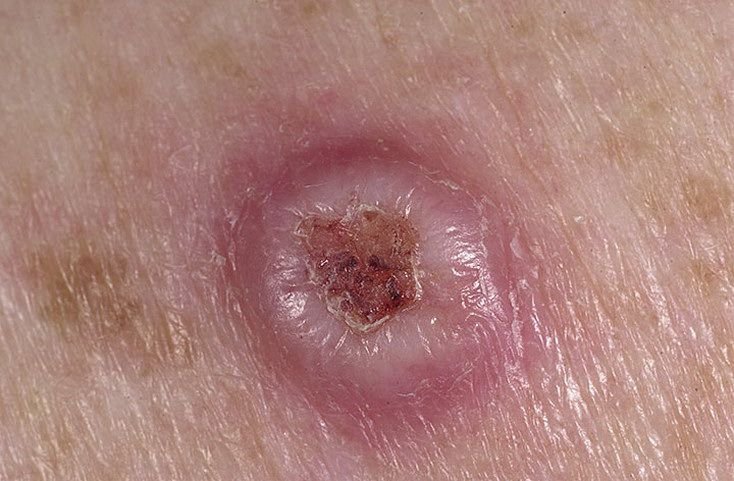
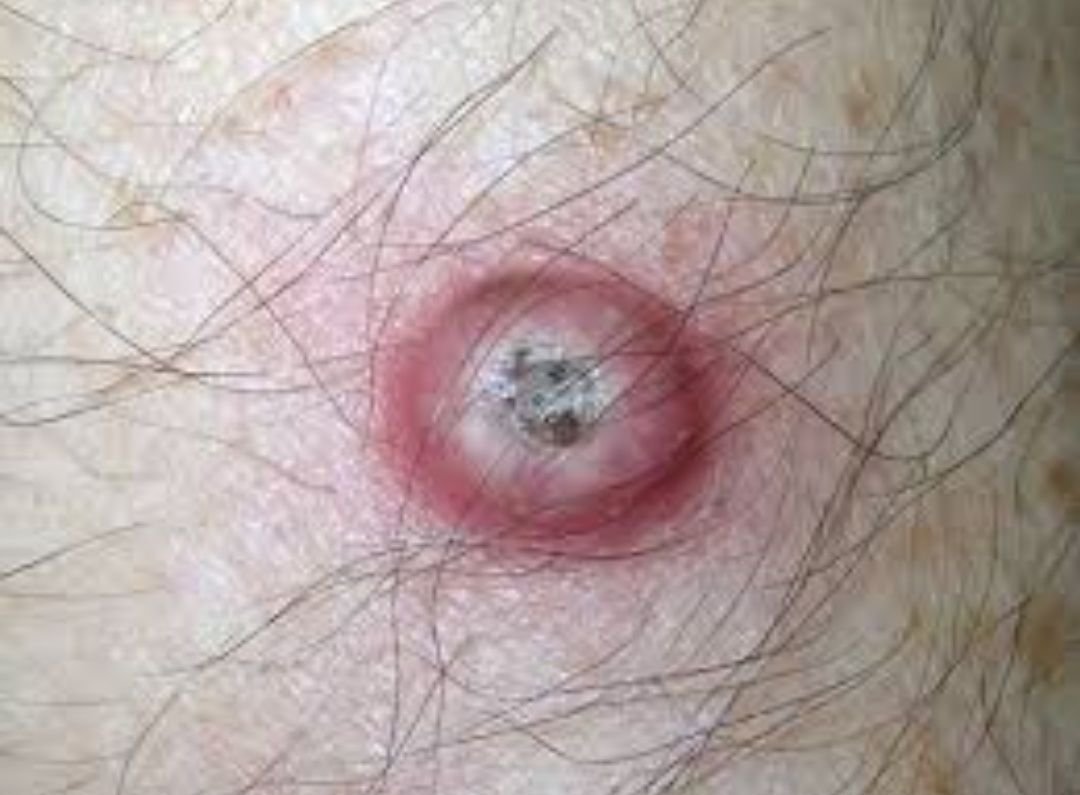
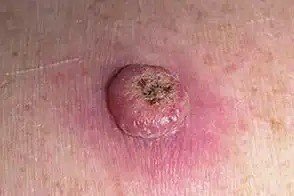
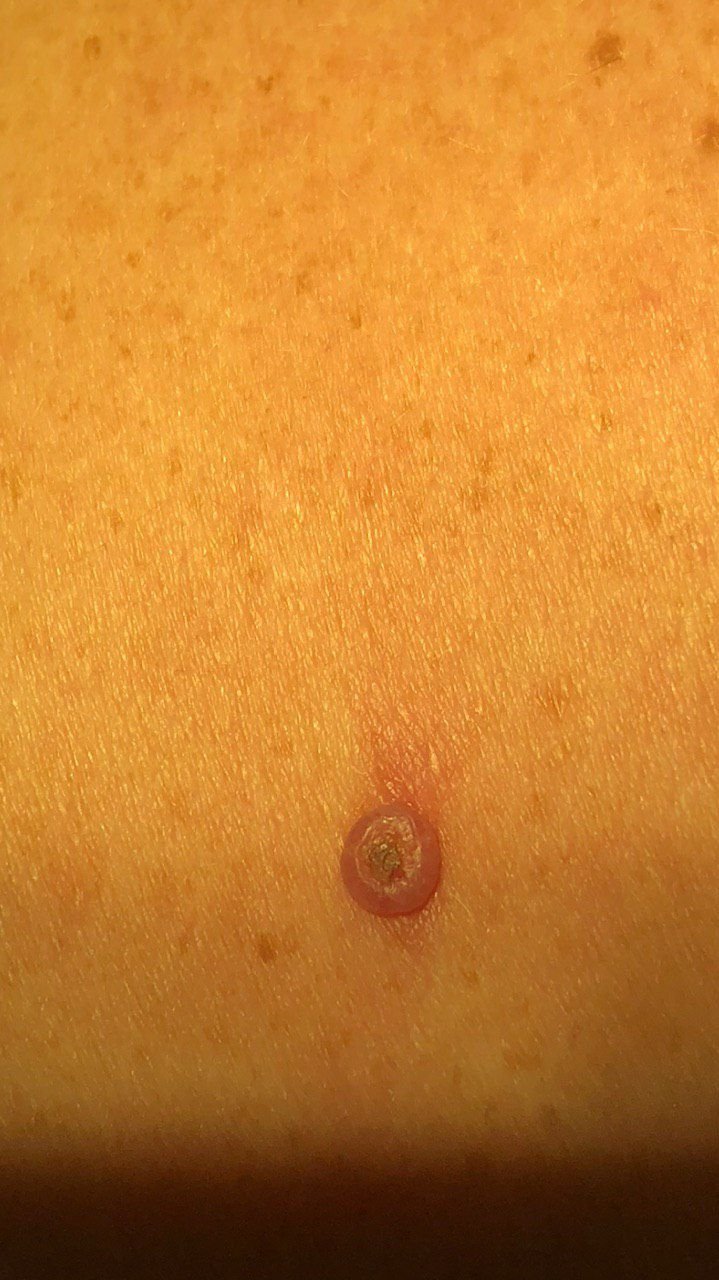
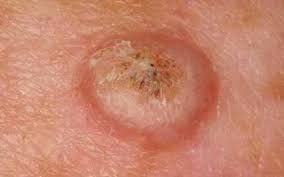
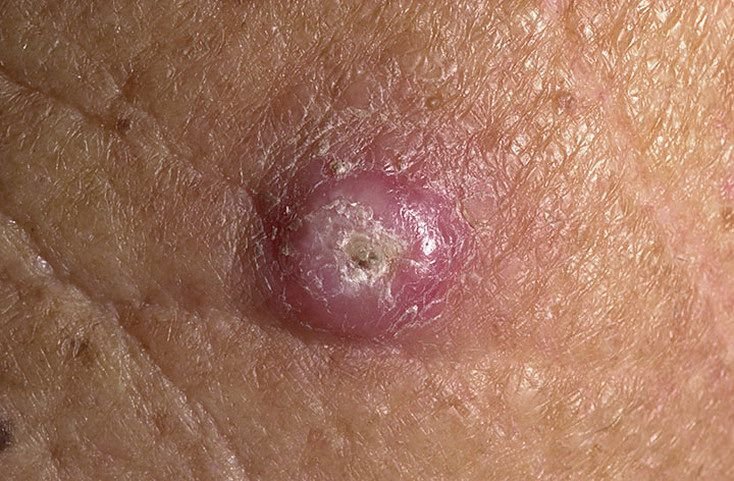
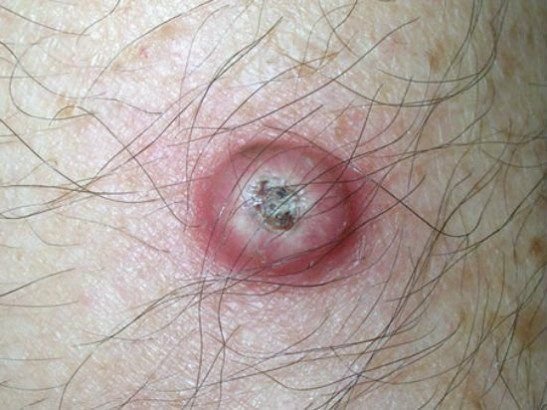
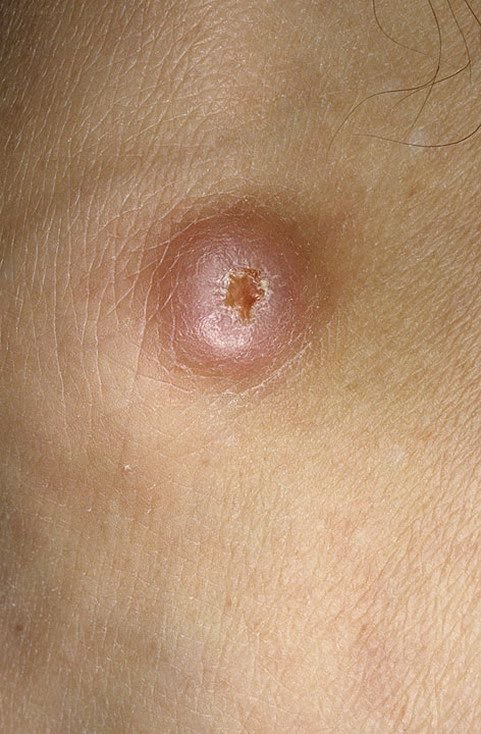
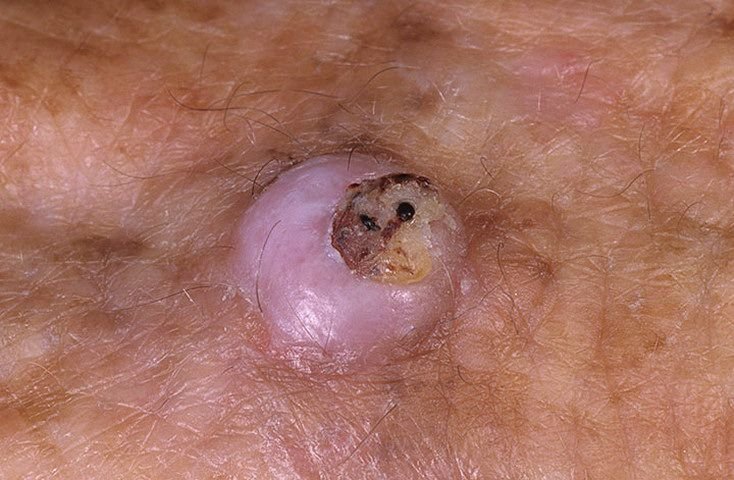
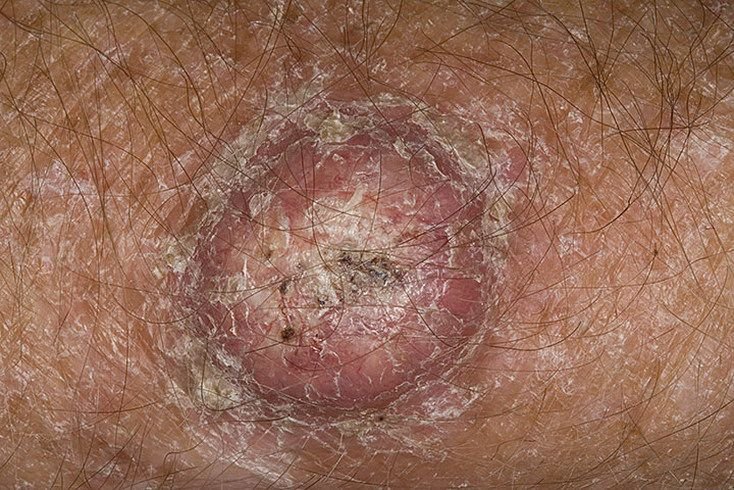
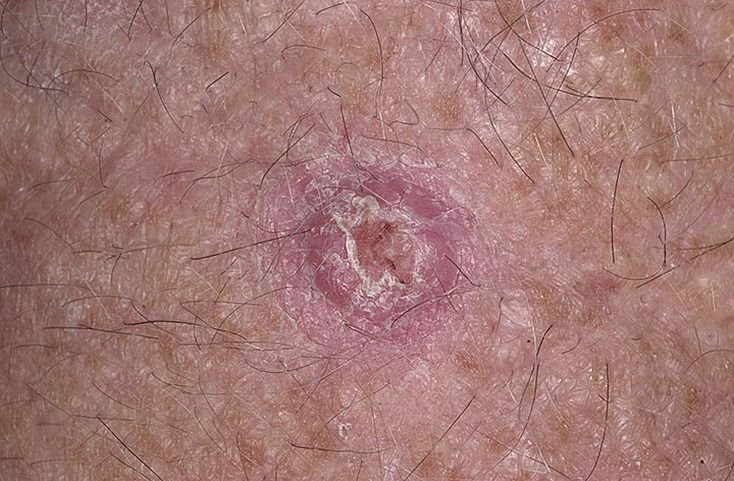
Keratoacanthoma often appears as a raised, dome-shaped lesion with a central crater or keratin-filled core. The peripheral surface is usually smooth and devoid of normal skin lines. In some cases, the center is ulcerated or crusted. The tumor may initially grow rapidly over weeks, reaching a size of 10–20 mm, after which growth typically slows. Lesions larger than 20 mm may develop bleeding or pain with minor trauma.
The borders of the lesion are usually symmetrical and regular, although some cases may show diffuse, ill-defined edges with surrounding erythema. The central area may appear grayish due to keratinization, while the periphery is often pink, red, or yellowish. Hair does not grow on the lesion’s surface. On palpation, the lesion feels firm yet mobile relative to deeper tissues. In smaller lesions, there are usually no subjective symptoms, but larger tumors may cause tenderness or discomfort.
Keratoacanthomas most frequently occur on sun-exposed areas of the body. Common sites include the forearms, hands, face, neck, back, and lower legs. Less commonly, lesions may arise on the chest, abdomen, or thighs.
Dermatoscopic Features
Dermatoscopic examination of keratoacanthoma may reveal the following features:
- Homogeneous Pink Peripheral Coloration: A uniform pink background in the periphery of the lesion.
- Whitish-White Annular Zone: Surrounding the central core, this ring-like zone reflects keratin-filled tissue.
- Central Keratin Plug: A hallmark of keratoacanthoma, seen as yellowish or grayish masses of keratin in the center.
- Blood Clots or Hemorrhagic Spots: Common in larger tumors or those subject to trauma.
- Peripheral Vascular Patterns: Linear, hairpin, or radially oriented vessels in the surrounding tissue.
Differential Diagnosis
Keratoacanthoma must be distinguished from several other dermatologic conditions, some of which are malignant. These include:
- Cutaneous horn
- Dermatofibroma
- Open comedone (blackhead)
- Seborrheic keratosis
- Bowen’s disease
- Squamous cell carcinoma
- Basal cell carcinoma
- Melanoma (especially amelanotic variants)
Risks and Prognosis
Although keratoacanthoma is generally benign and may undergo spontaneous regression, it is generally managed as a lesion that can be difficult to distinguish from squamous cell carcinoma. The reason to treat a keratoacanthoma is not that it may turn into something else. It is that a keratoacanthoma cannot be reliably told apart from a squamous cell carcinoma clinically, so the lesion is removed both to establish what it is and to prevent it destroying local tissue while that question remains open.
Furthermore, individuals with a history of keratoacanthoma may have an elevated risk of developing other skin cancers elsewhere on the body. This necessitates careful follow-up and regular skin examinations to ensure early detection and differentiation of new lesions.
Management and Clinical Strategy
Upon suspicion or confirmation of keratoacanthoma, referral to a dermatologist or oncologist is recommended. Due to its clinical resemblance to invasive carcinomas, histological confirmation is essential. Even with a confirmed benign diagnosis, surgical excision is generally recommended due to the potential for growth, discomfort, bleeding, and malignant transformation.
If surgery is declined, the patient must undergo active dynamic observation, including photographic documentation of the lesion to monitor for subtle changes. Monitoring is especially important for tumors exceeding 20 mm or those that exhibit new symptoms.
How often someone should be examined afterwards depends on their history of skin cancer, their risk factors, and whether new or changing lesions appear. There is no fixed interval, and no particular season, that applies to everyone; full-body skin mapping is not needed routinely. Mapping remains a reasonable option for someone at high risk — a patient with many atypical or dysplastic nevi, or with a previous melanoma — where it is decided individually.
Treatment
The gold-standard treatment is surgical excision with a margin of healthy tissue, ensuring complete removal and minimizing recurrence risk. Excision should be full-thickness to capture the entire lesion.
Flat plane excision or superficial removal techniques are discouraged, as they increase the chance of recurrence. Similarly, methods such as laser ablation or cryodestruction are not recommended for keratoacanthoma due to poor histological control and a higher rate of local relapse.
Prevention
Preventive strategies aim to reduce the likelihood of developing keratoacanthoma and limit environmental and physical insults to the skin:
- Limit sun exposure and avoid artificial UV sources like tanning beds.
- Use broad-spectrum sunscreens and wear protective clothing during sun exposure.
- Prevent chronic trauma or mechanical irritation to the skin.
- Practice good skin hygiene and regularly inspect the skin for changes.
- Undergo periodic dermatological evaluations to detect potentially malignant lesions early.
Early identification and timely management are critical to minimizing complications and improving outcomes in patients with keratoacanthoma.

Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)