
Wart Plantar (ICD-10: B07) ⚠️
Plantar Wart (Verruca Plantaris): A Common Viral Neoplasm of the Foot
Overview
Plantar warts, also referred to as verruca plantaris, are benign skin tumors of viral origin that typically develop on the weight-bearing surfaces of the feet. Caused by specific strains of the human papillomavirus (HPV), they are most frequently diagnosed in children and adolescents, affecting up to 10% of this population. These warts are distinct for their deep location, keratinized surface, and frequent resistance to treatment, especially in older individuals.
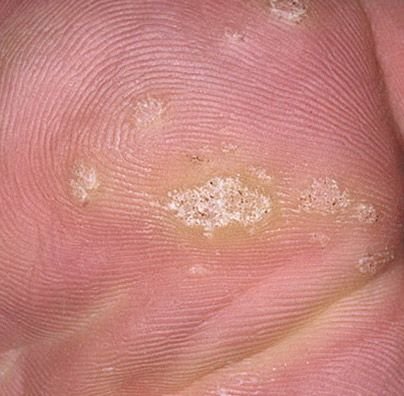
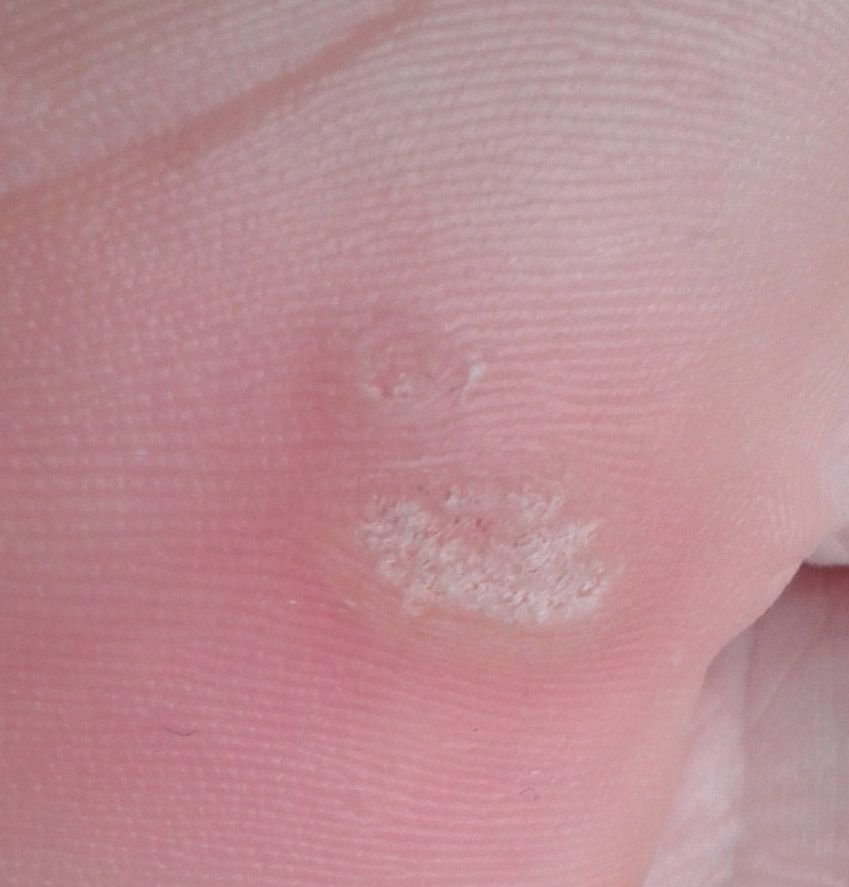
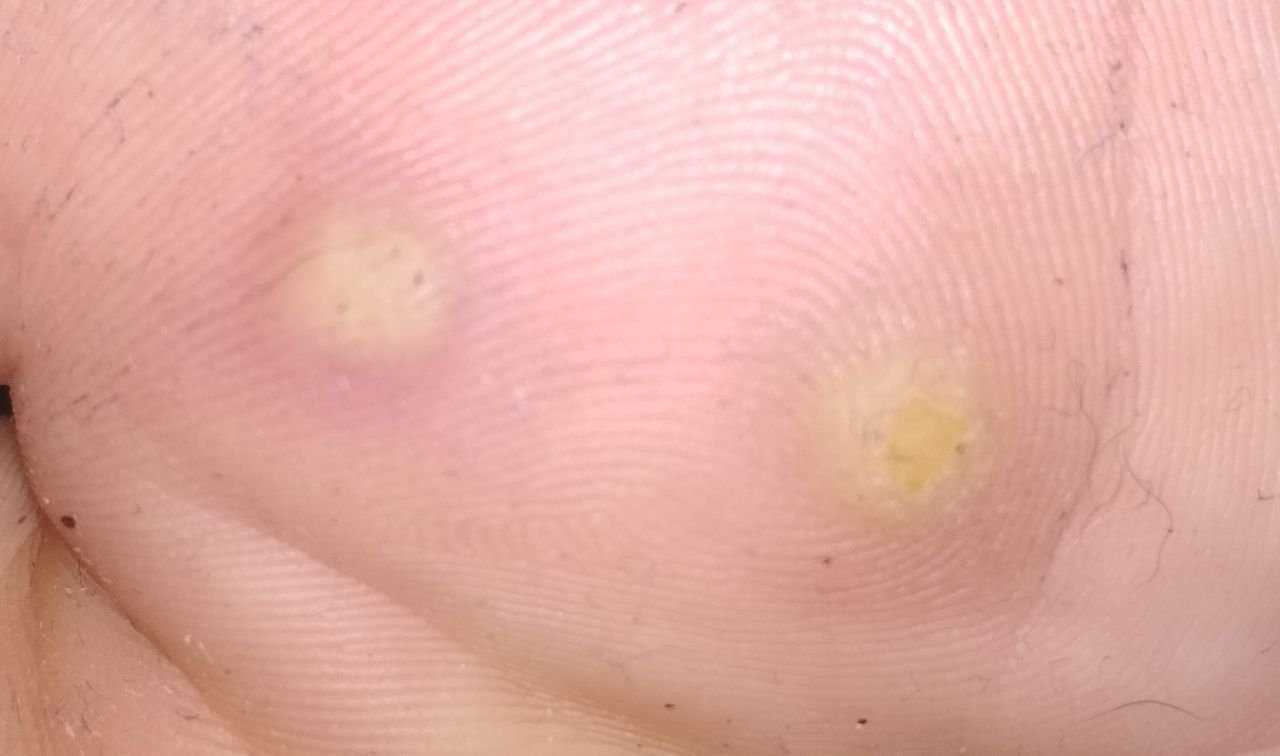
Plantar warts often appear singly but can also occur in clusters or merge into large mosaic lesions. Due to the pressure from walking, these warts may grow inward rather than outward, making them painful when walking or standing for long periods. This distinguishes them from warts in other locations, which are usually asymptomatic.
Predisposing Factors and HPV Transmission
The underlying cause of plantar warts is infection with HPV, typically low-risk cutaneous types such as HPV 1, 2, 4, or 57. Despite the high global prevalence of HPV (up to 90% of the adult population may be carriers), only a subset of individuals develop visible warts, highlighting the importance of additional predisposing factors for clinical manifestation.
These factors include:
- Exposure to HPV through direct contact or a contaminated surface: Walking barefoot in public showers, changing rooms, gyms and around swimming pools is the classic route;
- Entry through minor breaks in the skin: Micro-tears from walking barefoot, tight shoes or heavy physical activity give the virus a way in;
- Softened skin: Feet that stay damp inside shoes, or skin softened by prolonged wet exposure, are easier for the virus to penetrate;
- Immunosuppression: Immunosuppressive therapy, HIV infection or organ transplantation make plantar warts more numerous and considerably harder to clear;
- Autoinoculation: Picking at a wart, or shaving and filing it, spreads virus to nearby skin and can produce the mosaic pattern of many small warts.
Transmission occurs via direct skin contact with viral particles or indirectly via contact with infected surfaces. The virus penetrates the skin through minor abrasions and settles in the basal layer of the epidermis, where it triggers the abnormal proliferation of keratinocytes.
Diagnosis of Plantar Warts
The diagnosis of plantar warts is based on clinical evaluation, considering lesion appearance, location, and patient symptoms. Due to the thick keratin layer and pressure from body weight, plantar warts may resemble calluses or corns.
Additional diagnostic approaches include:
- Dermatoscopy: Enables identification of characteristic vascular patterns and keratin plugs;
- HPV DNA testing: Not needed for recurrent or atypical plantar warts; the viral subtype does not alter management;
- Histological examination: Performed if malignancy is suspected or to confirm the diagnosis in refractory lesions.
Symptoms and Clinical Features
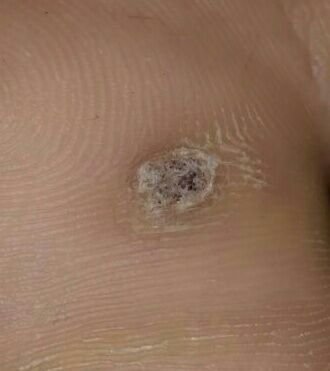
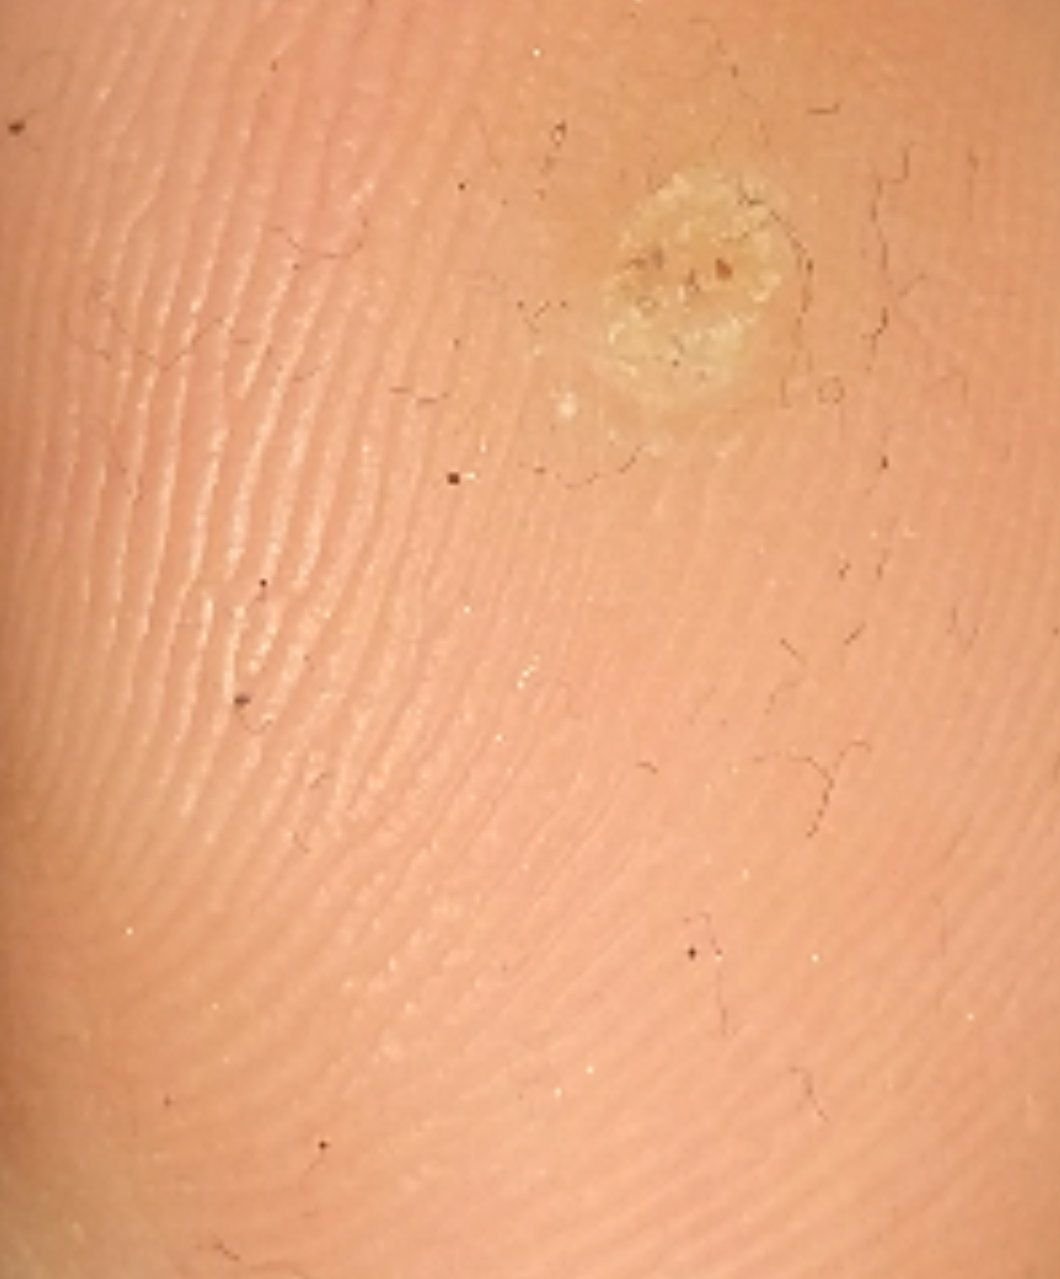
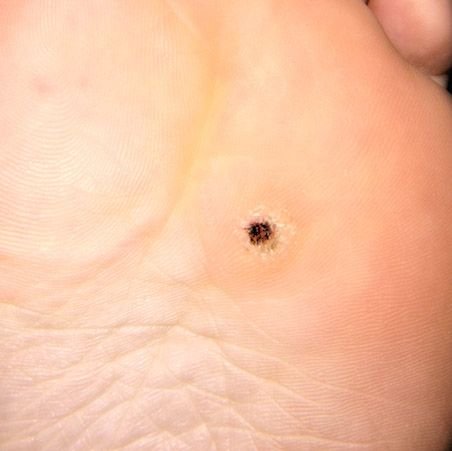
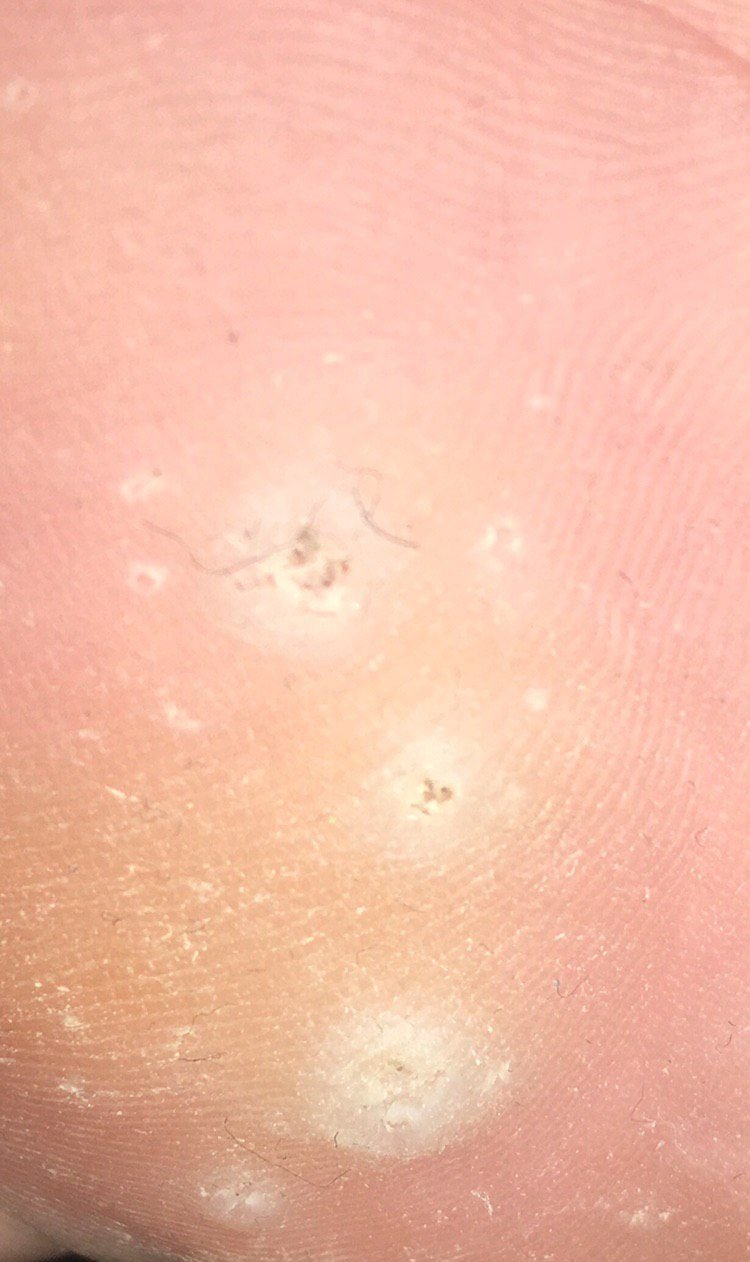
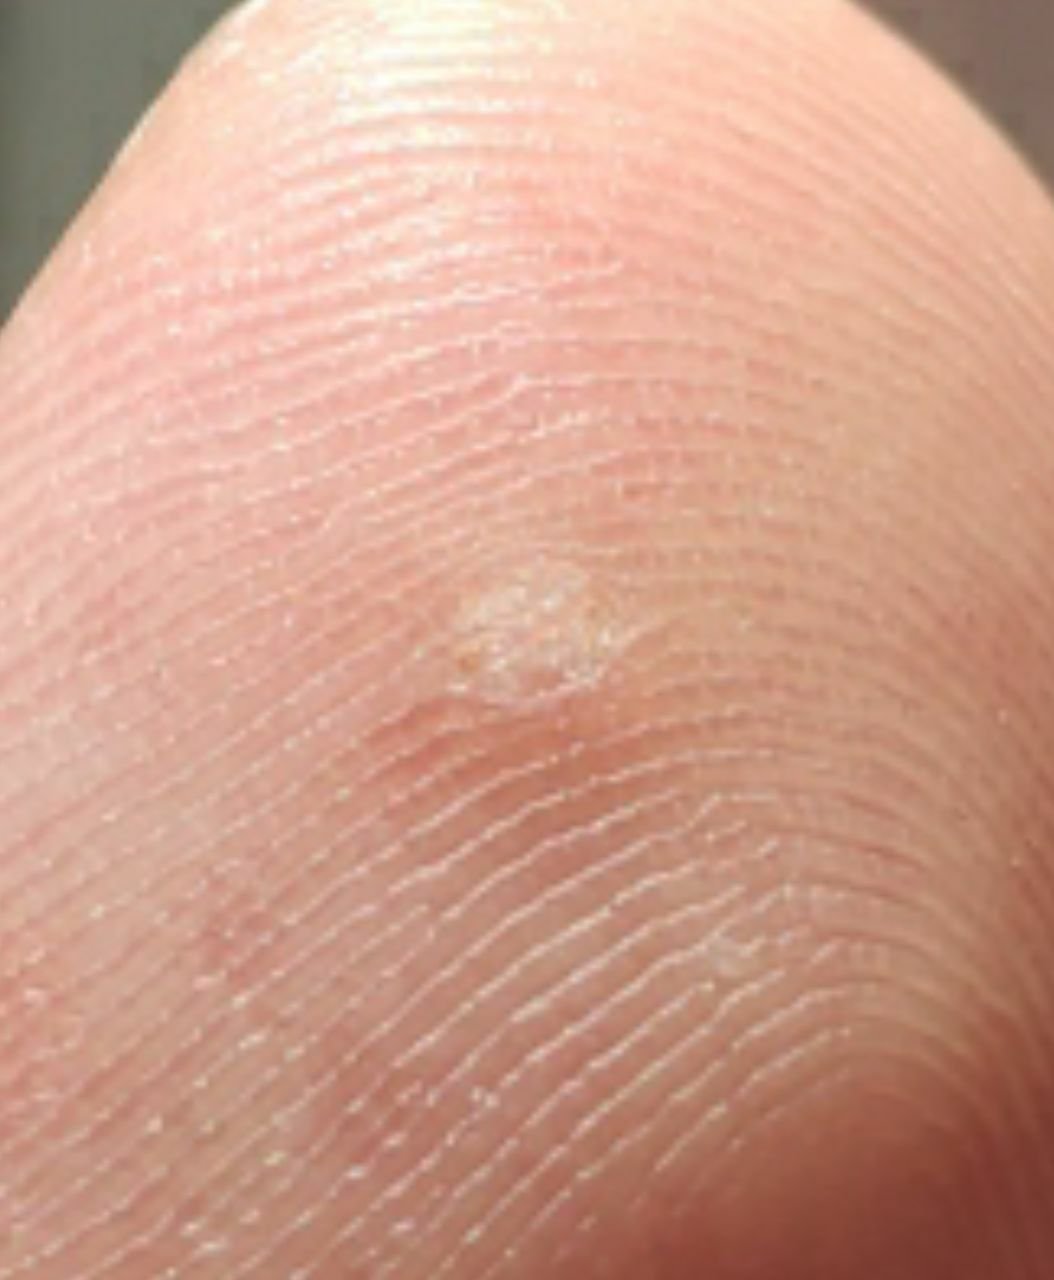
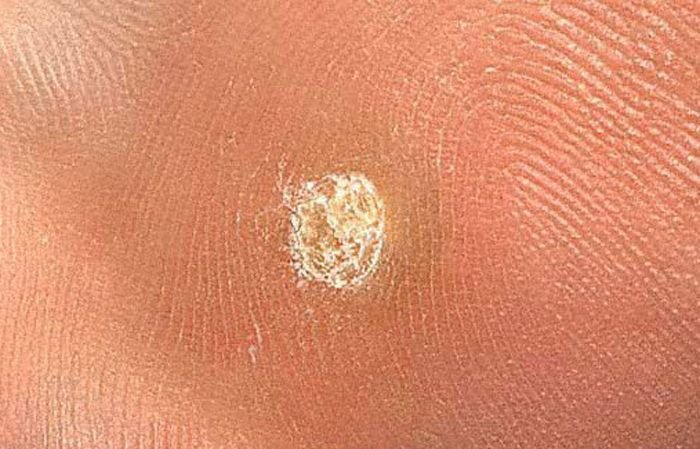
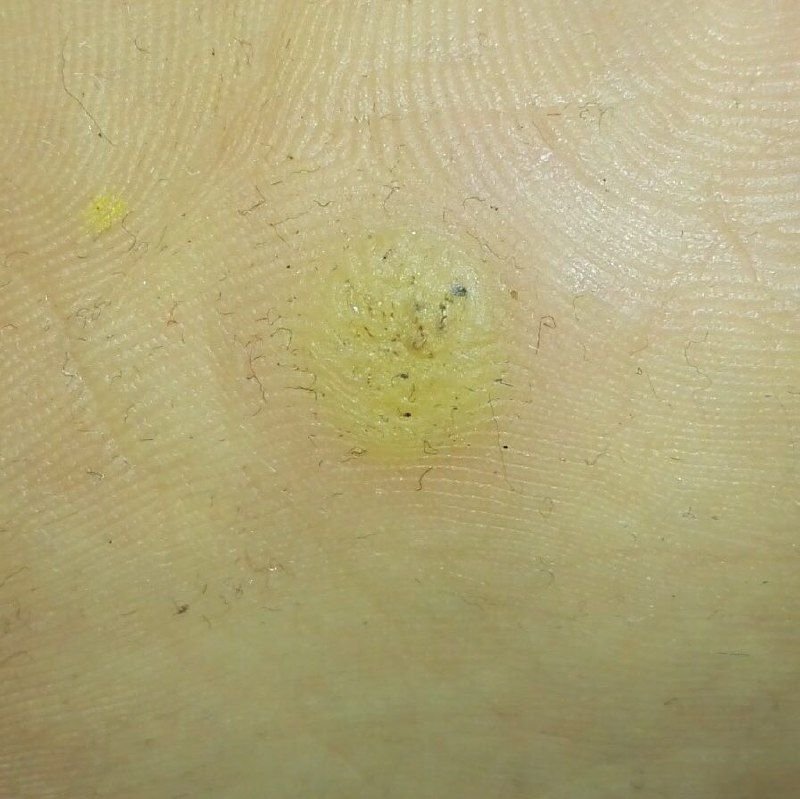
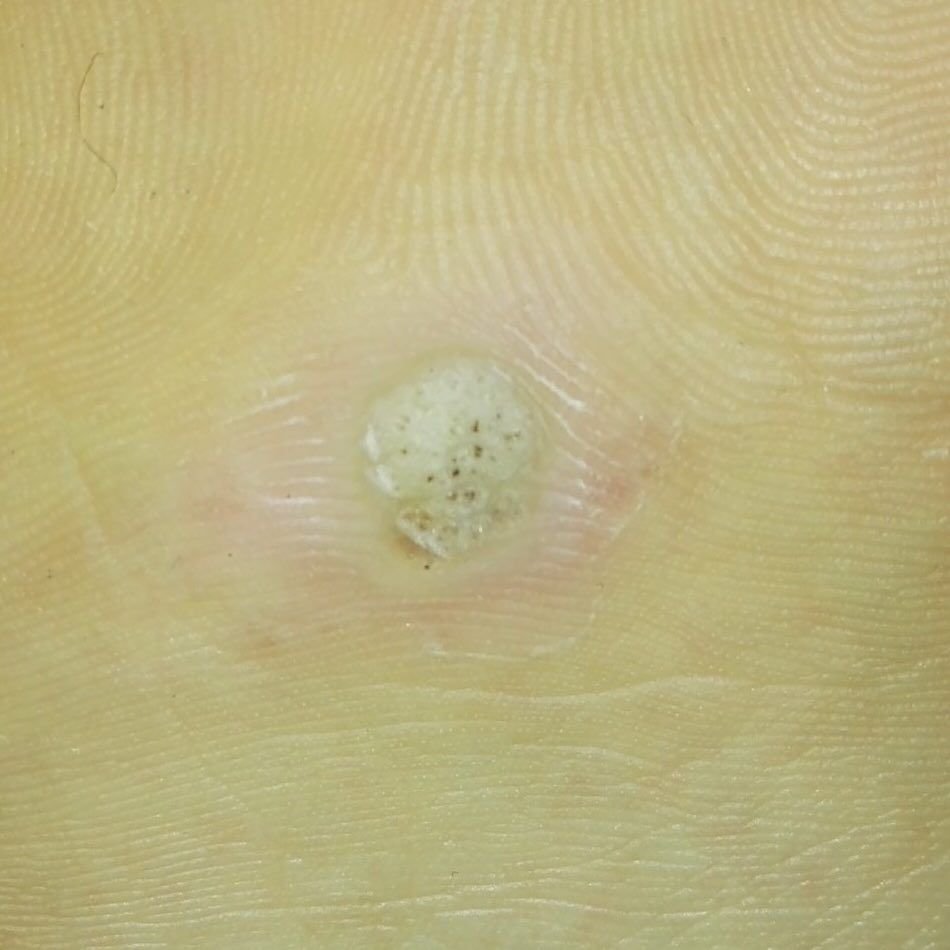
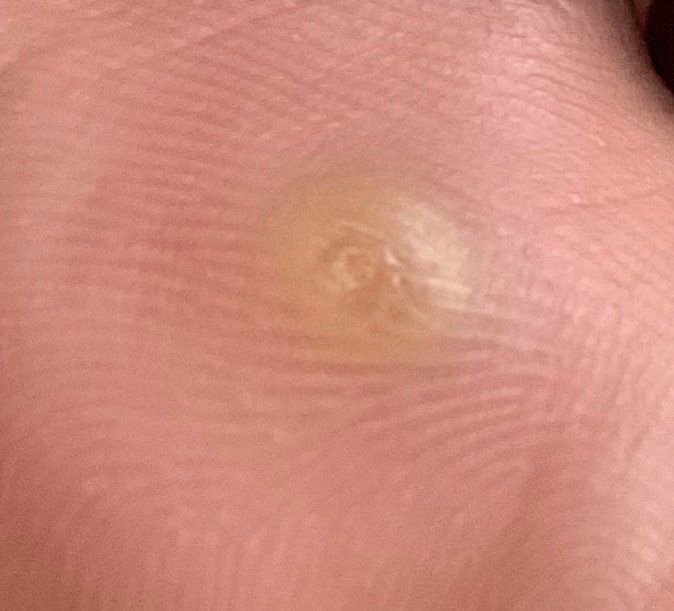
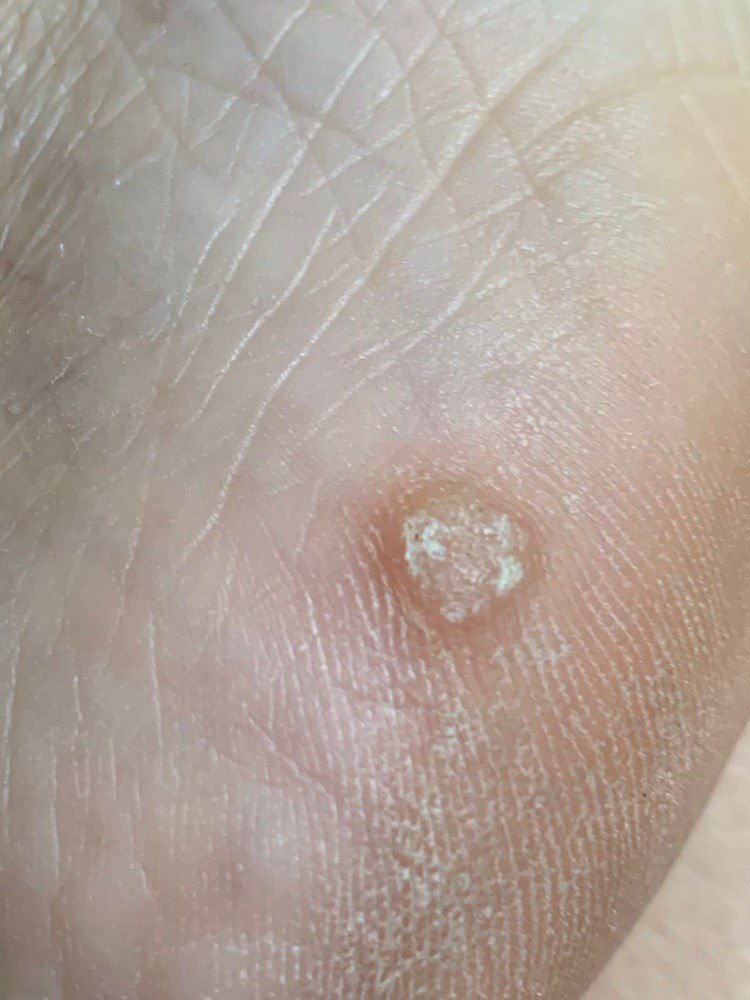
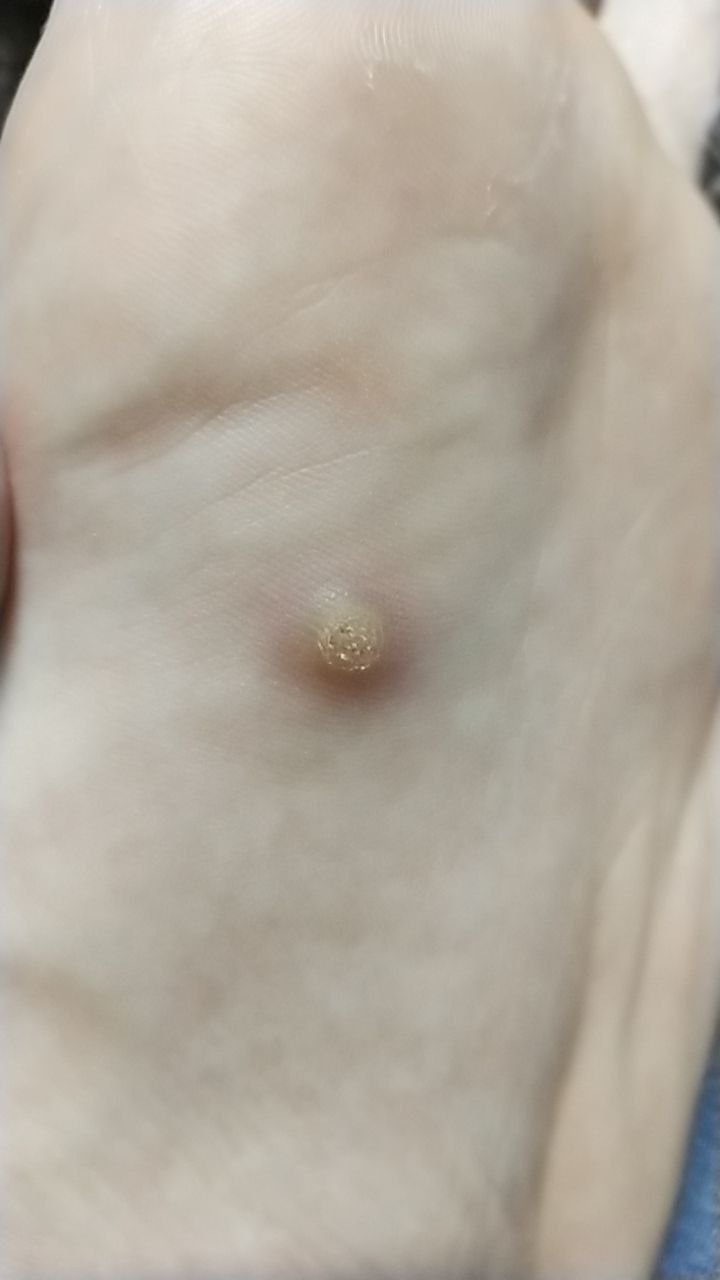
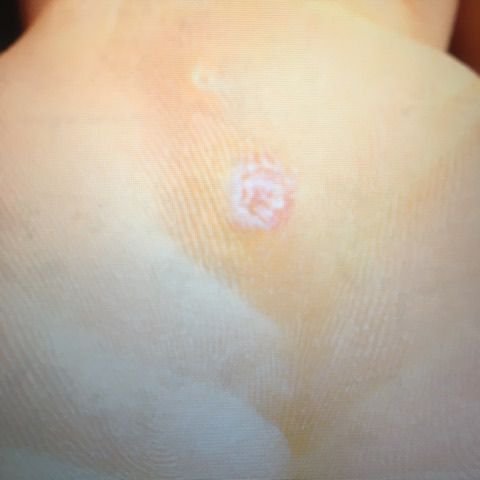
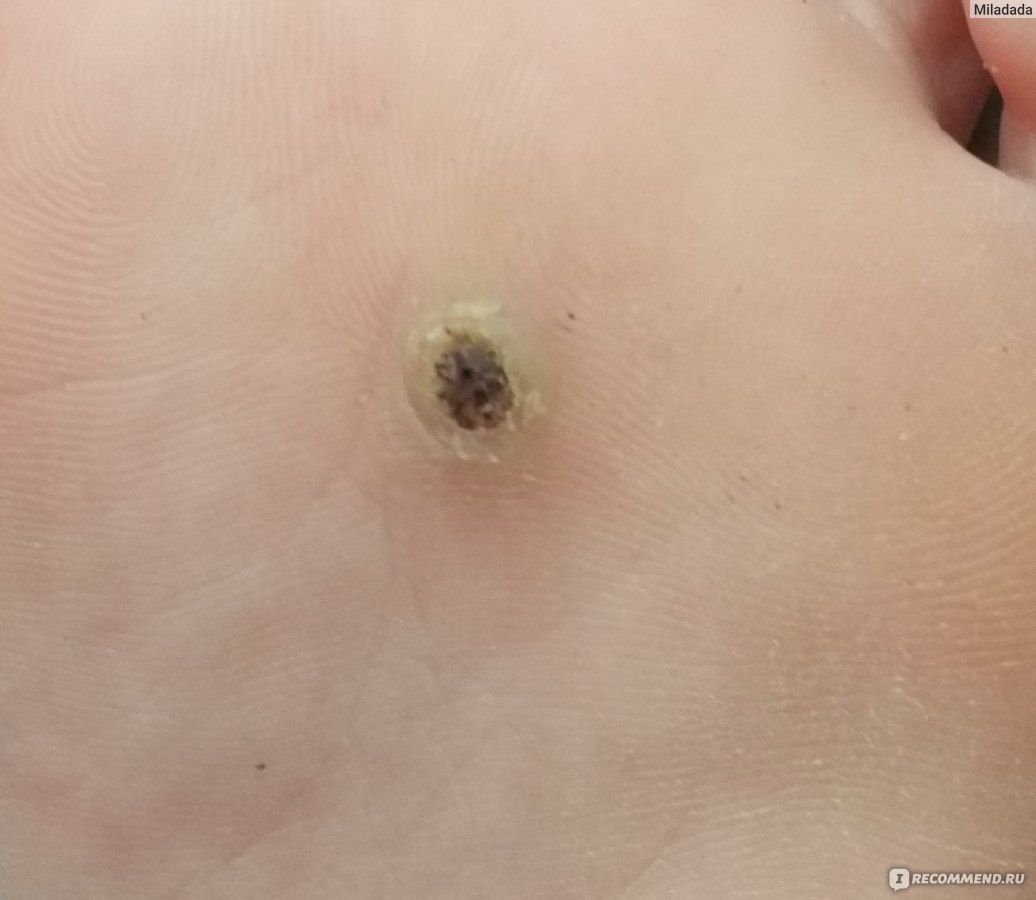
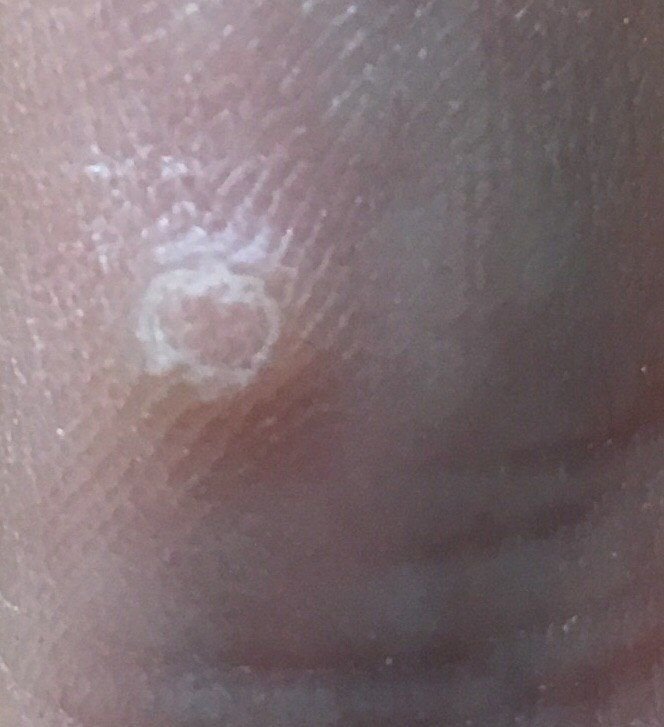
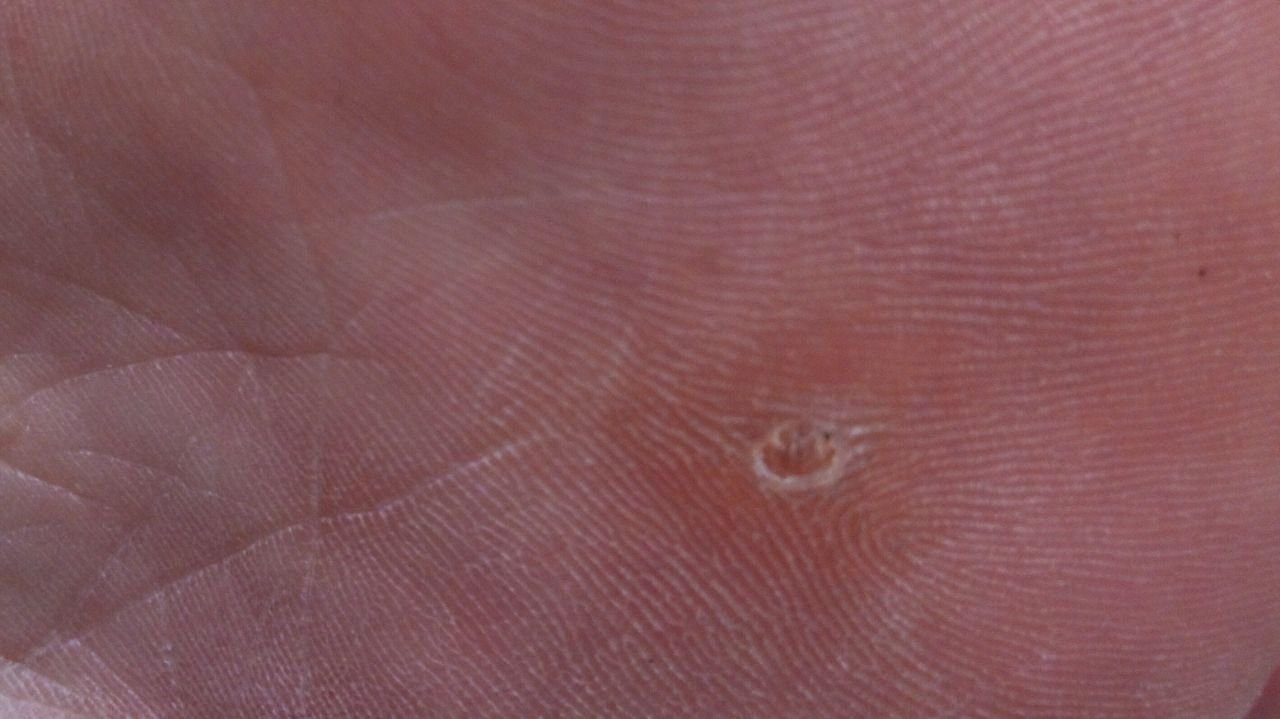
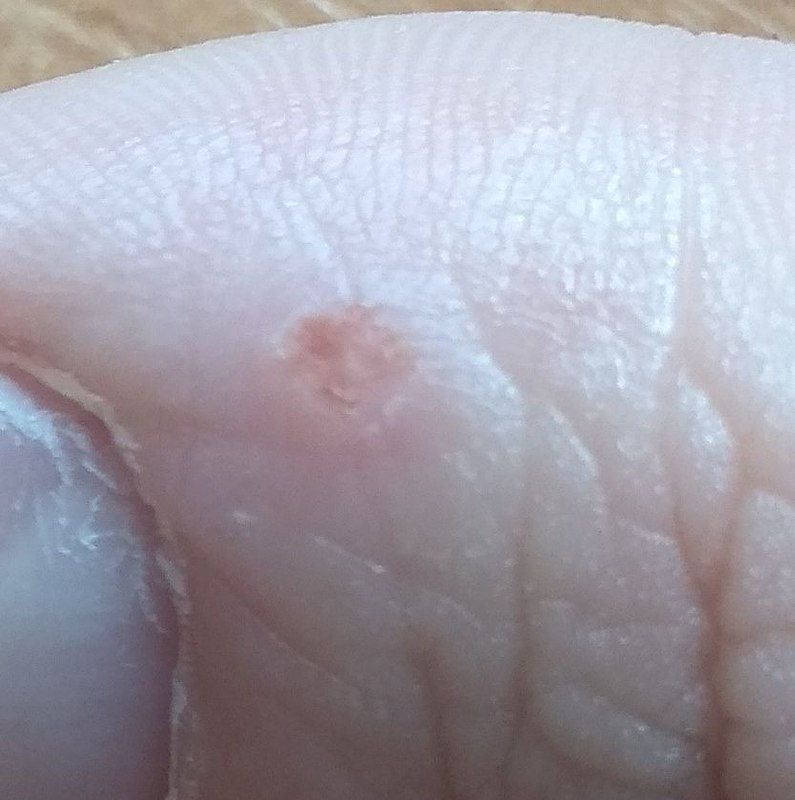
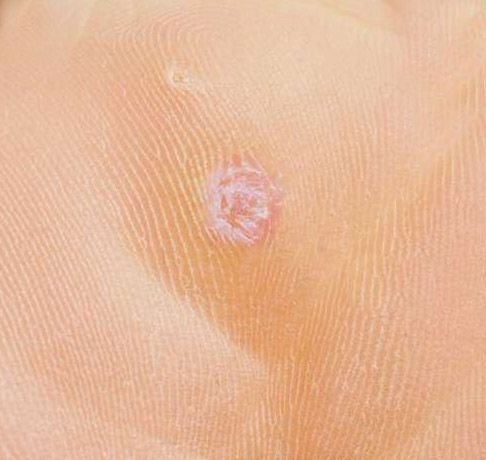
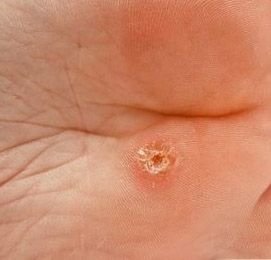
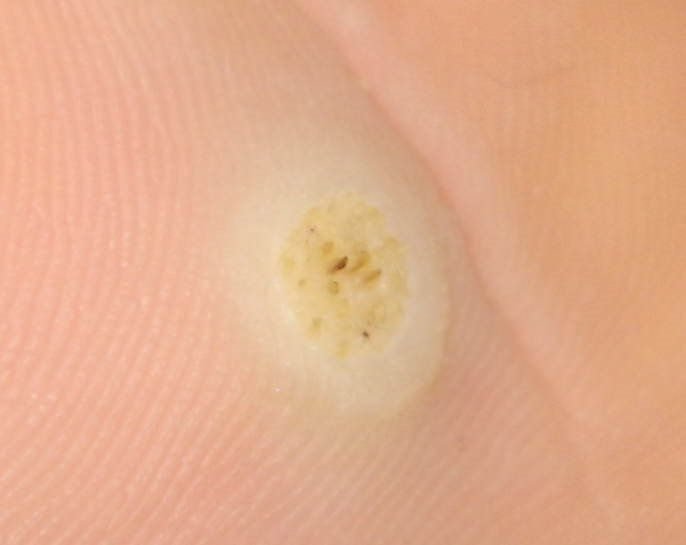
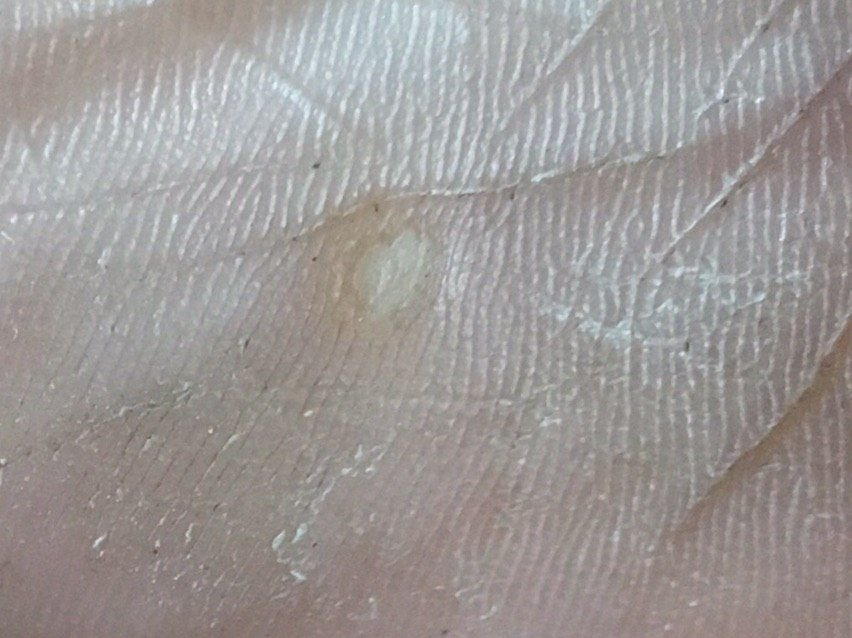
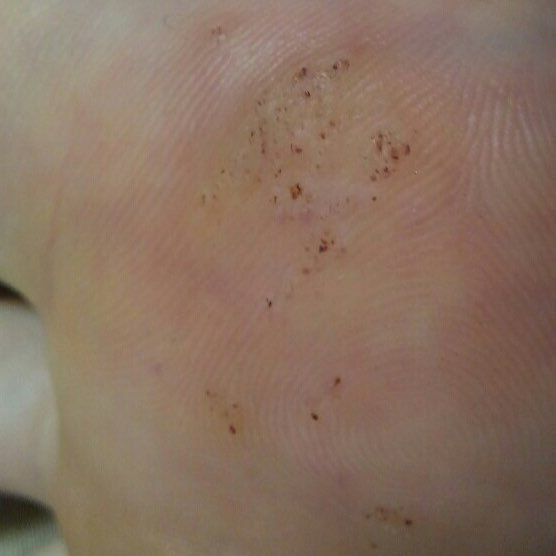
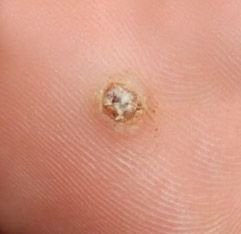
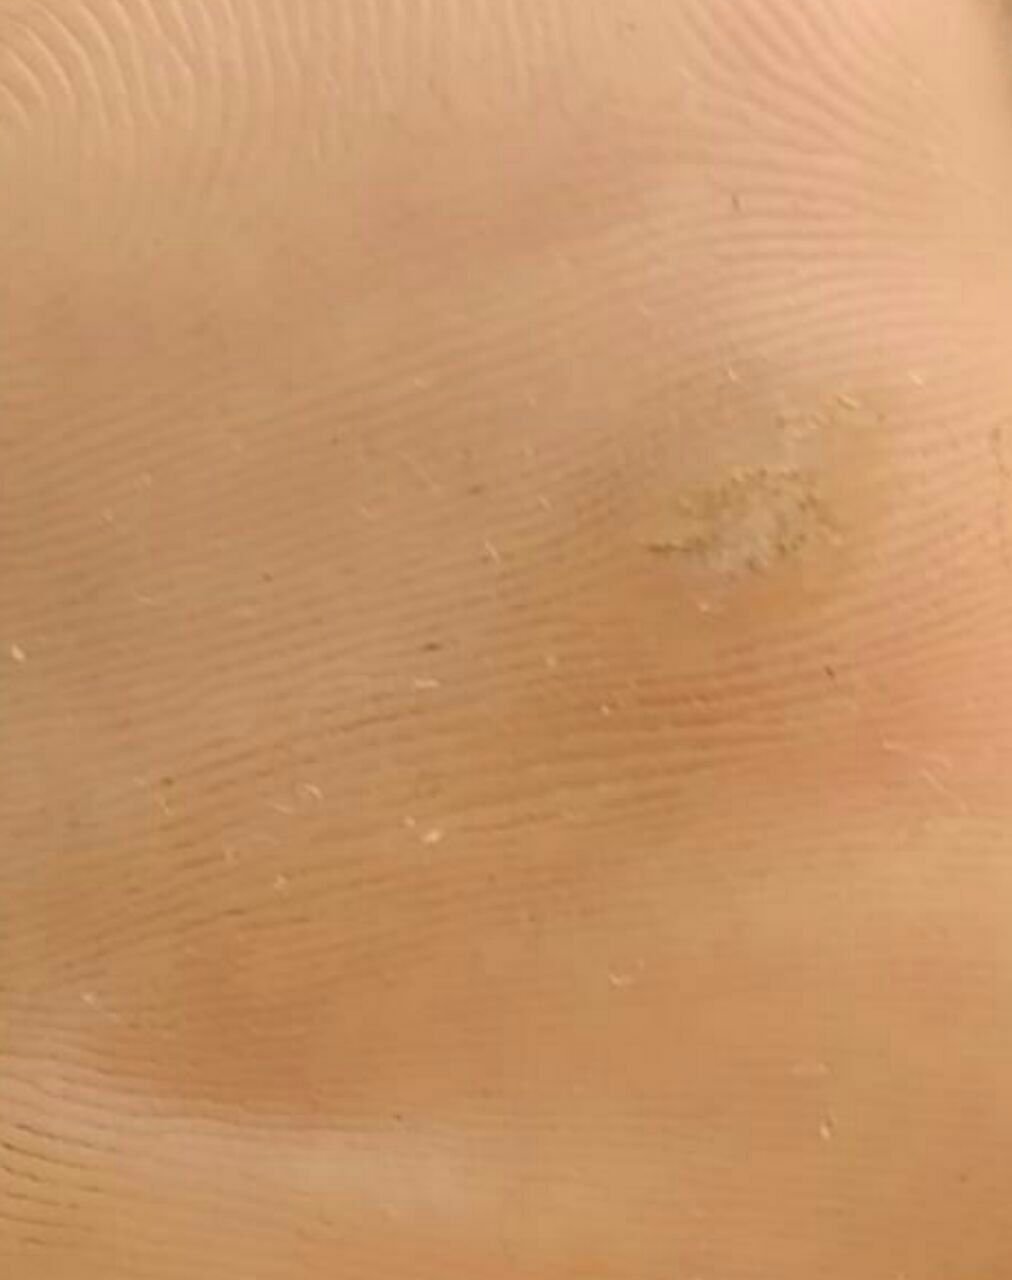
Plantar warts appear as flat or slightly elevated lesions with a rough, thickened surface and often a keratin plug at the center. Their growth is often directed inward due to pressure from standing and walking.
Clinical characteristics include:
- Location: Soles of the feet, especially weight-bearing areas like the heel or forefoot;
- Size: Typically 2–5 mm in diameter; larger lesions may result from confluence of multiple warts;
- Surface: Coarse, with fine papillae or papillary ridges, often with visible thrombosed capillaries;
- Color: Flesh-colored, pale, or grayish, depending on keratin content and age of lesion;
- Margins: Well-defined with a keratinized border separating the lesion from healthy skin;
- Symptoms: Pain or tenderness when walking, pressure sensitivity, and possible tingling or discomfort.
Dermatoscopic Description
Dermatoscopy is an invaluable tool for differentiating plantar warts from other keratotic lesions. Classic findings include:
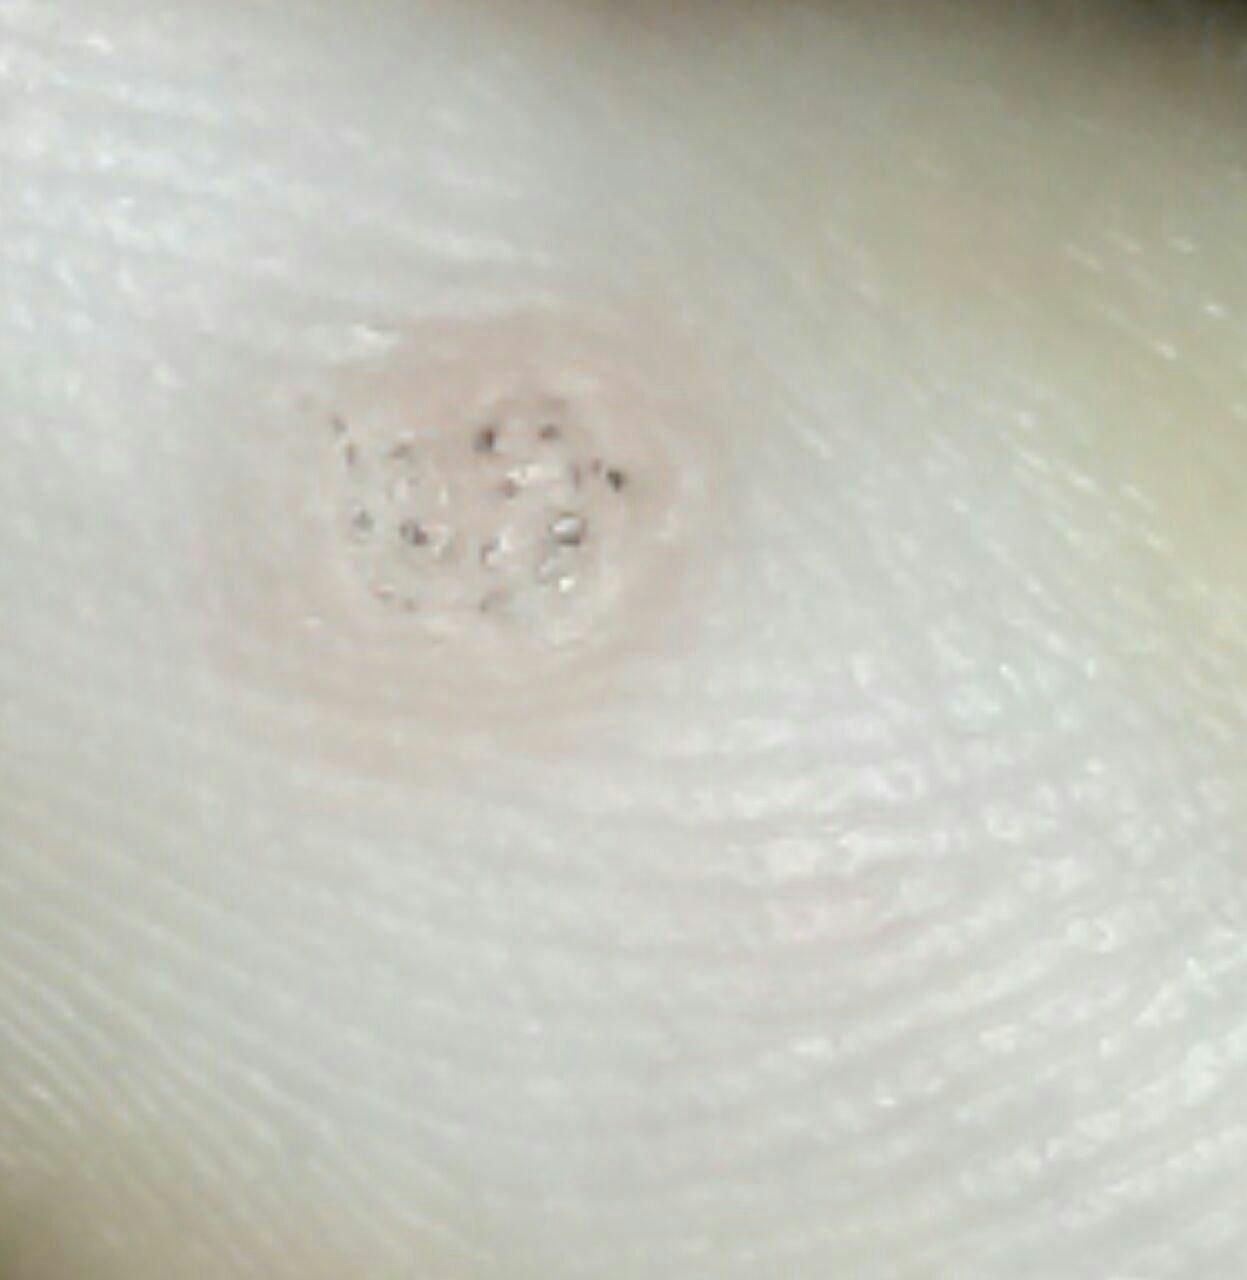
- “Frogspawn” pattern: Clustered papillae each surrounded by a white keratin ring and containing a central red or black dot (capillary loop or thrombosed vessel);
- Punctate red or black dots: Thrombosed capillaries, the most useful positive finding, and what is left behind when the overlying keratin is pared away;
- Interruption of the normal skin lines: A plantar wart pushes the dermatoglyphic ridges aside, whereas a callus or corn leaves them running across the lesion. This is the single most helpful way to tell them apart;
- Yellowish structureless zones: Caused by hyperkeratosis from weight-bearing pressure.
These features help differentiate plantar warts from corns, calluses, seborrheic keratoses, and pigmented lesions.
Differential Diagnosis
Plantar warts must be differentiated from other skin lesions on the soles of the feet, as their appearance can mimic several common and uncommon conditions. Important differential diagnoses include:
- Corn (clavus): Central core surrounded by keratin; lacks vascular puncta and is usually less painful on side pressure;
- Callus: Diffuse thickening of the stratum corneum without central vessels or pain on vertical pressure;
- Flat wart: Smooth surface, smaller size, often found on the face or hands;
- Common wart: More raised, rougher surface, typically found on hands or periungual areas;
- Dermatofibroma: Firm, hyperpigmented lesion with a “dimple sign” when squeezed laterally;
- Pigmented nevus: Stable, symmetrical pigmented lesion; may need biopsy if change is observed;
- Molluscum contagiosum: Central umbilicated papules with a pearly appearance, more common in children;
- Amelanotic melanoma: Rare, but must be ruled out in rapidly changing or atypical plantar lesions.
Risks and Clinical Implications
Plantar warts are considered non-cancerous and carry no inherent oncogenic risk under normal conditions. However, certain clinical scenarios may warrant closer observation, particularly when:
- The lesion changes rapidly in shape, color, or texture;
- Pain worsens or bleeding occurs without trauma;
- The wart recurs quickly after removal or spreads to nearby areas;
- The patient has a known immunosuppressive condition.
Additional concerns include:
- Physical discomfort: Pain during ambulation or exercise can reduce mobility and affect quality of life;
- Injury and bleeding: Constant pressure increases the risk of skin breakdown and secondary bacterial infection;
- Psychological stress: Visibility, especially in multiple lesions, may cause self-consciousness or embarrassment;
- Immune dysfunction: Multiple or recalcitrant lesions may reflect reduced immune control over HPV infection.
Tactics: Monitoring and Clinical Management
Where plantar warts are asymptomatic and do not interfere with walking, leaving them alone is reasonable, and no fixed schedule of dermatological screening is required. Many resolve in time, and treatment on the sole is often uncomfortable and slow.
Patients should promptly consult a dermatologist if:
- Lesions become painful, ulcerated, or increase in number;
- There is trauma, bleeding, or recurrent infection in the wart area;
- They are immunocompromised or have a history of skin malignancy;
- The wart causes gait disturbances, occupational difficulty, or psychological distress.
In such cases, the dermatologist will determine whether to proceed with removal or to continue observation. Routine photographic tracking and lesion mapping are not needed for plantar warts.
Treatment of Plantar Warts
The choice of treatment depends on lesion size, number, location, patient age and pain. It is worth knowing from the outset that plantar warts are the most treatment-resistant of the common warts, that several courses are often needed, and that treatment itself can be painful on a weight-bearing surface. Established options are:
- Topical salicylic acid: The established first choice. Applied daily over weeks to months, after soaking the foot and paring the hard skin back, it needs persistence more than anything else;
- Cryotherapy: Freezing with liquid nitrogen, repeated every two to three weeks. Effective but sore afterwards, which matters on a sole that has to be walked on;
- Observation: Entirely reasonable for a wart that is not painful, since many clear without treatment;
- Laser, radiofrequency surgery or electrocoagulation: Selected resistant cases only, not preferred first-line options. A scar on a weight-bearing part of the sole can hurt more, and for longer, than the wart did;
- Surgical excision: Reserved for diagnostic uncertainty. Histology is recommended for all excised lesions.
Patients with diabetes, peripheral neuropathy or impaired circulation in the feet should not use destructive treatments or strong acid preparations without supervision, and are best assessed by a clinician experienced in foot care: a minor self-inflicted wound on a foot with reduced sensation or poor blood supply can become a serious ulcer.
Self-treatment is discouraged due to risk of incomplete removal, infection, bleeding, and difficulty distinguishing benign from malignant growths.
Prevention of Plantar Warts
Effective prevention of plantar warts involves protecting the skin, controlling HPV exposure, and maintaining immune health. Key measures include:
- Wearing protective footwear: Especially in public showers, locker rooms, and pool areas;
- Practicing foot hygiene: Keep feet clean and dry, and change socks regularly;
- Disinfecting personal items: Do not share towels, shoes, or nail clippers;
- Avoiding trauma: Choose properly fitting shoes and use insoles if needed;
- Not picking, cutting or shaving lesions, which spreads the virus across the sole and risks infection;
- Covering a wart with a waterproof plaster for swimming or communal showers, and not walking barefoot in those places.
With prompt attention, safe treatment methods, and preventive care, plantar warts can be effectively controlled—minimizing recurrence, discomfort, and viral transmission risk.


Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)