Pyogenic Granuloma (ICD-10: L98) ⚠️
Pyogenic Granuloma (Telangiectatic Granuloma, Botriomycoma, Granulation Tissue-type Hemangioma, Lobular Capillary Hemangioma, Eruptive Angioma, Inflammatory Hemangioma)
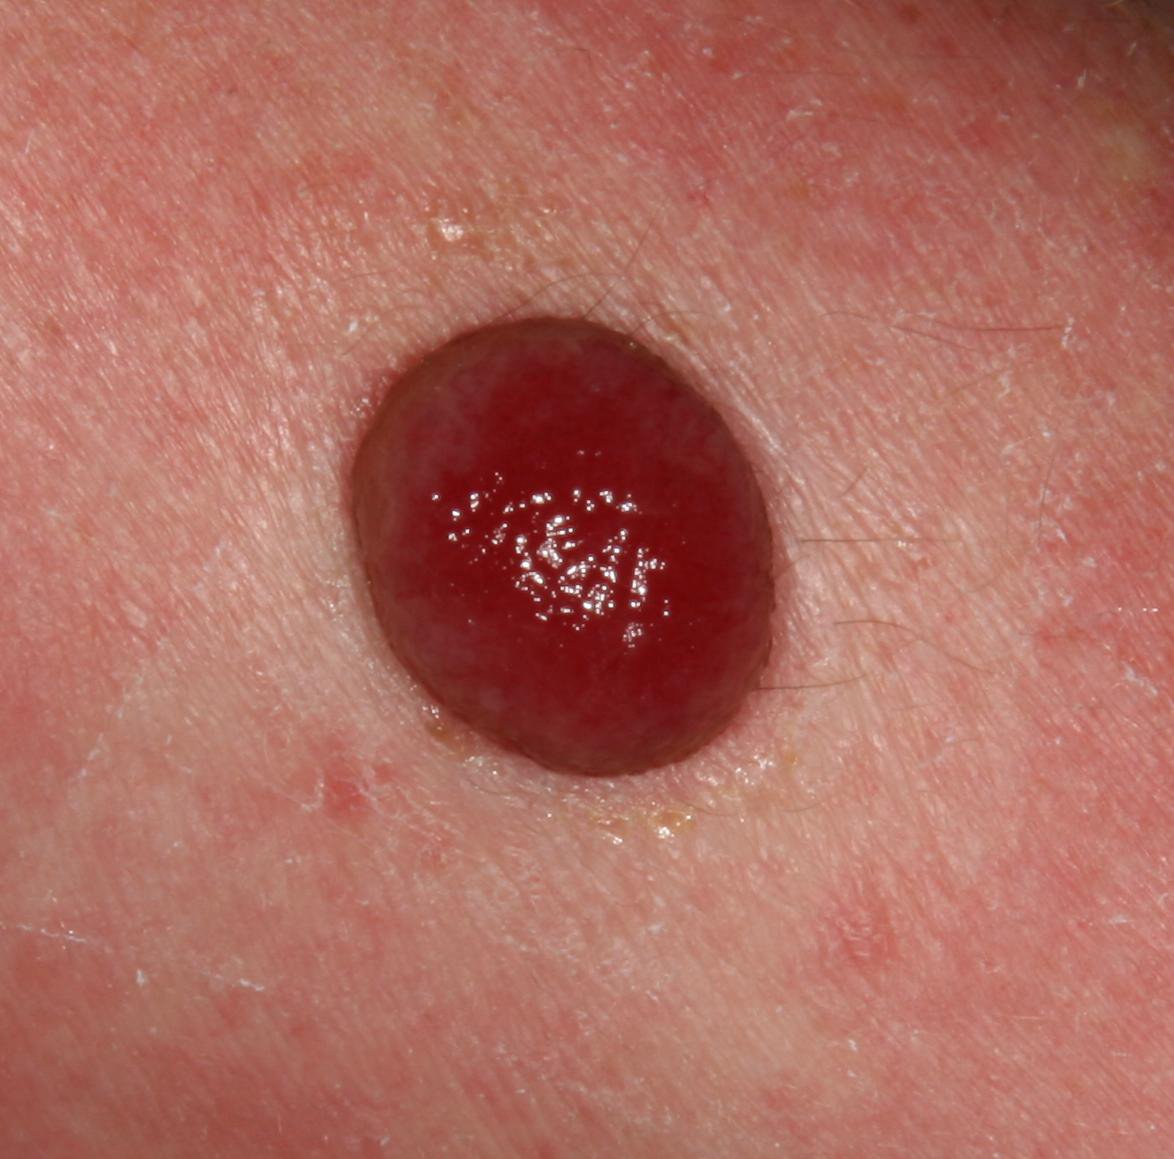
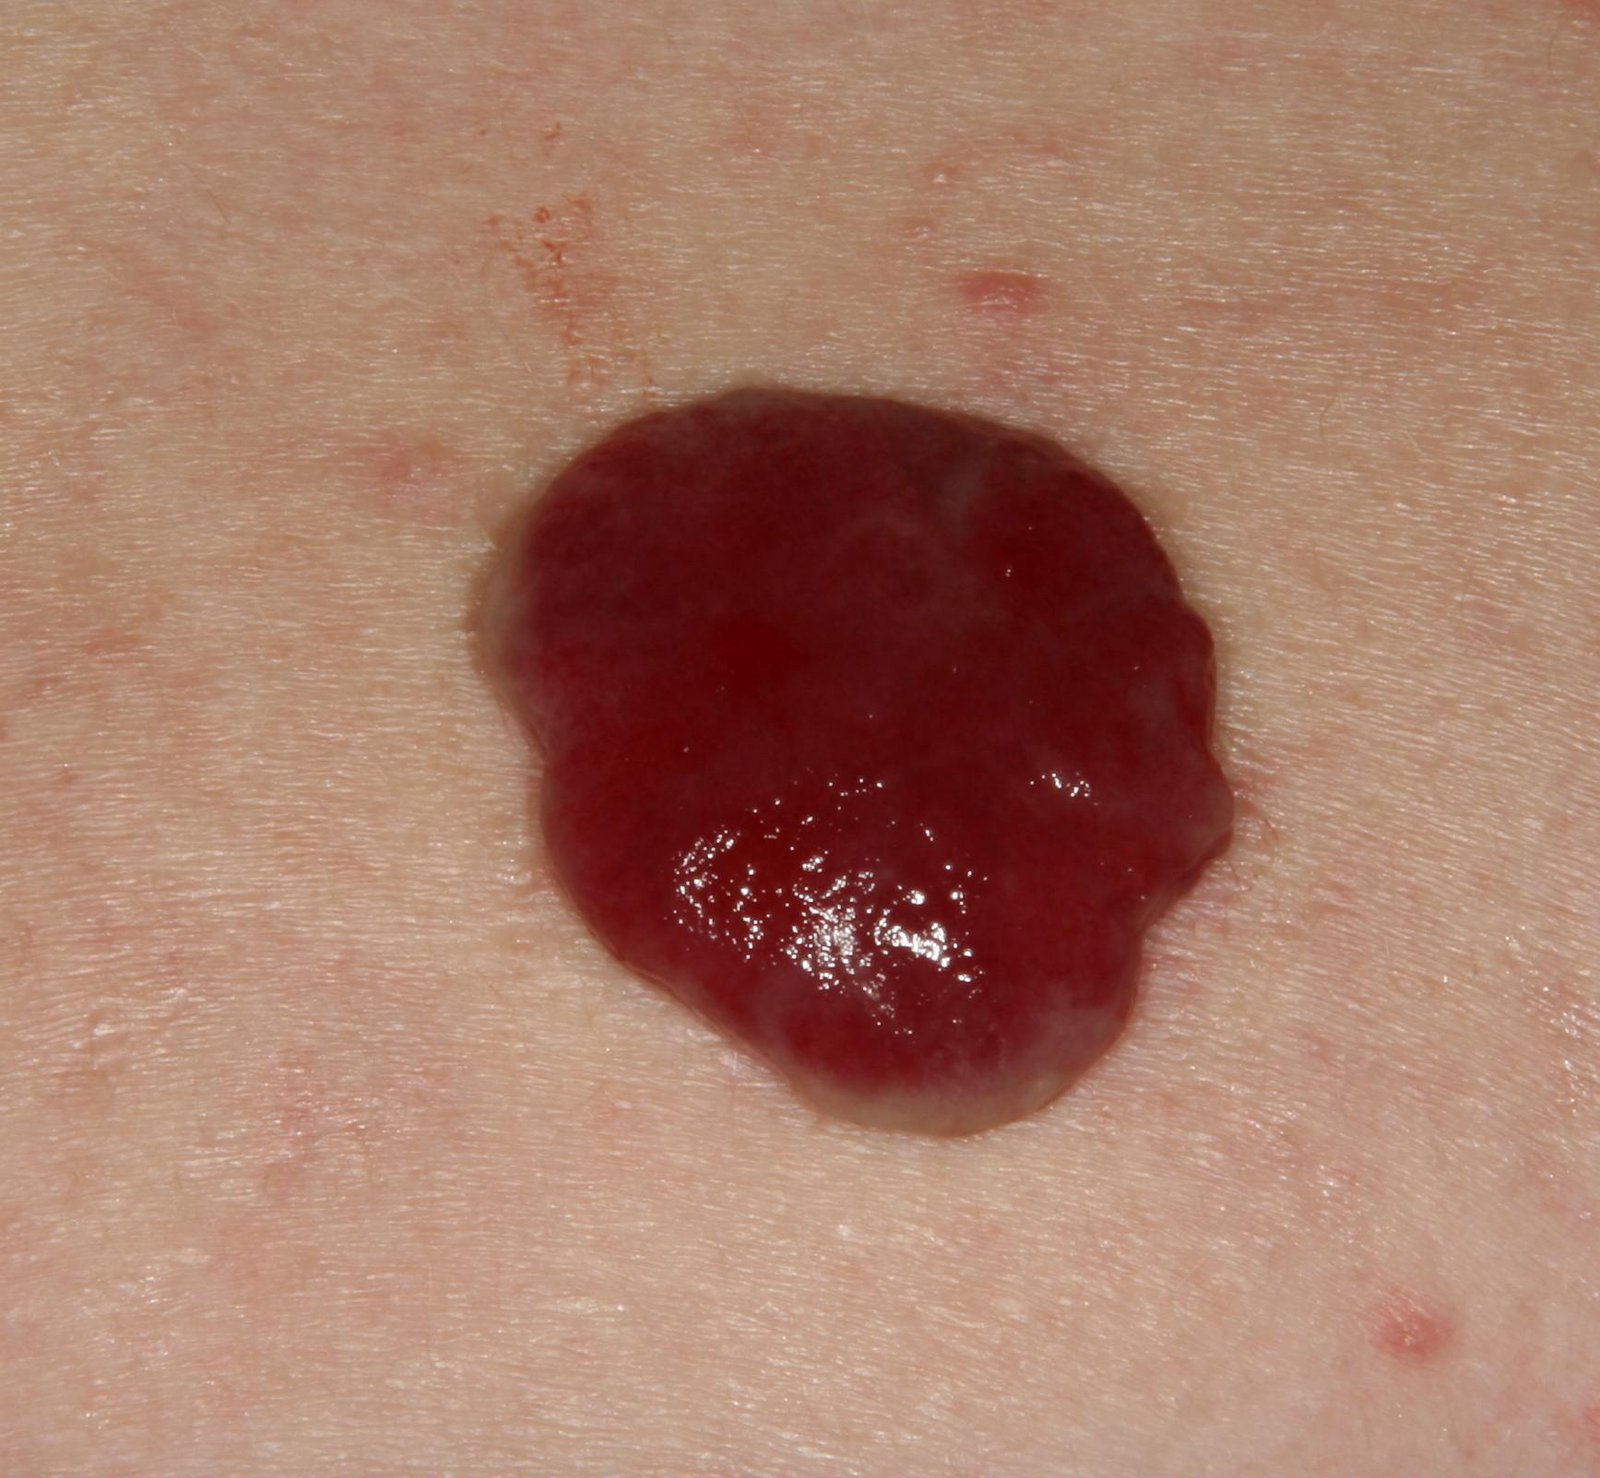
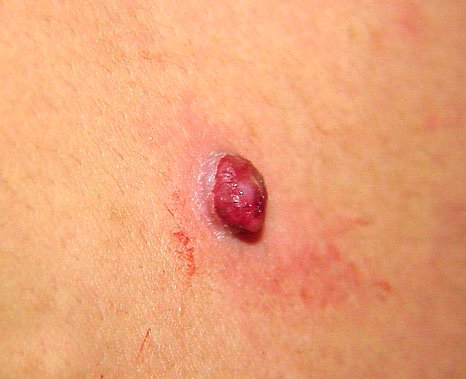
Pyogenic Granuloma is a benign vascular proliferation — a lobular capillary hemangioma — in which blood capillaries multiply in one spot, often after an external injury. The name is a misnomer inherited from older literature: the lesion is neither an infection nor a true granuloma, and there is no viral cause. This type of neoplasm appears as a small, raised, bright red lesion, which can vary in size and shape. Pyogenic granulomas are commonly found in various parts of the body, including mucous membranes, conjunctiva, and even the cornea. These lesions are more prevalent in young individuals and pregnant women due to the changes in immune and hormonal functions that can influence their formation.
Predisposing Factors
The exact cause of pyogenic granulomas is not well-defined. While injuries were previously considered the primary cause, recent research shows that only 25% of all pyogenic granulomas are linked to injuries. There are numerous potential predisposing factors, including:
- Dermatoses: Chronic skin conditions may create an environment conducive to the development of these lesions.
- Large Burn Surfaces: Extensive burns can damage skin and lead to the formation of pyogenic granulomas as part of the healing process.
- Use of Oral Contraceptives: Hormonal changes due to the use of birth control pills can trigger the appearance of pyogenic granulomas.
- Protease Inhibitors: Certain medications, such as protease inhibitors, can increase the risk of developing pyogenic granulomas.
- Isotretinoin Acne Treatment: Use of isotretinoin, a common treatment for acne, has been associated with an increased risk of pyogenic granulomas.
- Pregnancy: Hormonal fluctuations during pregnancy, such as an increase in growth factors, may lead to the development of pyogenic granulomas.
Diagnostics
Diagnosing a pyogenic granuloma is typically based on a thorough clinical examination, which includes visual inspection of the lesion and dermatoscopic evaluation. These can strongly suggest the diagnosis, but they cannot settle it on their own: amelanotic melanoma and other vascular and malignant lesions can look very similar. Histopathologic examination is therefore appropriate whenever the diagnosis is uncertain, and is worth considering for any lesion that is removed.
For congenital or large pyogenic granulomas located in anatomically sensitive cutaneous or mucosal sites, an ultrasound and a multidisciplinary evaluation by specialists may be required to assess the extent of the lesion and determine appropriate treatment.
Symptoms
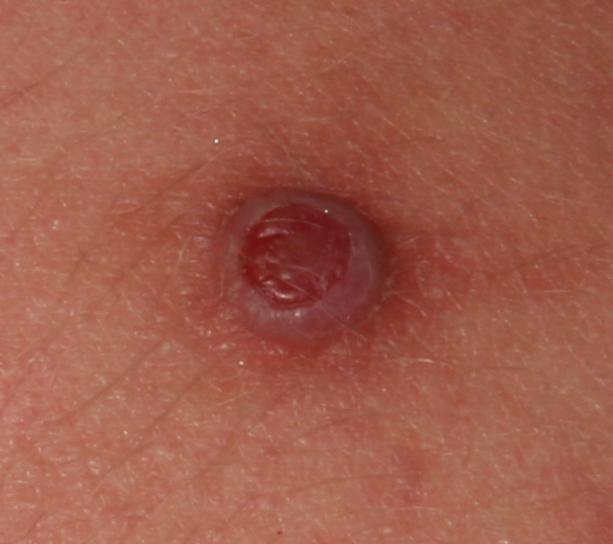
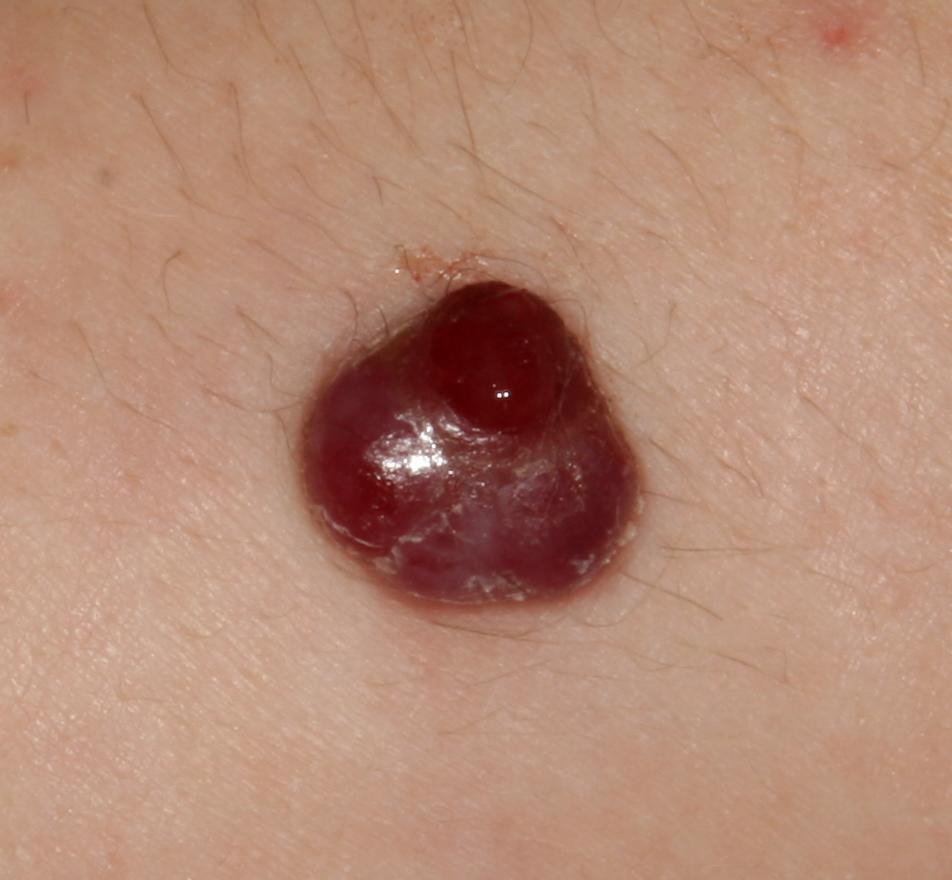
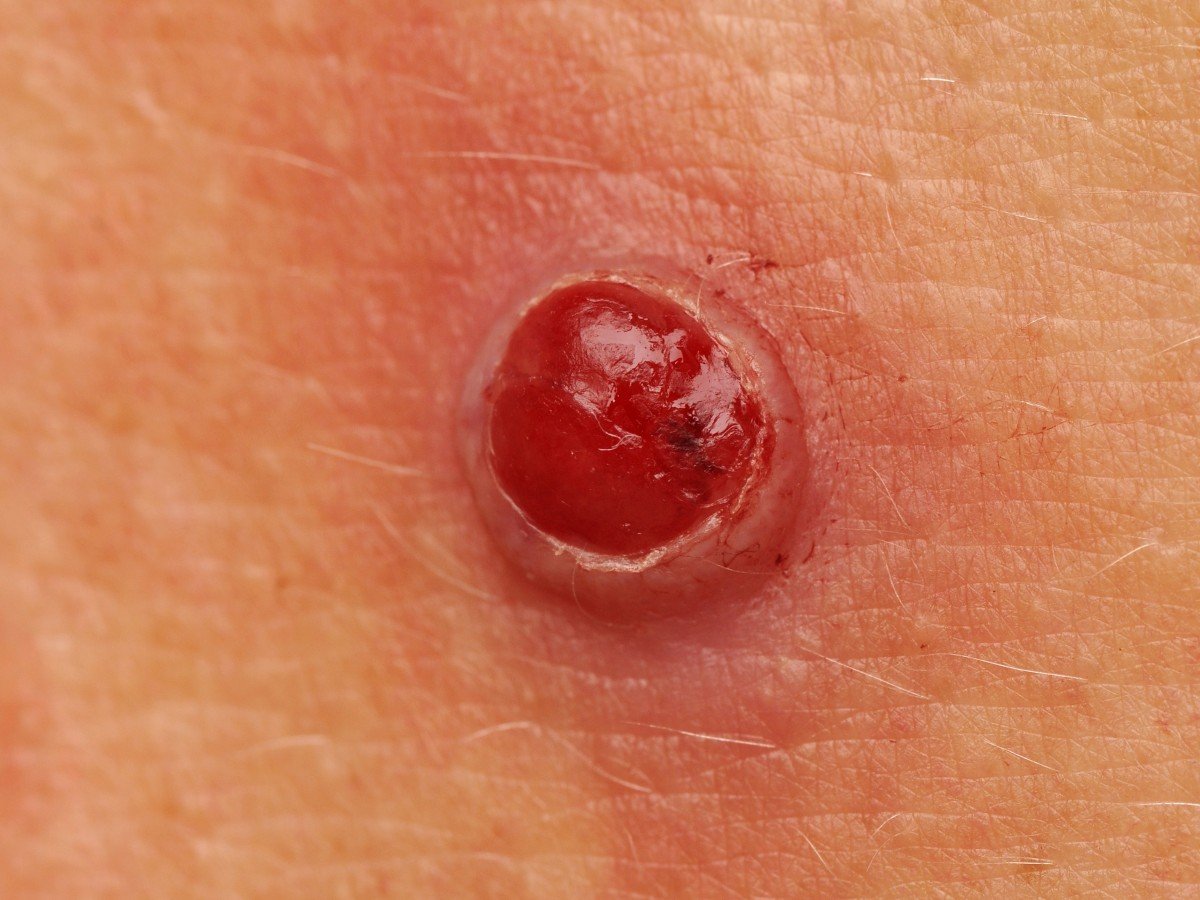
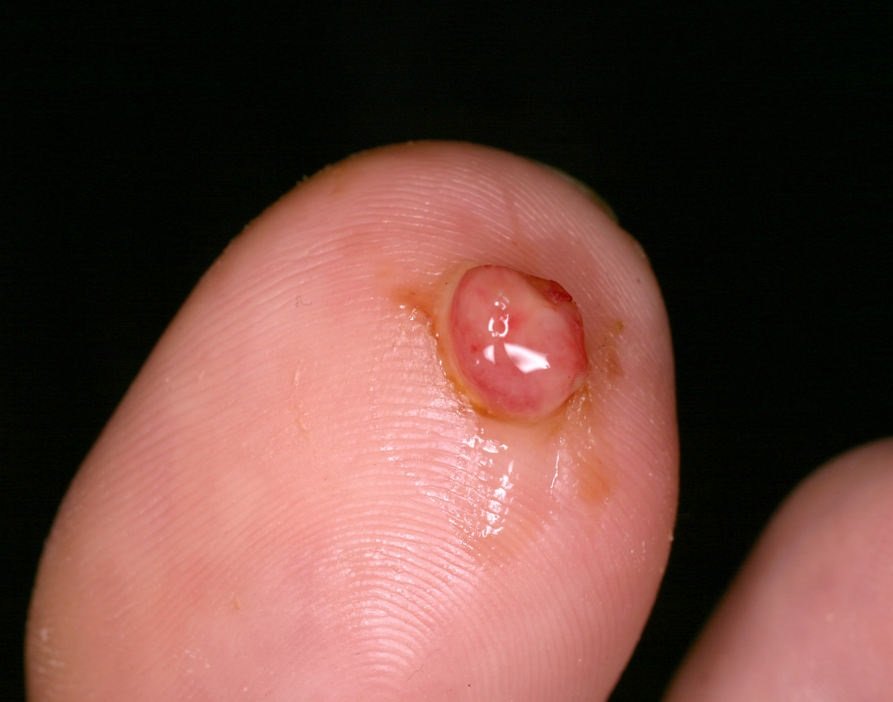
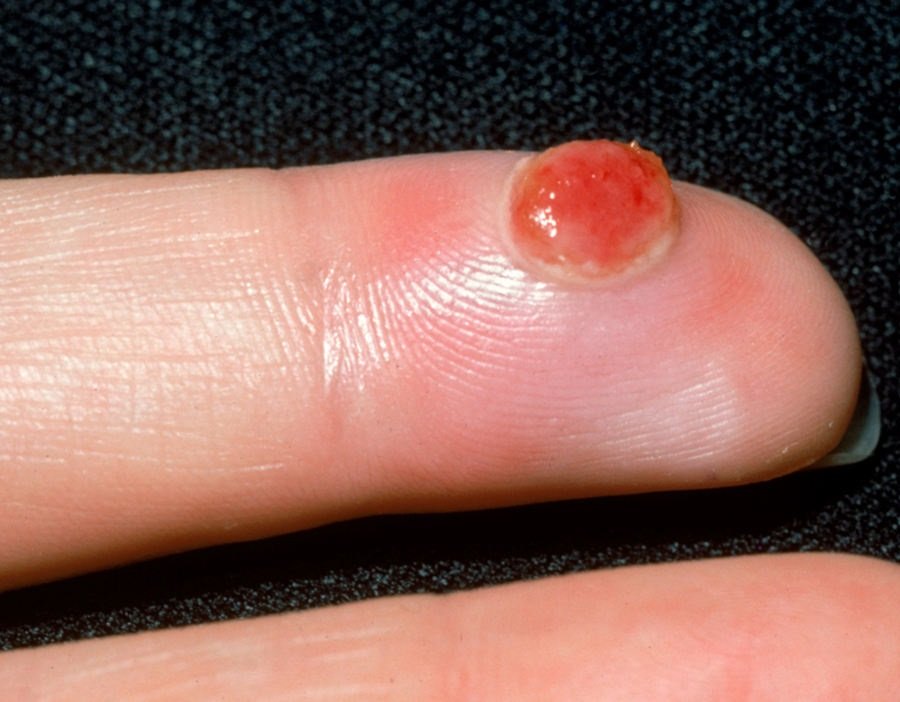
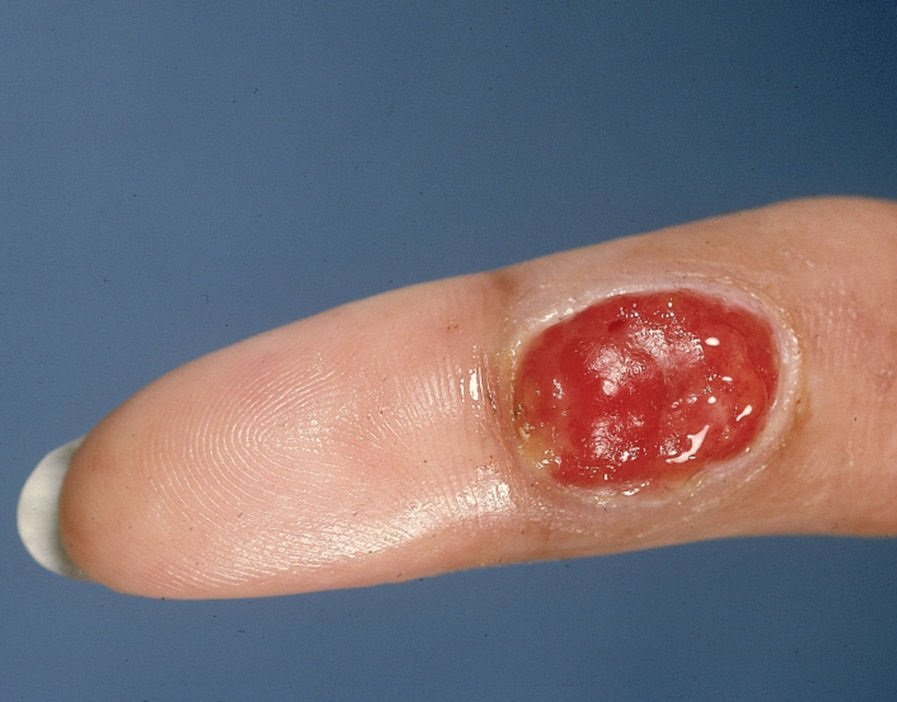
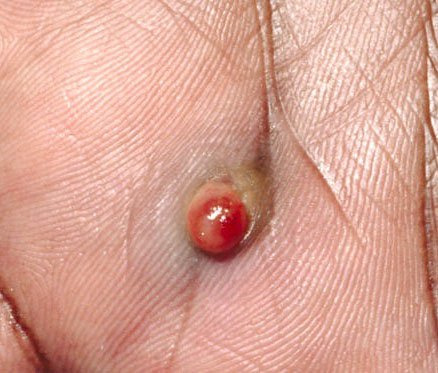
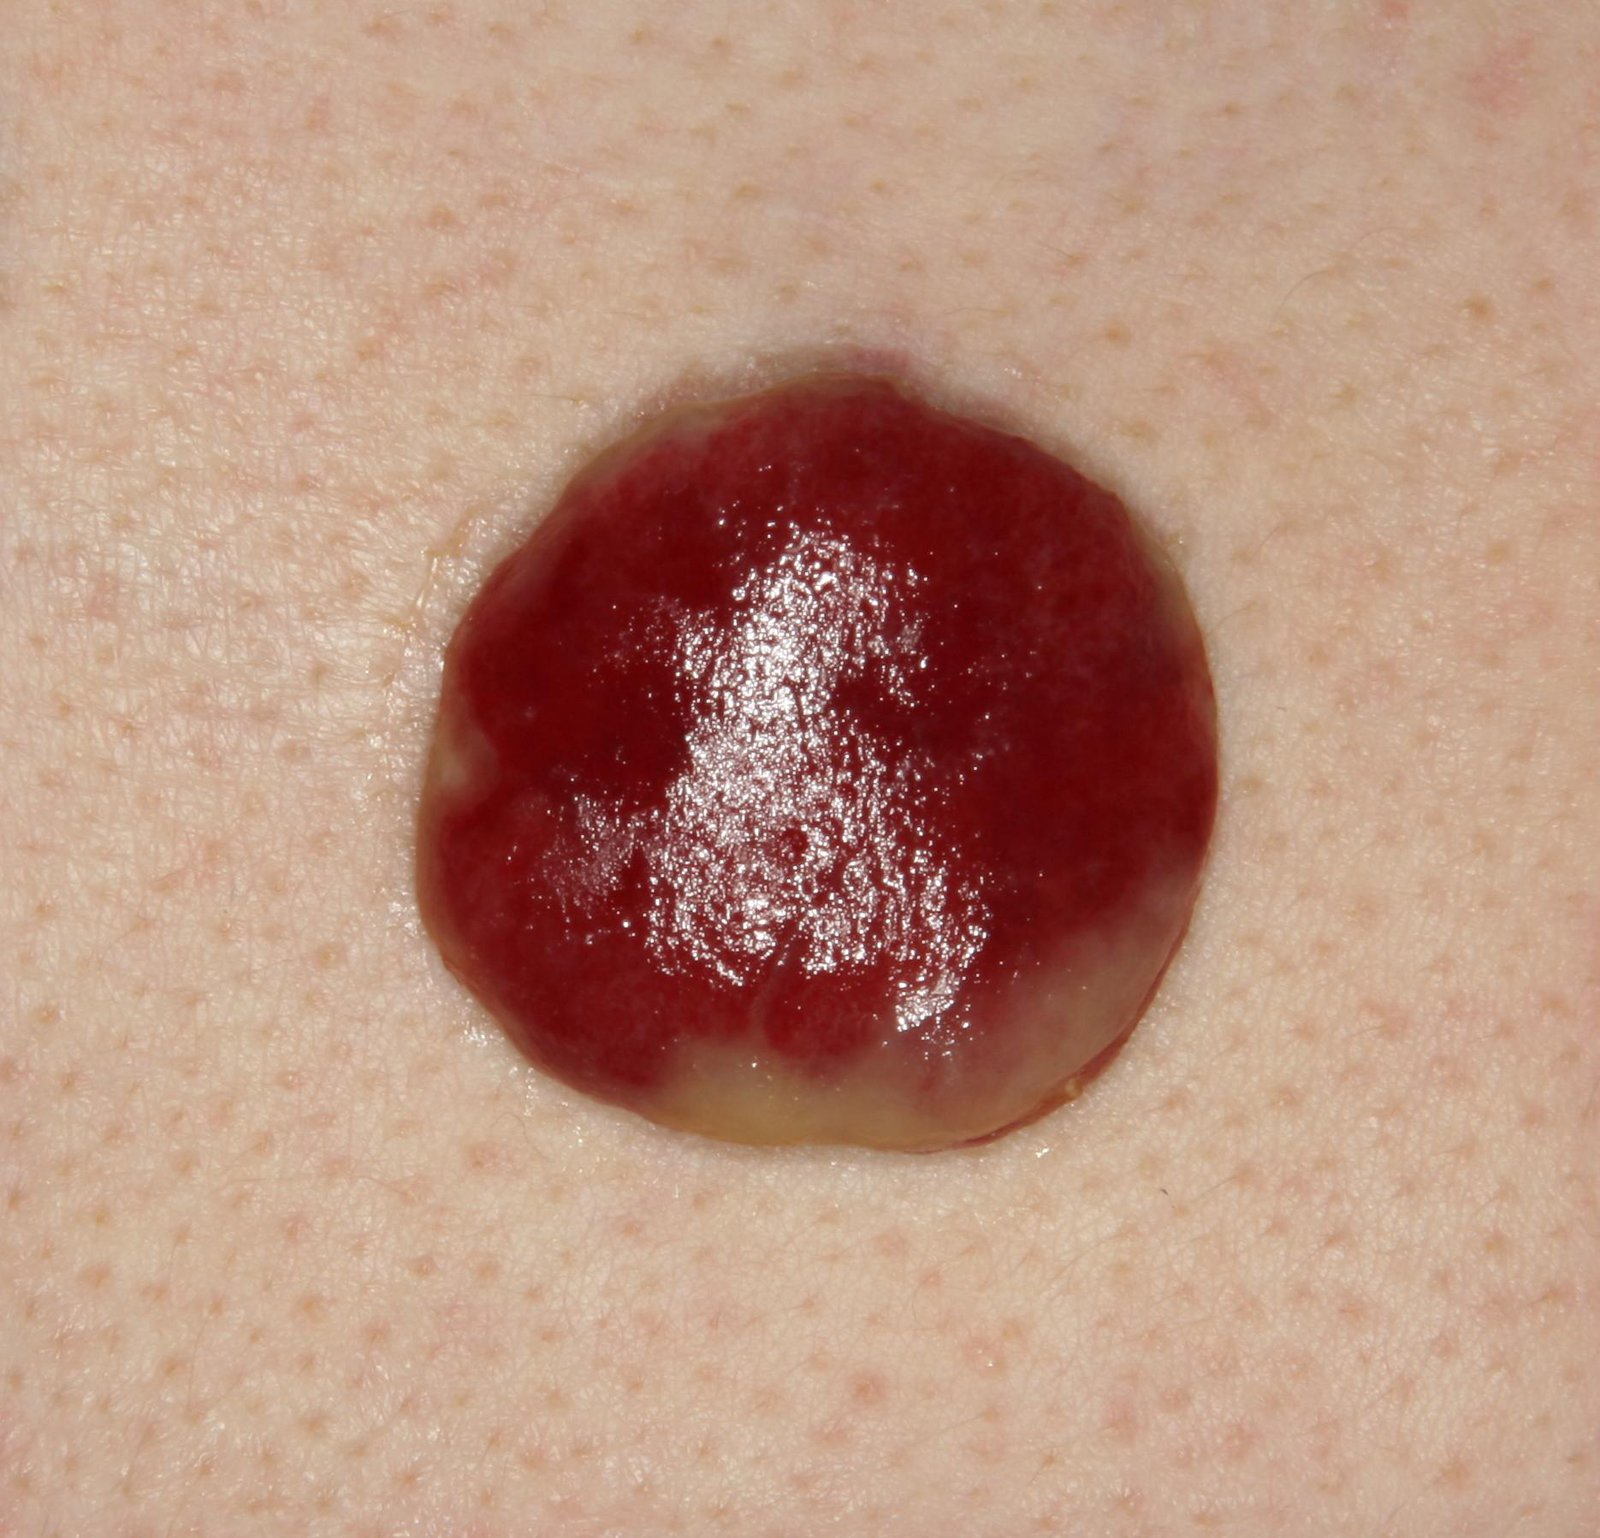
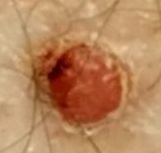
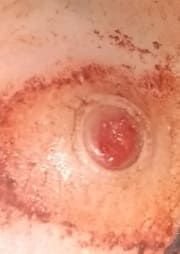
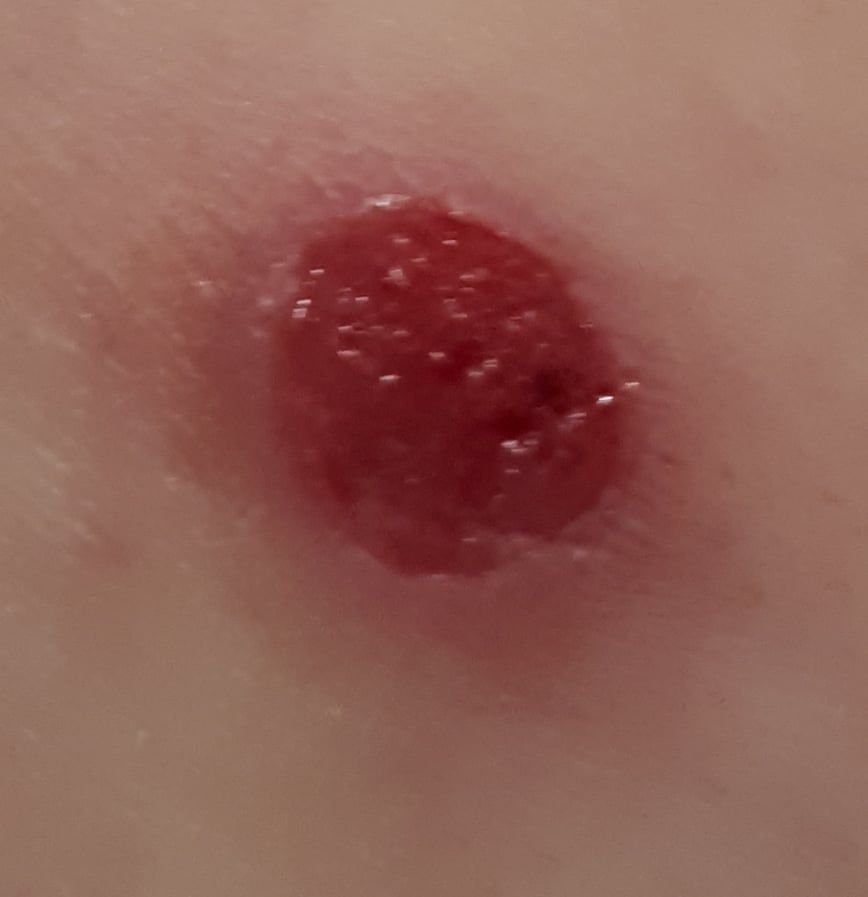
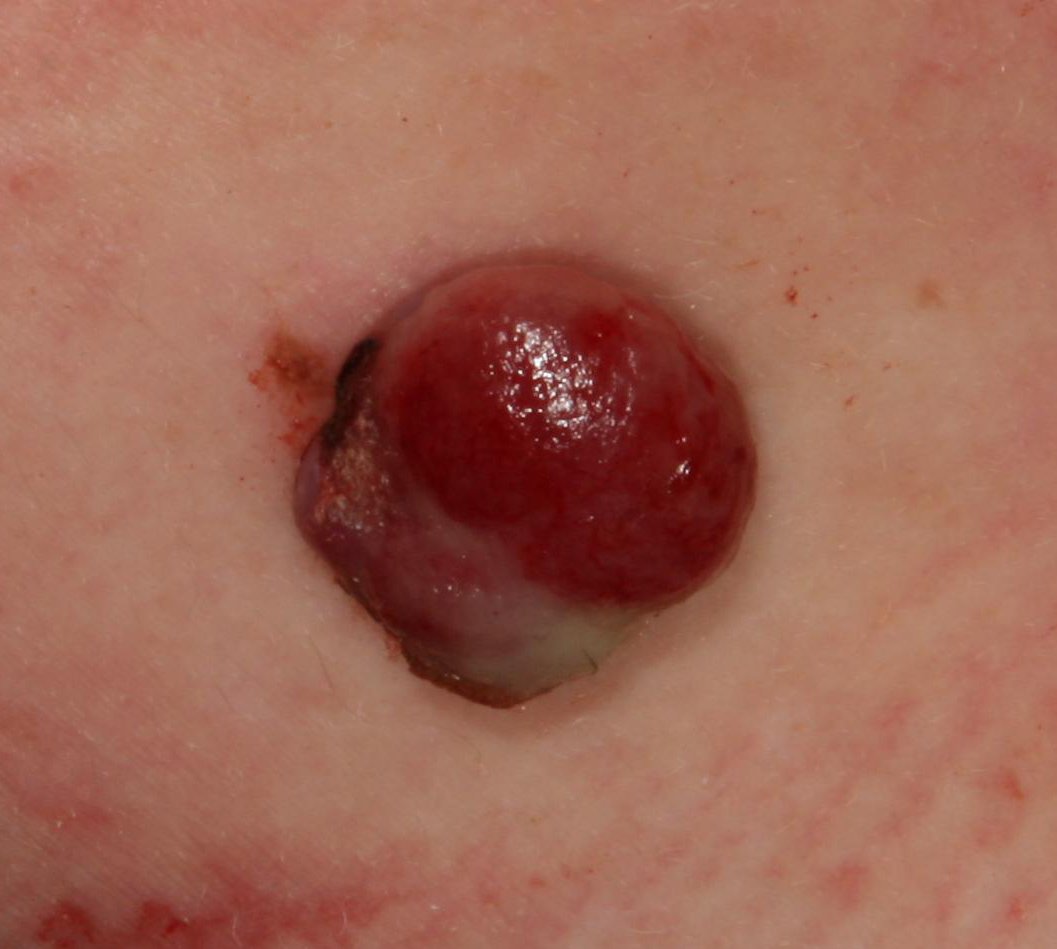
Upon visual examination, pyogenic granulomas present as a hemispherical or dome-shaped growth that rises above the skin on a short, wide stalk (pedicle). Most often, these growths are symmetrical, appearing oval or round. The surface texture of the granuloma can differ from the surrounding skin, sometimes appearing smooth or lobed, resembling raspberries. The granuloma may have a shiny or “wet” appearance due to the presence of minor erosion or crusts. If the granuloma is injured, it may bleed easily, and larger granulomas that become infected can form a purulent plaque with areas of necrosis.
The boundaries of pyogenic granulomas are usually well-defined but can be uneven in larger lesions. The color of the granuloma is often bright red, though it may appear cyanotic (blue or purple) or even yellow or gray in the presence of purulent material or necrotic tissue. When pressure is applied to the granuloma, the red color fades temporarily.
Hair does not grow in the area of a pyogenic granuloma. However, in some cases, coarse hair may grow at the center of the lesion, particularly in congenital forms or large granulomas.
The size of pyogenic granulomas typically ranges from 3 to 15 mm. Lesions larger than 15 mm are rarer and are often associated with underlying systemic diseases or immunodeficiency states. The granuloma grows rapidly, often reaching a diameter of 1-1.5 cm within a short period. Its height typically does not exceed 5 mm. Spontaneous regression is rare but may occur, especially in pregnant women after childbirth.
On palpation, pyogenic granulomas feel soft and elastic, without tenderness. After infection, the granuloma may become painful. There are typically no subjective symptoms unless the granuloma becomes injured or infected.
These lesions are most commonly found on the hands and feet, particularly on the palmar and plantar surfaces of the fingers, where injuries and contact with foreign bodies are more likely. Pyogenic granulomas can also appear near the nail ridges (such as from ingrown nails) or on the face. Less commonly, they may appear on mucous membranes, depending on predisposing factors like burns, pressure sores, or physical trauma.
Dermatoscopic Description
Dermatoscopic examination of a pyogenic granuloma reveals the following characteristics:
- Rigidity and Filling: These signs indicate the elasticity of the granuloma. When compressed, the granuloma pales and decreases in size. Once the pressure is released, the lesion returns to its original color and shape.
- Vascular Features: A large number of small bright red vascular gaps can be seen, indicating the blood vessel network within the lesion.
- Absence of Vascular Pattern: In some cases, the vascular pattern may be absent or appear as irregular gaps.
- White Whiskers: These represent areas where the granuloma is undergoing necrosis or injury.
- Superficial Ulceration: Areas of the granuloma may have superficial ulceration, particularly if the lesion has been traumatized.
Differential Diagnosis
Pyogenic granulomas must be differentiated from other skin lesions with similar characteristics, including:
- Dermatological diseases (such as pyoderma)
- Spitz nevus
- Glomus tumors
- Keratoacanthoma
- Basal cell carcinoma
- Squamous cell carcinoma
- Melanoma (especially non-pigmented forms)
- Angiosarcoma
- Kaposi’s sarcoma
- Lymphoma of the skin
Risks
From an oncological perspective, pyogenic granulomas are safe and do not carry an increased risk of malignant transformation. If there is a noticeable change in the appearance of the granuloma, such as rapid growth, increased density, or new symptoms like itching or pain, a dermatologist should be consulted.
One of the primary risks associated with pyogenic granulomas is their susceptibility to injury due to their raised and delicate nature. This can lead to bleeding, soreness, and infection, which can further complicate the condition. In large granulomas, bleeding can be difficult to manage without medical intervention. Furthermore, because some malignant tumors can resemble pyogenic granulomas or develop next to them, it is important to undergo a timely differential diagnosis to ensure that no malignant growth is overlooked.
Tactics
If a pyogenic granuloma is detected, a consultation with a dermatologist is recommended. After confirming that the lesion is benign, the possibility of conservative management or the need for treatment can be evaluated. Small granulomas, especially in pregnant women, may resolve spontaneously, and observation may be sufficient. In all other cases, treatment is typically recommended.
For patients who refuse treatment, active monitoring is essential. This includes photo documentation of the lesion to track any changes in appearance. How often someone with multiple pyogenic granulomas needs to be seen depends on the lesions rather than on the time of year. Regular mapping of skin neoplasms can also help with observation and tracking any new or altered lesions.
Treatment
The established treatments are curettage with cautery and complete excision. Excision can be done with a classic, electric or radio scalpel, and there is no need to take away surrounding skin along with the lesion. Cryotherapy and laser are alternatives, generally for smaller lesions.
Tissue from a removed lesion is worth sending for histological examination, and it should be sent whenever the diagnosis was not certain beforehand. In that situation the lesion should be excised or curetted rather than destroyed, so that there is tissue to examine.
Given the vascular nature of pyogenic granulomas, bleeding during removal is common. Therefore, proper hemostasis (control of bleeding) is critical after excision.
Pyogenic granulomas can come back, particularly after incomplete treatment or where whatever provoked the lesion is still present. Treatment should therefore aim at complete removal, and at dealing with the trigger — repeated trauma, a medication, a piercing, or a local source of irritation in the mouth.
Prevention
Preventing the appearance of pyogenic granulomas involves a careful approach to skin care and proper management of injuries:
- Excluding chronic trauma to the skin, such as repeated friction or burns.
- Limiting or eliminating exposure to occupational hazards and environmental factors that could damage the skin.
- Maintaining good personal hygiene and staying informed about skin health.
- Caring for wounds and other skin injuries properly while they heal.
In addition, regular examination of the skin, timely consultation with a healthcare specialist in the event of changes in skin lesions, and the removal of potentially dangerous neoplasms are key to maintaining good skin health.