Halo Nevus (ICD-10: D22) 💚
Halo Nevus (Sutton’s Nevus)
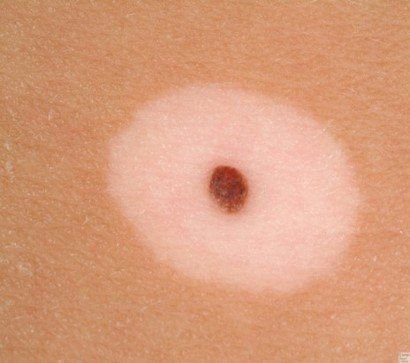
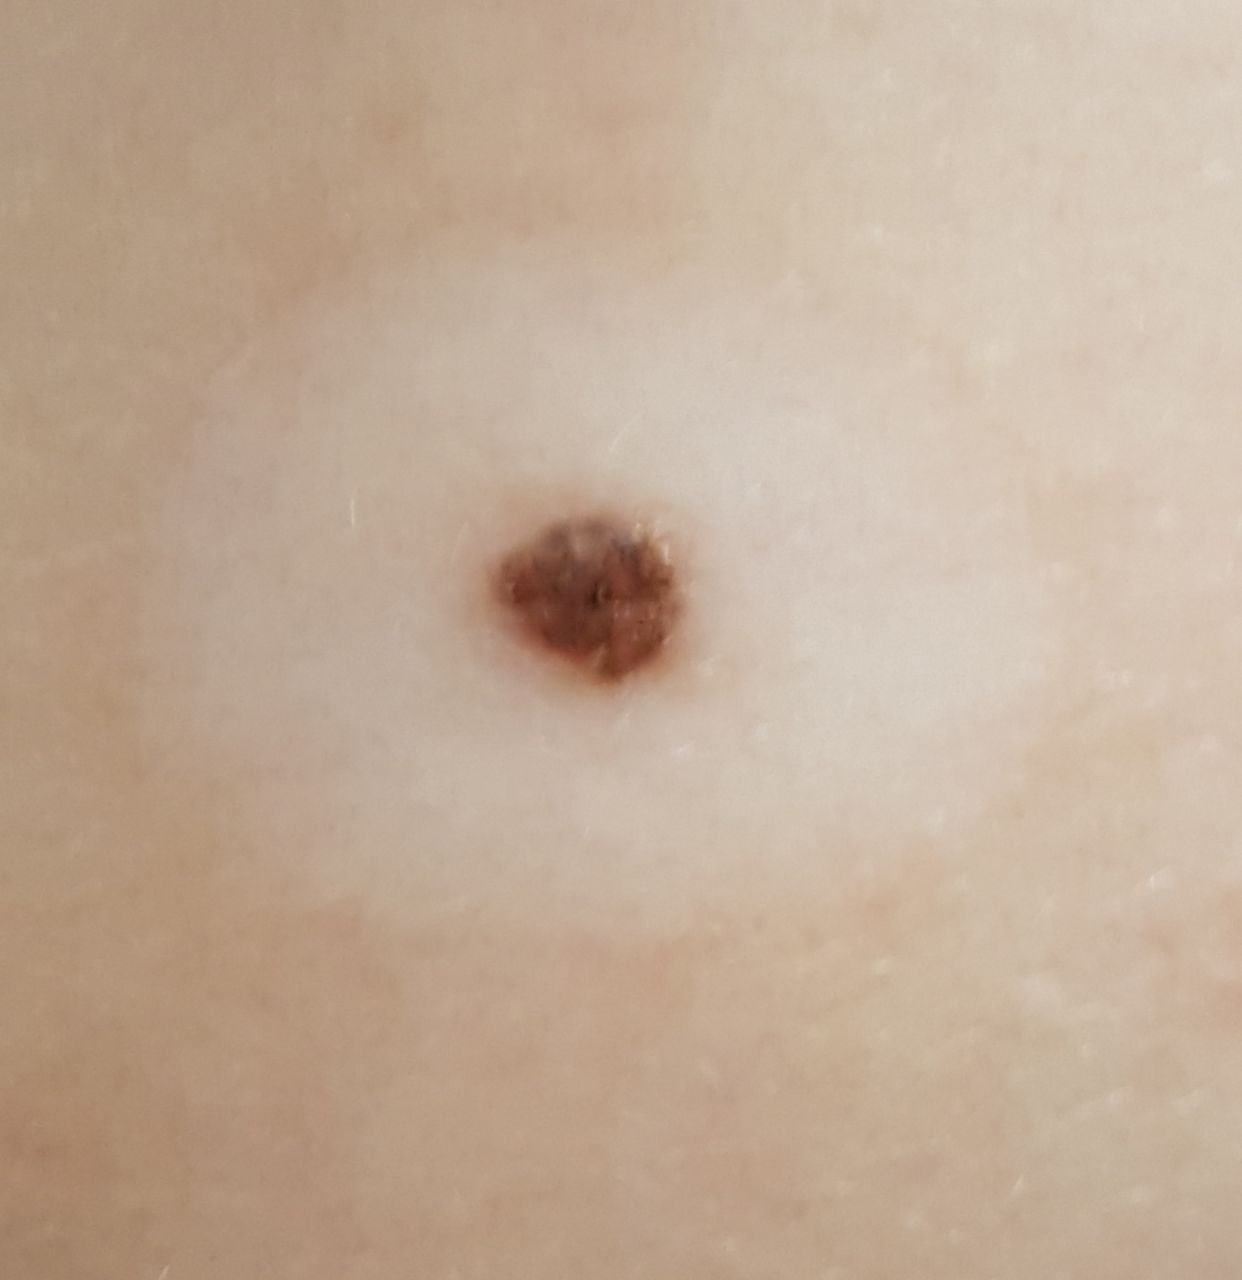
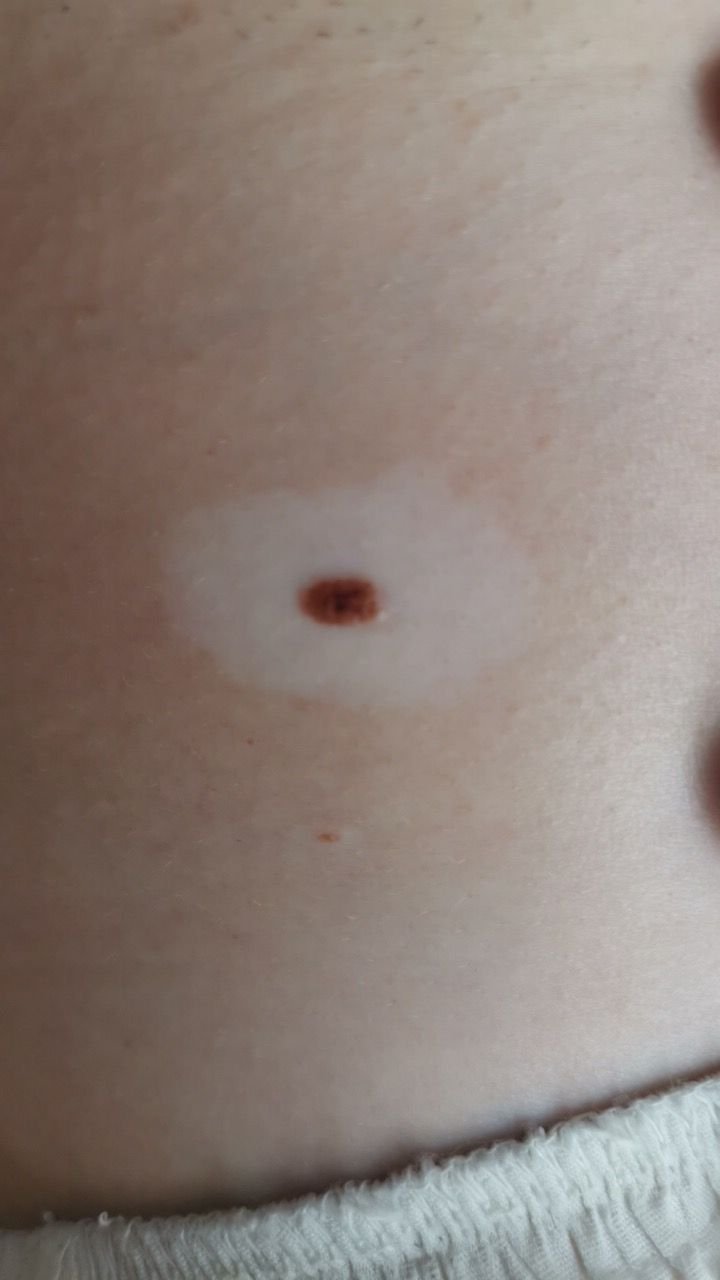
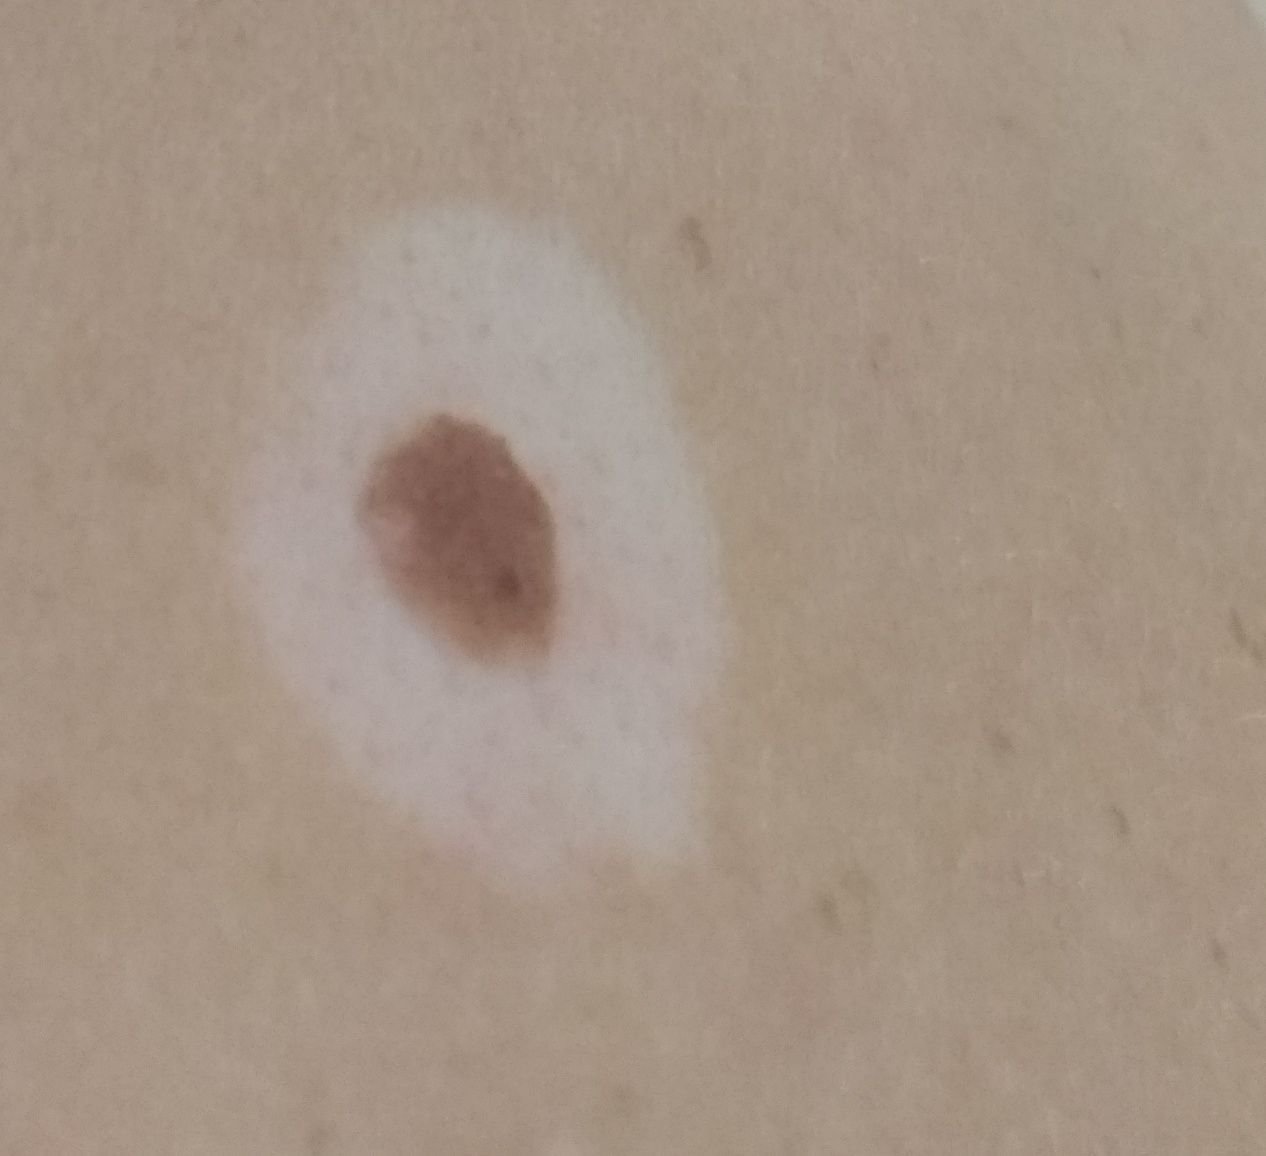
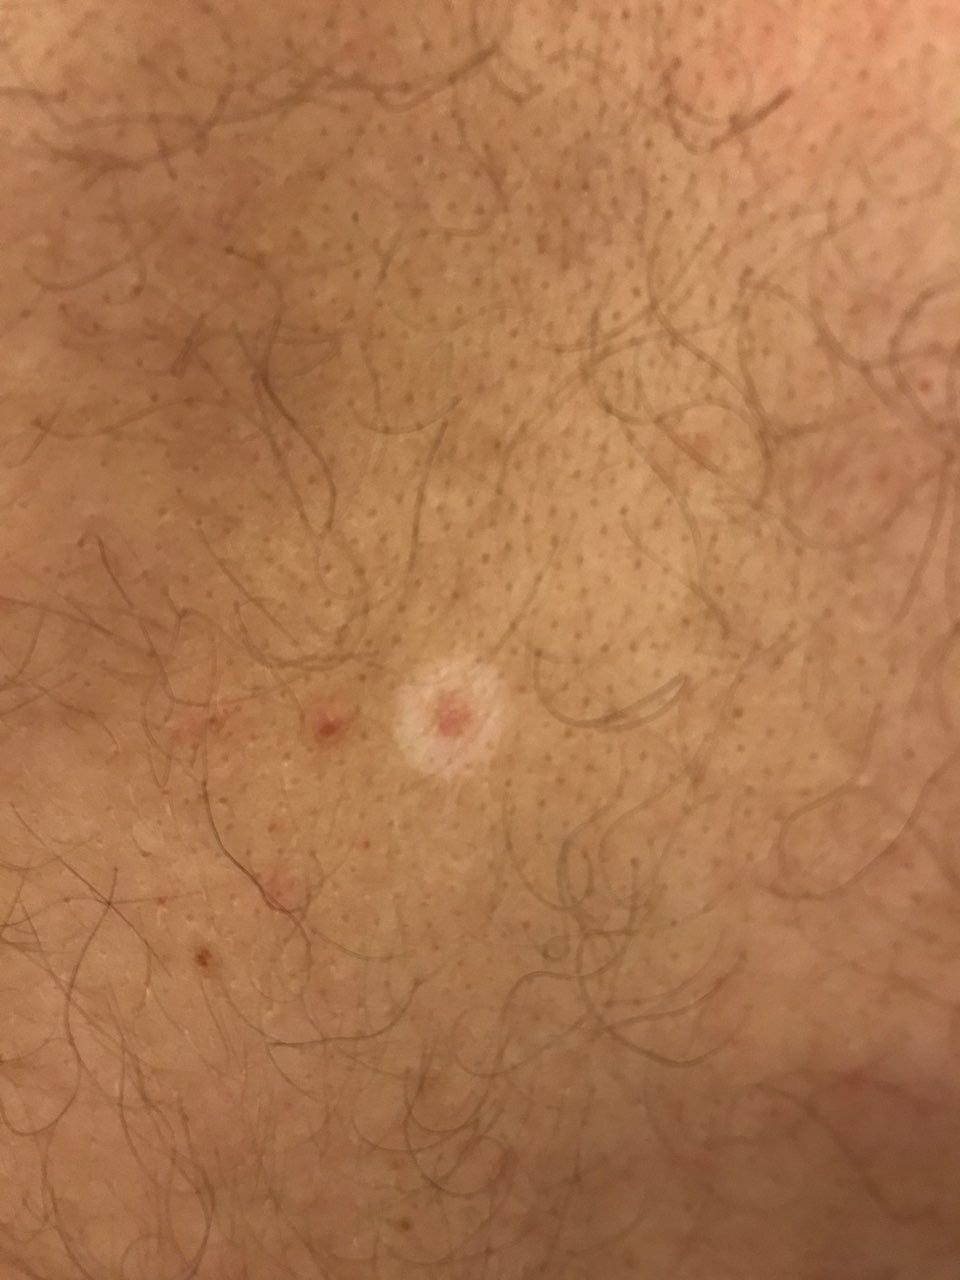
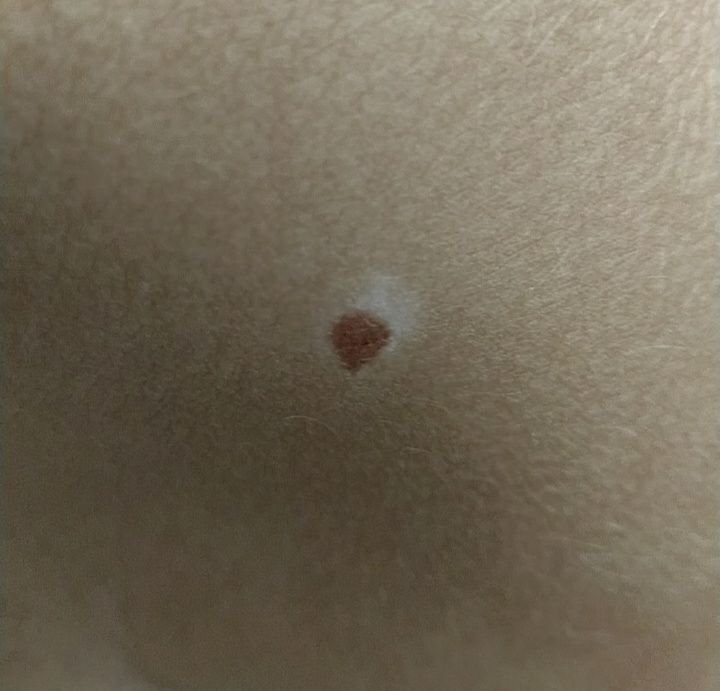
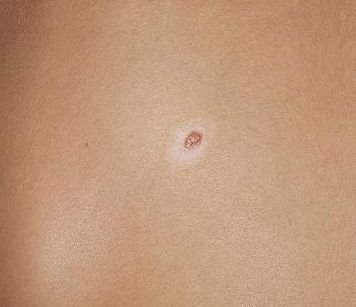
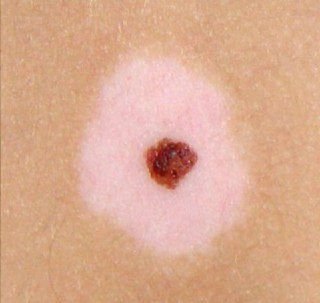
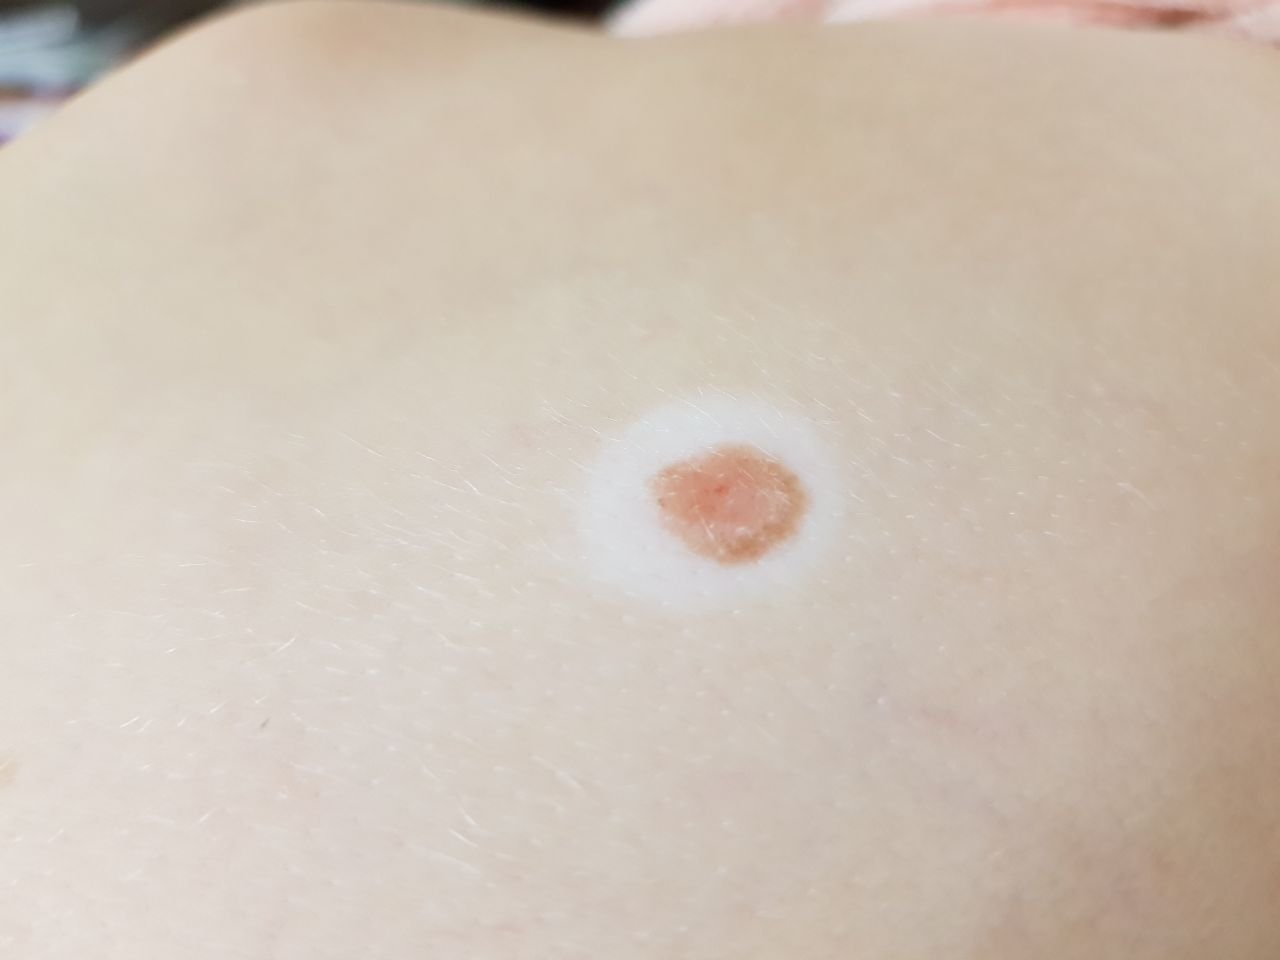
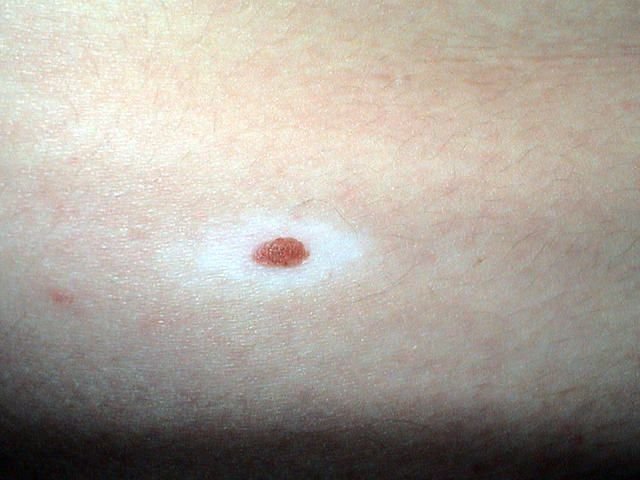
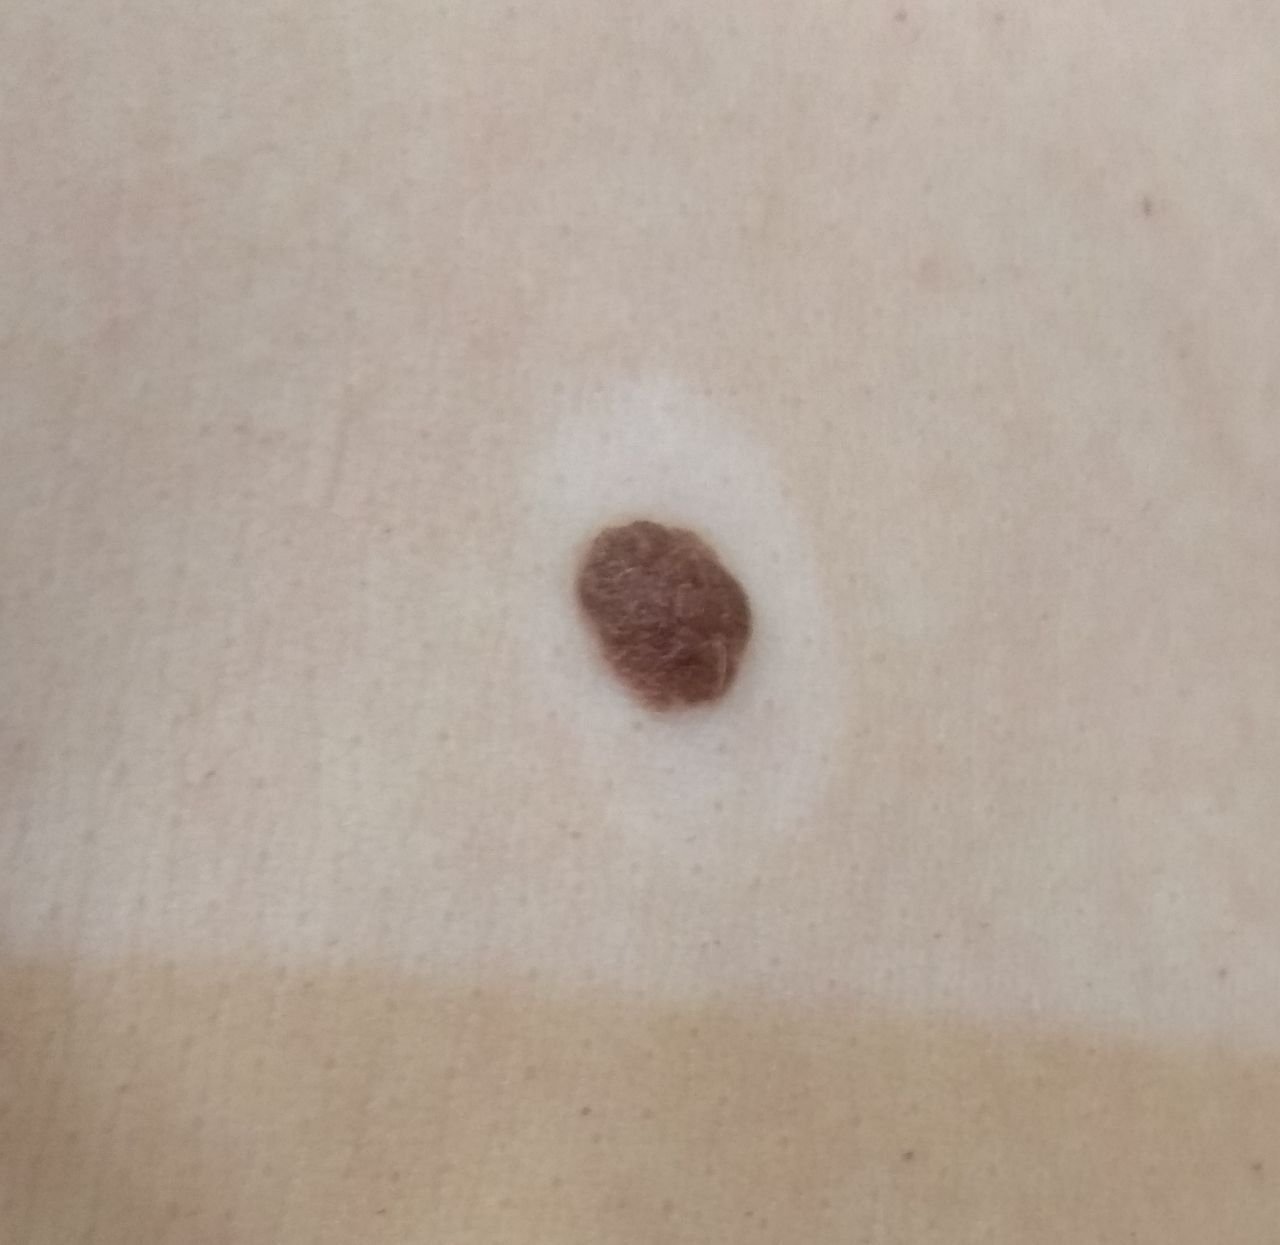
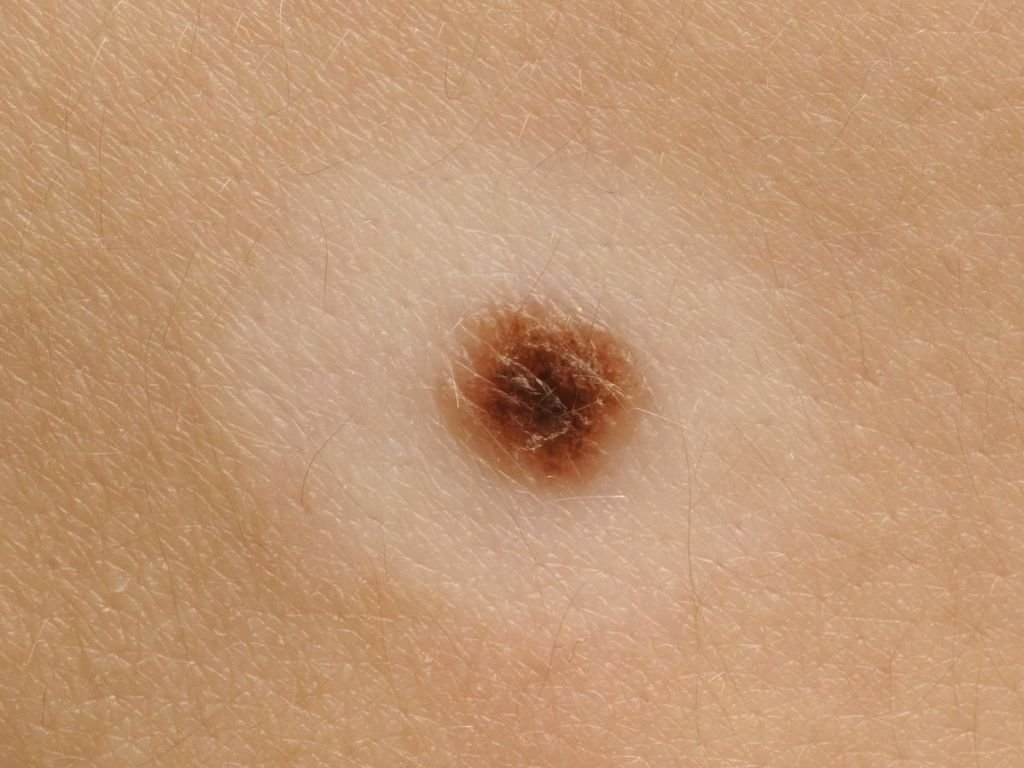
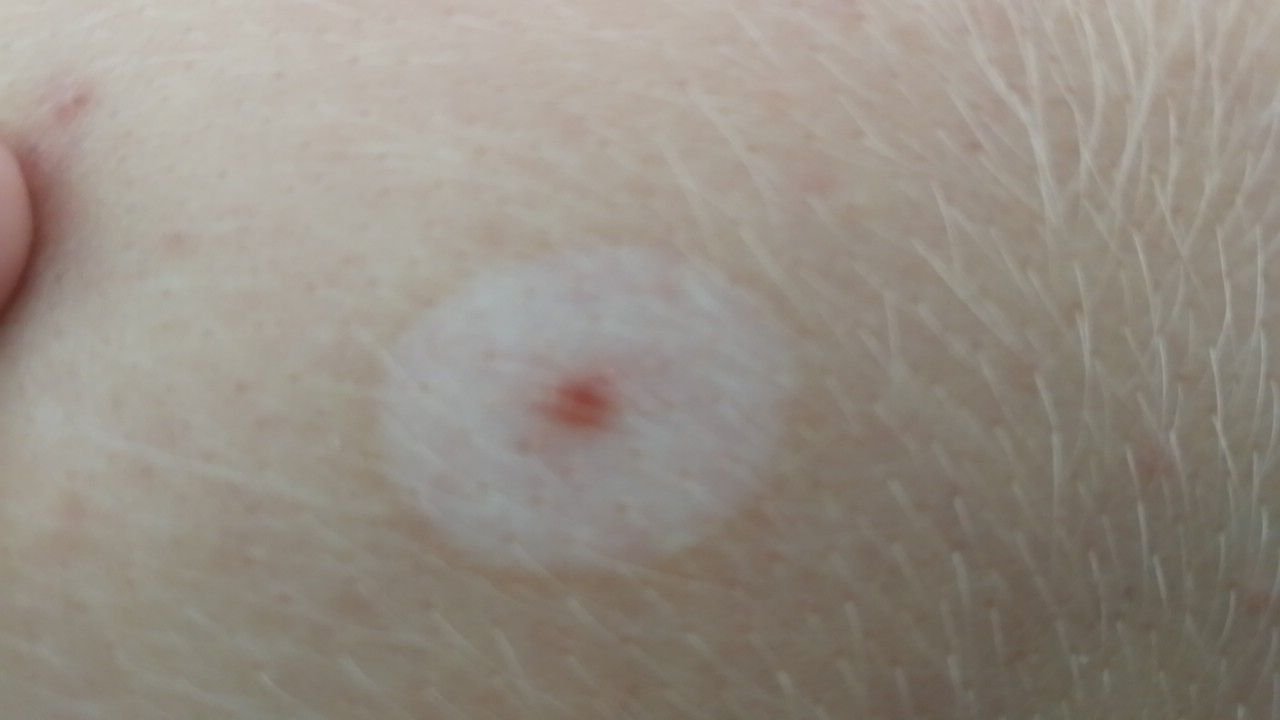
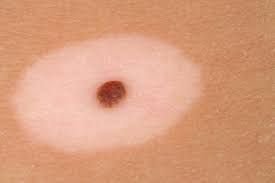
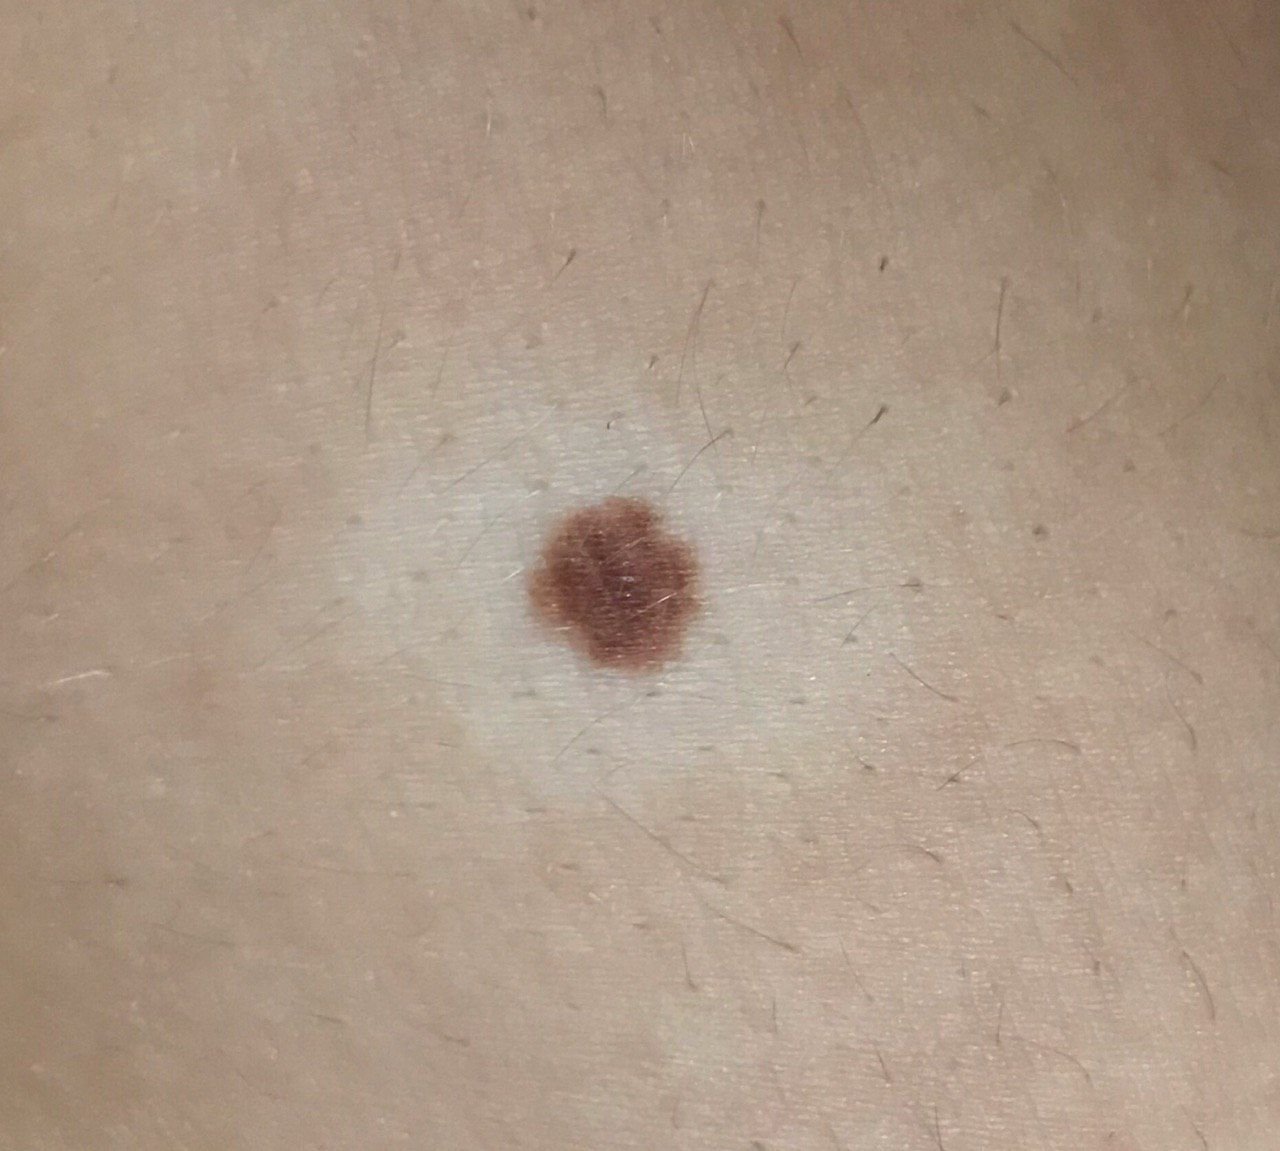
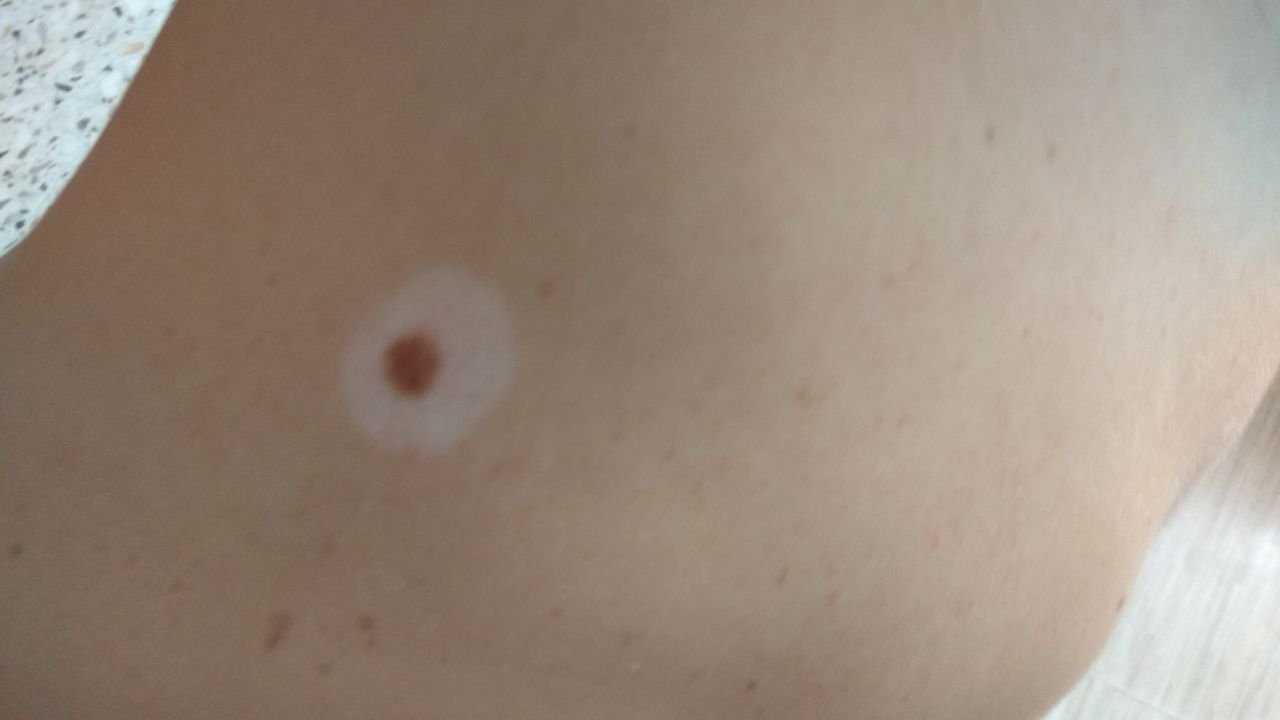
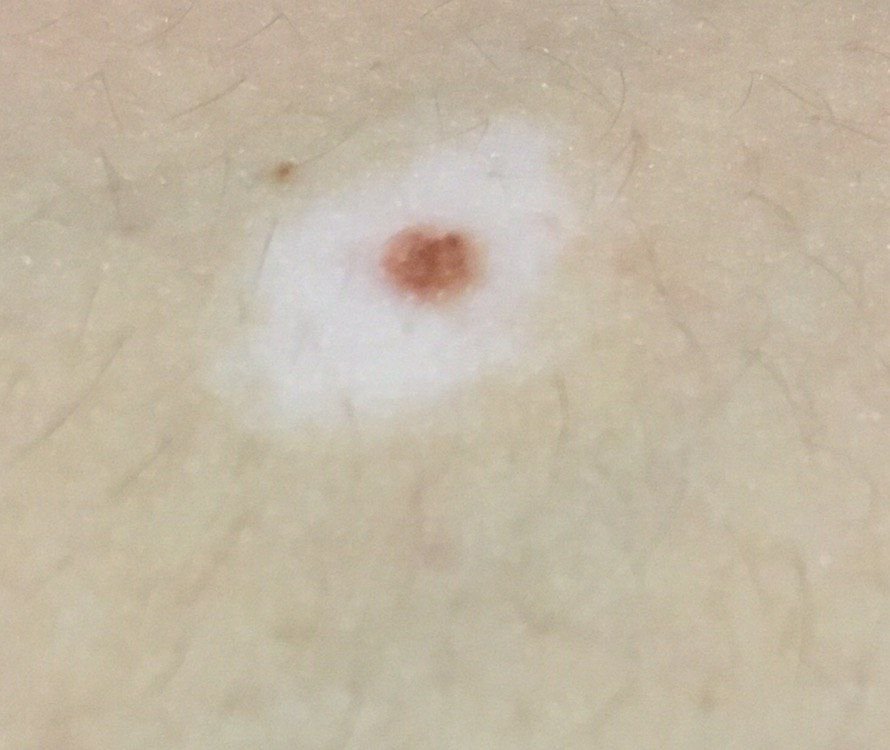
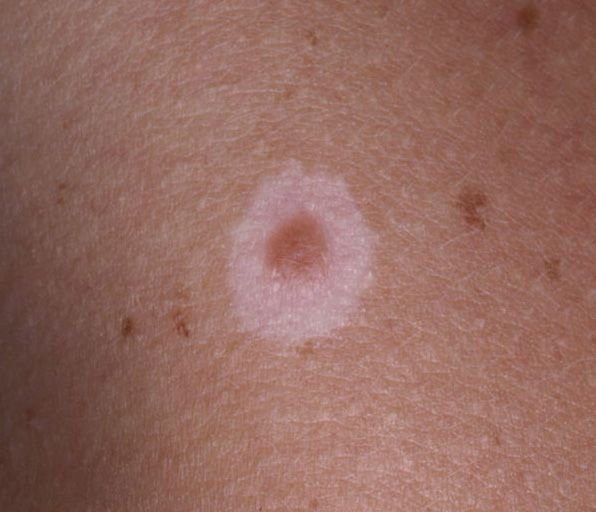
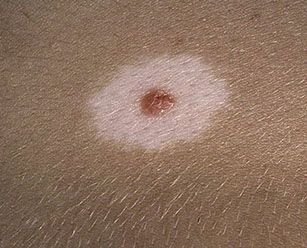
Halo Nevus (also known as Sutton’s Nevus) is a benign skin neoplasm that typically appears as a raised spot surrounded by a rim of hypopigmented skin, creating a characteristic “halo” effect. Most commonly, halo nevi are first observed in individuals between the ages of 15 and 25, starting as a pigmented central area with a gradually expanding colorless ring around it. Over time, the central pigmented part of the nevus may undergo involution, either fading into hypopigmentation or completely disappearing after a period of 3 to 4 years, leaving only the surrounding hypopigmented ring.
Predisposing Factors
Although the exact cause of halo nevus remains unclear, several predisposing factors are believed to influence the likelihood of its appearance. These factors may contribute to an increased risk of the development of halo nevi:
- Genetic Factors: The presence of a halo nevus may be linked to genetic factors, with certain individuals being more predisposed due to their genetic makeup.
- Vitiligo: The presence of vitiligo, a condition characterized by depigmentation of the skin, may increase the risk of developing halo nevi. The relationship between the two conditions is thought to be due to similar autoimmune mechanisms.
- Ultraviolet Radiation: Exposure to ultraviolet radiation, whether from the sun or artificial sources like tanning beds, may trigger the appearance of halo nevi. UV radiation is known to have various effects on the immune system, which may play a role in the formation of these lesions.
- Autoimmune Diseases: Halo nevi are believed to result from a secondary localized immune response, where the body’s immune system attacks melanocytes (cells responsible for pigment production), leading to the characteristic depigmented ring around the nevus. This immune response is often associated with autoimmune diseases.
Diagnostics
The diagnosis of halo nevus is primarily based on a thorough clinical examination. This includes a visual assessment of the lesion and dermatoscopic evaluation to closely inspect its structure and characteristics. A typical halo nevus does not need a biopsy to confirm it: it can be diagnosed clinically and simply observed. Complete excision is appropriate where the central nevus is atypical in structure or colour, or shows other features suspicious for melanoma.
Symptoms
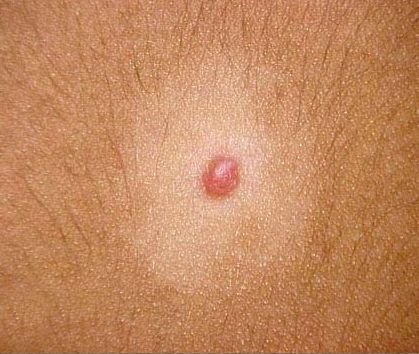
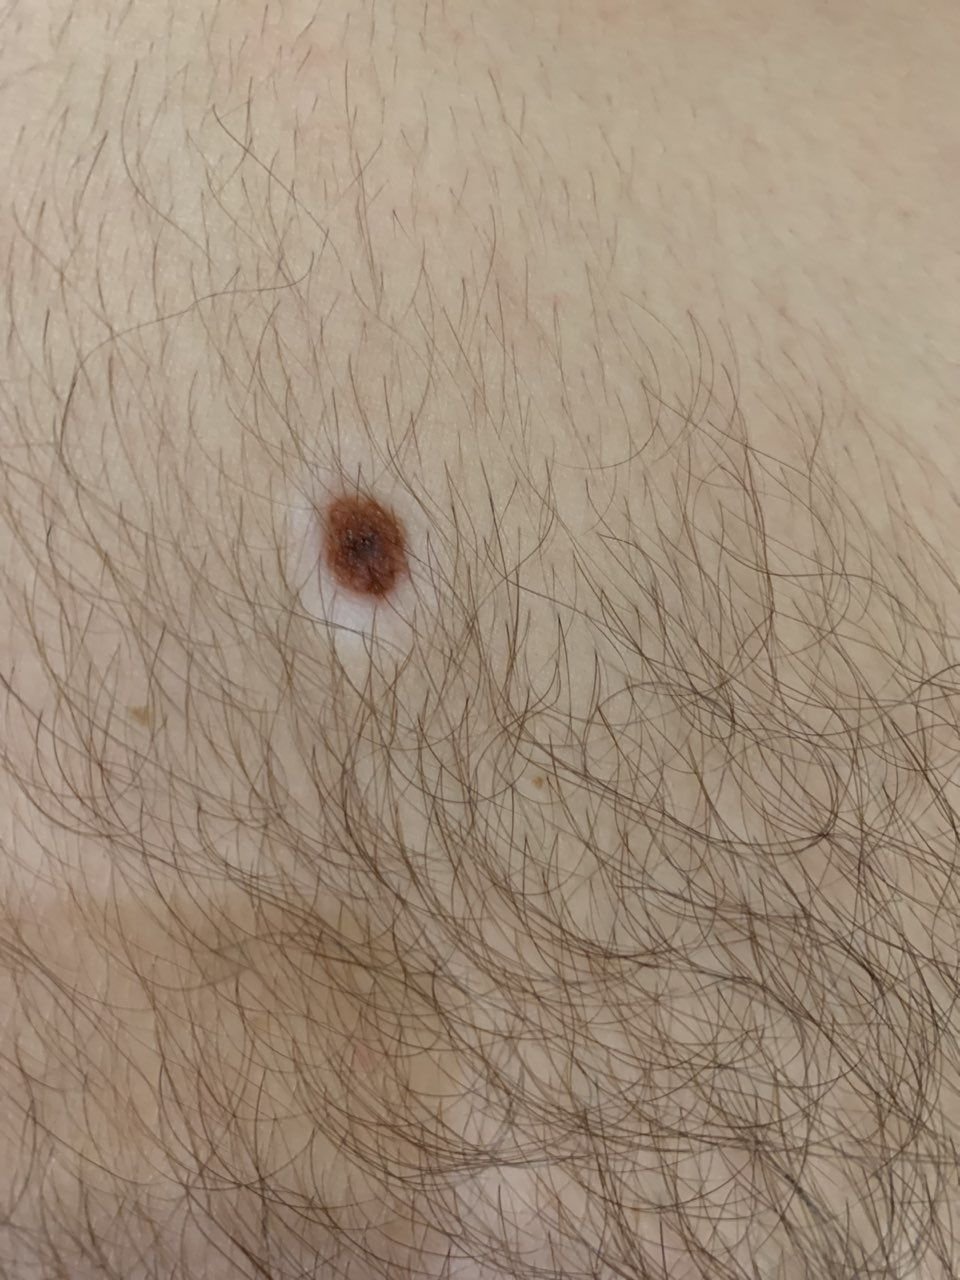
When visually examined, a halo nevus presents as a hemispherical or slightly raised formation, often symmetrical in shape (commonly oval or round). Surrounding the central pigmented area, there is a noticeable ring of hypopigmented skin. This colorless ring typically has a regular oval or round shape and is symmetrical in appearance.
The surface of the central pigmented area of the nevus may appear slightly different from that of the surrounding skin, with a smoother texture or a finely tuberous surface. The skin pattern of the depigmented ring remains unchanged and follows the natural texture of the skin.
The edges of the halo nevus are generally clear and well-defined. The central pigmented area may range in color from flesh-colored or tan to dark brown, with pigment uniformly distributed across the lesion. Sometimes, the intensity of the color gradually decreases from the center towards the periphery, or various shades of the same color may be present within the central area. The surrounding rim is typically colorless, although it can occasionally be light brown or pale pink, sometimes with slight hyperemia. The color of the hypopigmented ring becomes more noticeable and contrasting, especially after tanning.
The presence of a halo nevus does not generally affect hair growth. However, in some cases, the central part of the nevus may have a small amount of coarse bristly or fluffy hair.
The diameter of the central pigmented part of the halo nevus is usually small, not exceeding 10 mm. The total diameter, including the surrounding depigmented ring, can reach 3-4 cm. Over time, the size of the depigmented area may change, either increasing or decreasing. The height of the raised part of the nevus above the skin’s surface typically does not exceed 3-4 mm.
Upon palpation, the halo nevus feels like normal skin or may be slightly softer, particularly in the central pigmented area. There are no subjective sensations associated with the lesion, although mild itching may occasionally occur in rare instances.
Halo nevi are most commonly located on the body, particularly the trunk, but they can occasionally be found on other parts of the body as well.
Dermatoscopic Description
The two features that characterise a halo nevus on dermatoscopy are these:
- Symmetrical Peripheral Depigmentation: A pale ring of even width running right around the central lesion. Its symmetry is the reassuring part.
- Benign Central Pattern: The central nevus shows an organised globular or homogeneous pattern, without asymmetry or multiple colours.
Other findings may be seen in the central pigmented area, but they are non-specific pigmentary changes and do not establish the diagnosis on their own:
- Cobblestone Pattern: A network of oval pigment elements resembling a cobblestone street pattern.
- Papillary Structures: Uneven, tuberous structures that may appear flattened due to pressure during dermatoscopy.
- Globules: Large, hyperpigmented ring structures that are evenly distributed throughout the nevus or concentrated in the center, with gray-brown globules sometimes indicative of hyperkeratosis.
- Spots: Hyperpigmented, structureless areas located in the center of the nevus.
- Pigment Network: A pattern of hypopigmented holes and homogeneous lines ranging from light brown to dark brown, with the lines thinning as they extend toward the periphery.
- Dots: Small, round, hyperpigmented structures that are found at the center or along the pigment lines.
- Vascular Network: A regular, slightly curved, diffuse network of monomorphic vessels.
- Diffuse Uniform Staining: The entire formation may show uniform pigmentation in some cases.
When dermatoscopically examining the depigmented area, it typically appears as normal skin with little to no pigment structures, though a subtle vascular network may be visible.
Differential Diagnosis
Halo nevus should be differentiated from other skin lesions and conditions, including:
- Simple nevus
- Spitz nevus
- Blue nevus
- Vitiligo
- Lichen planus
- Molluscum contagiosum
- Dysplastic nevus
- Basal cell carcinoma
- Melanoma
Risks
Halo nevi are typically benign in children and young adults, but new-onset halo nevi in adults or atypical-appearing lesions warrant clinical evaluation. Signs that warrant evaluation include changes in the appearance of the nevus or new sensations such as itching, pain, or tenderness.
A halo nevus is a benign lesion, and the halo itself does not mean the central nevus is more likely to turn into a melanoma than any other benign nevus. What does matter is that, rarely, a halo can form around a melanoma. So the question is not whether a halo is present but what the central lesion looks like: an atypical, asymmetric, multicoloured or changing centre needs assessment, while a typical halo nevus does not need to be treated as high-risk.
Tactics
A lesion you have not had looked at is a different matter from one a clinician has already identified. Monitoring follows assessment, not the other way round: a newly noticed halo, particularly in an adult, should be examined by a dermatologist. A halo can rarely form around a melanoma, and it is the central lesion that needs looking at.
Once a lesion has been assessed as a typical halo nevus, watching it between reviews is reasonable. Go back sooner if the central nevus becomes asymmetric, develops more than one colour, changes shape, bleeds, or becomes painful or itchy.
The healthcare provider will assess whether further dynamic monitoring is needed or if the nevus should be removed. Nevi that are subject to chronic trauma from clothing, jewelry, or occupation should be removed to prevent further irritation or potential complications.
Where a lesion is being followed, photographing it helps detect minor change over time. Neither frequent routine examinations nor scheduled digital dermatoscopy is necessary for every typical halo nevus. A full skin examination is particularly worthwhile in an adult who develops a halo nevus, and an atypical lesion should be assessed on its own merits. Mapping of skin lesions is not needed routinely. Mapping remains a reasonable option for someone at high risk — a patient with many atypical or dysplastic nevi, or with a previous melanoma — where it is decided individually.
Treatment
Halo nevus is usually monitored clinically; excision is reserved for atypical or suspicious lesions, performed with either a classic scalpel or a radiofrequency scalpel. A histological examination of the excised tissue is necessary to ensure the lesion is benign.
Destructive methods such as laser removal or cryodestruction are not recommended for halo nevi due to the risk of relapse and incomplete removal.
Prevention
Preventing the appearance of halo nevi and minimizing their risk of malignancy requires careful skin care:
- Avoidance of excessive ultraviolet radiation, including the use of tanning beds and prolonged sun exposure.
- Application of sunscreen and protective clothing during periods of high sun exposure.
- Avoiding chronic skin trauma that can result from friction, pressure, or irritation.
- Following safety protocols when handling skin-damaging agents.
- Maintaining good personal hygiene and regularly monitoring the skin for changes.
It is essential to regularly inspect halo nevi, seek prompt consultation with a healthcare professional if any changes are noticed, and remove potentially dangerous lesions when needed.