
Onychomycosis (ICD-10: B35.1) 🚨
Onychomycosis: Fungal Infection of the Nail Plate
Overview
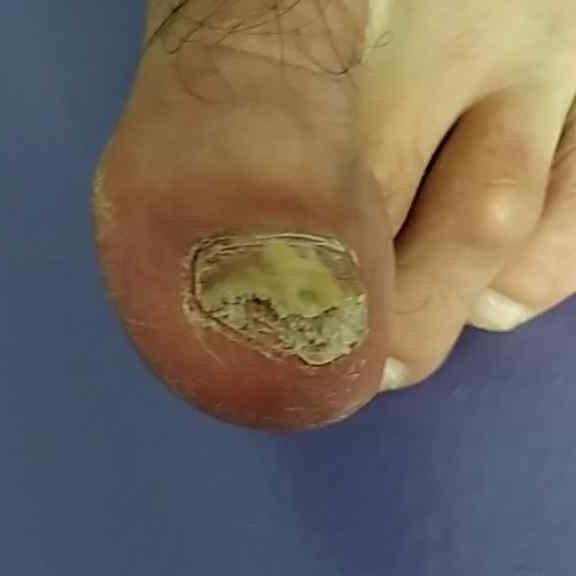
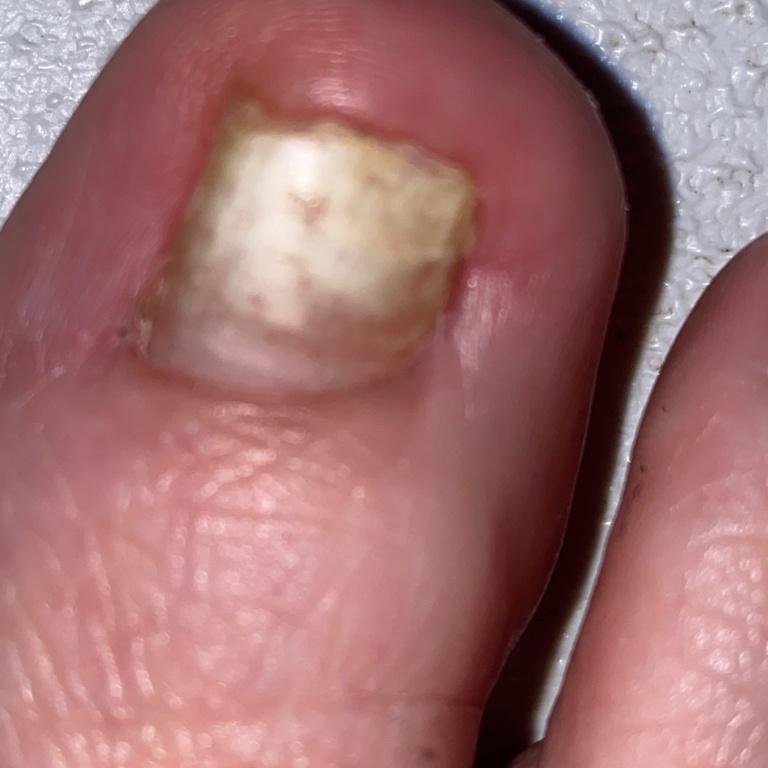
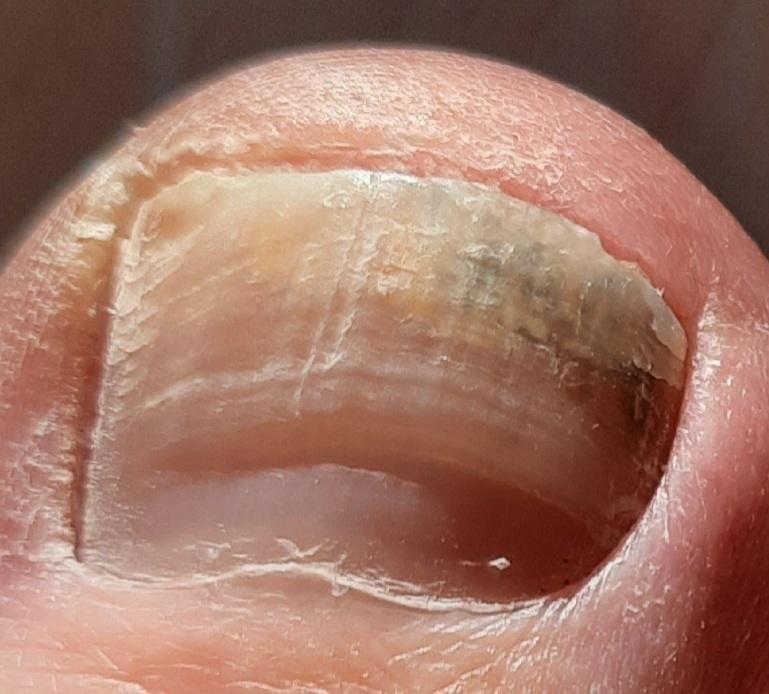
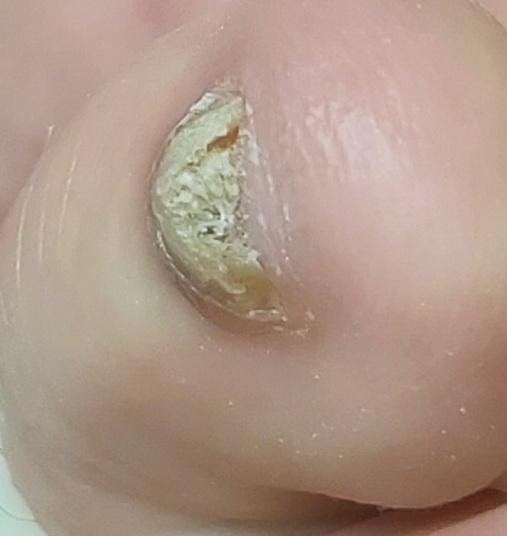
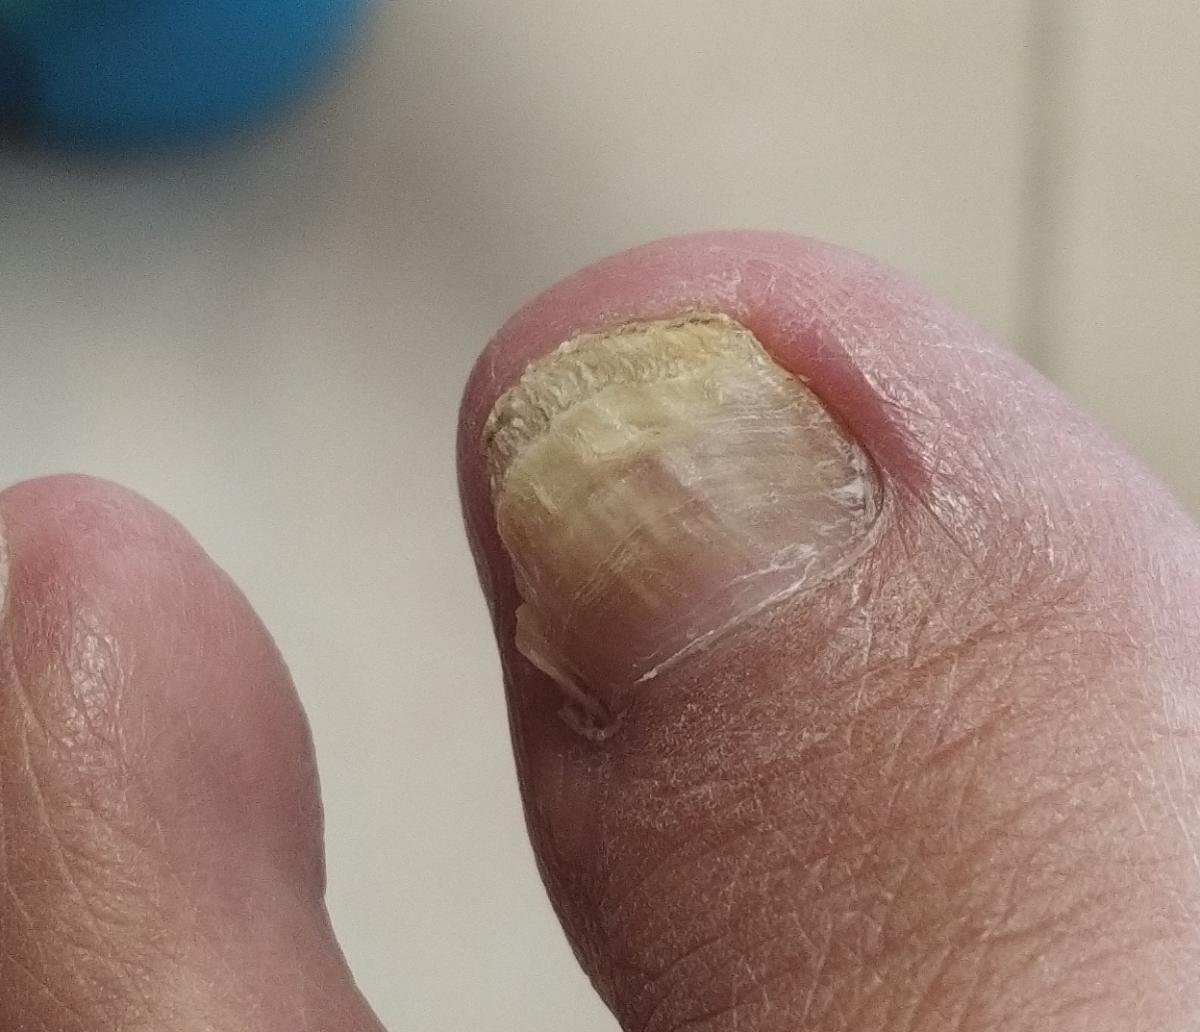
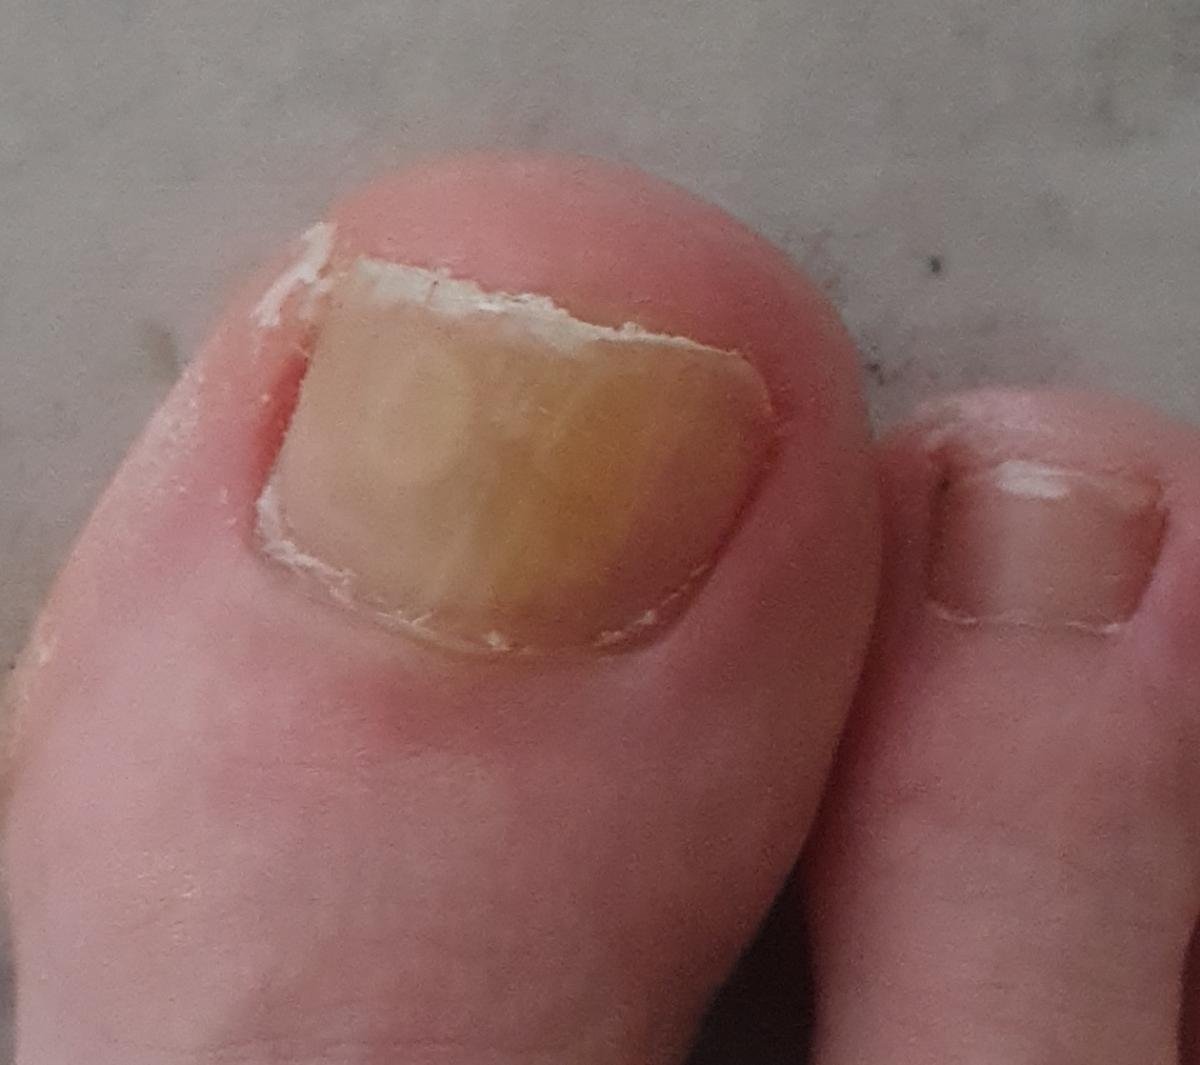
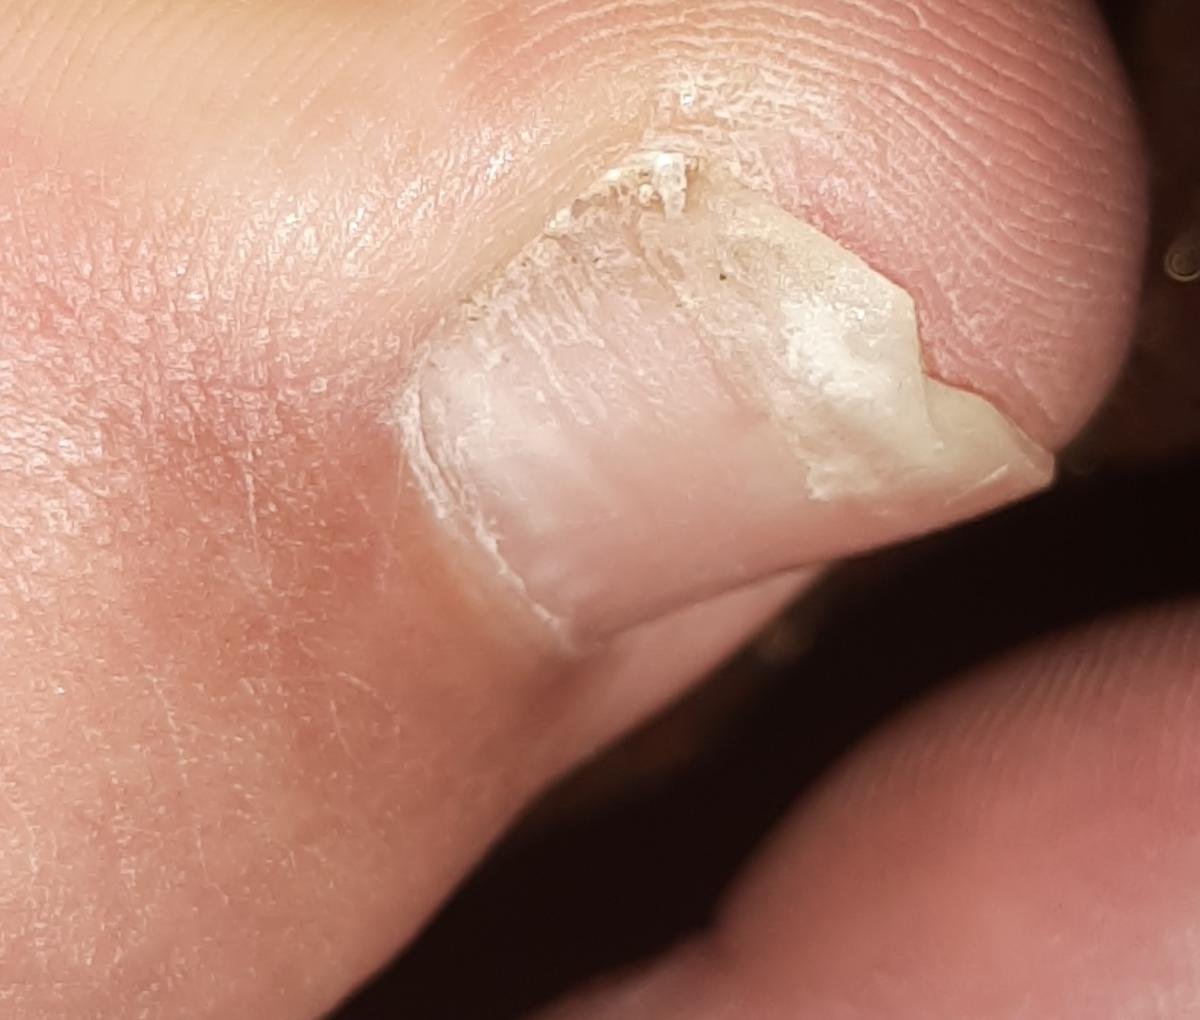
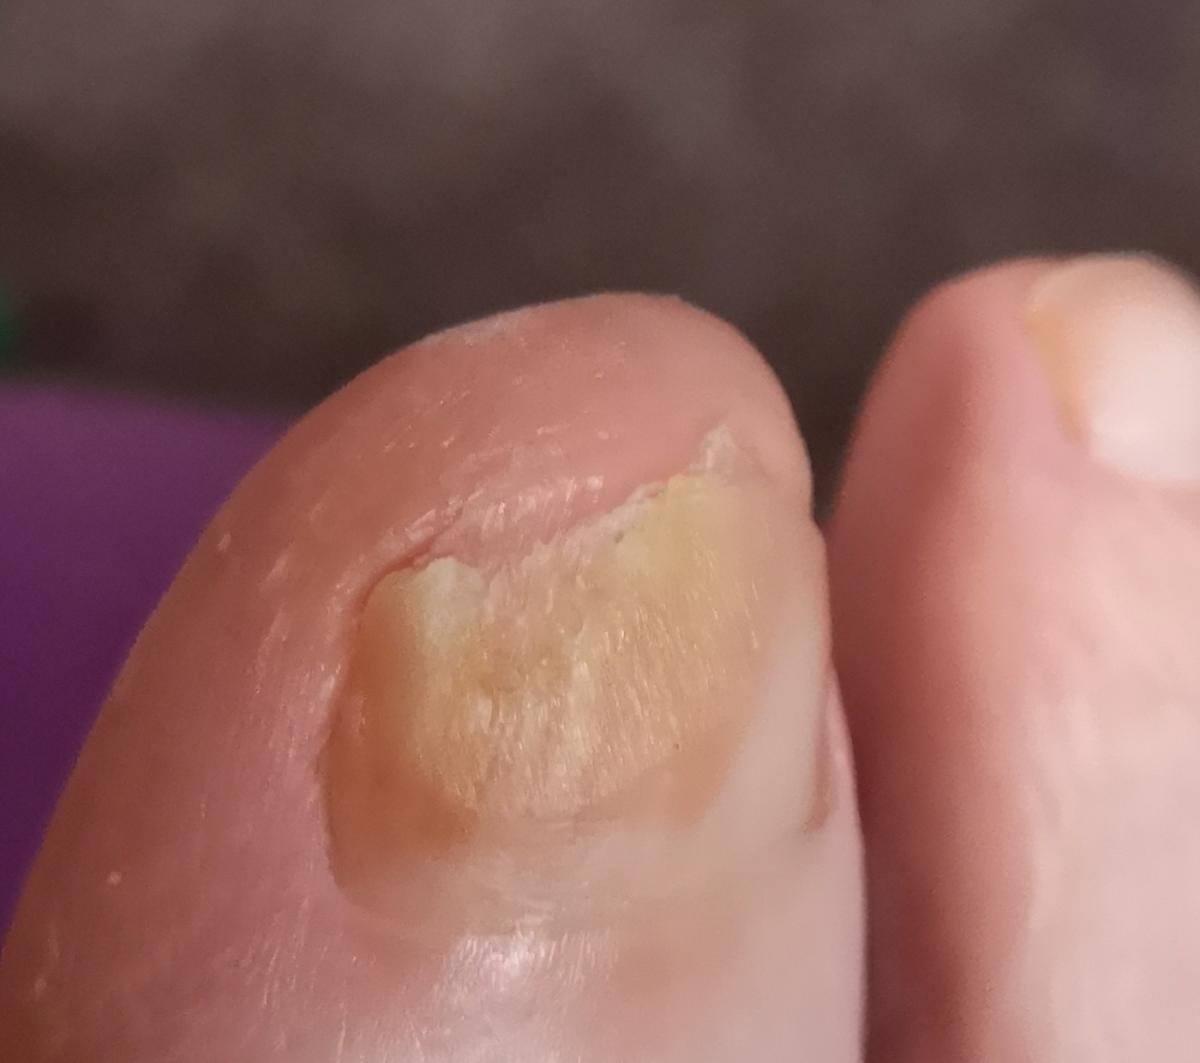
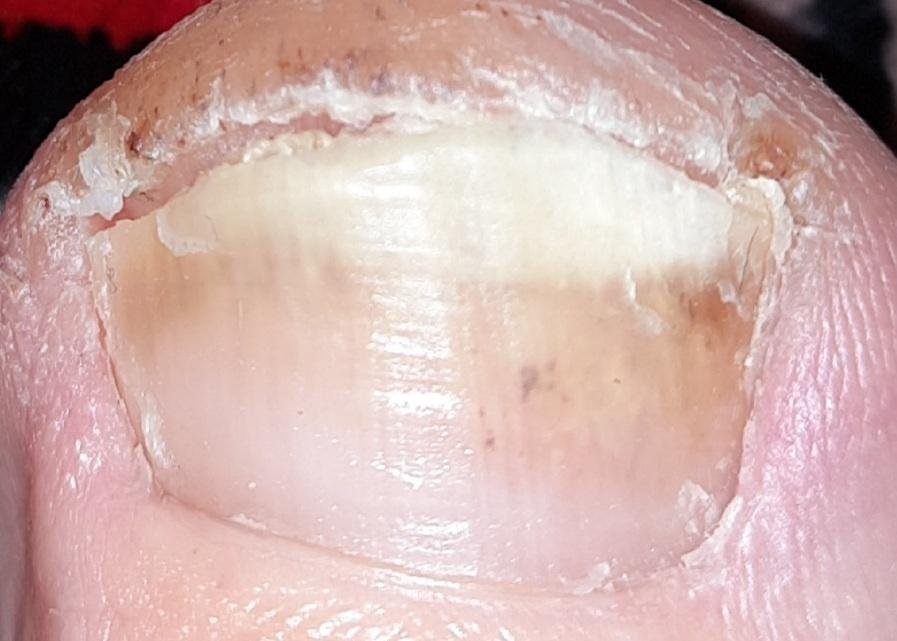
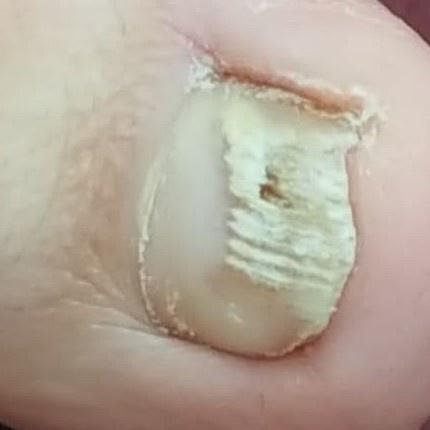
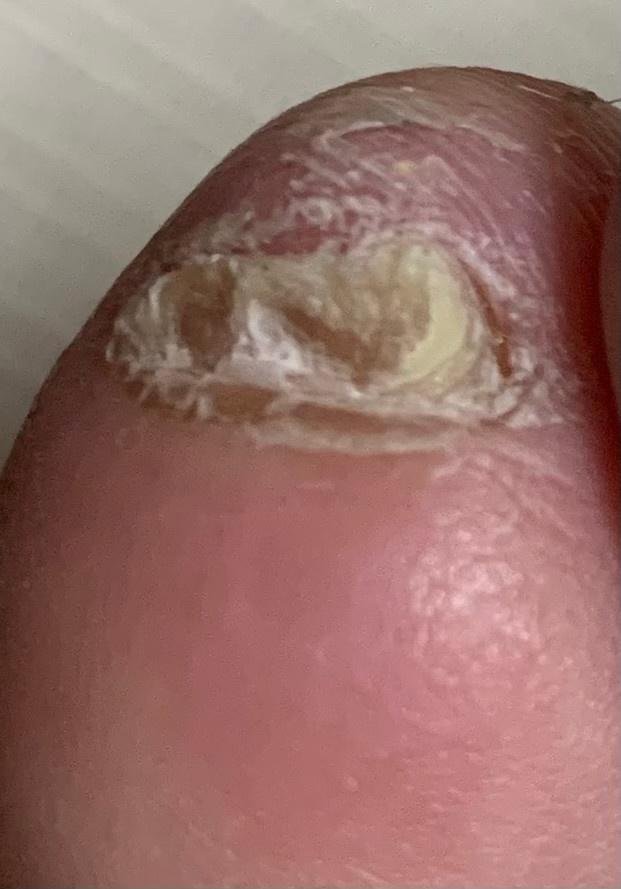
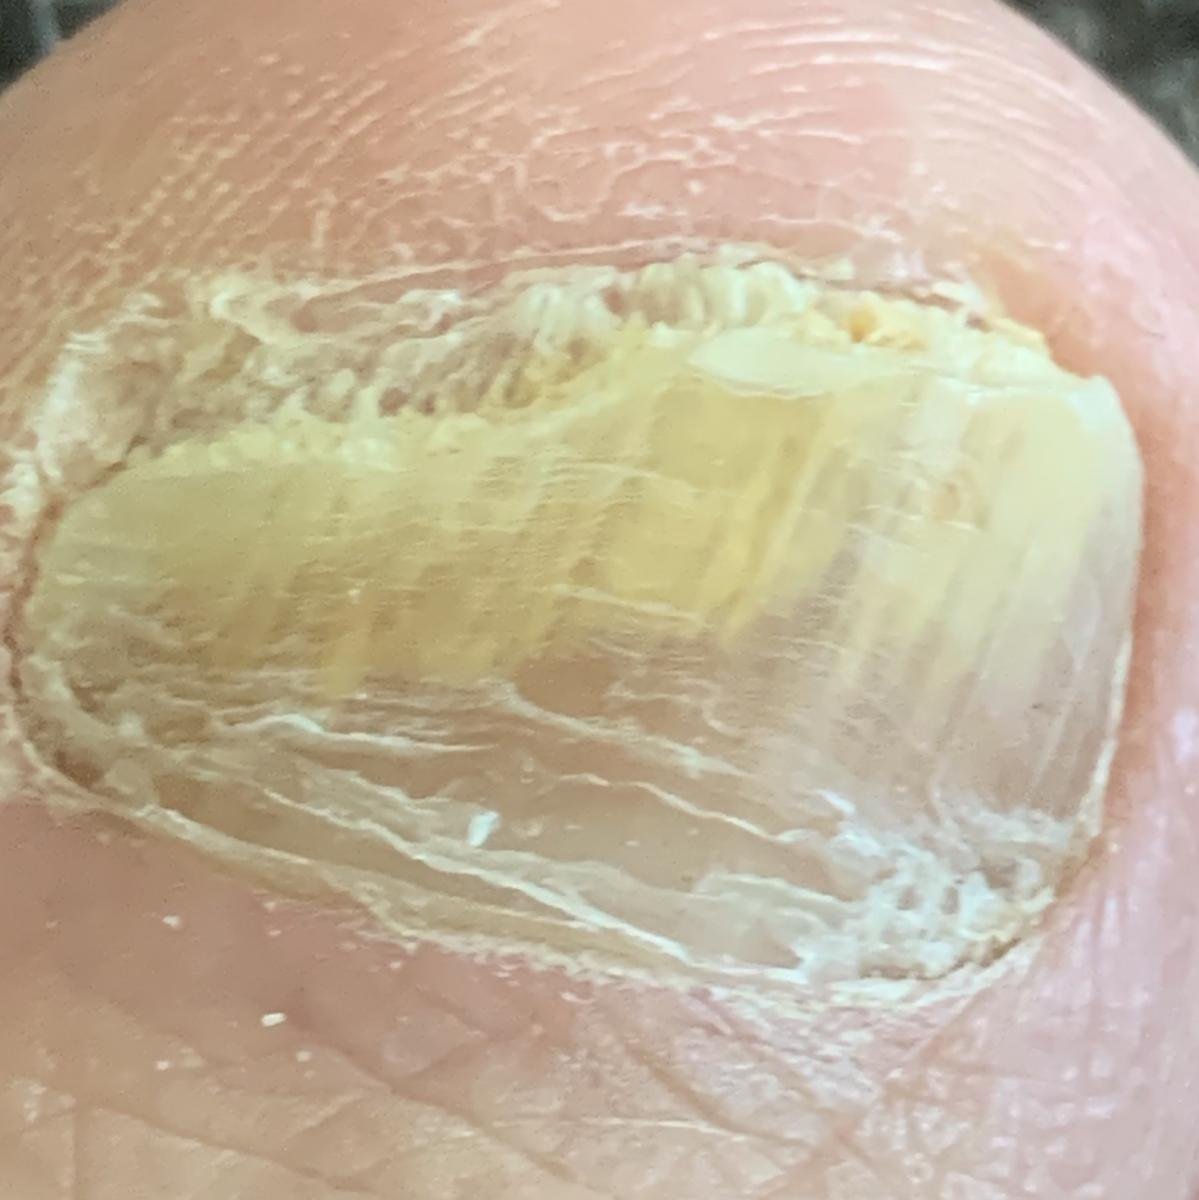
Onychomycosis is a chronic fungal infection of the nail unit, including the nail plate, nail bed, and sometimes the surrounding skin. It is caused by dermatophytes, non-dermatophyte molds, or yeasts (primarily Candida species). This condition is among the most common nail disorders worldwide and represents up to 50% of all nail diseases.
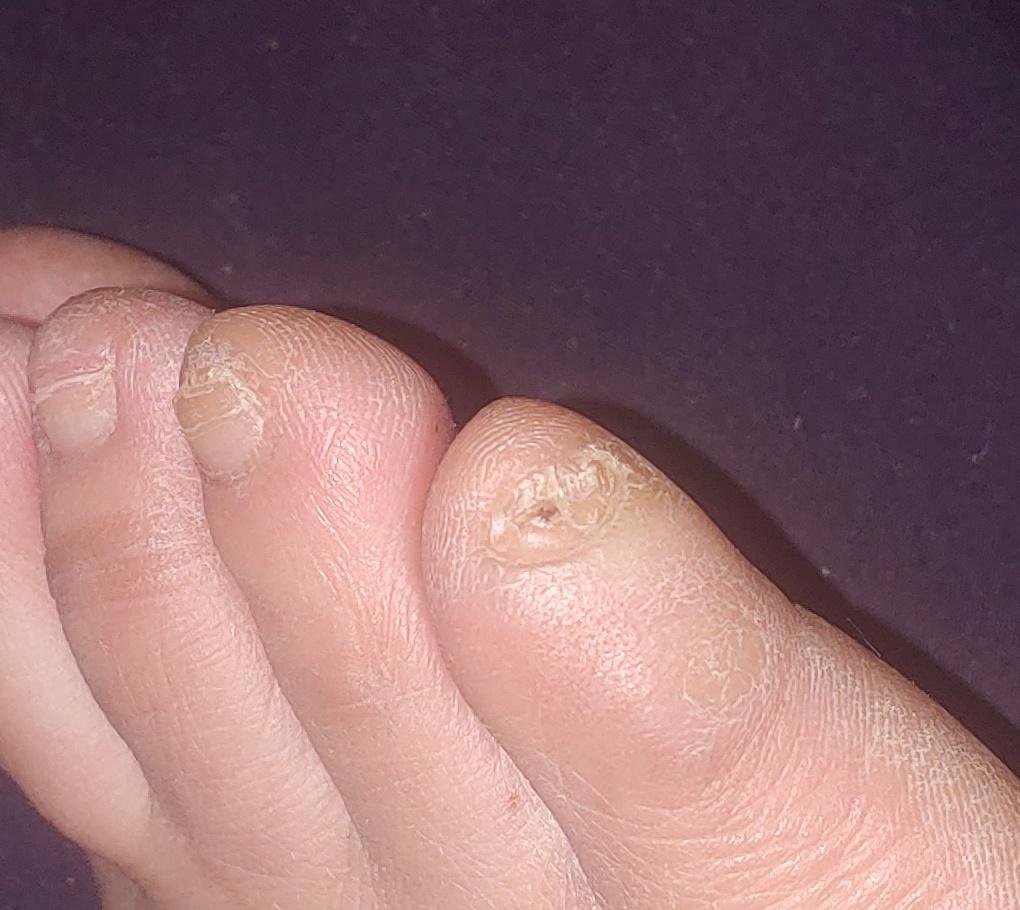
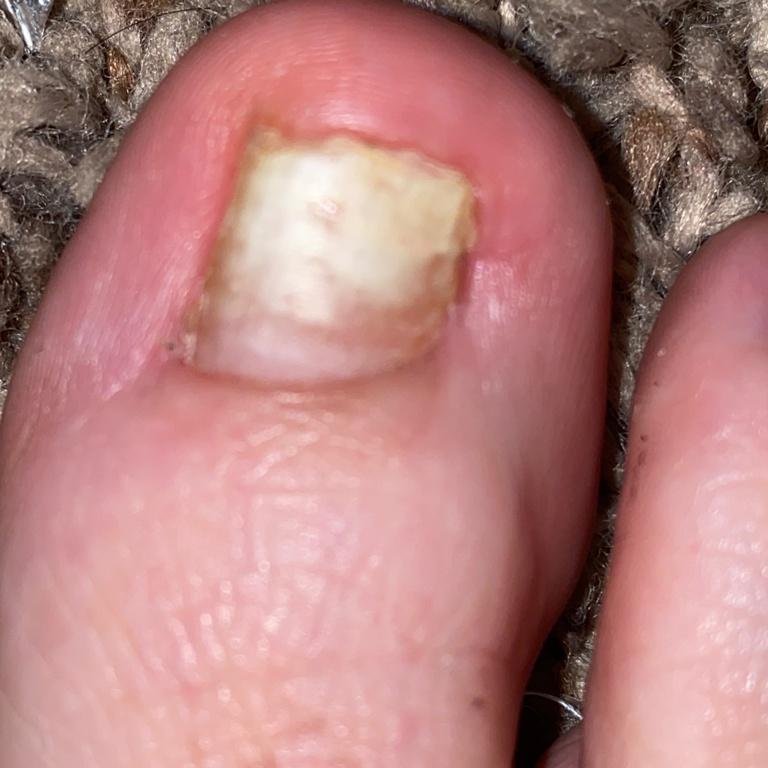
The disease affects individuals of all ages but is more common in adults and the elderly, particularly those with underlying health conditions such as diabetes, peripheral vascular disease, or immunosuppression. Onychomycosis often presents as discoloration, thickening, deformation, or crumbling of the nail, and may affect one or multiple nails, typically starting on the toenails and potentially spreading to fingernails.
Without treatment, onychomycosis can cause significant discomfort, secondary bacterial infections, and cosmetic dissatisfaction. It is also a common source of recurrent fungal transmission to other body areas or family members.
Clinical Forms of Onychomycosis
Onychomycosis presents in several clinical patterns, depending on the route of fungal invasion and location of infection within the nail unit:
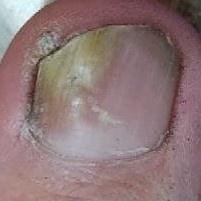
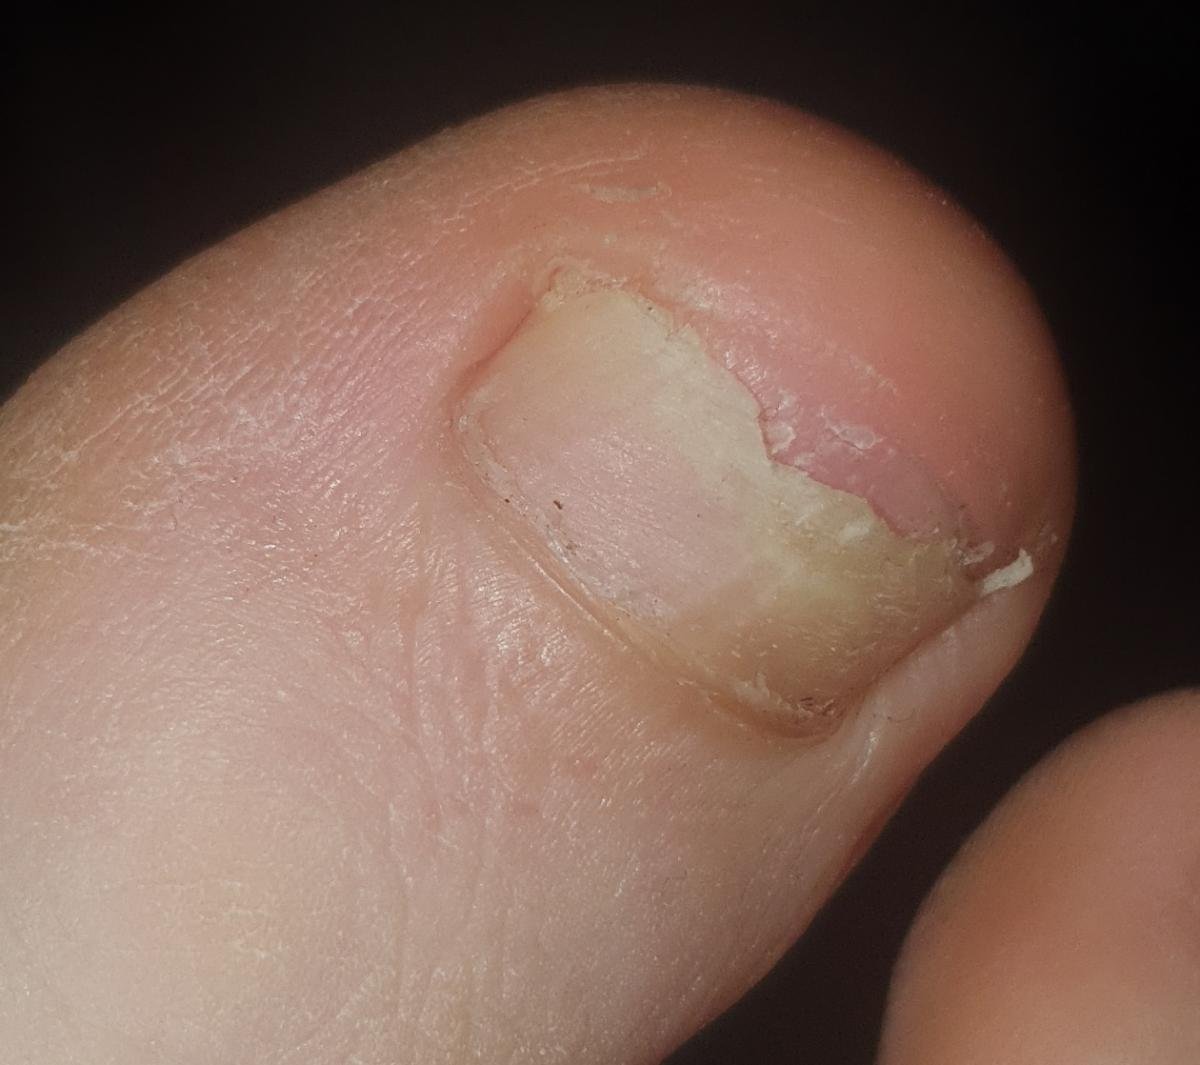
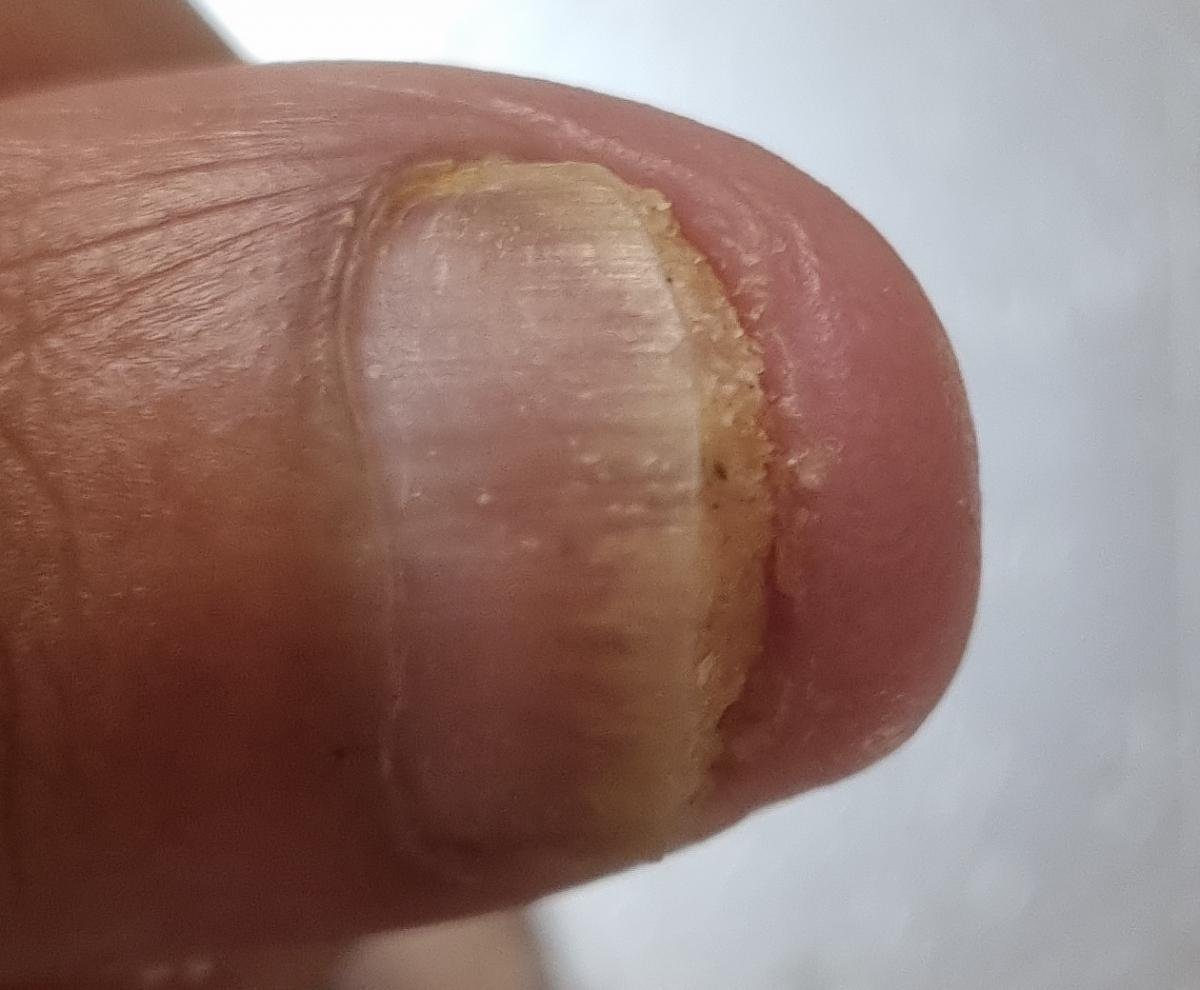
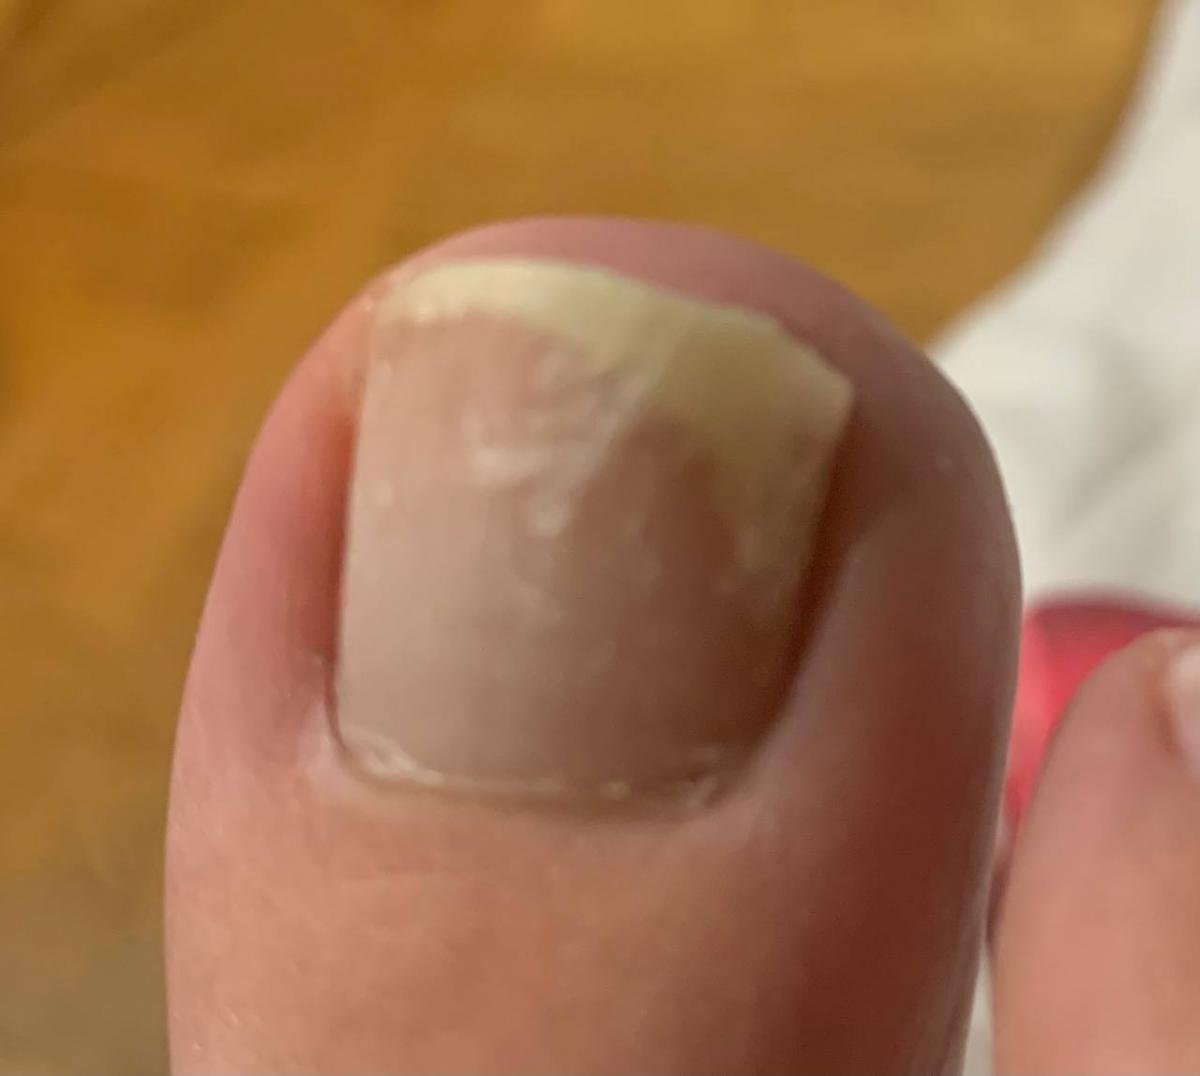
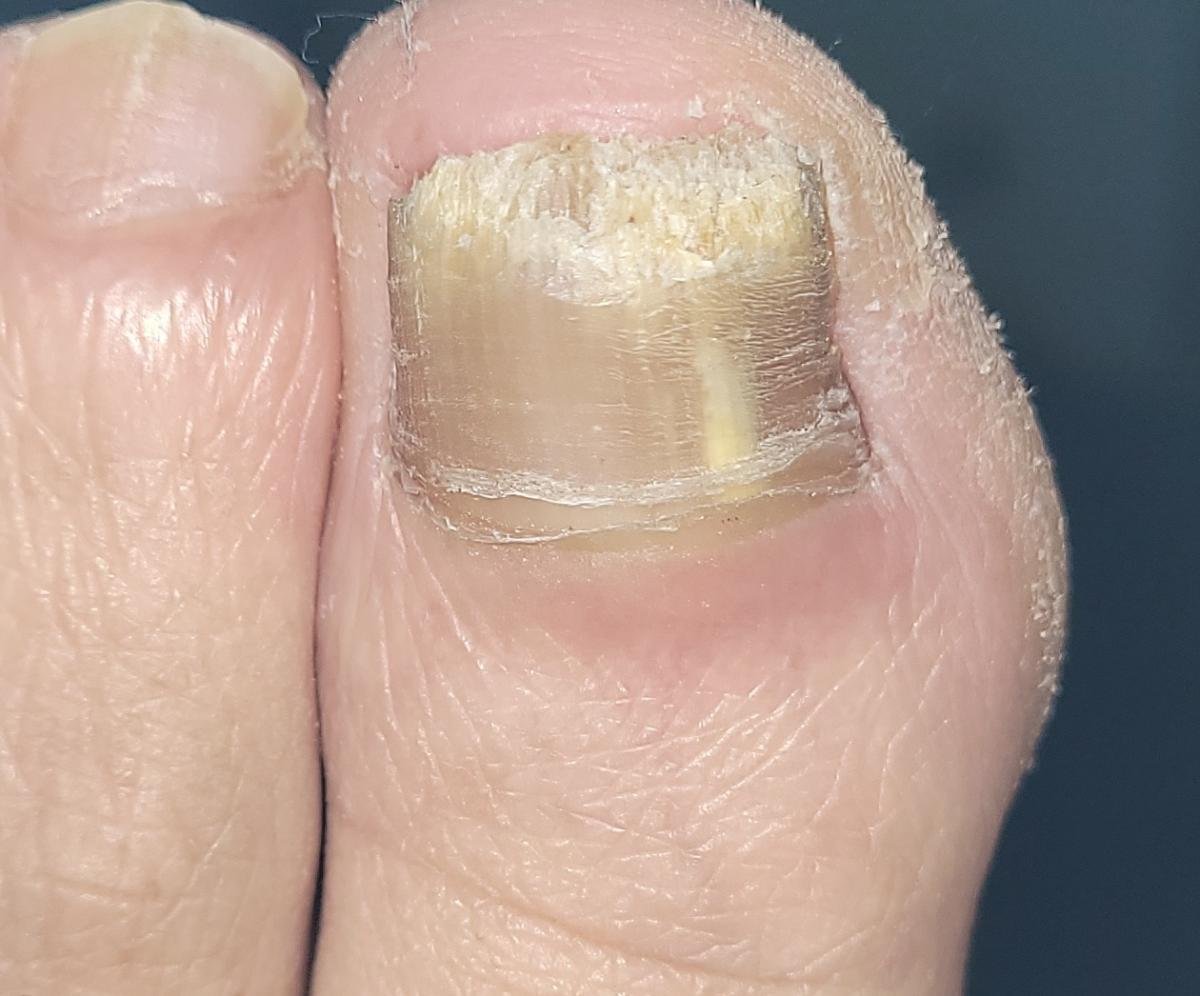
- Distal (Lateral) Subungual Onychomycosis: The most frequent form. Infection begins at the hyponychium or lateral nail fold and progresses proximally along the nail bed. Characterized by yellow-white discoloration, thickening, subungual debris, and eventual detachment (onycholysis);
- Proximal Subungual Onychomycosis: Less common; occurs when fungi penetrate the nail matrix via the proximal nail fold. It is more often observed in immunocompromised individuals. Early signs include discoloration near the lunula and proximal plate distortion;
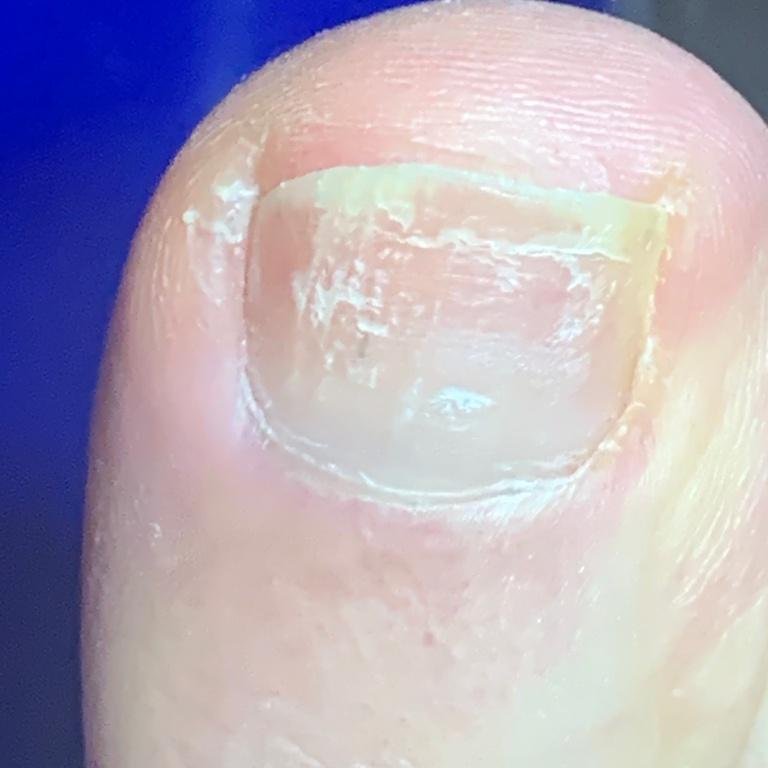
- White Superficial Onychomycosis: Fungi directly invade the superficial nail plate, causing the formation of white, chalky, or dull yellow spots on the surface. These spots may coalesce, leading to fragility and brittleness of the nail.
Classification by Nail Plate Involvement
Based on the appearance and thickness of the nail plate, onychomycosis can be categorized into:
- Normotrophic: The nail retains its normal thickness and shape but shows discoloration (yellow, white, or brownish areas) with minor surface changes;
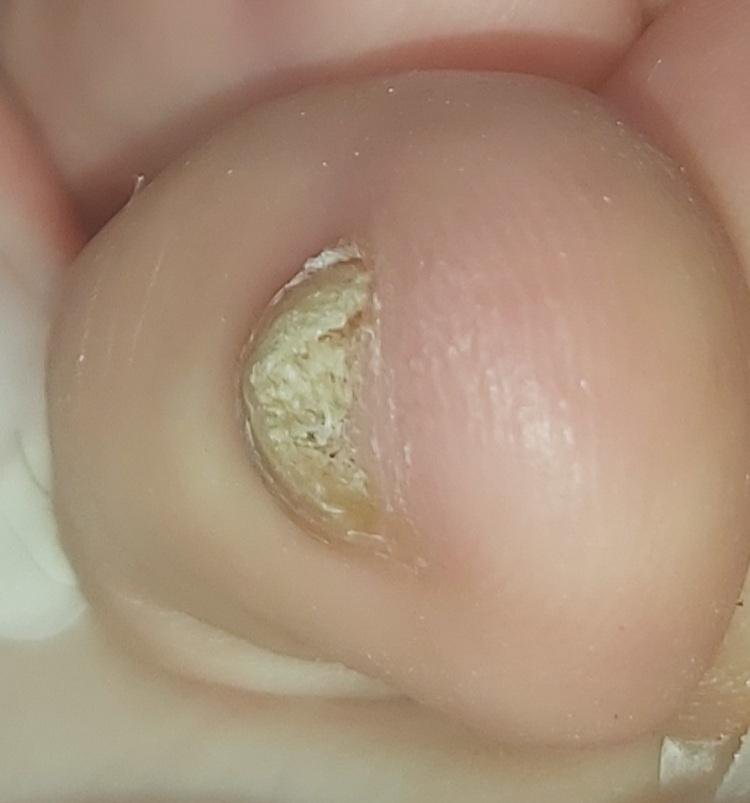
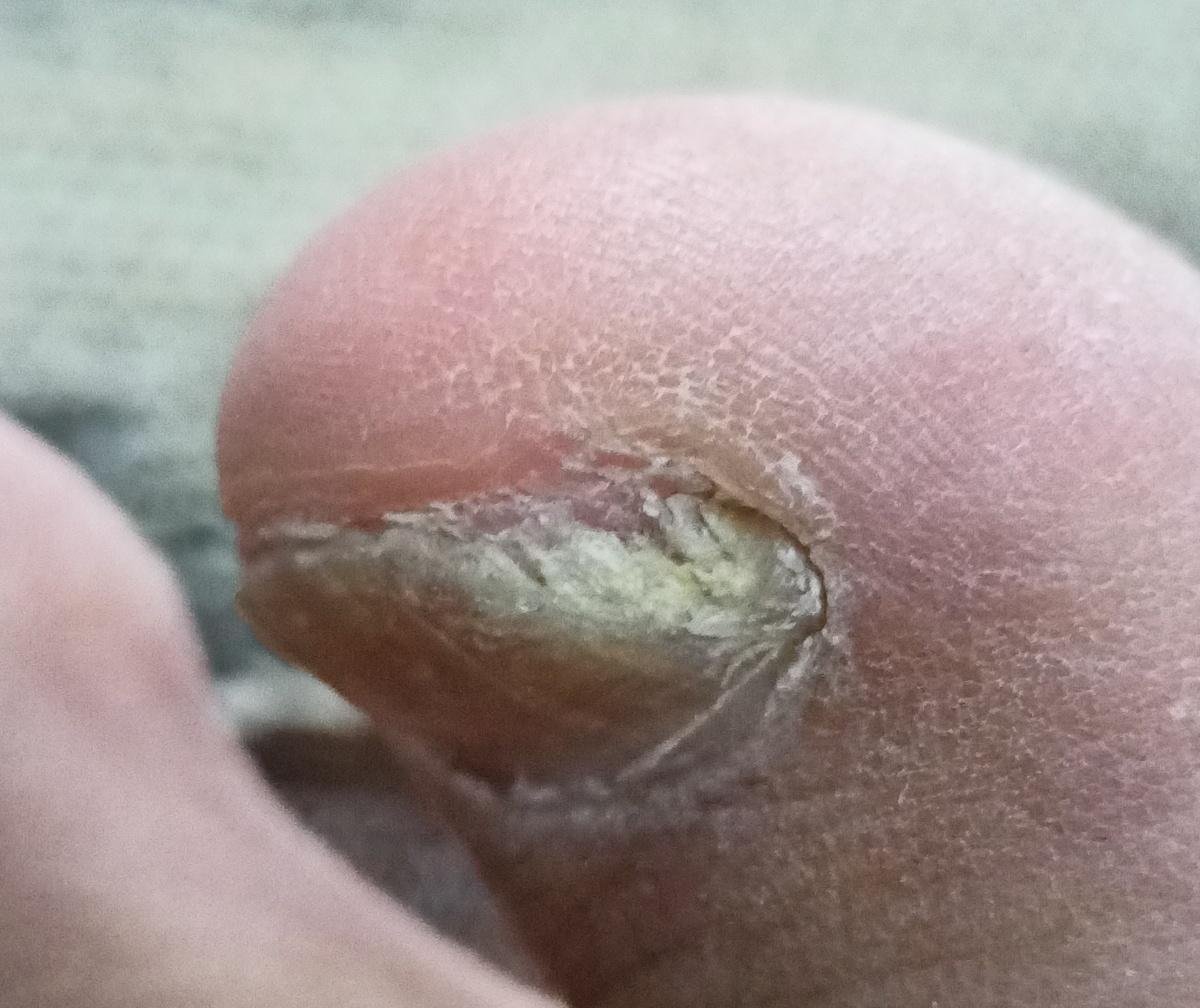
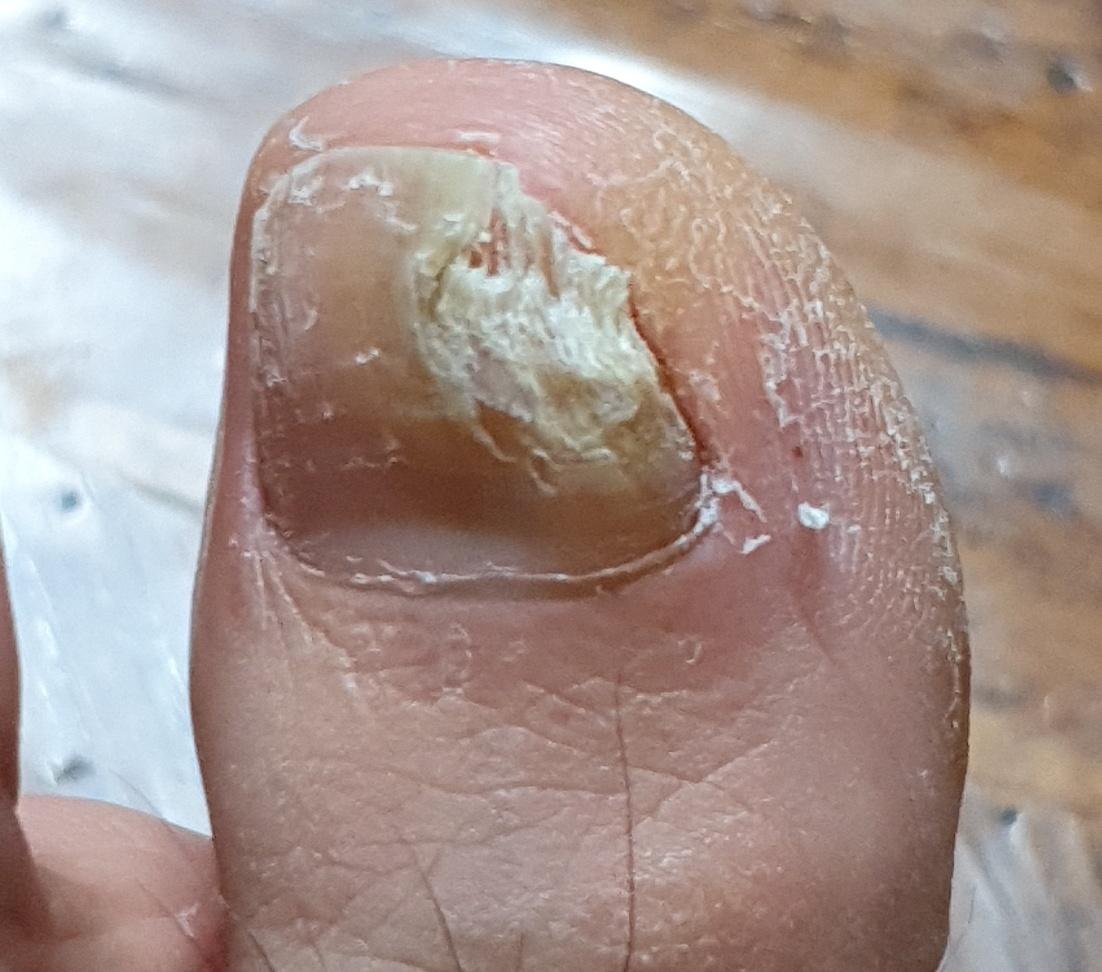
- Hypertrophic: Characterized by nail thickening, subungual hyperkeratosis, deformation, and development of longitudinal ridges. The underlying nail bed may also become hypertrophic and painful;
- Atrophic: The infected nail becomes thinned, fragile, and often detaches partially or completely from the nail bed (onycholysis).
Diagnosis of Onychomycosis
Accurate diagnosis is essential before initiating antifungal therapy, as several other conditions can mimic fungal nail disease. Clinical evaluation should be supported by laboratory confirmation to identify the specific fungal pathogen and exclude differential diagnoses (e.g., psoriasis, trauma, lichen planus).
Recommended diagnostic methods include:
- Clinical examination: Evaluation of nail color, texture, thickness, and involvement of other skin areas (e.g., tinea pedis);
- Dermatoscopy: Aids in visualizing characteristic features such as spikes, longitudinal striae, and subungual debris;
- Nail clipping for histology: PAS staining of a clipping, or PCR, where microscopy and culture are inconclusive;
- Microscopy: Direct KOH (potassium hydroxide) examination of nail scrapings for hyphae;
- Culture: Fungal cultures are useful for identifying dermatophytes, yeasts, or molds;
- PCR (Polymerase Chain Reaction): Highly sensitive and specific method to detect and type fungal DNA, especially in difficult or recurrent cases.
Treatment of Onychomycosis
The treatment of onychomycosis is prolonged. Combination therapy is not routinely required: oral terbinafine is generally preferred for moderate to severe disease, while topical agents are reasonable for limited or mild disease and where systemic treatment is unsuitable. The options are systemic and topical antifungal therapies. Successful management depends on accurate diagnosis, the extent of nail involvement, the type of pathogen, and the patient’s overall health.
Systemic Antifungal Therapy
Systemic (oral) treatment is generally considered the standard of care in moderate to severe cases, particularly when:
- More than 50% of the nail plate is affected;
- Multiple nails are involved (especially >3 toenails);
- The matrix or proximal nail is involved;
- Topical treatments have failed or are impractical;
- The patient is immunocompromised or has diabetes;
- There is concurrent tinea pedis or tinea manuum, which is treated alongside the nail rather than being in itself a reason for systemic therapy.
Common systemic antifungal agents include:
- Terbinafine, generally the preferred oral agent, taken for some weeks for fingernails and longer for toenails;
- Itraconazole, sometimes given as pulse therapy;
- Fluconazole, used off-label in some countries. Dosing and duration are set by the prescriber.
Oral terbinafine warrants a baseline check of liver function; whether further monitoring is needed is decided individually, and matters most in patients with pre-existing hepatic disease, alcohol use, or those on hepatotoxic medications.
Topical Antifungal Therapy
Topical treatments may be effective for superficial, distal, or limited onychomycosis, especially when the nail matrix is not involved. These are also suitable for patients with contraindications to oral antifungals.
Commonly used agents include:
- Ciclopirox 8% lacquer: Applied daily; nail surface must be filed weekly;
- Efinaconazole 10% solution: Once daily for 48 weeks; does not require nail filing;
- Tavaborole 5% solution: Once daily; approved for distal lateral subungual onychomycosis.
Combining an oral and a topical agent is sometimes chosen in extensive disease, where the aim is both clearance and relapse prevention.
Prevention of Onychomycosis and Relapse
Because fungal spores persist in the environment, reinfection and relapse are common. Long-term management includes preventive measures to reduce recurrence and minimize exposure to risk factors.
- Foot hygiene: Keep feet clean and dry; change socks daily; alternate shoes to allow airing;
- Footwear care: Use antifungal sprays or powders in shoes; avoid tight-fitting or non-breathable footwear;
- Public space precautions: Wear sandals in communal showers, swimming pools, gyms, and saunas;
- Avoid shared nail care tools: Use personal nail clippers and files; ensure sterile instruments during pedicures/manicures;
- Manage comorbidities: Control diabetes and vascular conditions to reduce susceptibility;
- Regular nail trimming: Keep nails short and smooth to avoid trauma and reduce fungal penetration;
- Follow-up after treatment: Follow-up is mainly clinical, and slow: a nail takes months to grow out, so progress is judged by the new nail at the base. Repeat testing is reserved for disease that persists, recurs or stays diagnostically uncertain.
Conclusion
Onychomycosis is a common but often underestimated infection of the nail unit that can cause significant functional, cosmetic, and psychological burden. Early diagnosis, appropriate treatment selection, and adherence to therapy are crucial for successful outcomes. Treatment chosen for the extent of disease, together with the foot-care measures above, gives the best long-term results.
Given the chronic nature and recurrence potential of onychomycosis, preventive strategies and patient education remain cornerstones of management. Individuals should work closely with dermatologists or podiatrists to ensure accurate diagnosis, safe therapy, and long-term nail health maintenance.

Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)