
Skin Mycoses (ICD-10: B35) 🚨
Cutaneous Mycoses: Dermatophytoses, Candidiasis, and Tinea Versicolor
Overview
Skin mycoses are a group of common fungal infections affecting the epidermis, hair follicles, nails, and skin appendages. They are predominantly caused by dermatophytes (filamentous fungi from the genera Trichophyton, Microsporum, Epidermophyton), yeasts of the genus Candida, and lipophilic fungi such as Malassezia. The dermatophytes are widespread in the environment and readily transmissible, while Malassezia is a normal inhabitant of human skin and the conditions it causes are not caught from other people. Dermatophytes spread through direct contact with infected people, animals, or contaminated surfaces.
Dermatophytes are further classified by their preferred reservoir:
- Geophilic: Reside in the soil; transmitted via environmental exposure;
- Zoophilic: Found in animals; transmitted through direct or indirect contact with infected hair or skin;
- Anthropophilic: Human-specific fungi; spread easily through skin-to-skin contact or shared objects (combs, towels, clothing).
Common Dermatophytoses
Tinea Corporis (Ringworm of the Body)
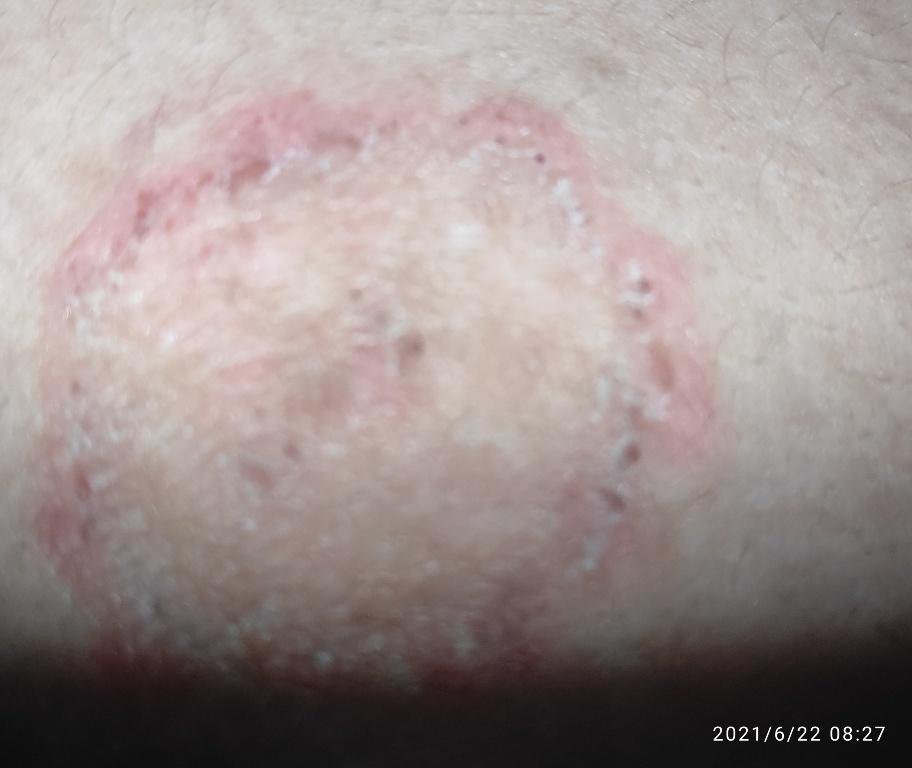
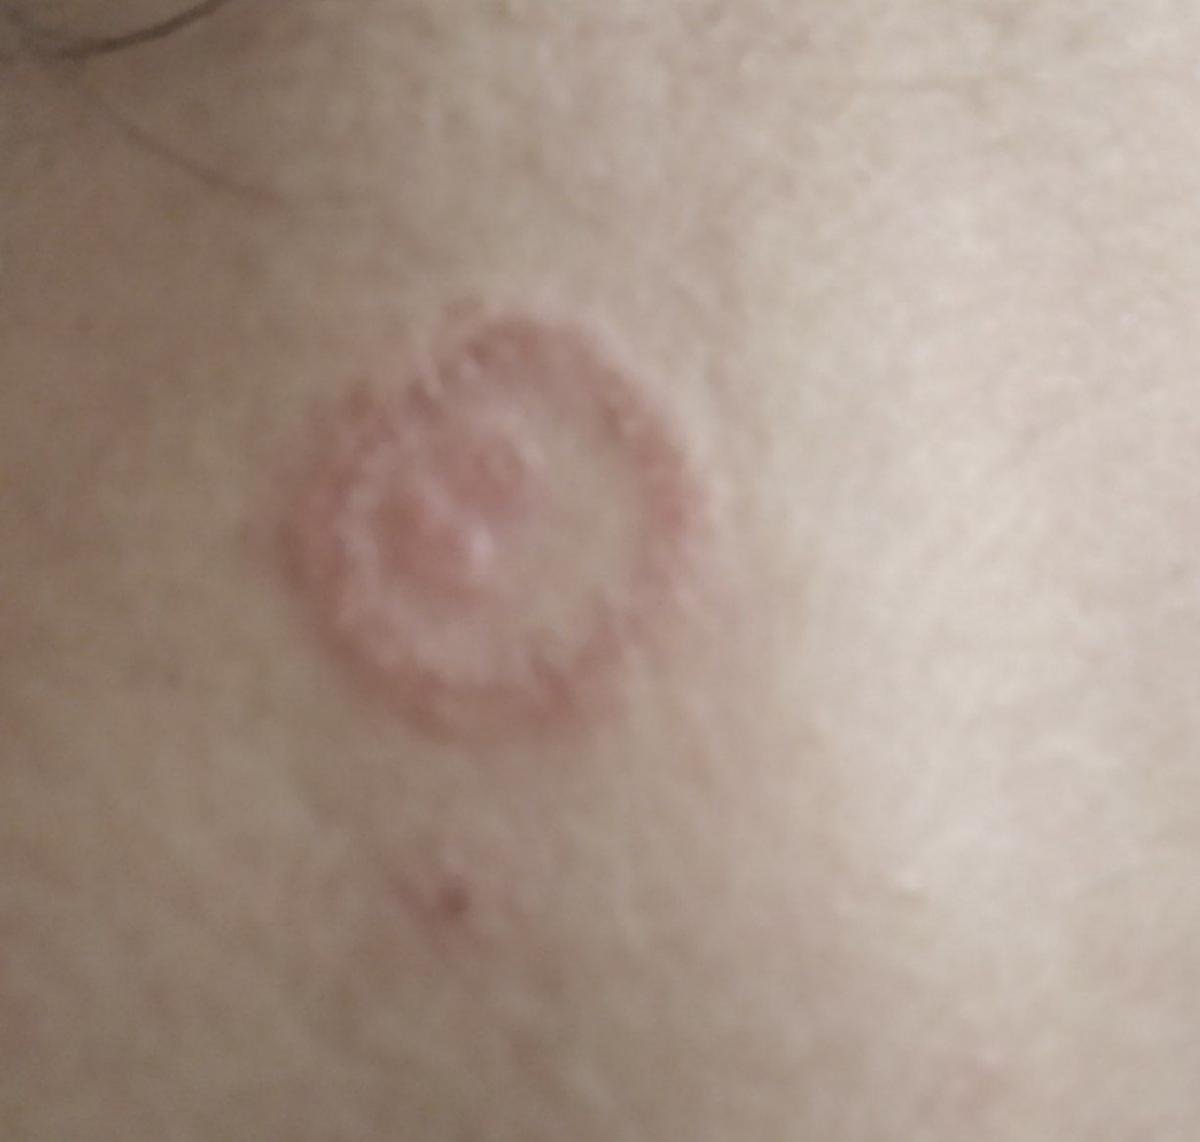
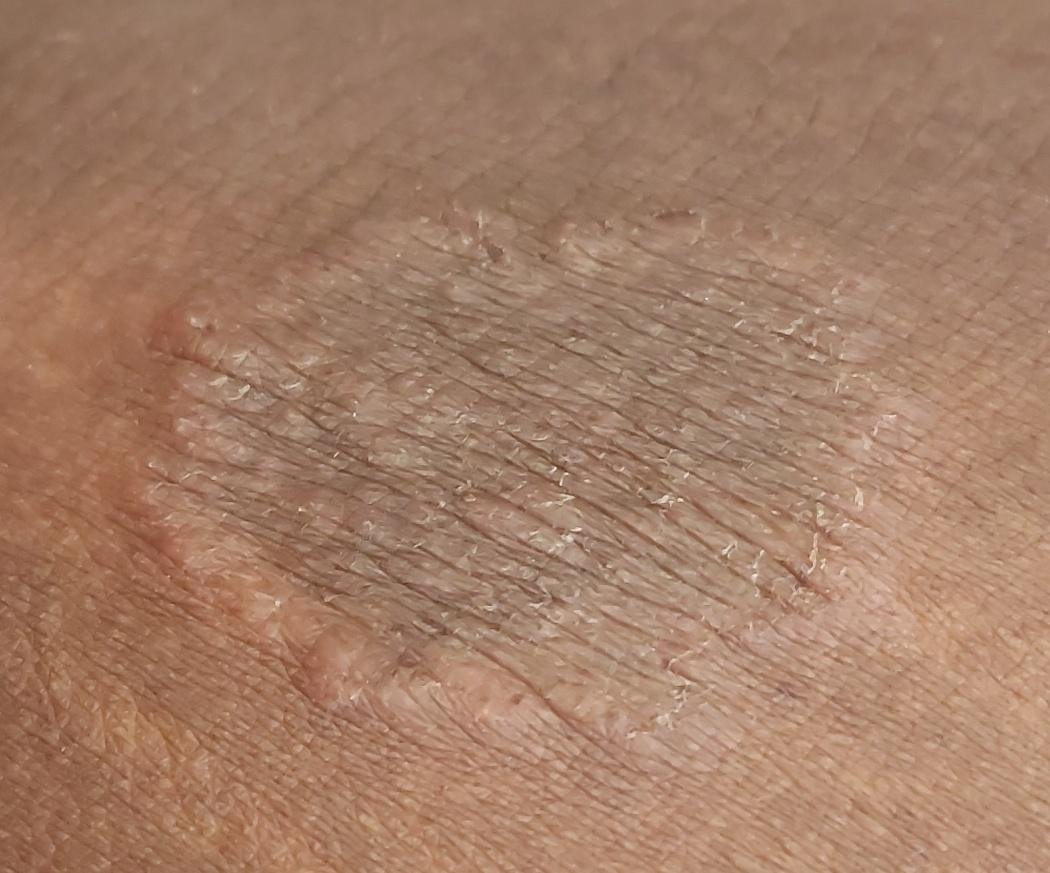
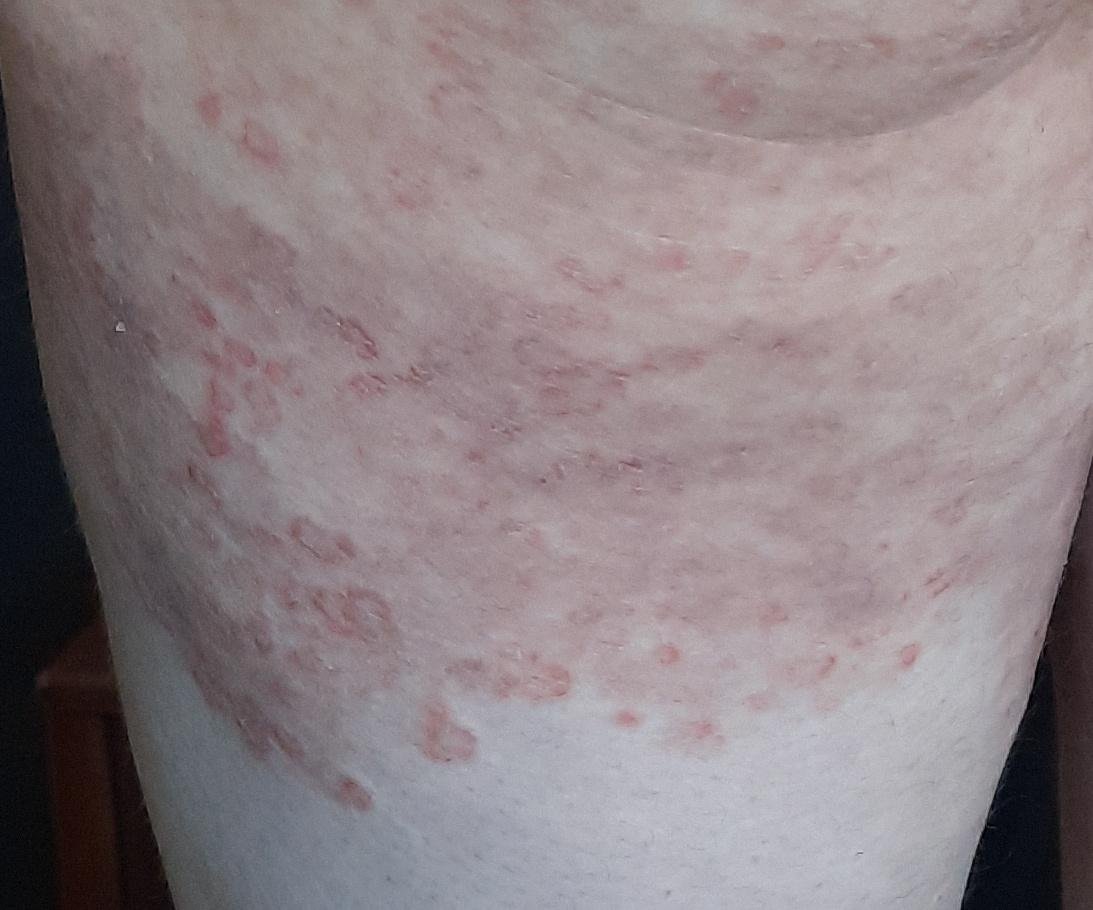
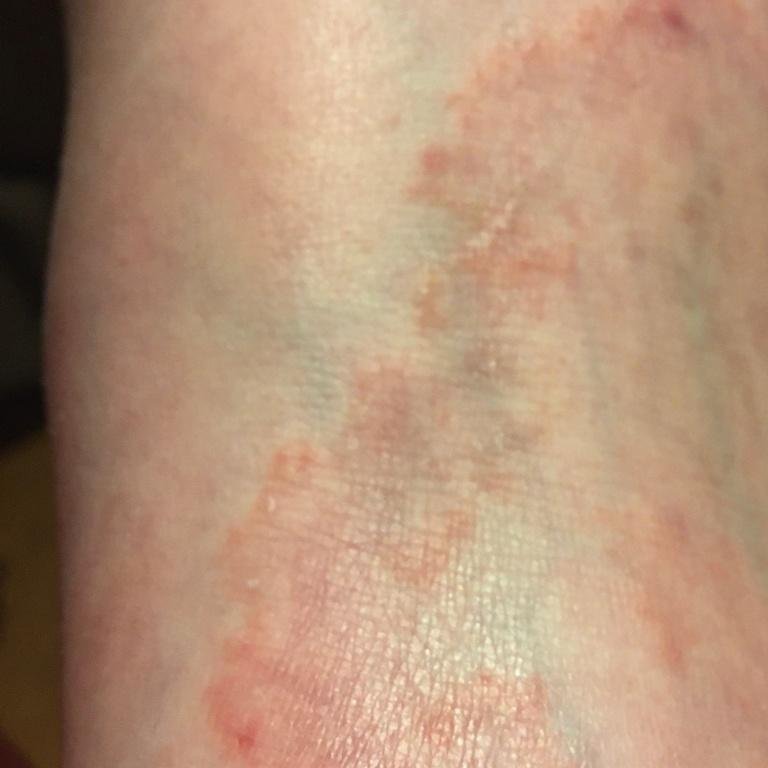
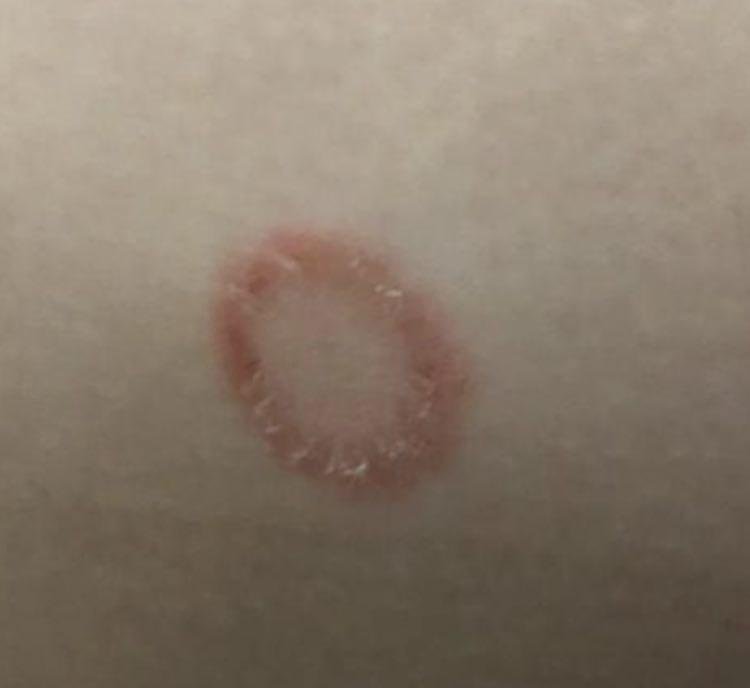
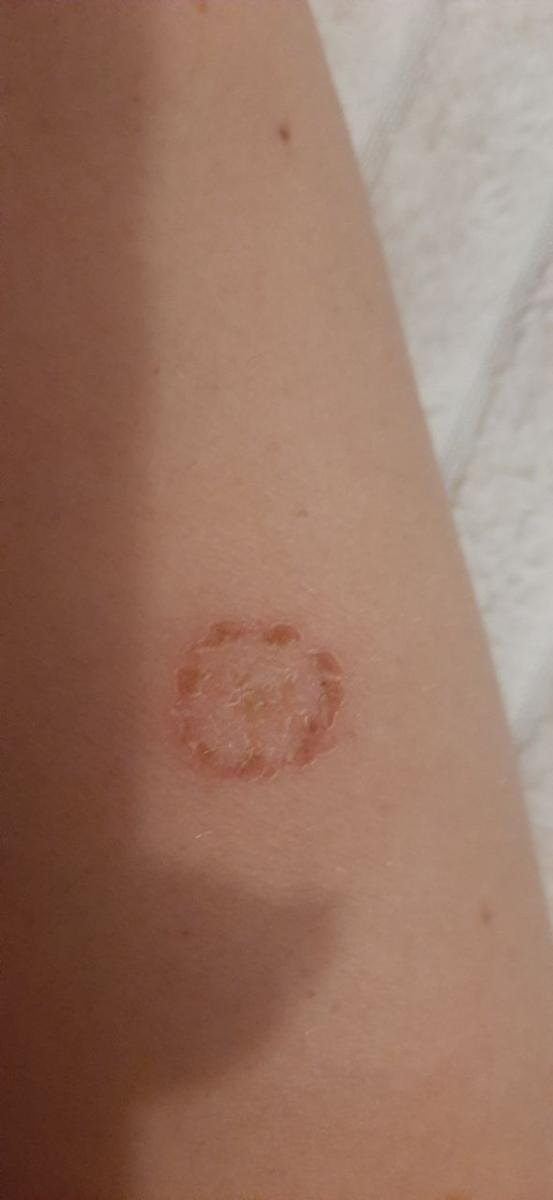
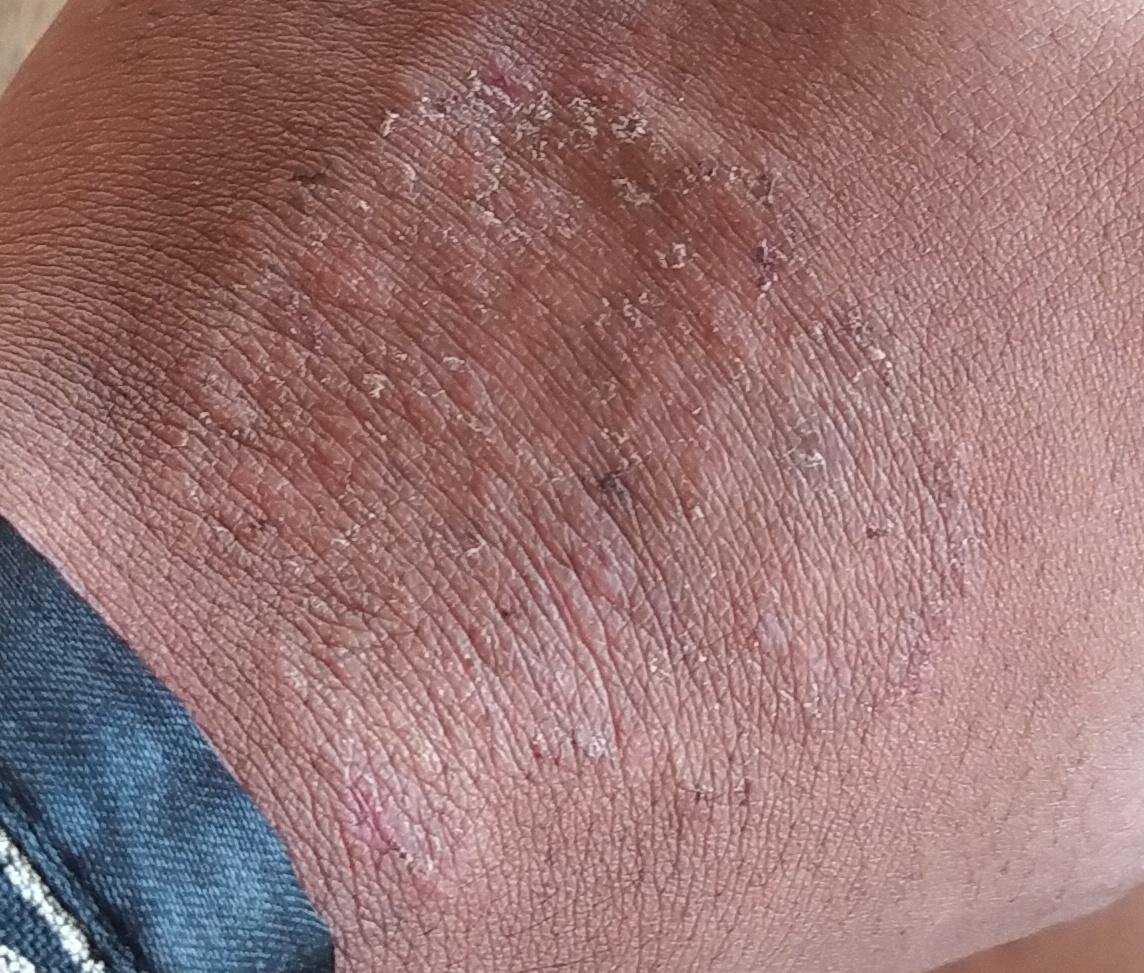
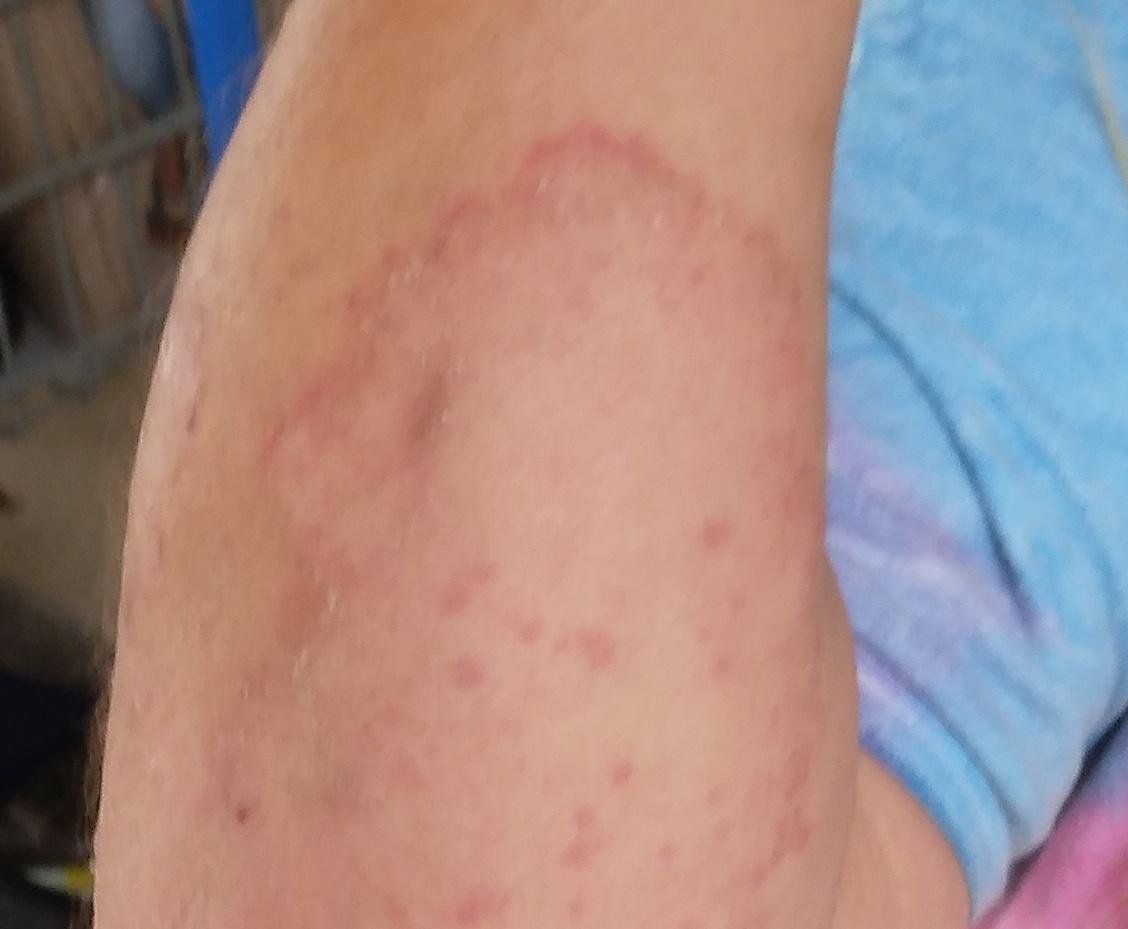
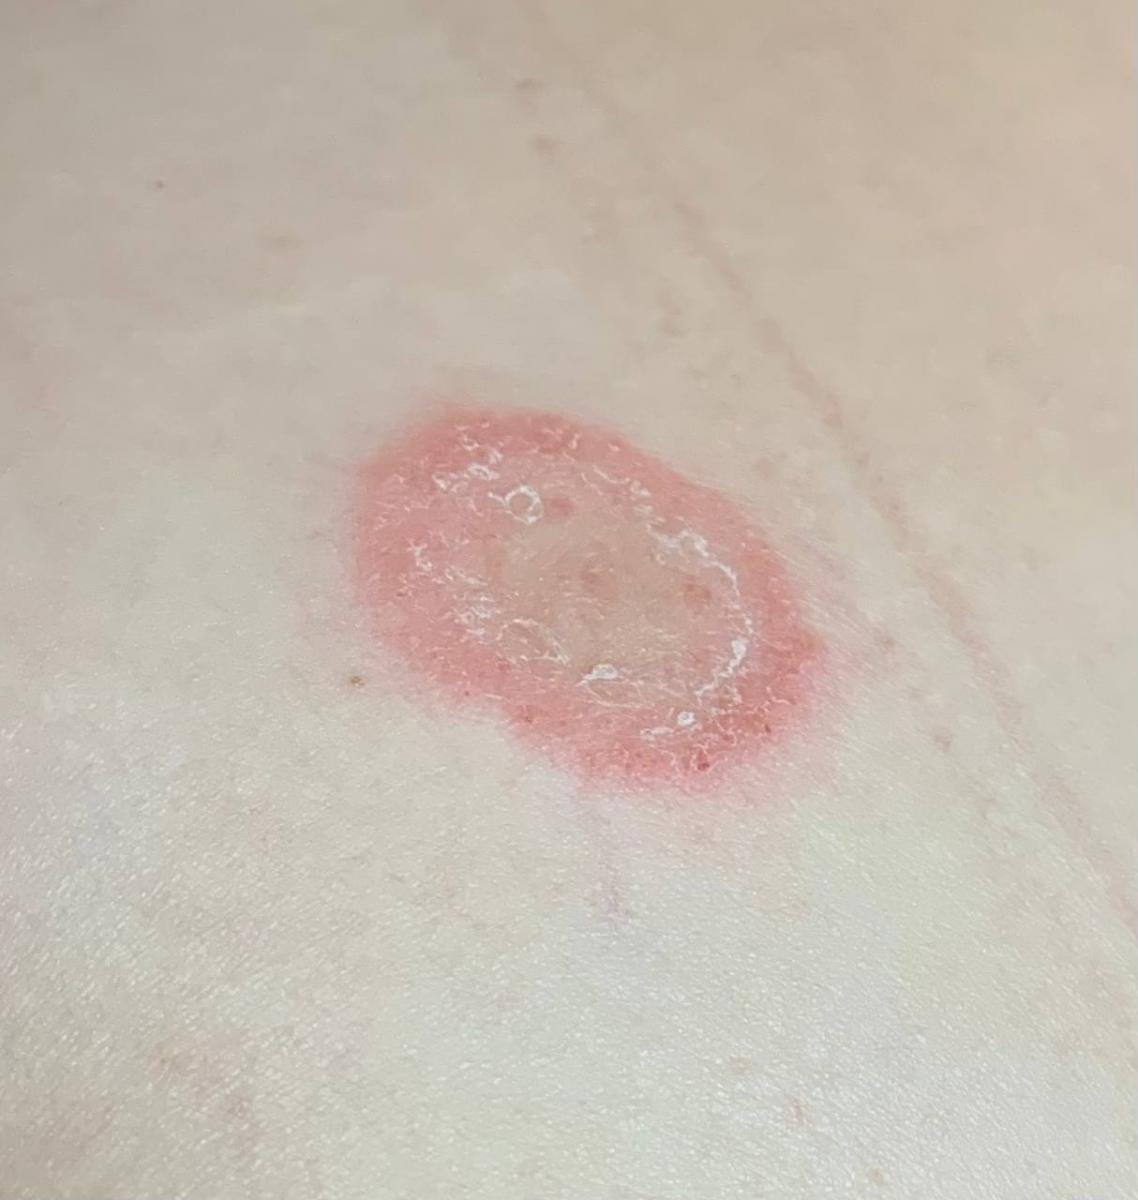
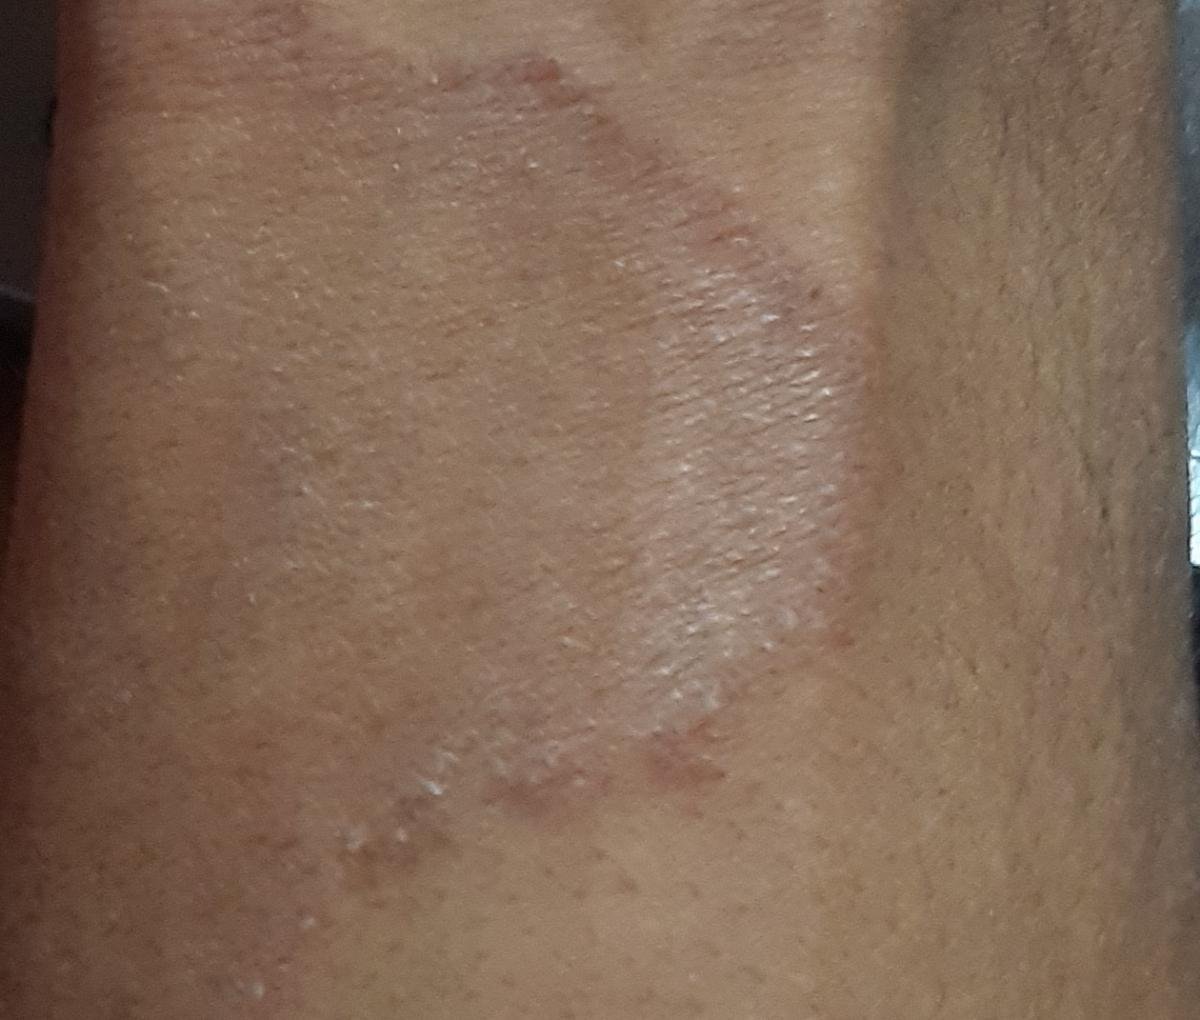
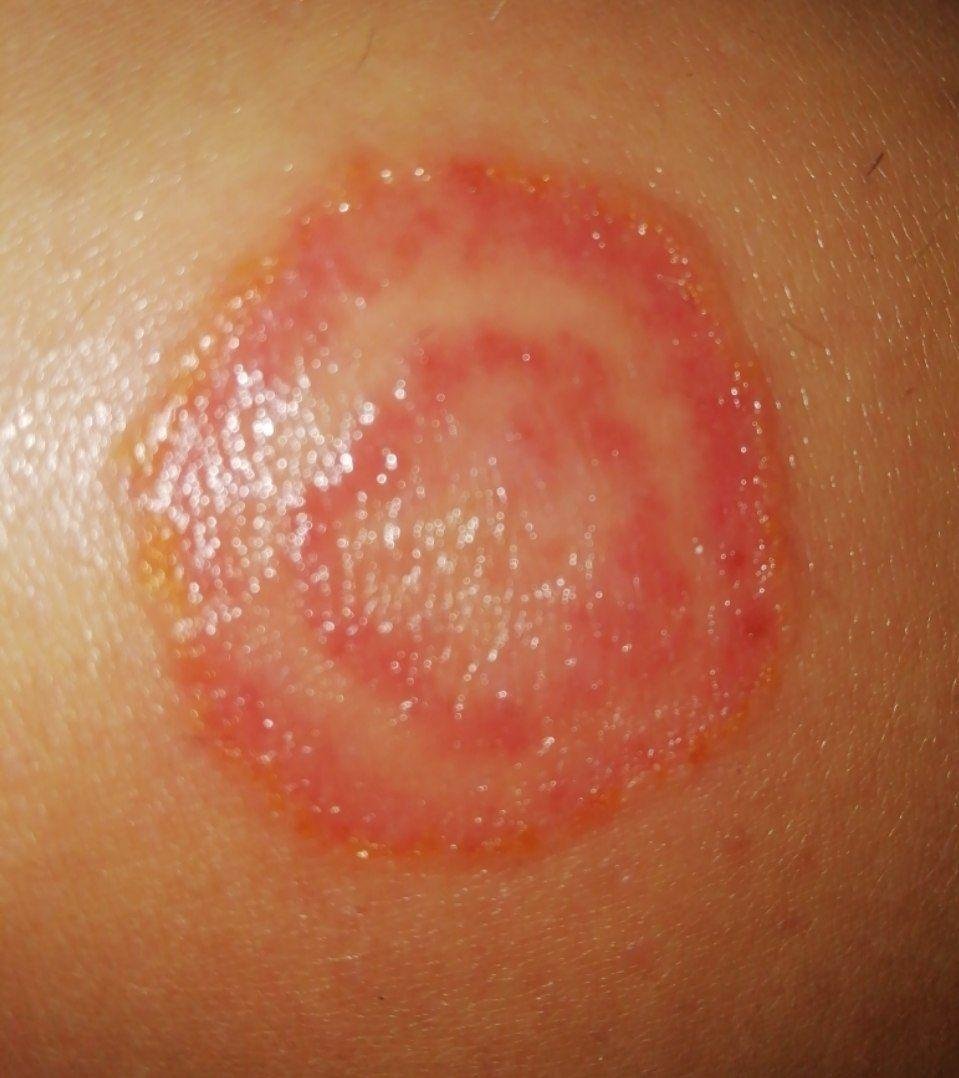
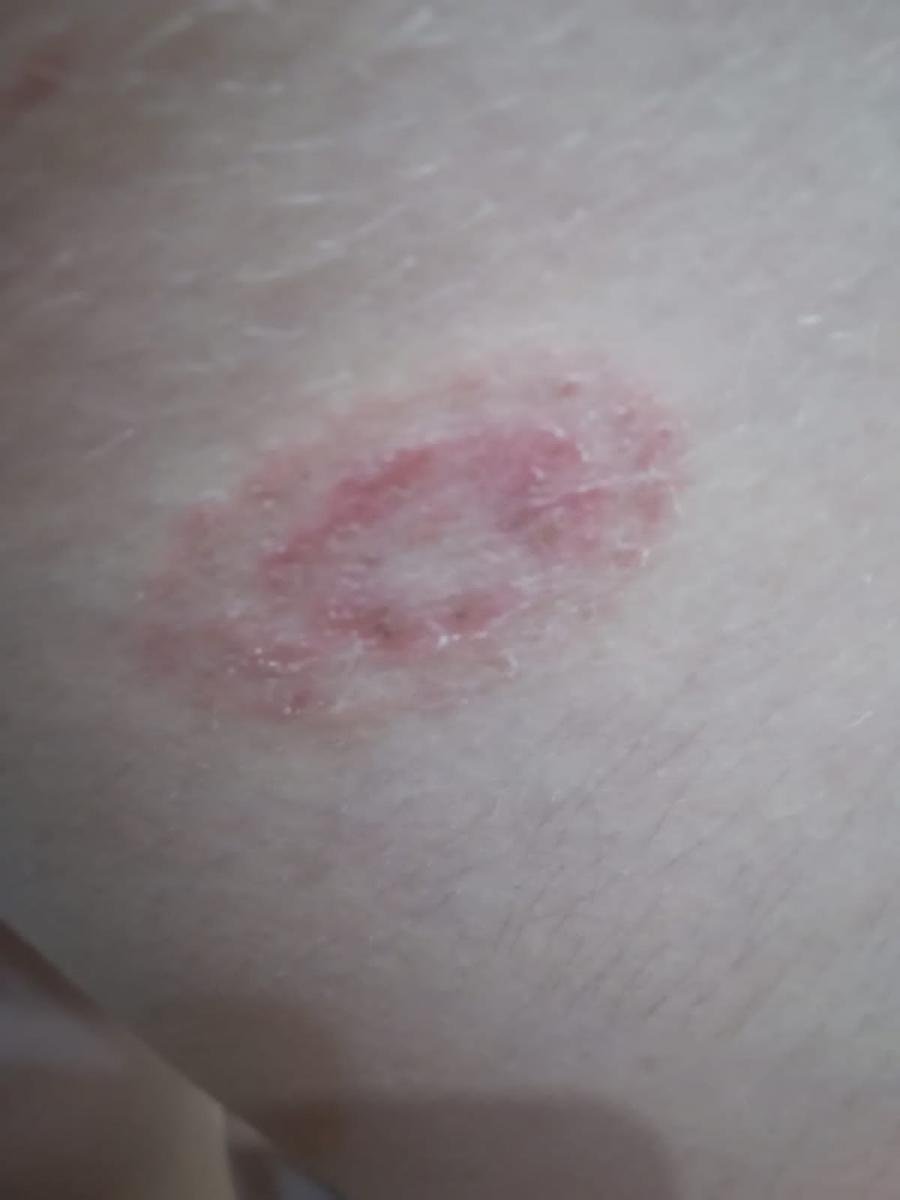
Tinea corporis refers to superficial fungal infections of smooth skin (excluding the scalp, nails, palms, and soles). It may occur on any part of the trunk or limbs and is especially prevalent in tropical climates.
Pathogens include:
- Microsporum canis (zoophilic): Often transmitted from pets or stray animals;
- Trichophyton rubrum (anthropophilic): A frequent cause of chronic, widespread infections in adults.
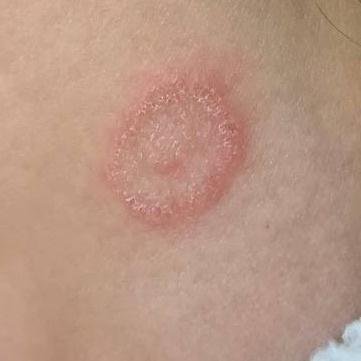
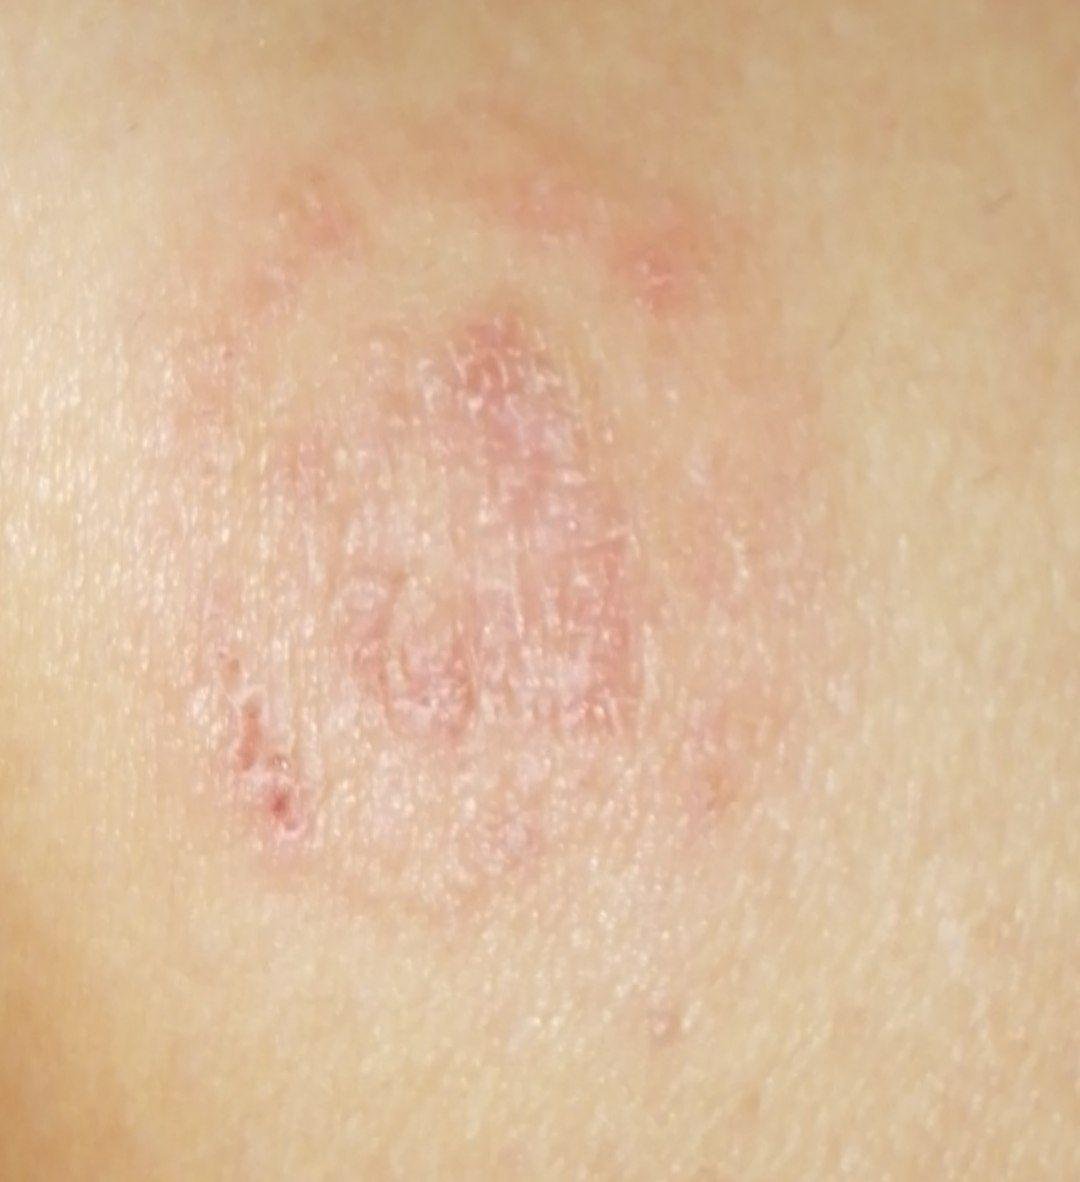
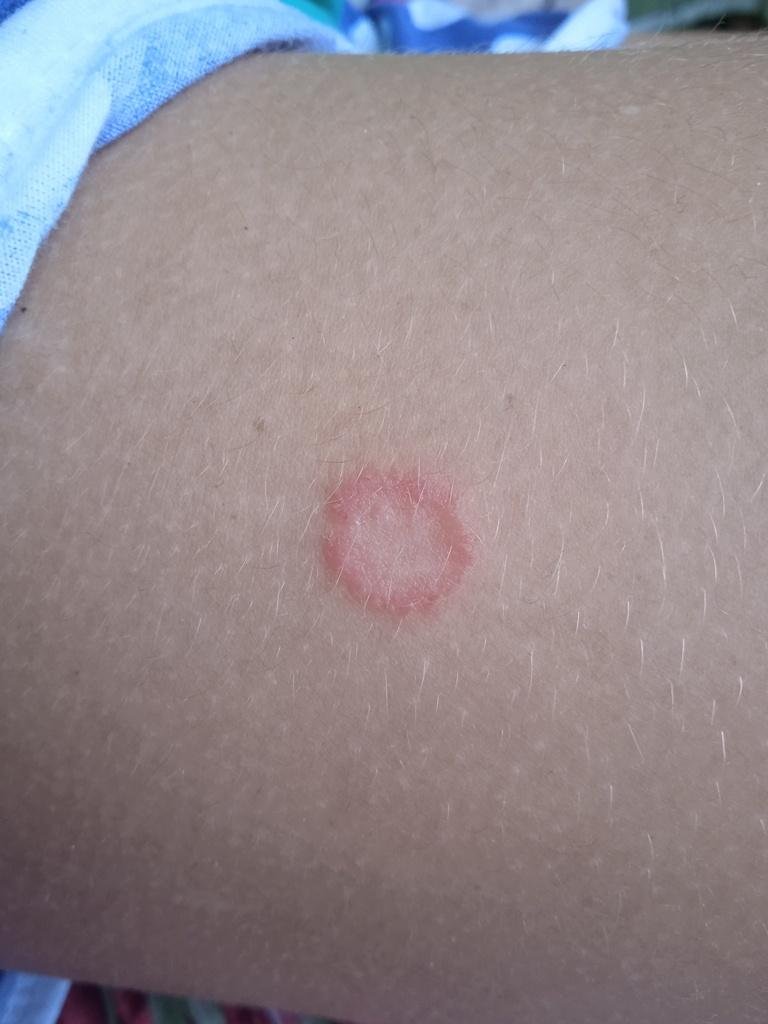
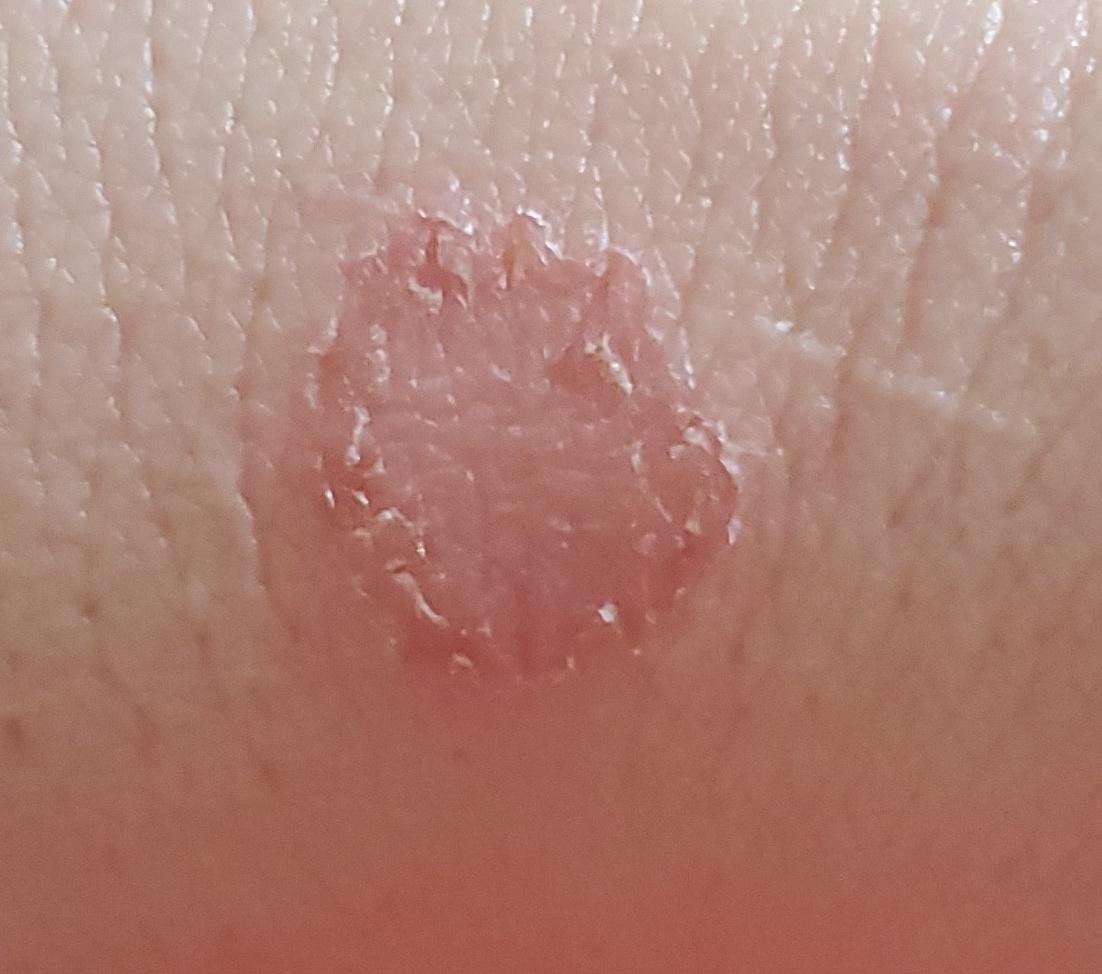
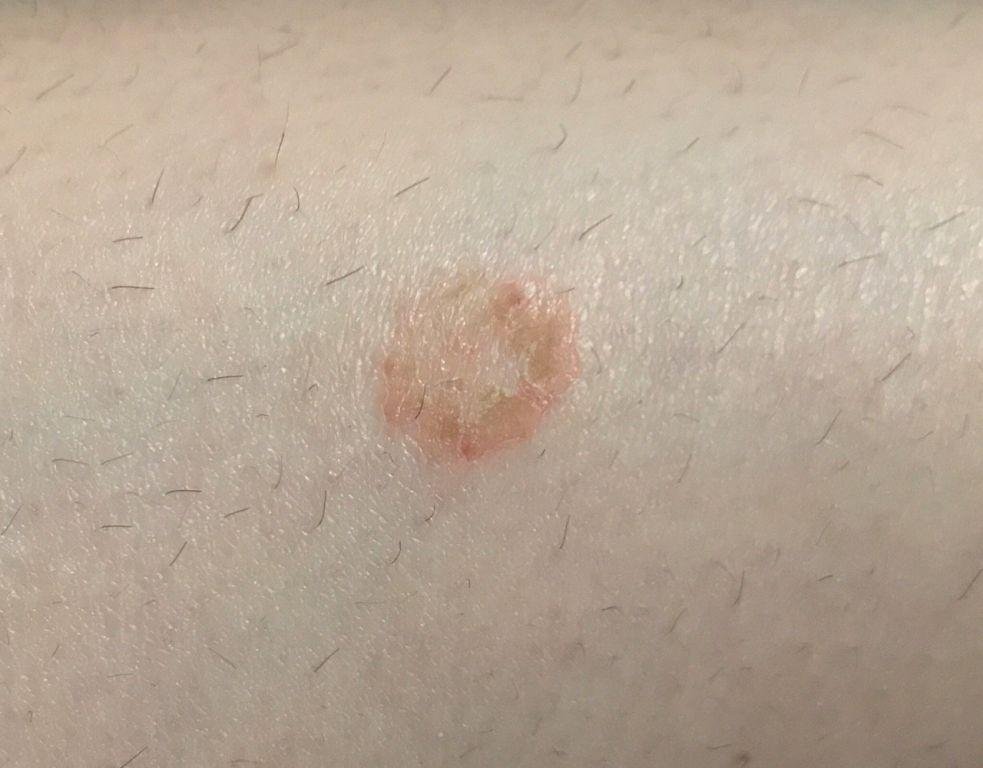
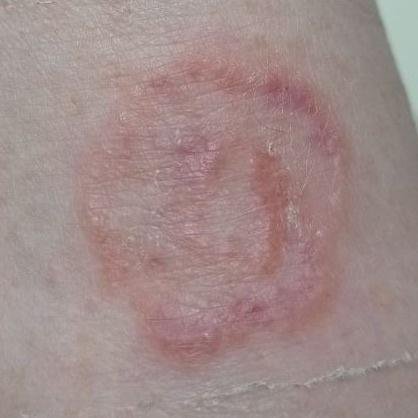
Clinical features: Ring-shaped erythematous patches with active, scaly, vesiculated borders and a central area that may be clear or slightly scaly. The lesions may enlarge over time and coalesce into larger plaques. Itching is common but may vary in intensity.
Tinea Pedis and Tinea Manuum (Athlete’s Foot and Hand Mycosis)
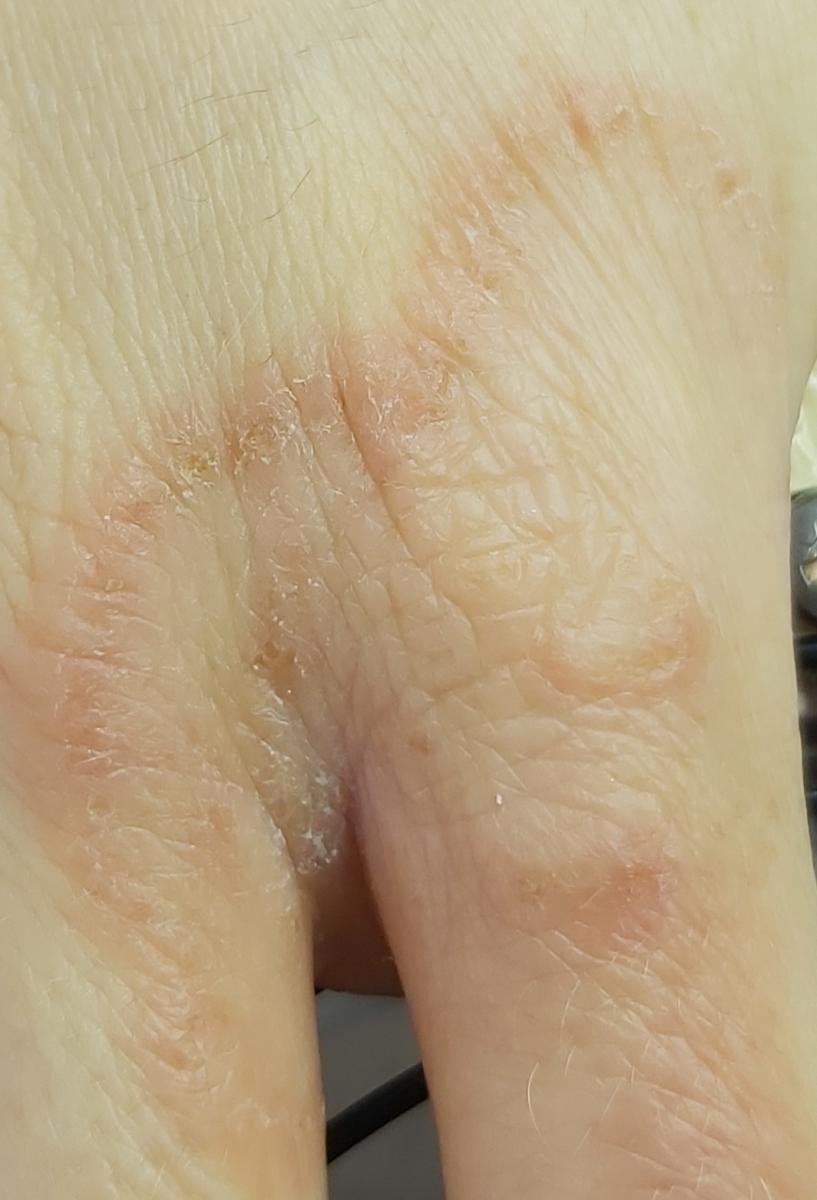
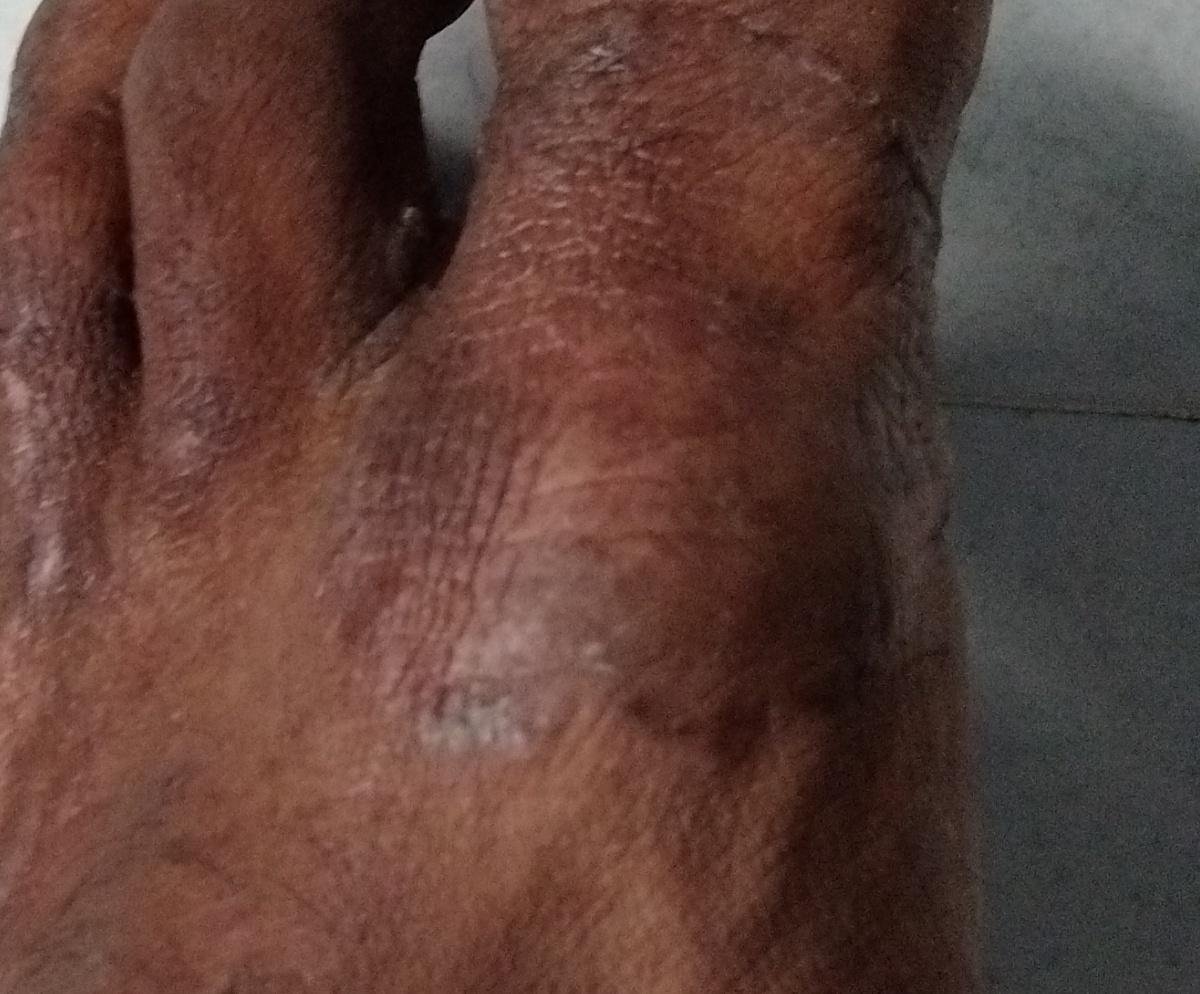
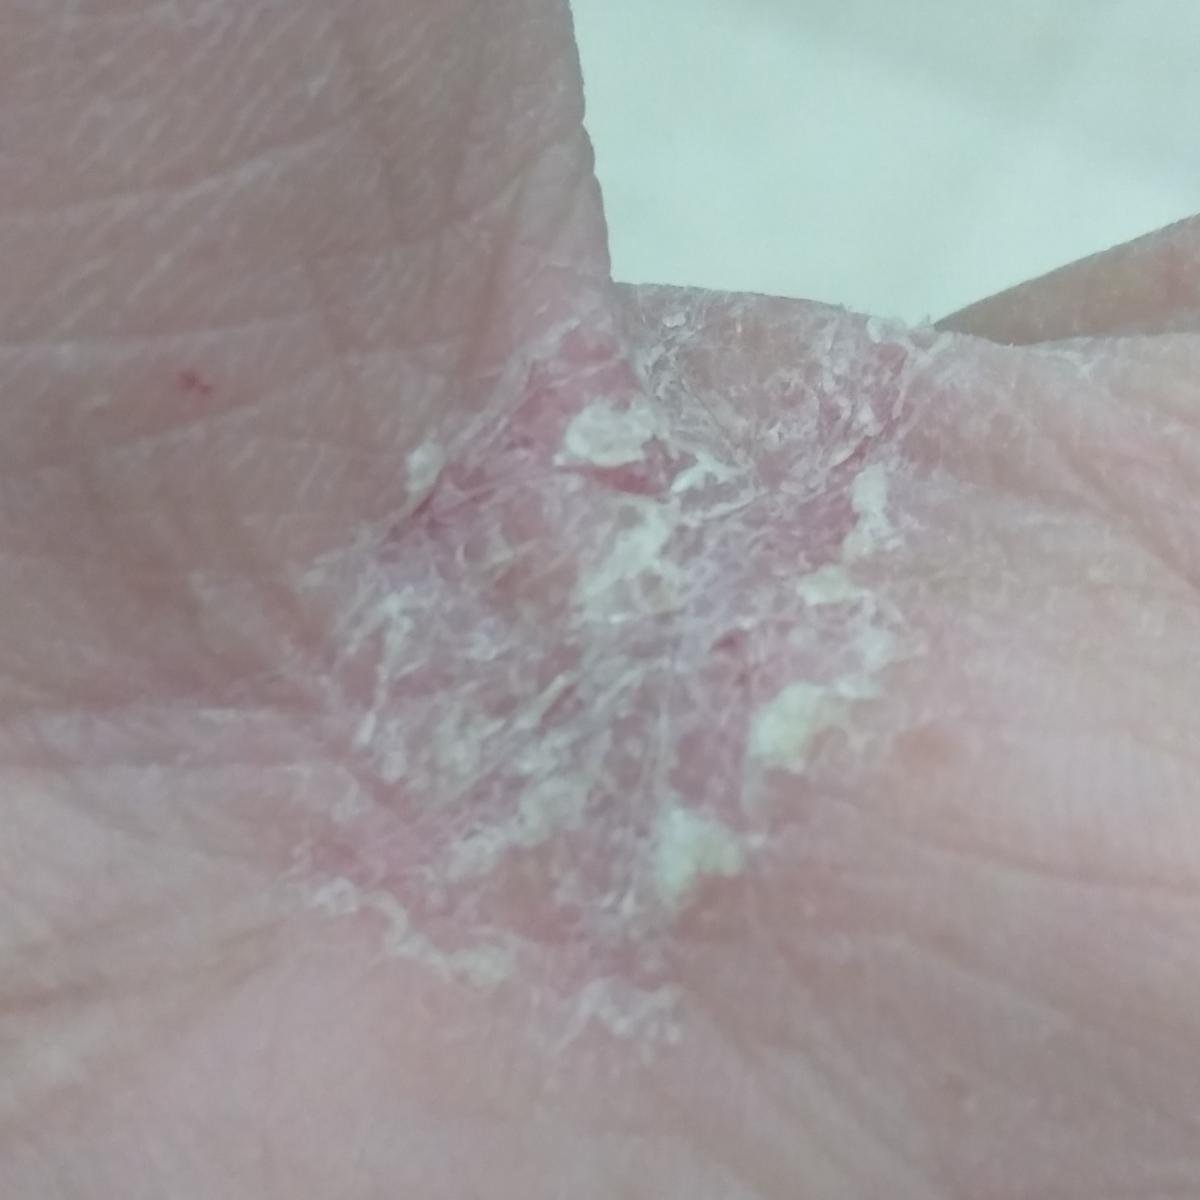
Tinea pedis is the most common fungal skin infection worldwide. It affects the soles, toes, and interdigital areas of the feet. Tinea manuum affects the palms and is often associated with unilateral involvement or concomitant nail or foot fungus.
Pathogens: Primarily Trichophyton rubrum; other causes include Trichophyton mentagrophytes and Epidermophyton floccosum.
Clinical variants:
- Latent type: Fine scaling in the toe webs or palms, often asymptomatic;
- Chronic hyperkeratotic type: Dry, thickened skin on the soles (“moccasin” pattern), often with fissures and pruritus;
- Interdigital type (“athlete’s foot”): Maceration, peeling, redness, and painful fissures between toes;
- Vesiculobullous type: Tense vesicles or bullae, often on the plantar surface, sometimes with secondary bacterial infection;
- Acute ulcerative type: Severe erosions and ulcers with purulence, lymphangitis, and systemic symptoms; typically secondary to bacterial coinfection.
Tinea Cruris (Jock Itch)
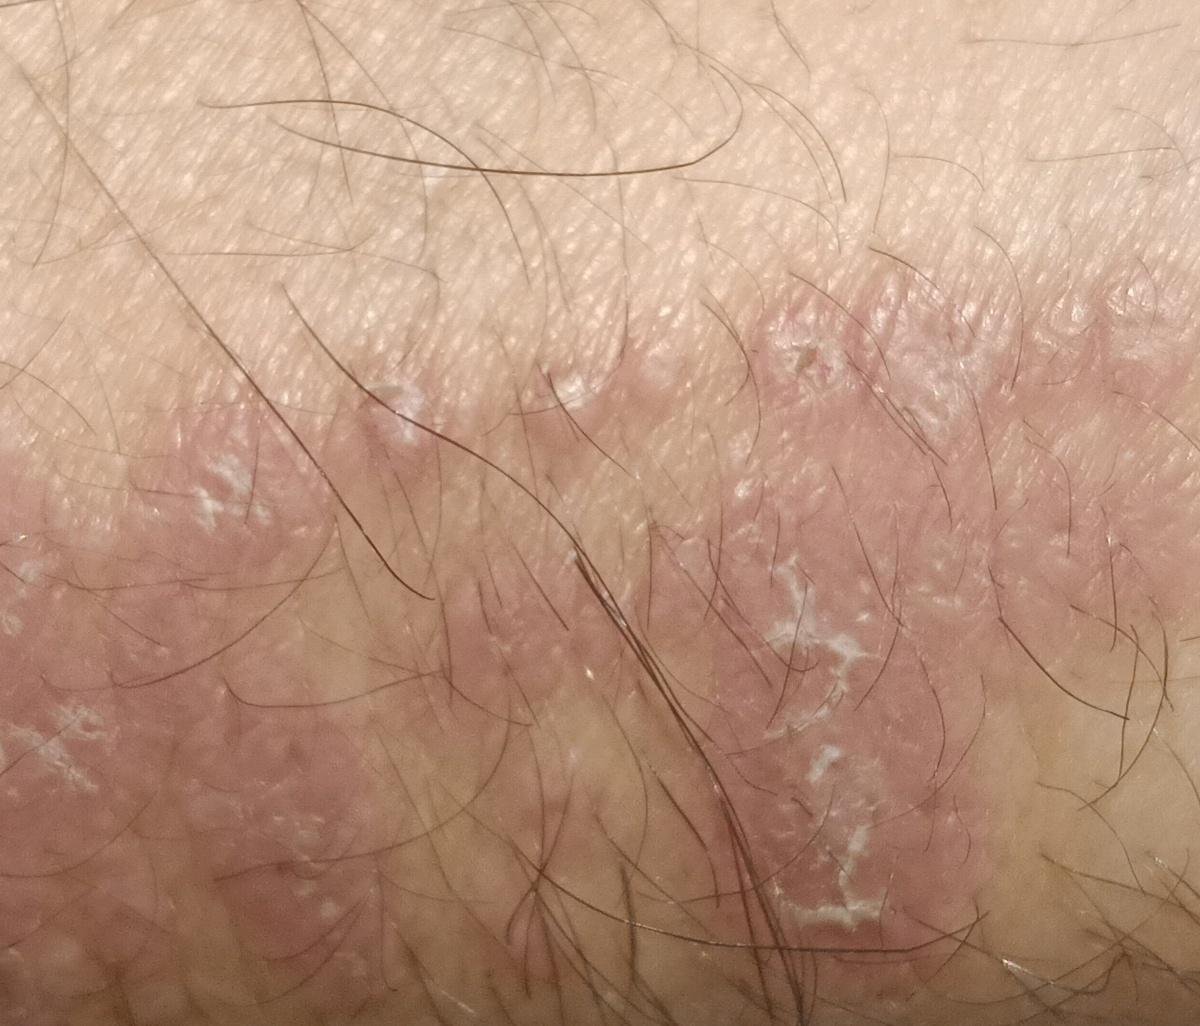
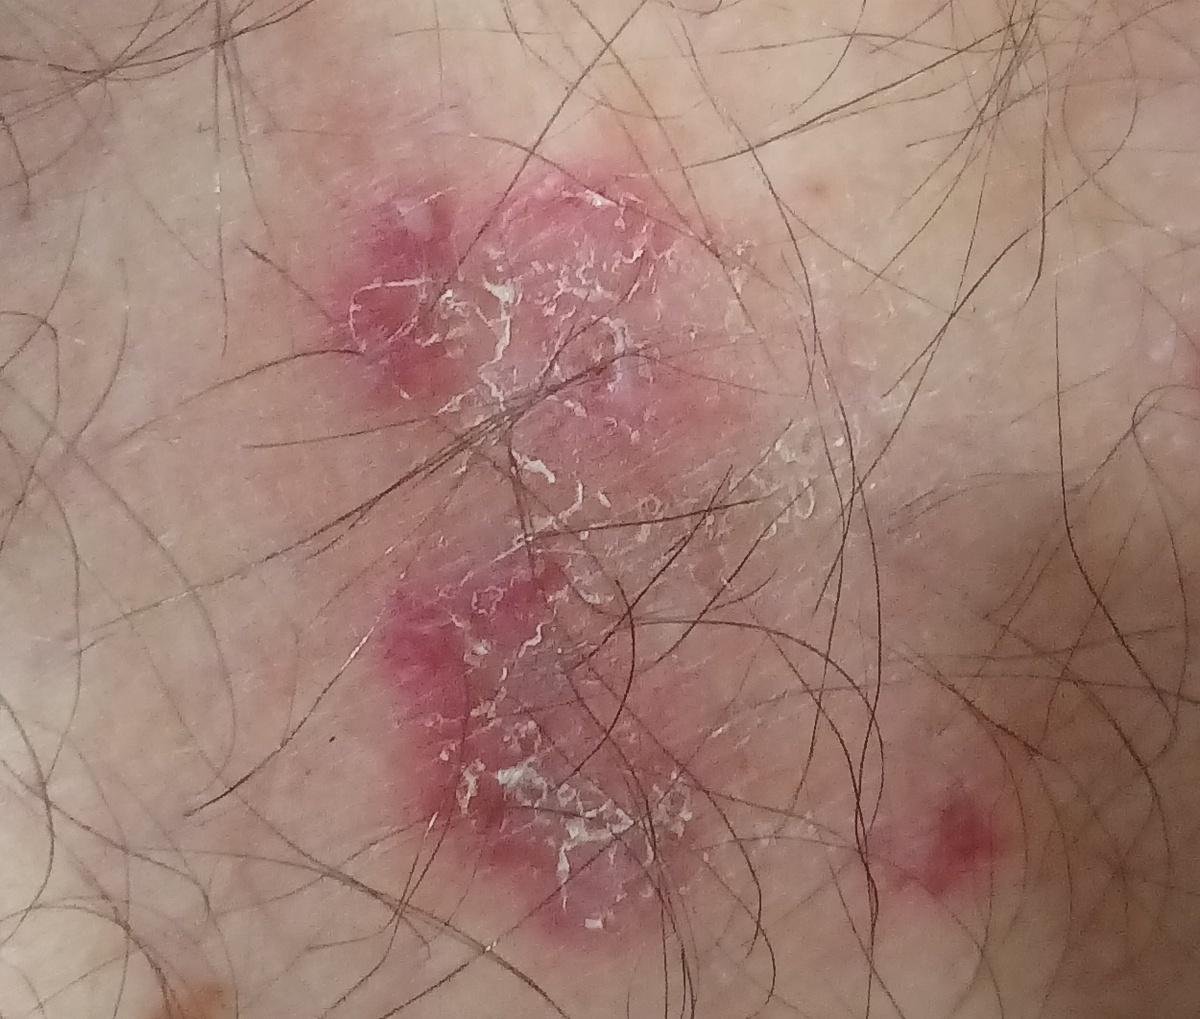
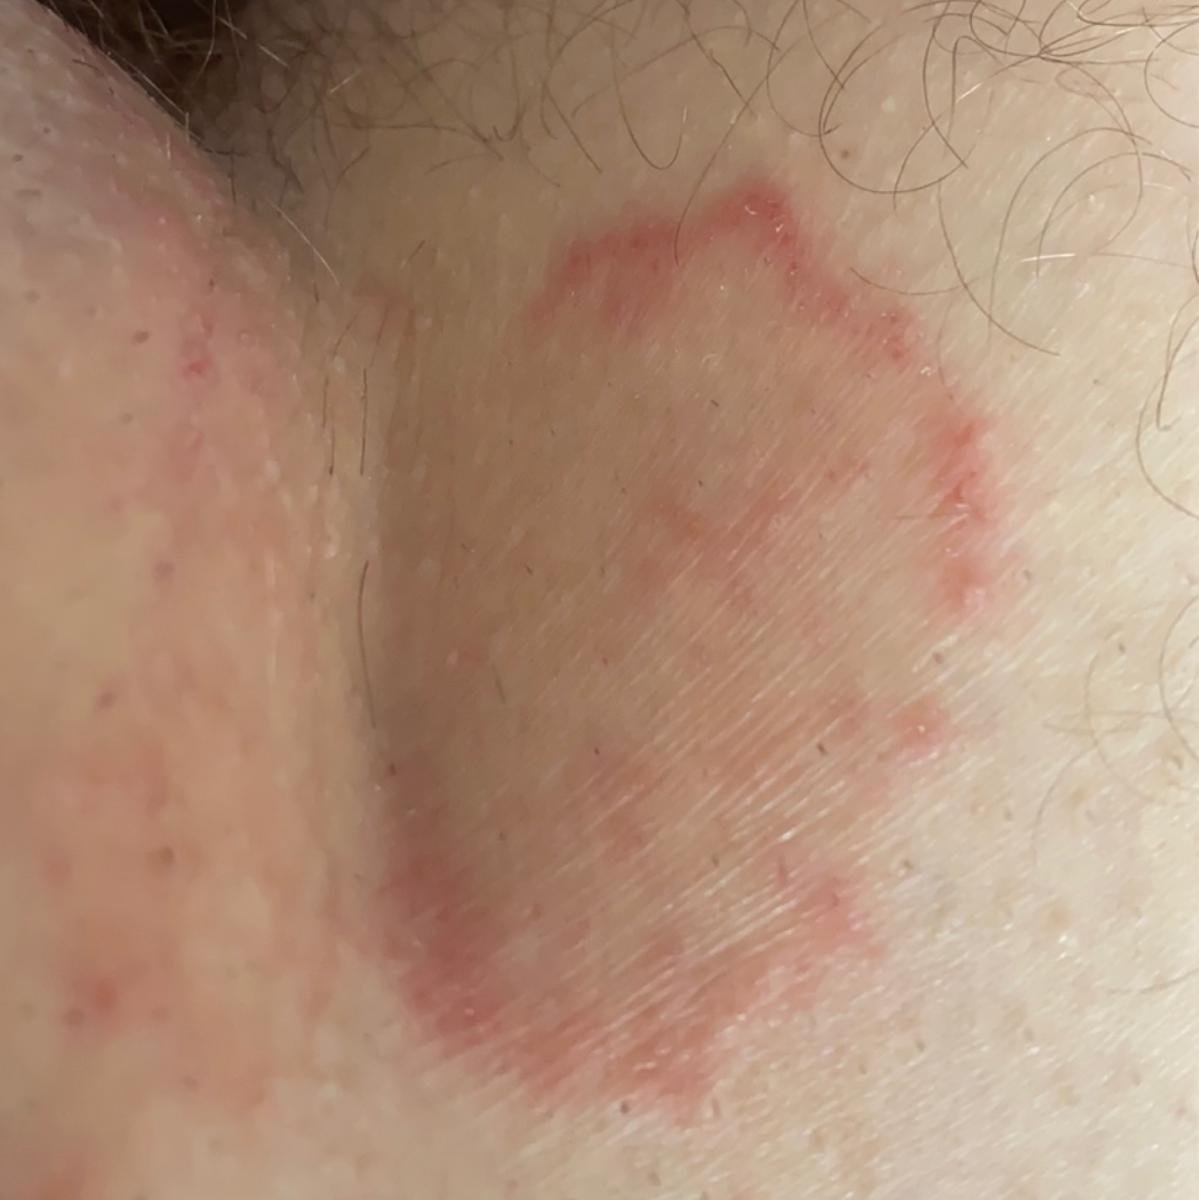
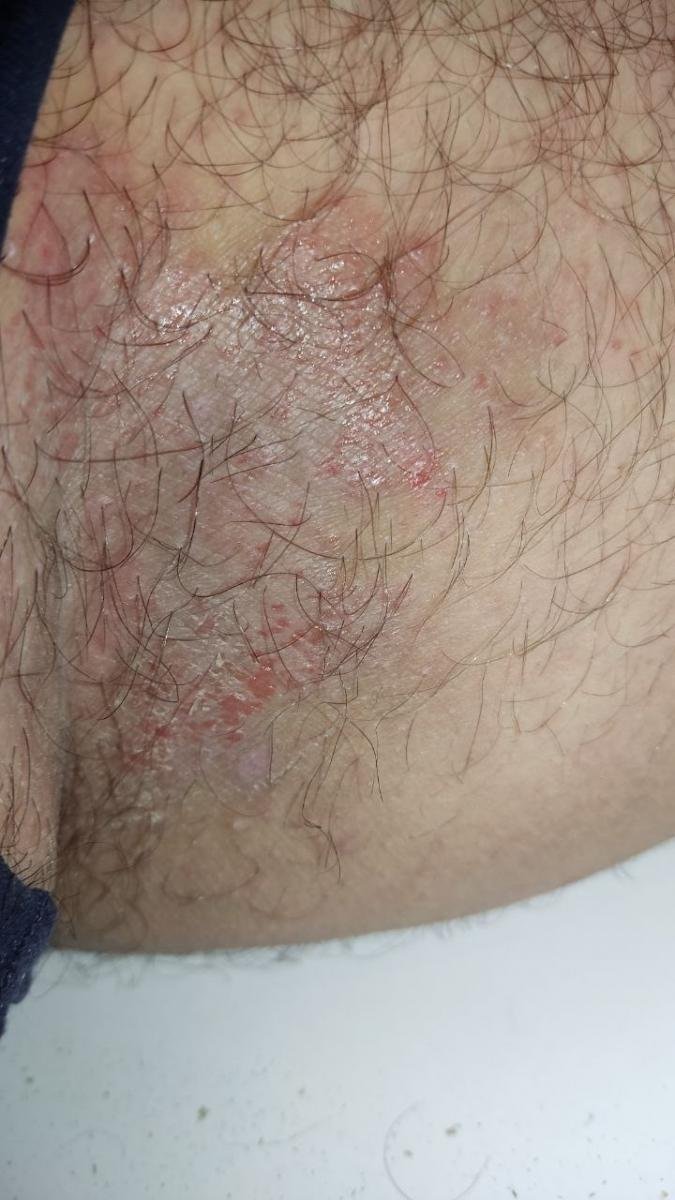
Tinea cruris is a fungal infection of the groin area, commonly affecting the inner thighs, perineum, buttocks, and pubic region. It is most common in adult males.
Pathogens: Most commonly Epidermophyton floccosum, followed by Trichophyton rubrum.
Clinical presentation: Erythematous, well-demarcated plaques with raised, scaly borders. Lesions may contain vesicles, pustules, or crusting. Pruritus is common, and maceration or secondary infection may increase discomfort.
Candidiasis of the Skin
Cutaneous candidiasis is caused by Candida species, primarily Candida albicans. Unlike dermatophytes, Candida forms pseudohyphae and thrives in warm, moist environments. It commonly affects skin folds, especially in immunocompromised individuals, infants, and people with obesity or diabetes.
Common locations:
- Inguinal and perineal folds;
- Axillae;
- Submammary area (under breasts);
- Intergluteal cleft and diaper area in infants;
- Interdigital spaces (hands and feet).
Clinical signs: Erythematous, moist, macerated patches with satellite pustules or vesicles at the periphery. Lesions may burn or itch. In bedridden patients, candidal intertrigo may appear on the back or under skin folds.
Disseminated Candidiasis
Disseminated candidiasis, also known as invasive candidiasis or candidemia, is a serious systemic fungal infection resulting from hematogenous spread of Candida species. It typically occurs in severely immunocompromised individuals, including patients in intensive care units, those receiving chemotherapy, transplant recipients, and neonates.
Clinical features may include:
- Persistent or unexplained fever and systemic signs of infection;
- Multiorgan involvement (kidneys, liver, brain, spleen);
- Skin manifestations such as erythematous papules with necrotic or hemorrhagic centers on the trunk or limbs.
Disseminated candidiasis requires urgent antifungal therapy and often hospitalization. Skin lesions can aid early diagnosis in systemic cases.
Diagnosis of Superficial Fungal Infections
Diagnosis of dermatophytosis and candidiasis is based on a combination of clinical findings and mycological confirmation:
- Clinical examination: Assessment of lesion morphology, location, scaling, and symptoms;
- KOH microscopy: The confirmatory test where the diagnosis is uncertain — skin scrapings examined with potassium hydroxide to detect hyphae or pseudohyphae;
- Cultural testing: Reserved for selected or treatment-resistant cases, to identify the species;
- Wood’s lamp: Useful for diagnosing Microsporum infections (green fluorescence) and tinea versicolor (yellow-orange glow);
- PCR diagnostics: Advanced molecular detection of fungal DNA, used in complex or recurrent cases.
Treatment of Cutaneous Fungal Infections
The treatment strategy depends on the type of infection, severity, extent, and immune status of the patient. It may involve topical therapy for localized disease and systemic antifungal agents in extensive or chronic cases.
Topical therapy:
For mild to moderate superficial infections:
- Imidazoles: Clotrimazole, ketoconazole, miconazole;
- Allylamines: Terbinafine, naftifine;
- Polyene agents: Nystatin for candidiasis;
- Corticosteroids are not a treatment for fungal infection. A steroid applied to a dermatophyte infection suppresses the appearance while the infection spreads — tinea incognito — so combined preparations are reserved for a specific clinical reason.
There is no single duration that fits every fungal infection: it depends on the organism, the site, the severity and the agent chosen, and treatment is continued for the course prescribed even once the skin begins to look better.
Systemic antifungals:
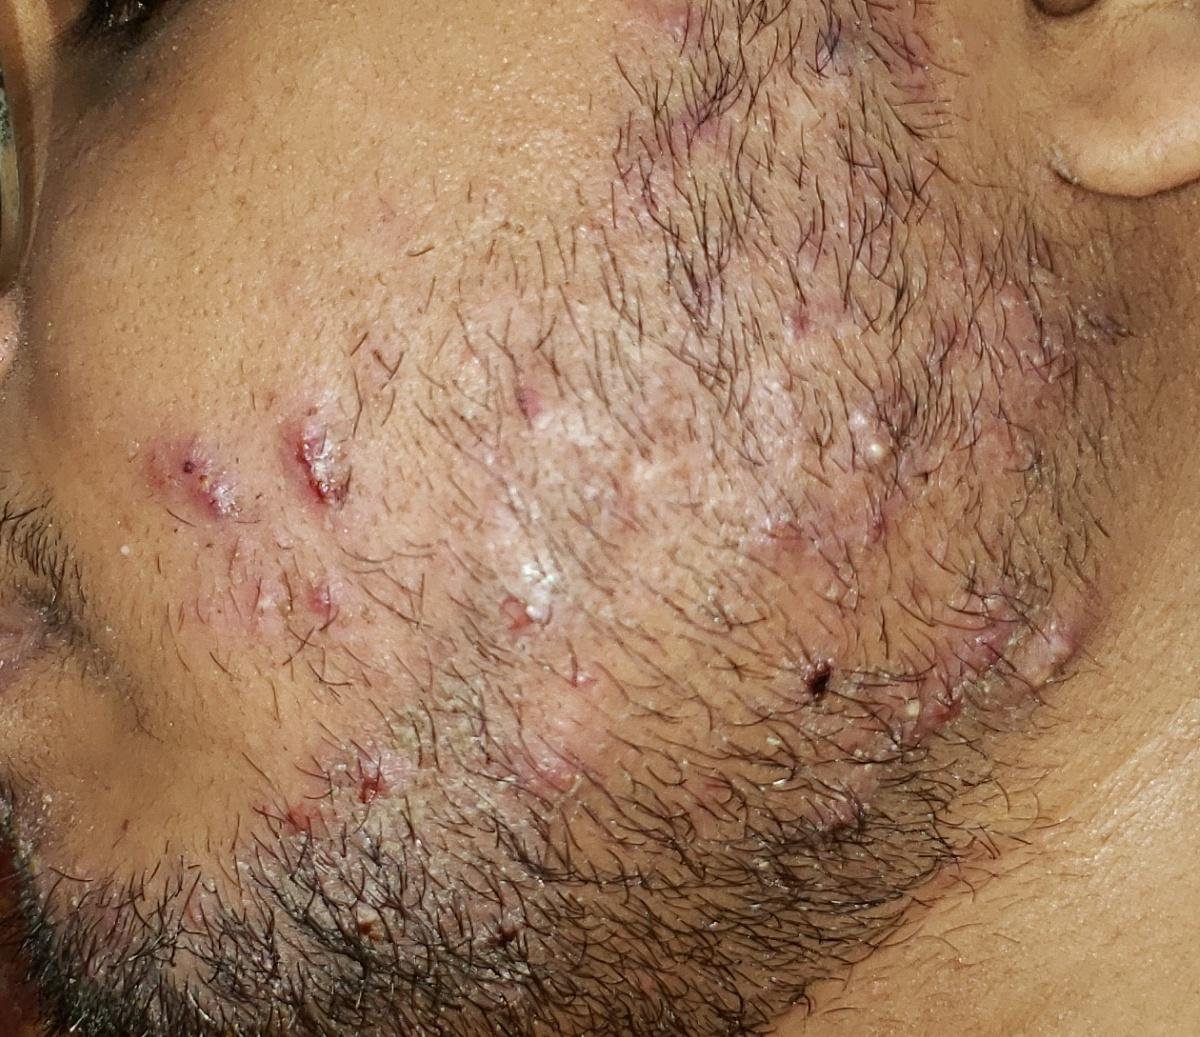
Indicated for widespread infection, for recurrent or immunocompromised cases, and for sites topical agents cannot reach: scalp, beard and nail dermatophytosis generally need systemic treatment, while many uncomplicated infections of the skin respond to topical agents alone. Terbinafine resistance is emerging in some dermatophytes, notably Trichophyton indotineae, so a case that does not respond is worth re-testing rather than simply re-treating.
- Terbinafine, for skin and for nails, over different courses;
- Itraconazole, continuous or as pulse therapy;
- Fluconazole, particularly for candidiasis. Dosing is set by the prescriber;
- Oral ketoconazole is not recommended for these infections, because of the risk of serious liver injury; other oral agents are used instead.
Tinea Versicolor Summary
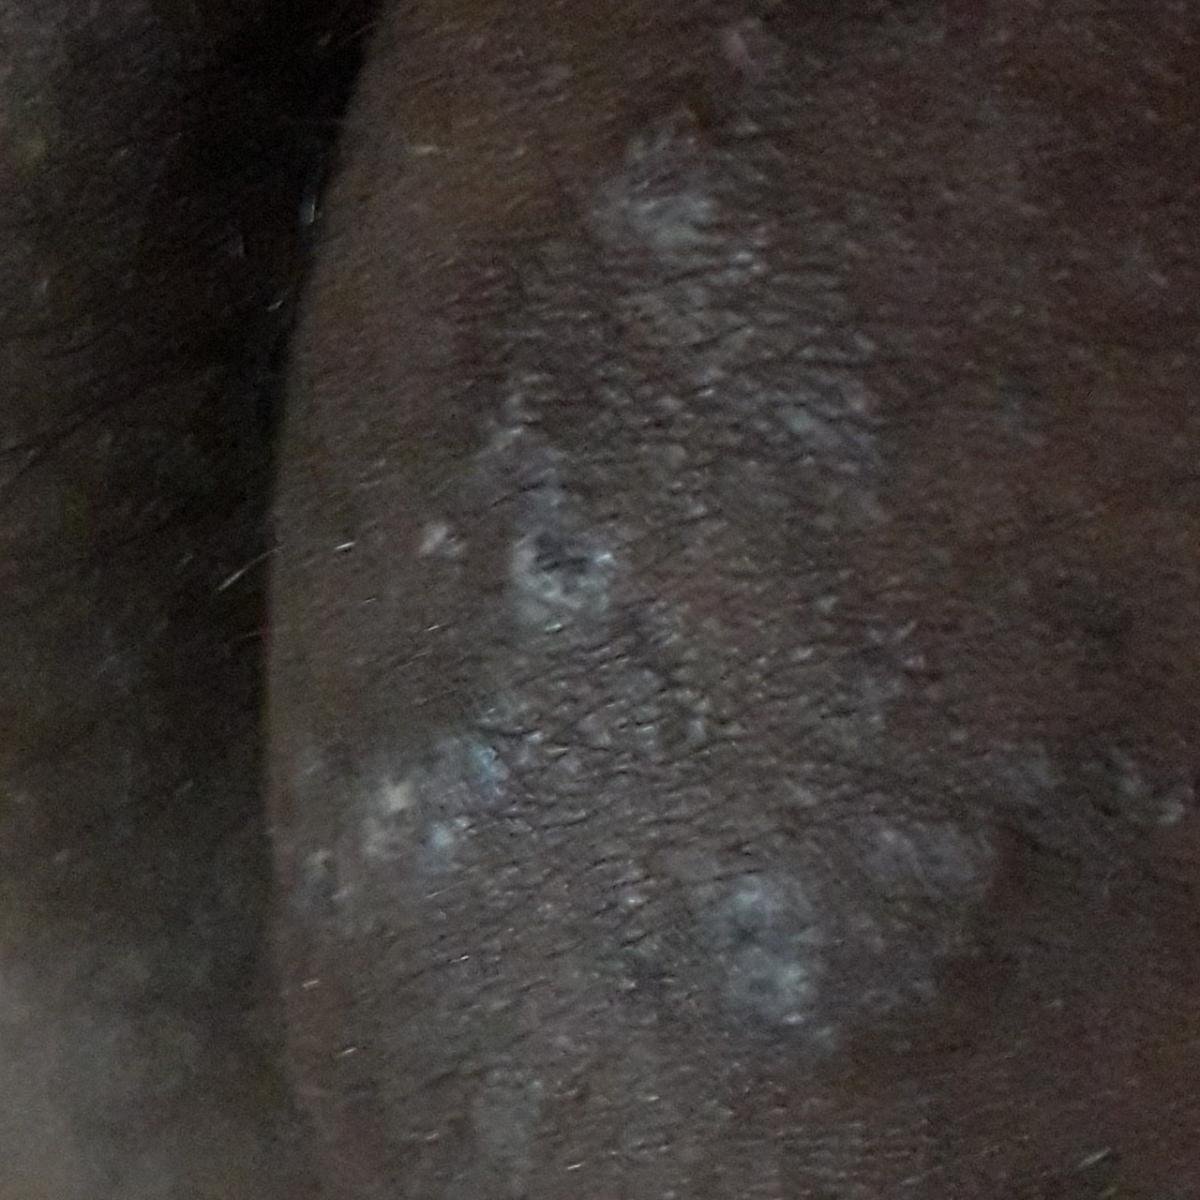
Tinea versicolor, caused by Malassezia species, is a superficial yeast infection of the stratum corneum. It presents as hypopigmented or hyperpigmented scaly patches, mostly on the upper trunk and arms. It is more common in warm, humid environments and among individuals with oily skin.
Diagnosis:
- Wood’s lamp: Yellow to orange fluorescence;
- KOH prep: “Spaghetti and meatballs” appearance (hyphae and spores);
- Culture: Rarely needed; Malassezia requires lipid-enriched media to grow at all.
Treatment:
- Mild cases: Topical ketoconazole, clotrimazole or selenium sulfide;
- Severe or recurrent cases: Systemic therapy with itraconazole or fluconazole, reserved for extensive, recurrent or treatment-resistant disease, with dosing set by the prescriber.
Prevention and Conclusion
Preventive measures include:
- Good hygiene: Daily cleansing, drying skin folds, changing socks and undergarments frequently;
- Avoid shared items: Don’t share towels, razors, footwear, or nail tools;
- Manage underlying conditions: Control blood glucose in diabetes, improve nutrition, and treat obesity or hormone disorders;
- Skin protection: Avoid skin trauma, occlusive clothing, and excessive heat or humidity;
- Environmental decontamination: Disinfect footwear, bedding, and commonly touched surfaces in communal areas;
- Prophylactic therapy: In recurrent tinea versicolor, maintenance treatment is sometimes used through the warmer months. Preventive courses are not a general measure and are decided case by case.
Cutaneous mycoses are generally treatable and preventable conditions. However, chronic or widespread forms may signal underlying systemic issues requiring medical evaluation. Early intervention, accurate diagnosis, and adherence to treatment protocols ensure high cure rates and reduced relapse risk. A combination of pharmacologic therapy, lifestyle modification, and infection control can effectively eliminate most superficial fungal infections and preserve healthy skin.

Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)