
Tinea Capitis and Tinea Barbae (ICD-10: B35) 🚨
Tinea Capitis and Tinea Barbae: Fungal Infections of the Scalp and Facial Hair
Overview
Tinea capitis and tinea barbae are fungal infections of the hair and hair follicles, affecting the scalp and the beard area respectively. They are sometimes called trichomycosis, though that term is better avoided: unqualified, it usually refers to trichomycosis axillaris, a bacterial colonisation of underarm hair that has nothing to do with fungi. These infections are caused by dermatophytes—filamentous fungi that have a particular affinity for keratinized tissues. The main genera responsible are Microsporum and Trichophyton. By site of infection these are:
- Tinea capitis: Dermatophytosis of the scalp and hair shafts;
- Tinea barbae: Fungal infection involving the beard or mustache area in adult males.
Both are contagious, and outbreaks may occur in schools, families, or close-contact settings. It spreads easily among children, but isolation is generally not required once antifungal treatment has started. Prompt diagnosis and treatment matter: severe inflammatory disease, particularly a kerion, can cause permanent scarring hair loss if treatment is delayed. Painful inflammatory plaques, pustules or boggy swelling need systemic treatment without waiting.
Patterns of Fungal Invasion
The clinical presentation depends on the type of dermatophyte and the pattern of hair shaft invasion. Two main invasion patterns are identified:
- Ectothrix invasion: Fungal spores (arthroconidia) develop outside the hair shaft; typical of Microsporum species;
- Endothrix invasion: Spores form within the hair shaft; more often seen in Trichophyton infections.
Clinical Forms of Tinea Capitis
1. Non-Inflammatory (Superficial) Type
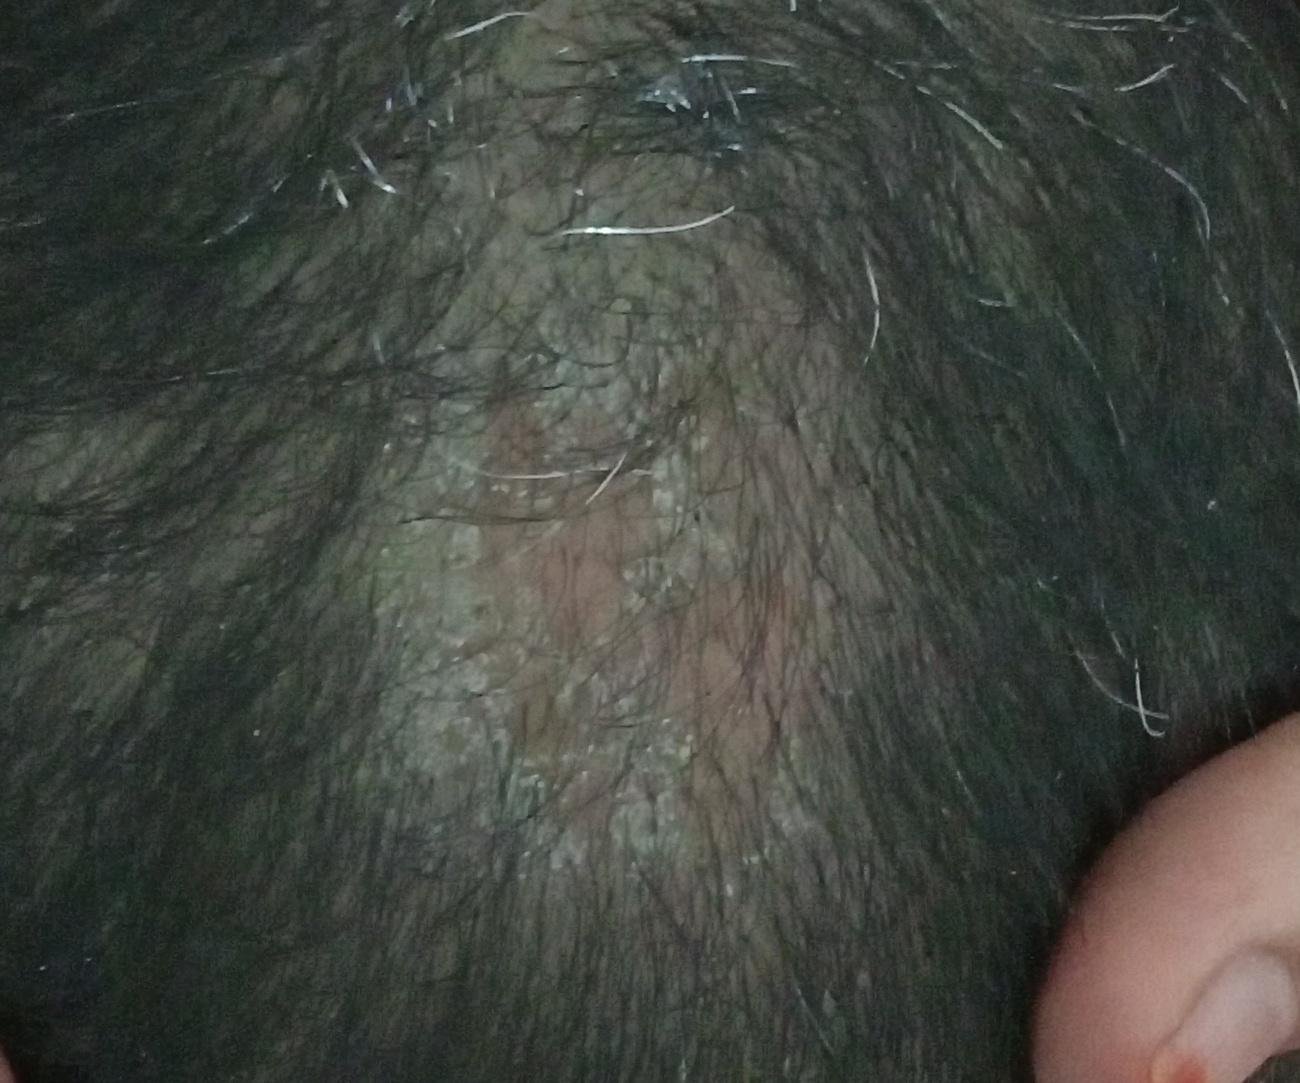
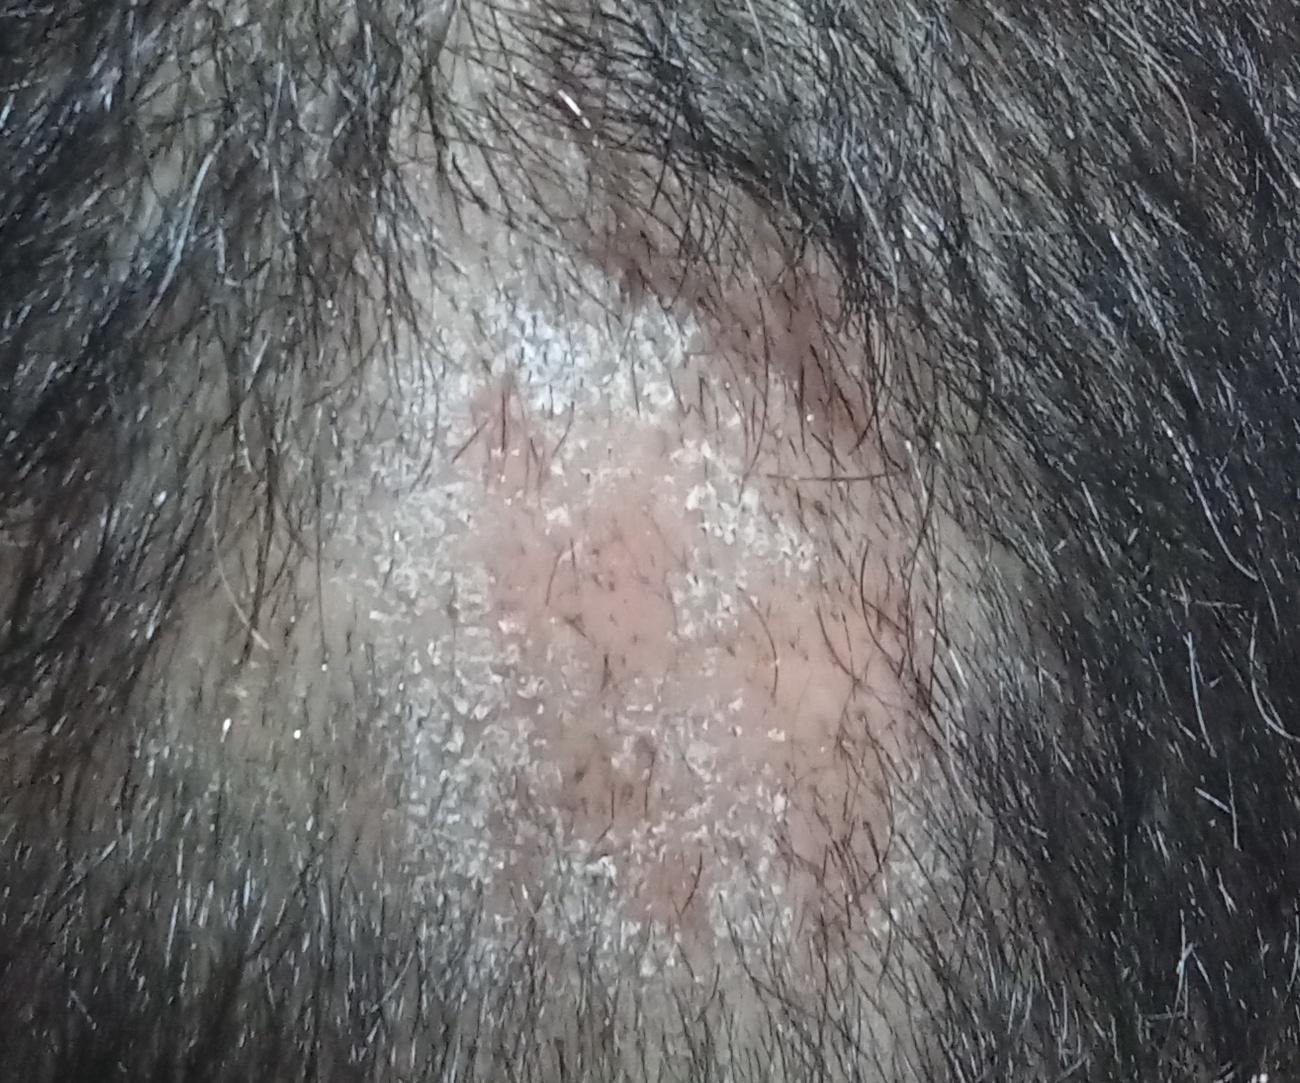
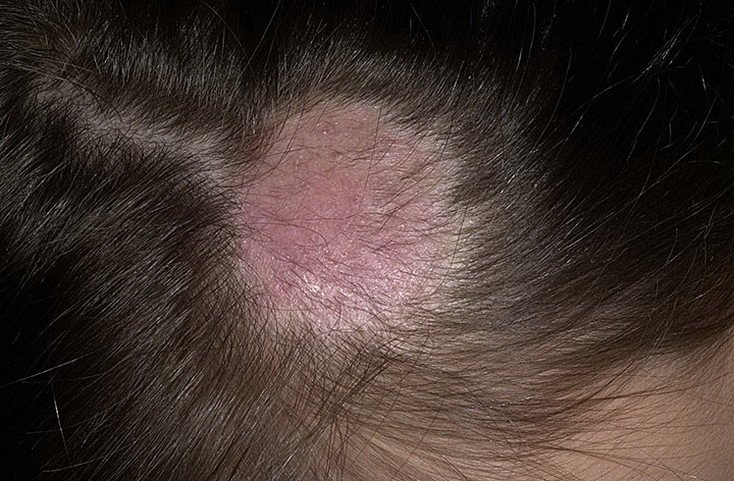
This form is commonly caused by anthropophilic fungi such as Trichophyton tonsurans (endothrix) and Microsporum canis or M. ferrugineum (ectothrix).
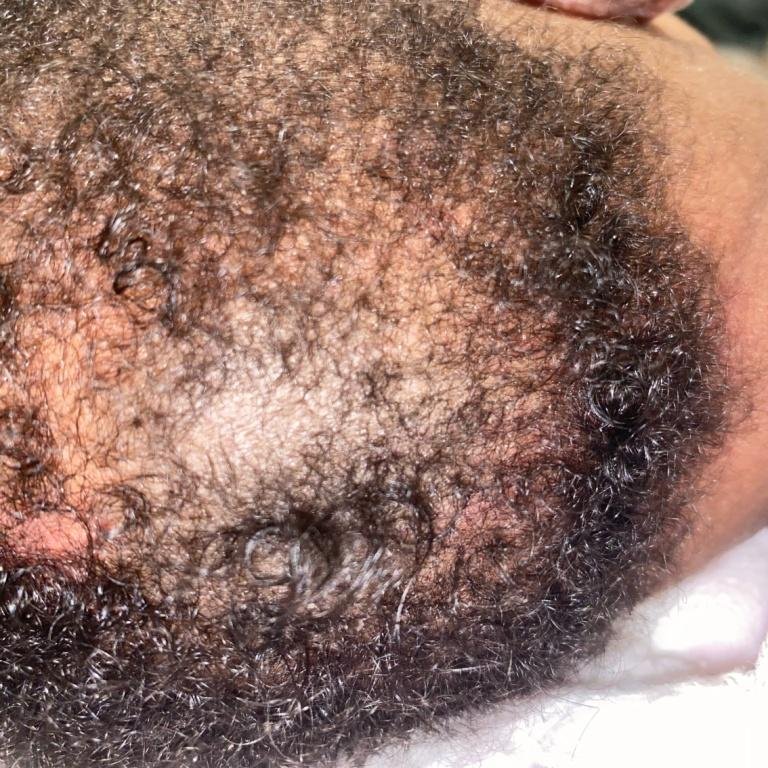
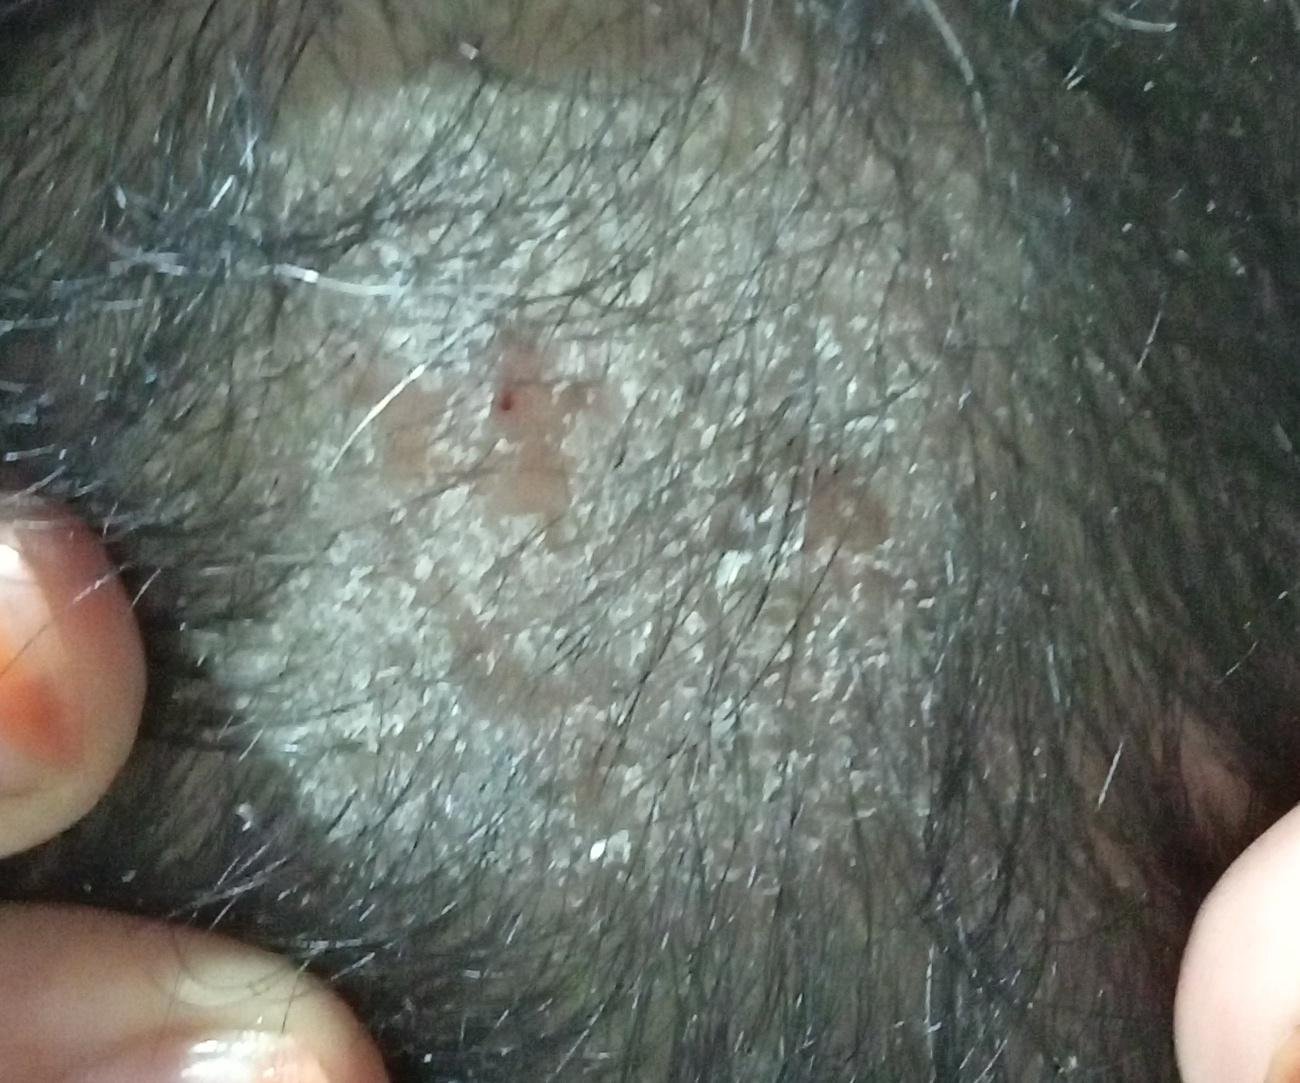
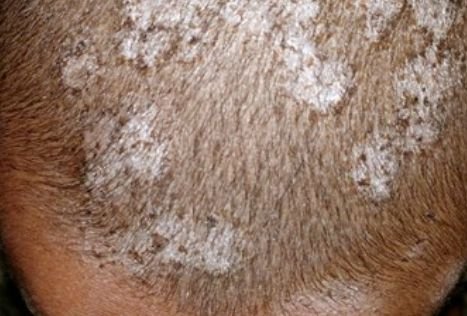
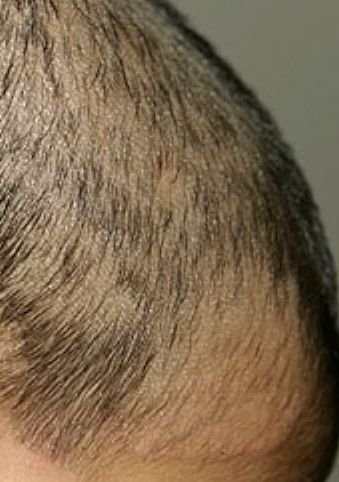
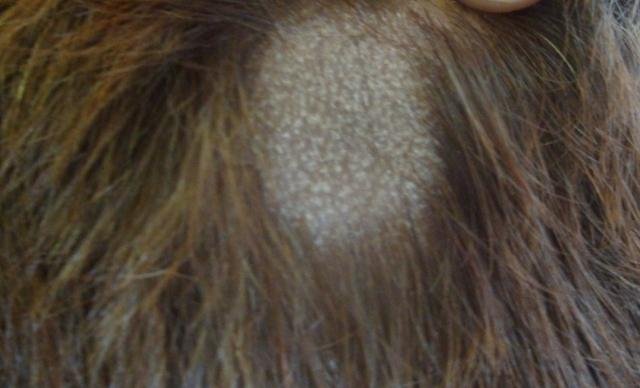
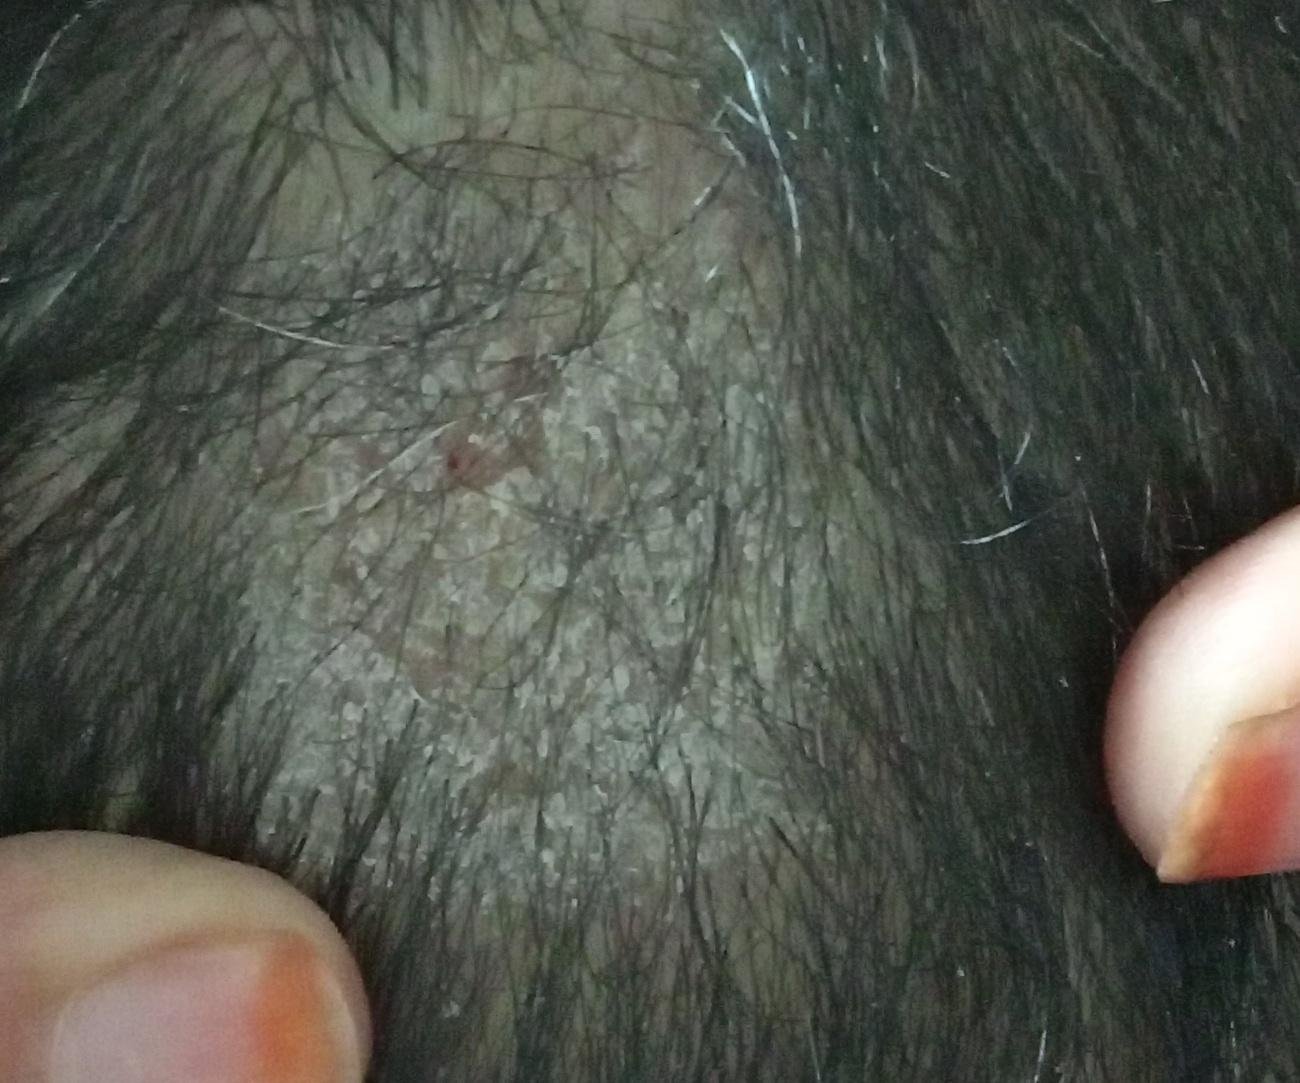
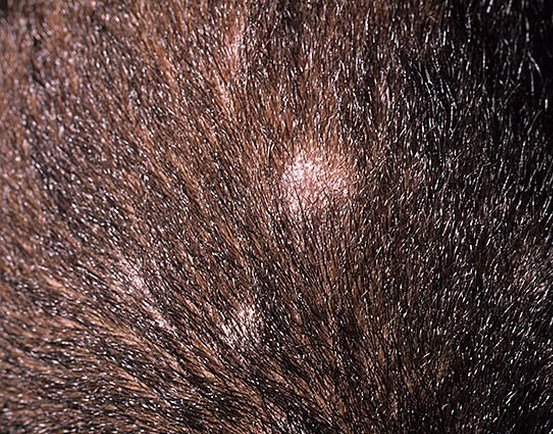
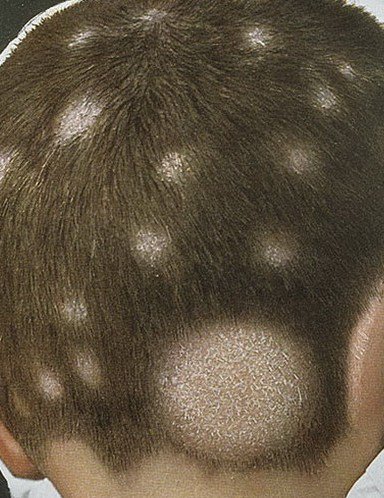
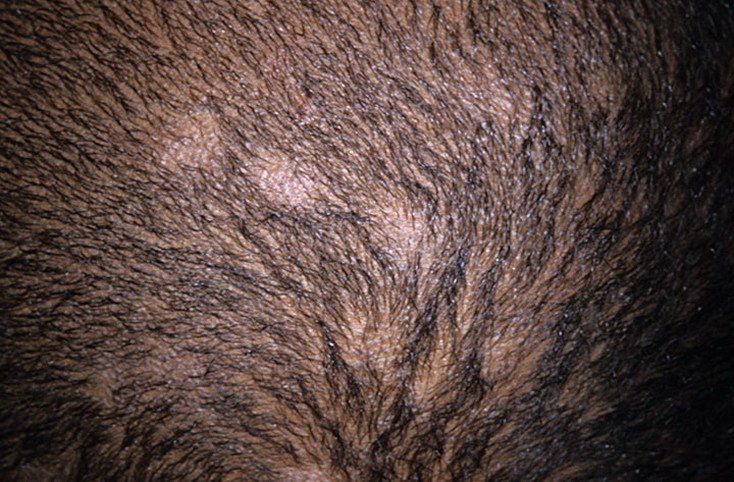
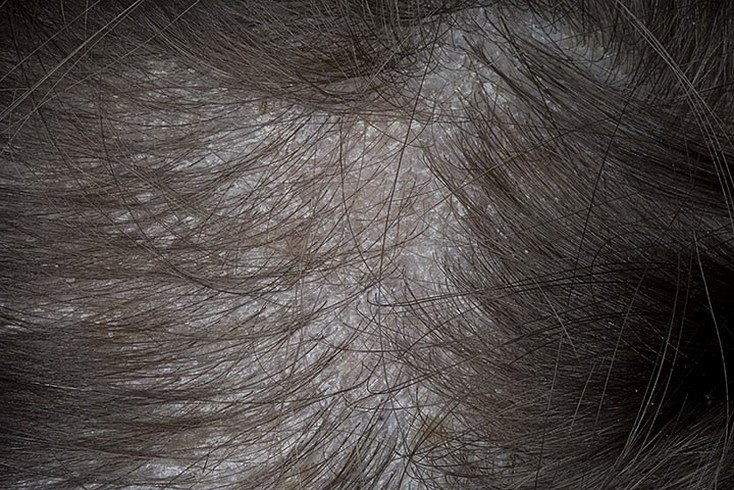
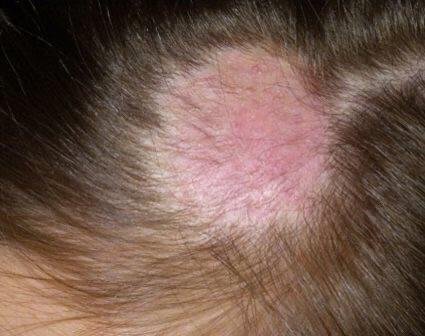
- Lesions: Round or oval scaly patches with mild redness or none at all; flaking and hair breakage are frequent;
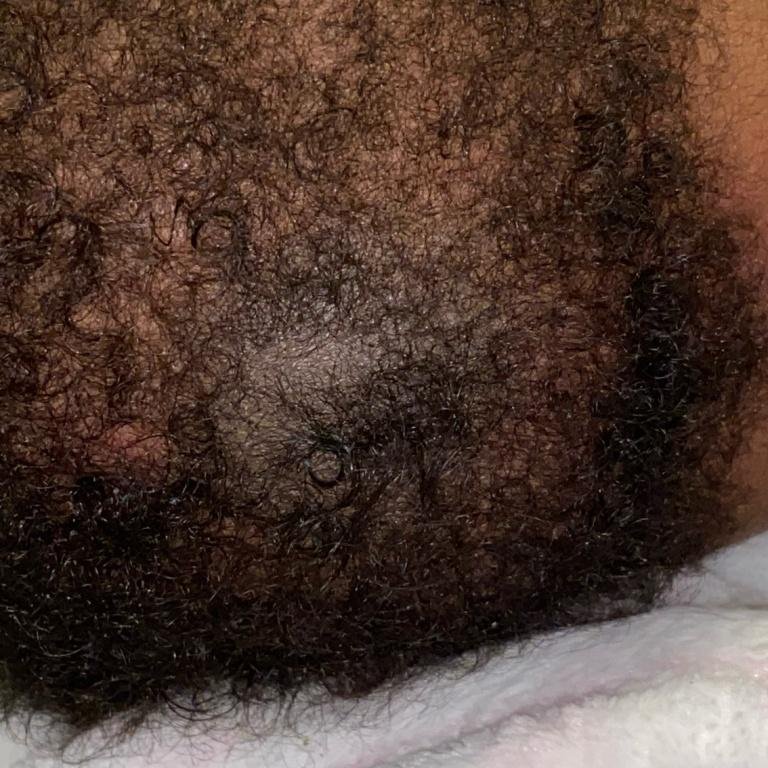
- Hair: Often broken at the scalp surface, creating bald patches with short hair stubs (“black dot” appearance);
- Location: Primarily the frontal and temporal scalp;
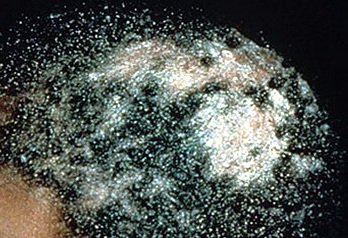
- Wood’s lamp: Hair infected with Microsporum fluoresces greenish under UV light;
- Appearance: In seborrheic type, resembles dandruff or dry seborrhea.
2. Inflammatory Type (Kerion)
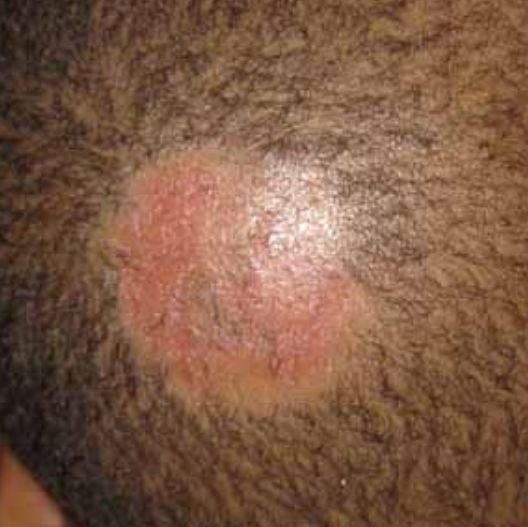
Triggered by zoophilic species such as Microsporum canis, or the geophilic Nannizzia gypsea (formerly Microsporum gypseum). This variant leads to a deep, painful inflammatory lesion.
- Lesions: 1–3 swollen, pustular plaques with intense erythema and purulence;
- Hair: Loosens easily and may fall out or be removed without resistance;
- Risk: May lead to cicatricial (scarring) alopecia if not treated promptly;
- Symptoms: Pain, edema, regional lymphadenopathy, and systemic malaise may be present.
3. “Black Dot” Tinea Capitis
This is the least inflammatory form of scalp ringworm and is caused by Trichophyton tonsurans. The hallmark feature is the presence of short, broken hairs at follicular openings which appear as black dots on close examination.
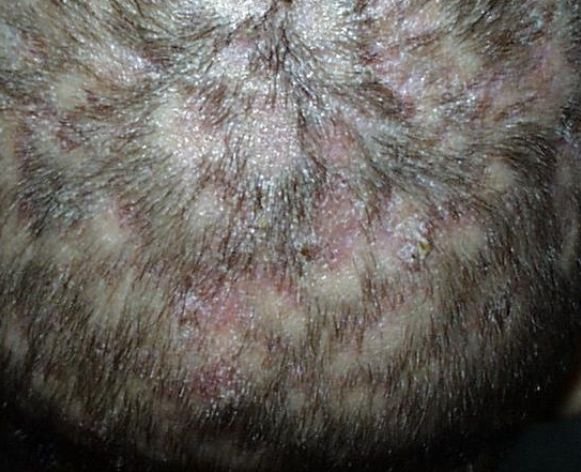
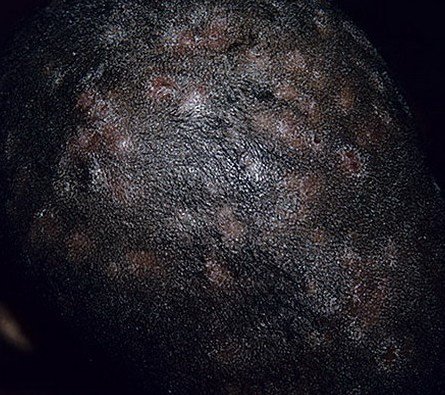
- Lesions: Multiple round or irregular patches, covered with fine scaling;
- Hair: Broken off at or below scalp level, producing black dot pattern;
- Complications: Risk of chronic infection and atrophic alopecia.
Clinical Forms of Tinea Barbae
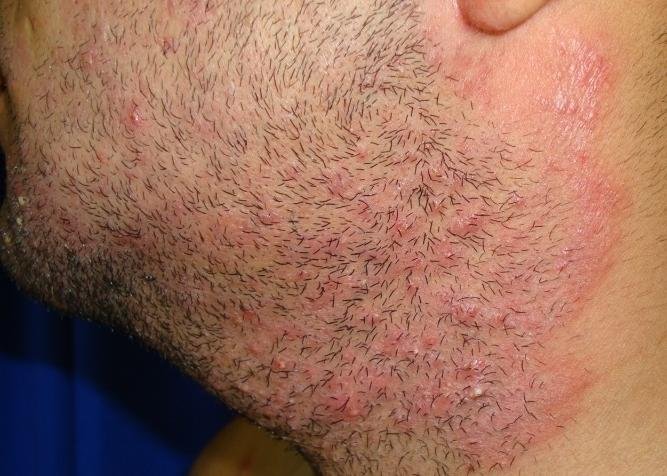
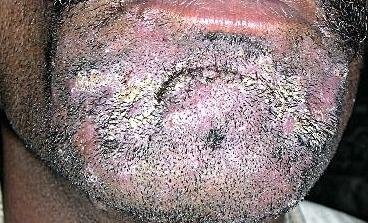
Tinea barbae affects adult males in the beard and mustache area and is most commonly caused by zoophilic fungi such as Trichophyton mentagrophytes and T. verrucosum.
1. Inflammatory Type (Parasitic Sycosis)
- Symptoms: Painful, nodular, and pustular lesions resembling kerion, with purulent discharge from follicular openings;
- Hair: Easily extracted with purulent material at the base.
2. Superficial Type
- Lesions: Mild follicular inflammation, erythema, and scaling that resemble bacterial folliculitis;
- Inflammation: Less severe than the kerion-type presentation.
3. Annular Type
- Appearance: Ring-shaped patches with elevated, scaling borders containing vesicles or crusts;
- Central area: Tends to clear partially, forming a classic tinea ring pattern similar to tinea corporis.
Diagnosis
Accurate diagnosis is critical for effective treatment and infection control. Diagnostic steps include:
- Wood’s lamp examination: Useful for detecting Microsporum species, which fluoresce under UV light;
- Microscopy: Direct KOH examination of plucked hairs or skin scales to detect fungal hyphae or spores;
- Cultural examination: Clinical examination with KOH microscopy usually suffices; culture on Sabouraud agar identifies the species and is most useful for atypical, recurrent or treatment-resistant cases;
- PCR testing: Highly specific molecular technique used to identify fungal DNA in clinical specimens;
- Epidemiological investigation: Important in the context of outbreaks or school-based transmission.
Differential Diagnosis
These infections can mimic various dermatologic and systemic conditions, making differential diagnosis essential to avoid mismanagement. Important conditions to distinguish from include:
- Alopecia areata: Sudden onset of patchy hair loss with smooth skin, no scaling or inflammation;
- Discoid lupus erythematosus: Erythematous, scarring plaques with follicular plugging and atrophy;
- Psoriasis and seborrheic dermatitis: May present with scaling on the scalp but lack hair breakage or inflammation;
- Pseudopelade of Brocq: Slowly progressive scarring alopecia with smooth, ivory-colored patches;
- Bacterial sycosis (folliculitis barbae): Painful pustules limited to beard area but caused by bacterial infection;
- Secondary syphilis (impetiginous syphilid): Must be ruled out in the presence of scaling and alopecia, especially in high-risk populations.
Treatment
Management involves both systemic antifungal therapy and adjunctive local treatment. Treatment should be guided by the clinical picture and, where mycology is available, by the species identified.
Systemic Antifungal Agents:
- Griseofulvin: Often preferred for Microsporum infections; well-tolerated and suitable for paediatric use (available as suspension);
- Terbinafine: Often more effective against Trichophyton species; used in both children and adults. Which agent is chosen follows the clinical picture and, where available, the mycology;
- Itraconazole: Broader-spectrum antifungal effective in resistant or recurrent cases.
How long systemic treatment runs depends on the organism and the drug: griseofulvin courses for Microsporum infections are generally longer than terbinafine courses for Trichophyton, and the clinical response and extent of infection also shape it.
Topical Therapy:
Used as adjunctive therapy only. Topical agents do not reach the fungus inside the hair shaft, so on their own they do not clear the infection. Options include:
- Topical antifungals: Adjuncts only. Tinea capitis and tinea barbae require systemic treatment, because topical agents do not reach the fungus inside the hair shaft and follicle;
- Antifungal shampoo: Ketoconazole or selenium sulfide, to reduce shedding of spores. An adjunct, not a treatment;
- Compounded preparations: Keratolytic and antiseptic lotions are still prescribed in some places, but they are not part of standard evidence-based care and do not substitute for systemic treatment.
Supportive Care and Hygiene During Treatment
Effective treatment requires not only medication but also proper hygiene and behavior modifications to reduce reinfection and transmission:
- Hair care: Routine weekly shaving or clipping is not needed, does not help the treatment, and risks injuring the skin and spreading the infection;
- Antifungal shampoo: Ketoconazole or selenium sulfide shampoo reduces shedding of spores and transmission to others. It is an adjunct and does not replace systemic treatment;
- Barrier protection: Use gauze or cotton head coverings to prevent spread; discard or sterilize daily;
- Avoid sharing personal items: Towels, combs, hats, razors should not be shared;
- Social hygiene: Avoid sharing hats, combs and towels. Isolation is not required once antifungal treatment has started.
Prevention
Prevention of recurrence and transmission involves a combination of public health education and personal care:
- Prompt treatment: Seek early medical attention for suspicious lesions of the scalp or beard area;
- Screening contacts: Family members or classmates of infected individuals should be examined for signs of infection;
- Sanitization: Disinfect combs, brushes, and barber tools after each use;
- Pet care: Since zoophilic fungi are often transmitted by animals, inspect household pets and consult a veterinarian if needed;
- General health: Poor nutrition or reduced immunity may make an infection more likely in some people, but neither is needed for a dermatophyte to take hold, and a healthy child can catch it just as readily;
- Avoid trauma: Prevent scratching and damage to the scalp or beard area that facilitates fungal entry.
Conclusion
Tinea capitis and tinea barbae are infectious dermatophytoses with diverse clinical manifestations depending on the fungal species and host immunity. Early recognition, laboratory confirmation, and appropriate treatment are essential to prevent complications such as scarring alopecia or widespread outbreaks.
With a combination of systemic antifungal therapy, topical agents, personal hygiene, and contact precautions, most cases can be treated successfully. Continued awareness and patient education are key in reducing recurrence and community transmission of fungal hair infections.




Medical review
Board-Certified Dermatologist · Fellow of the American Academy of Dermatology (FAAD)