Papillomatous Nevus (ICD-10: D22) 💚
Papillomatous Nevus (Intradermal Melanocytic Nevus)
Papillomatous nevus is a particular kind of benign melanocytic nevus: a papillomatous, intradermal nevus that rises above the surface of the skin. It is one member of the broader family of benign melanocytic nevi, not a synonym for the family as a whole. This type of nevus is generally acquired, and its occurrence tends to increase with age, peaking between the ages of 15 and 30. Papillomatous nevi are often characterized by their multiplicity, and the number of such lesions tends to increase over time. In terms of gender, papillomatous nevi are somewhat more common in women compared to men, with a ratio of 3:2, respectively.
Predisposing Factors
The exact cause of papillomatous nevi remains unclear. However, several predisposing factors have been identified that may increase the risk of developing these skin neoplasms. These factors can influence the onset and growth of papillomatous nevi:
- Genetic Factors: A genetic predisposition may play a role in the appearance of papillomatous nevi.
- Ultraviolet Radiation: Sun exposure is associated with the number of acquired nevi a person develops, and with melanoma risk generally. It is not established that ultraviolet radiation causes a papillomatous nevus to appear or to grow.
Diagnostics
The diagnosis of papillomatous nevi is primarily based on a clinical examination, which includes visual inspection of the lesions and dermatoscopy to assess the structure of the growths. If malignant growth is suspected, a biopsy may be conducted to obtain a definitive diagnosis and rule out other skin conditions.
Symptoms
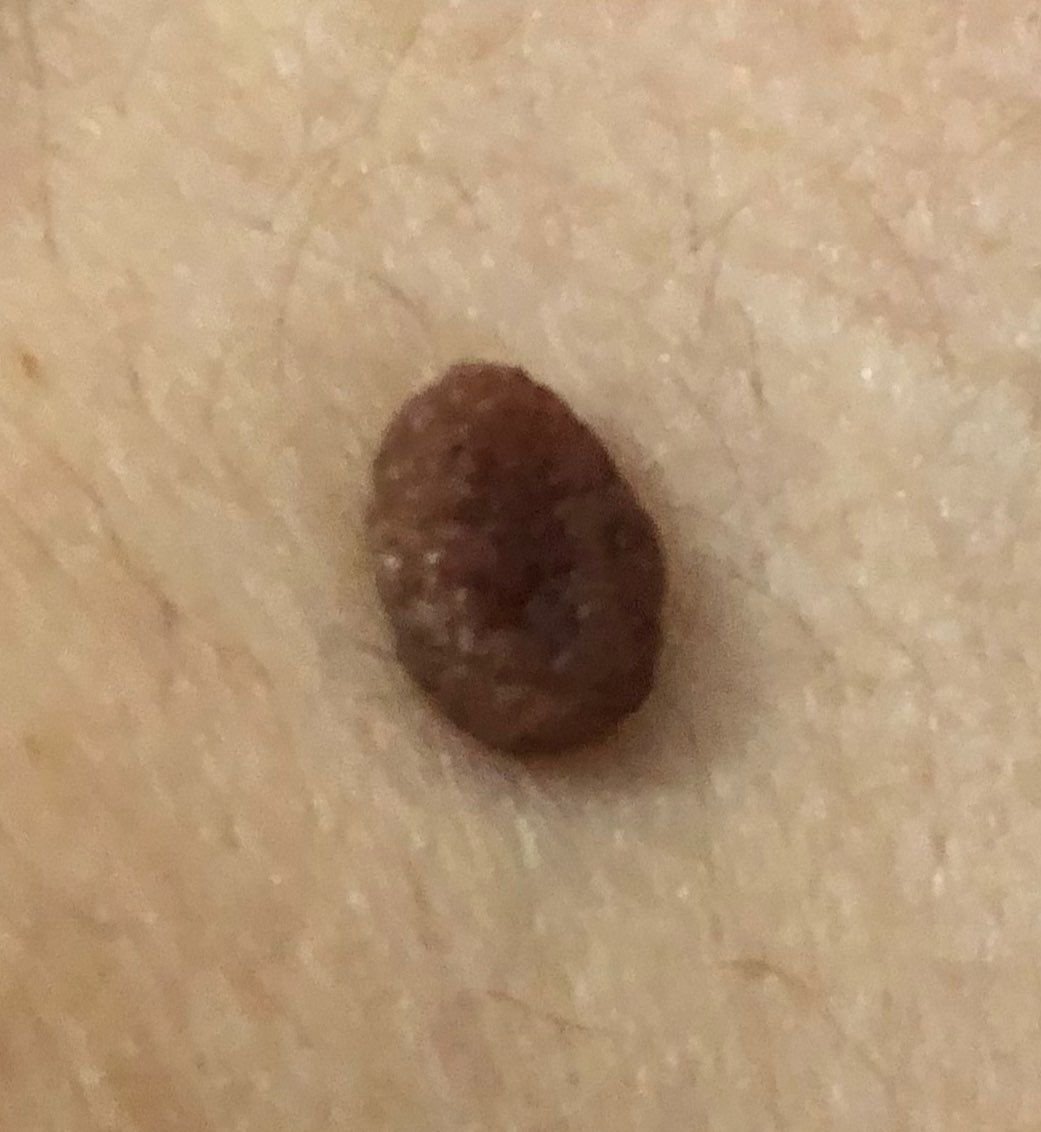
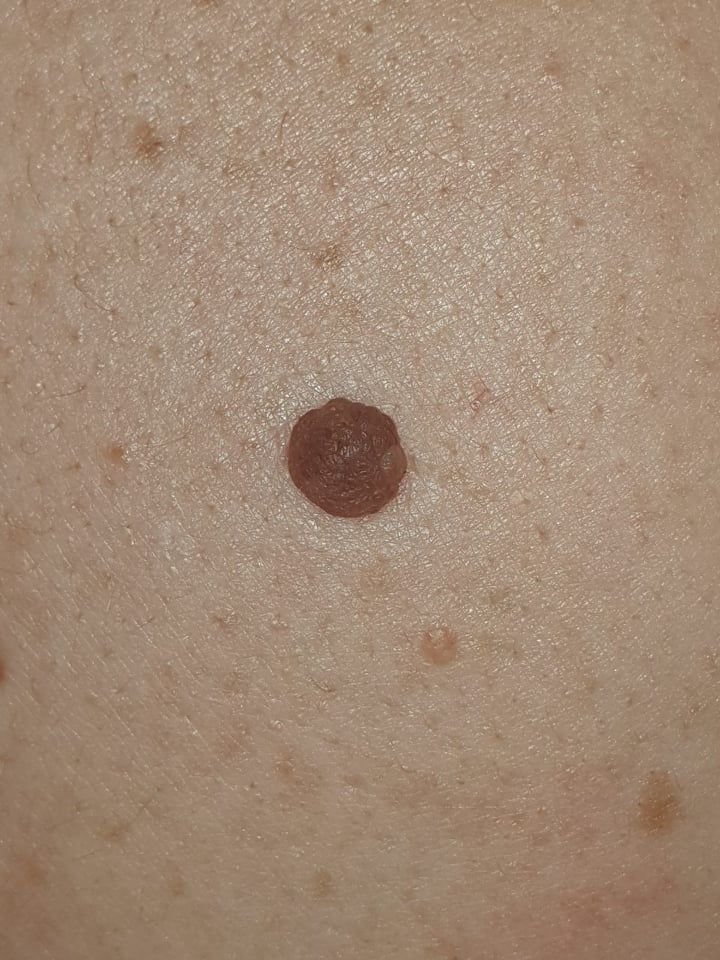
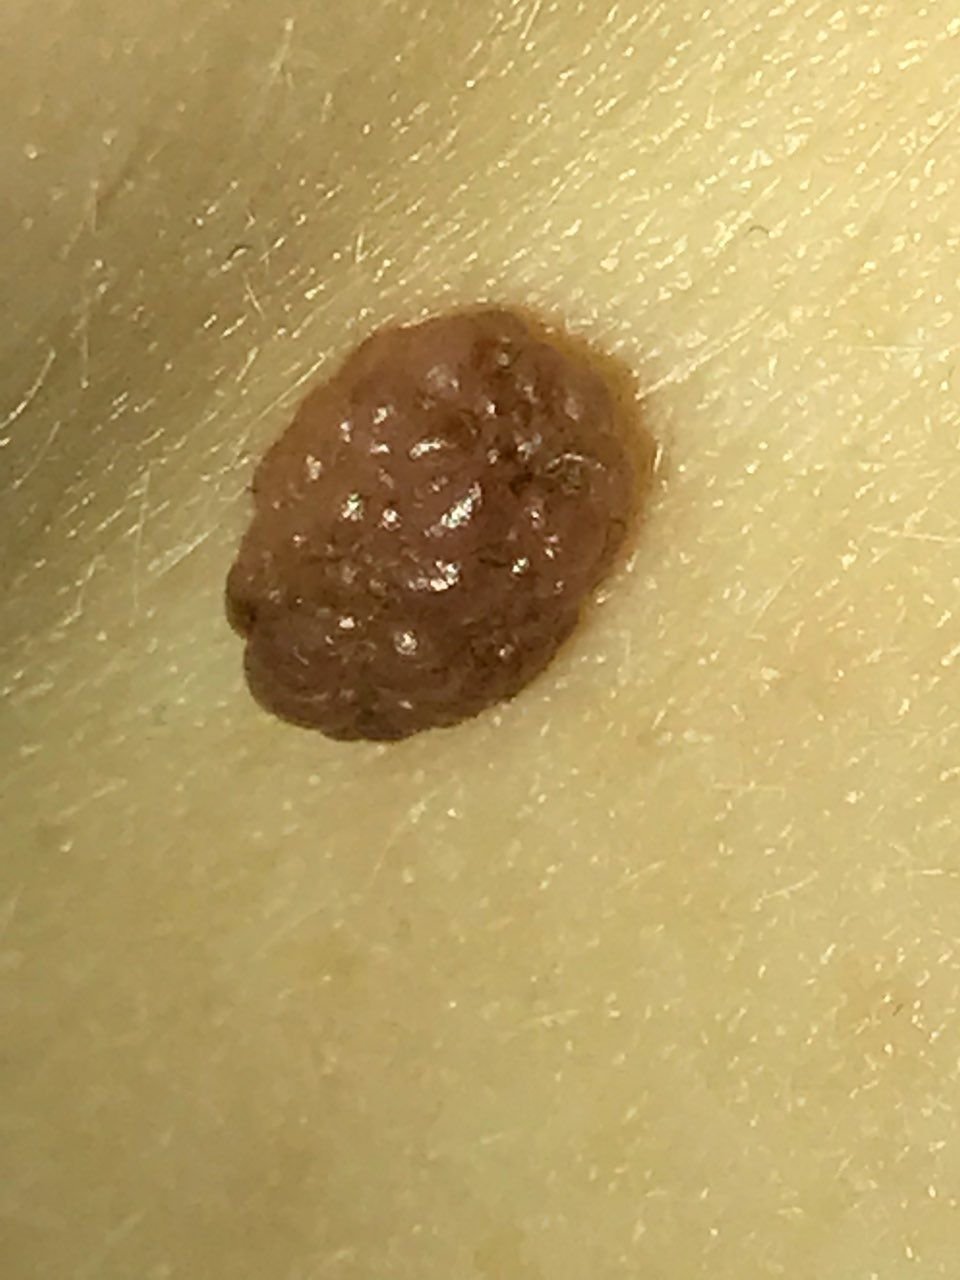
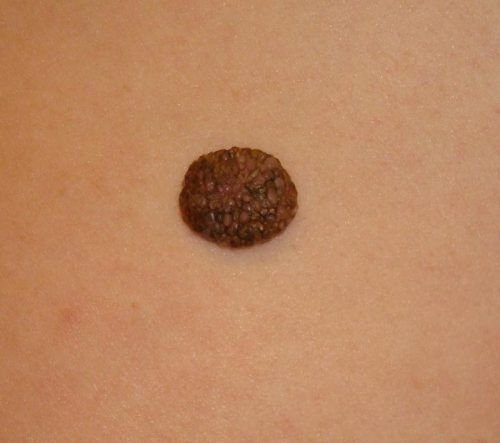
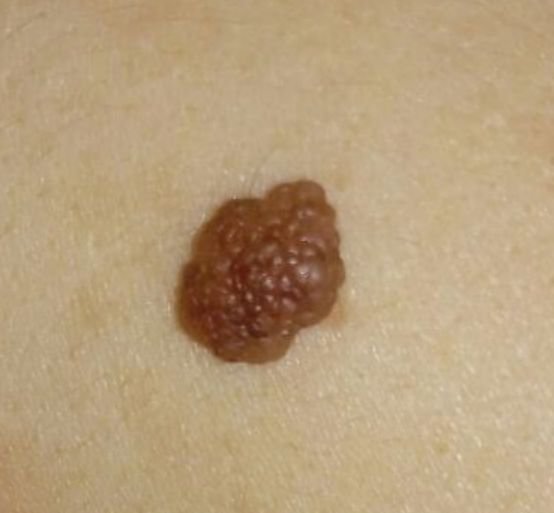
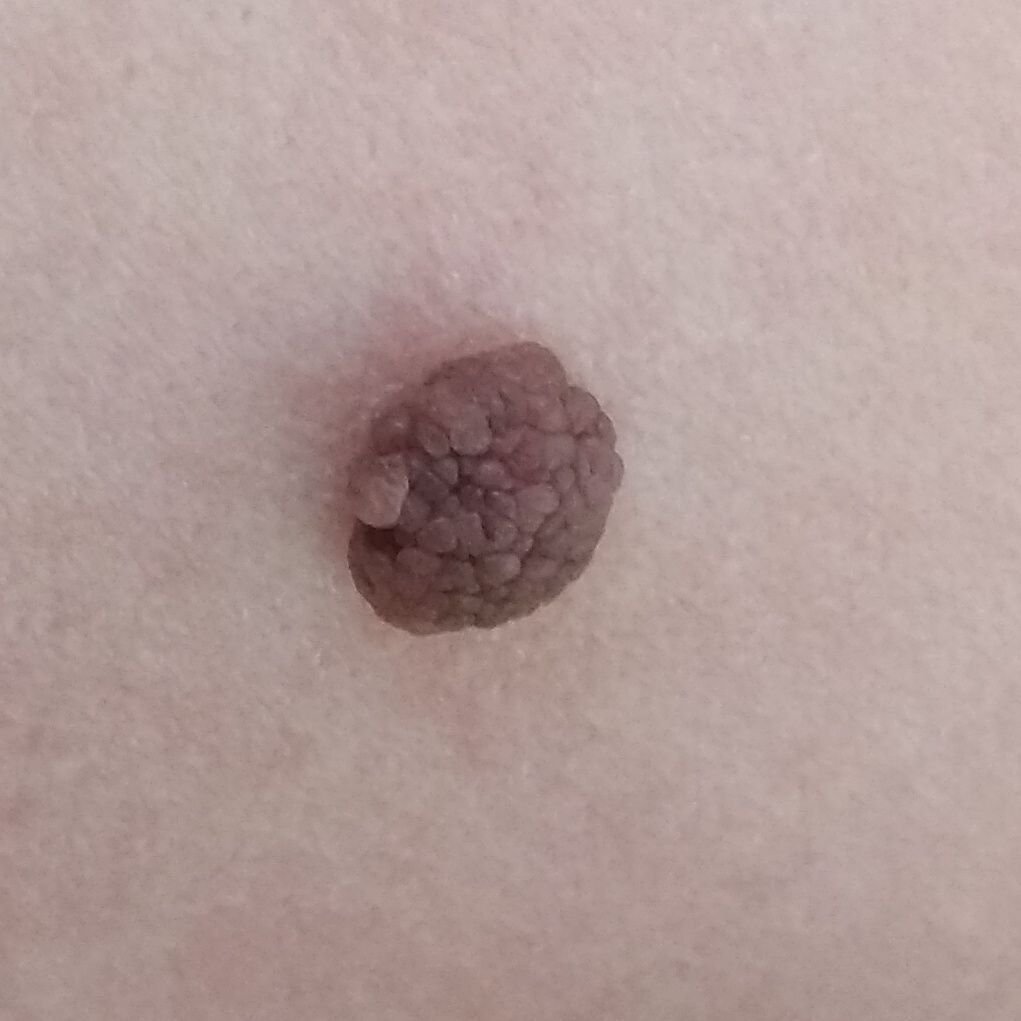
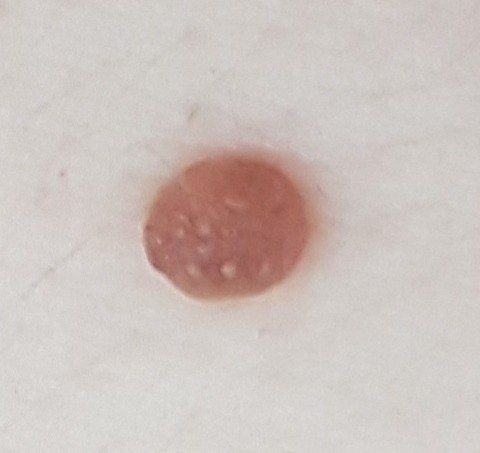
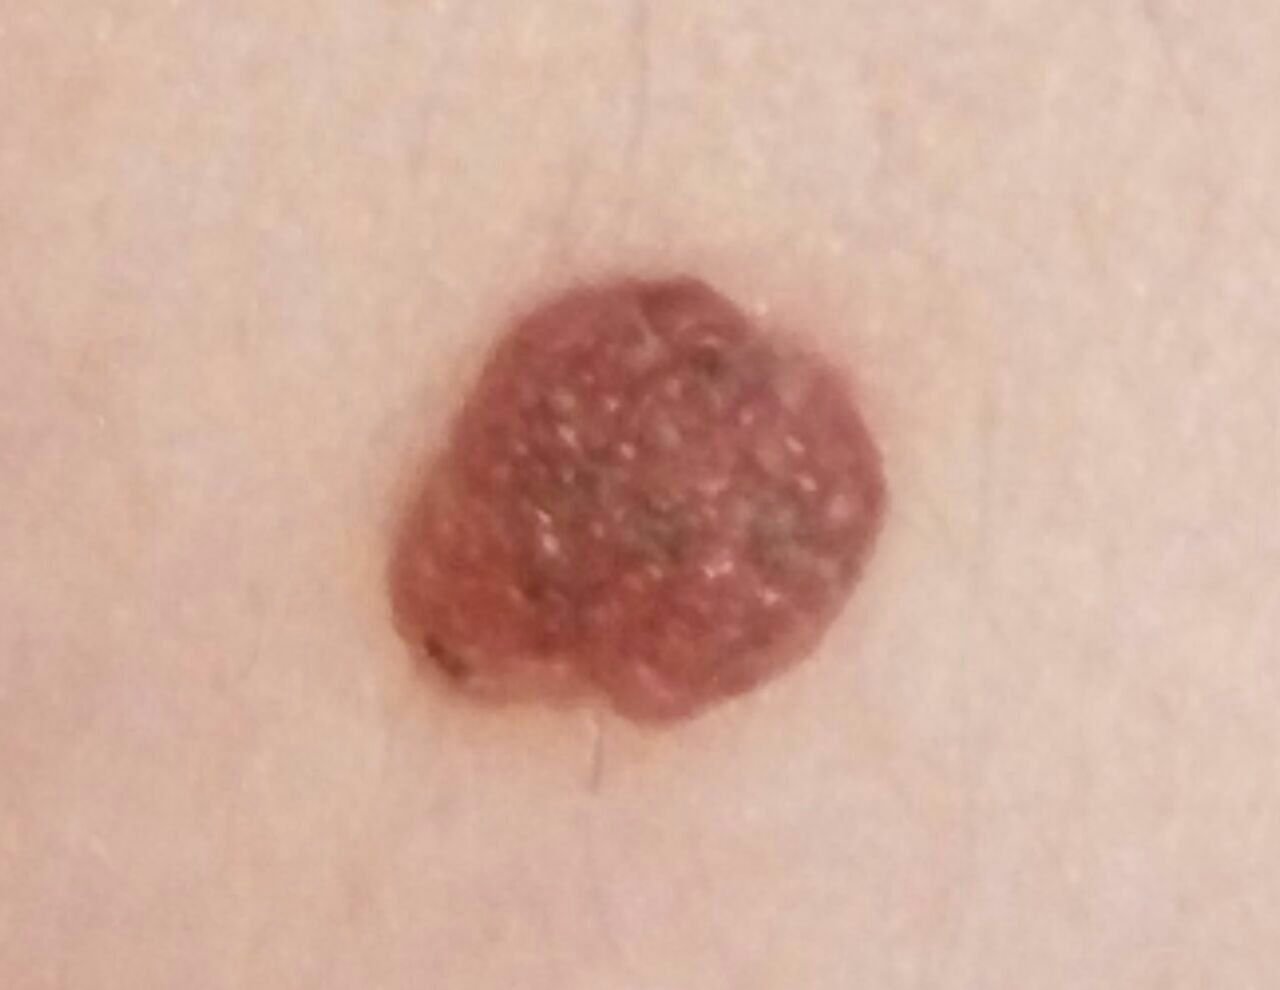
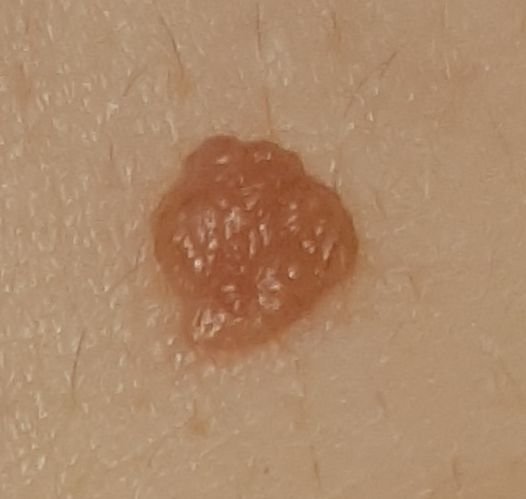
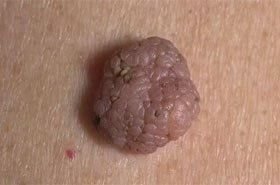
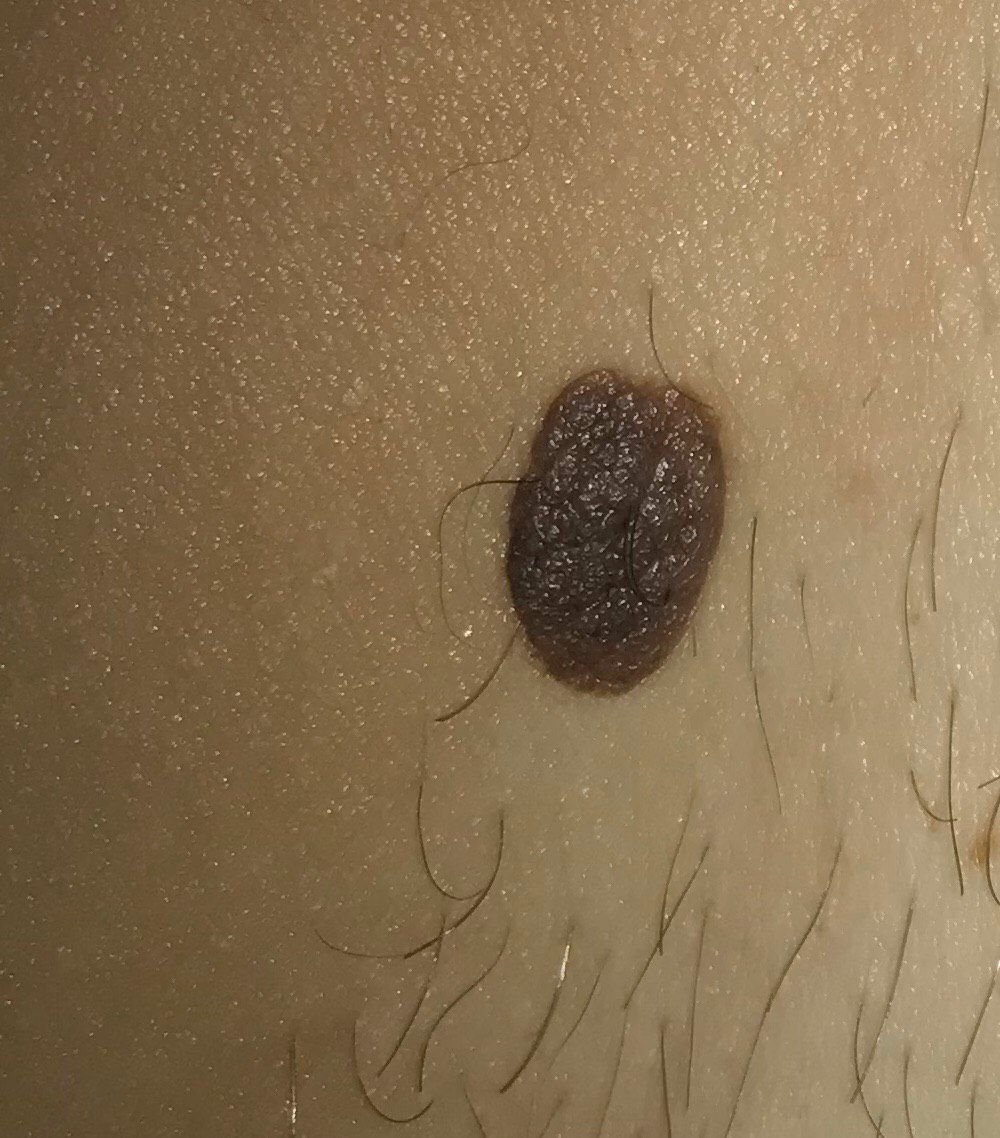
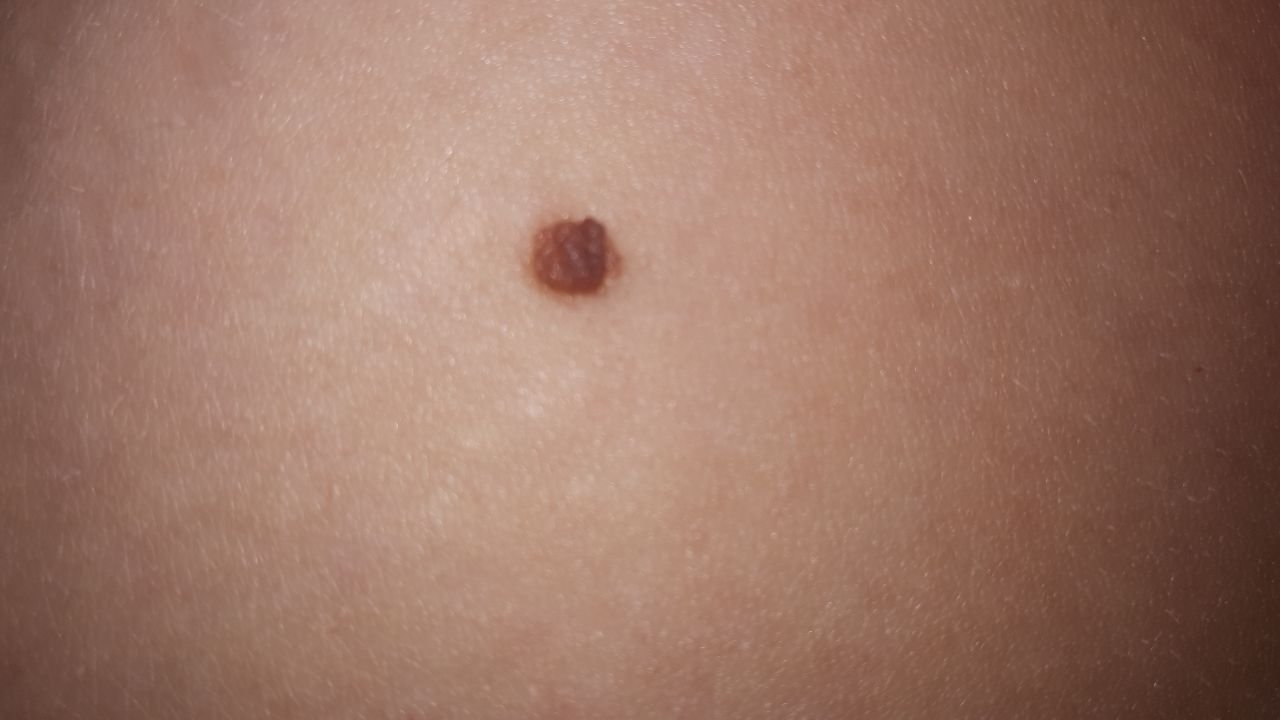
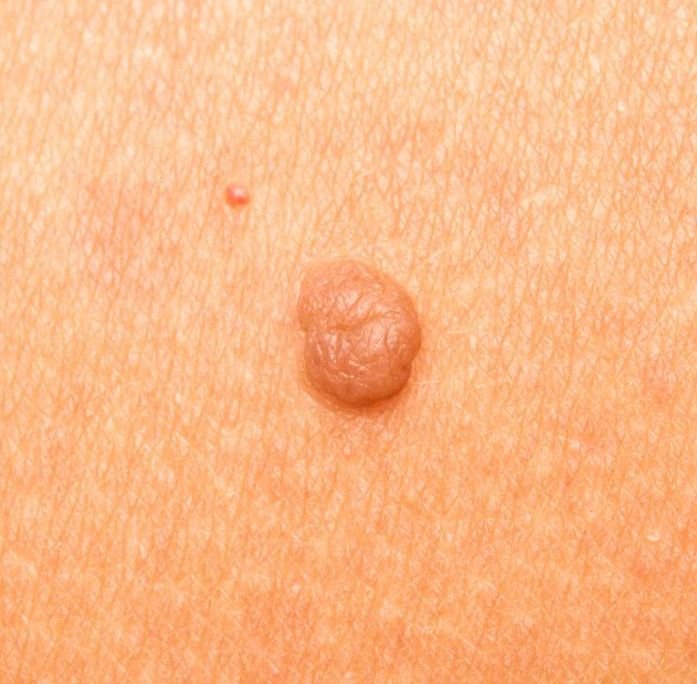
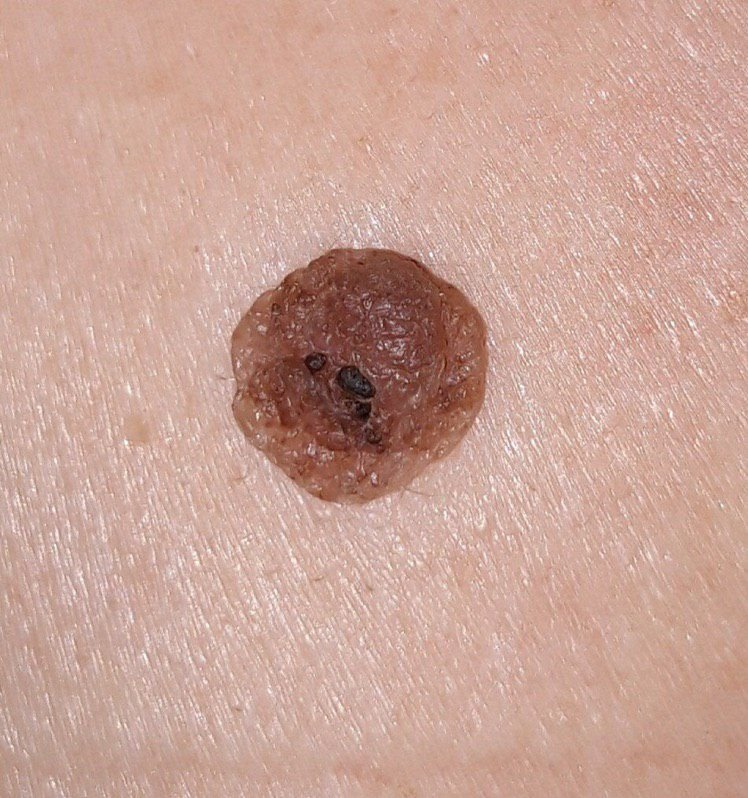
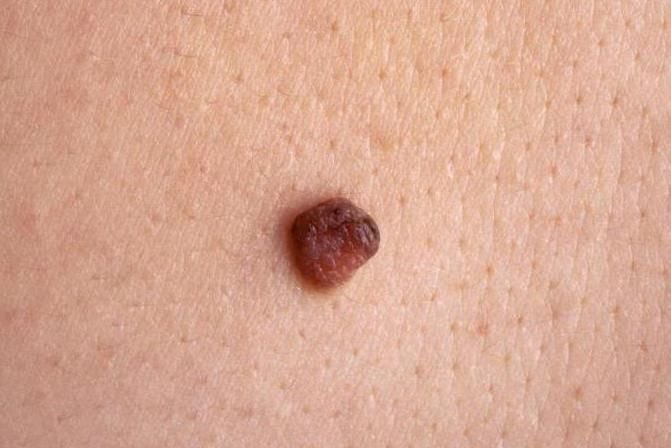
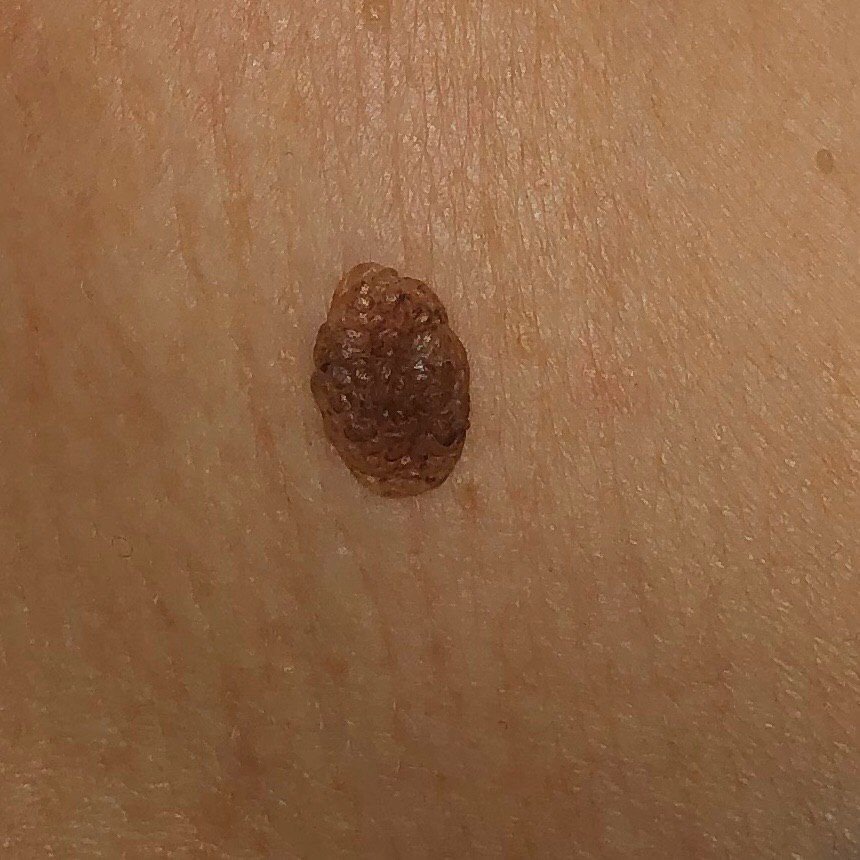
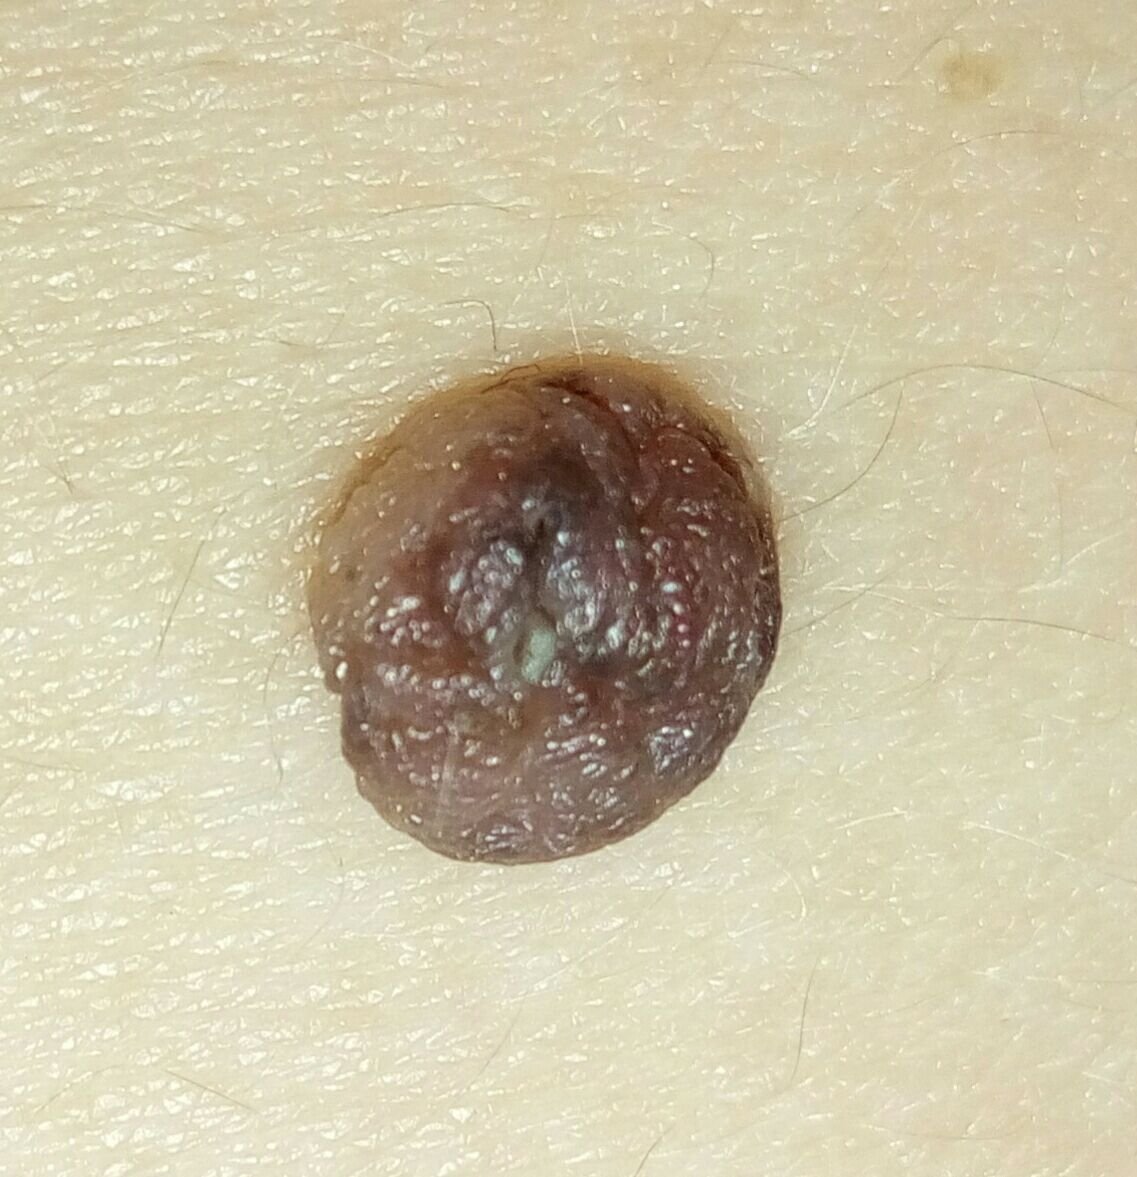
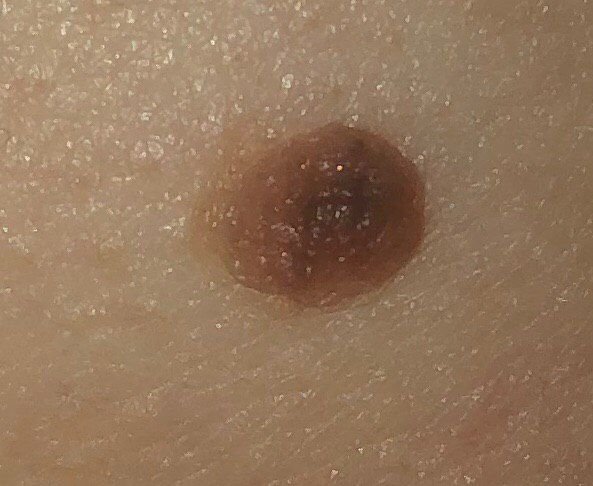
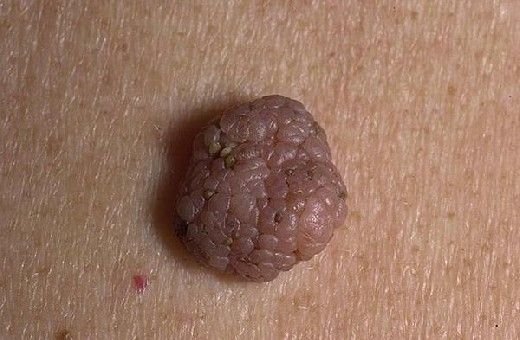
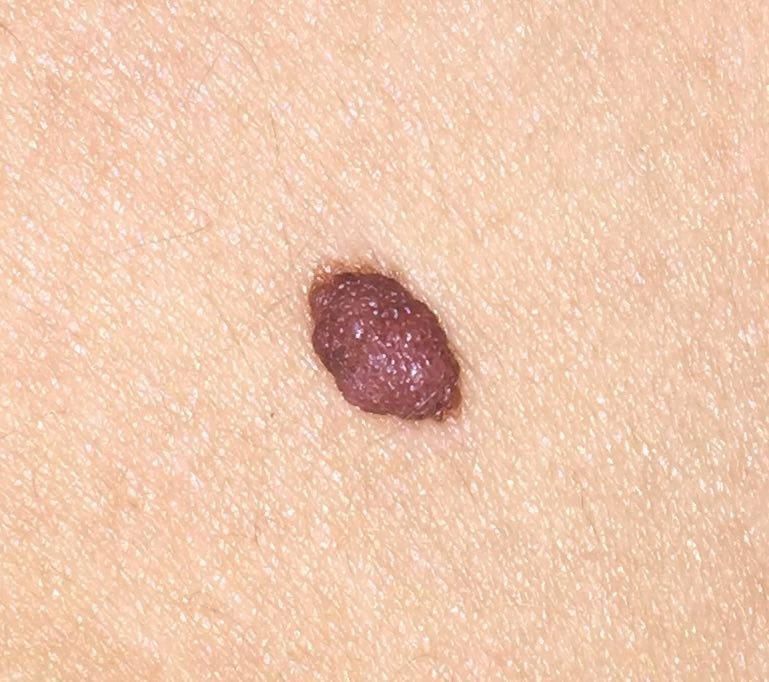
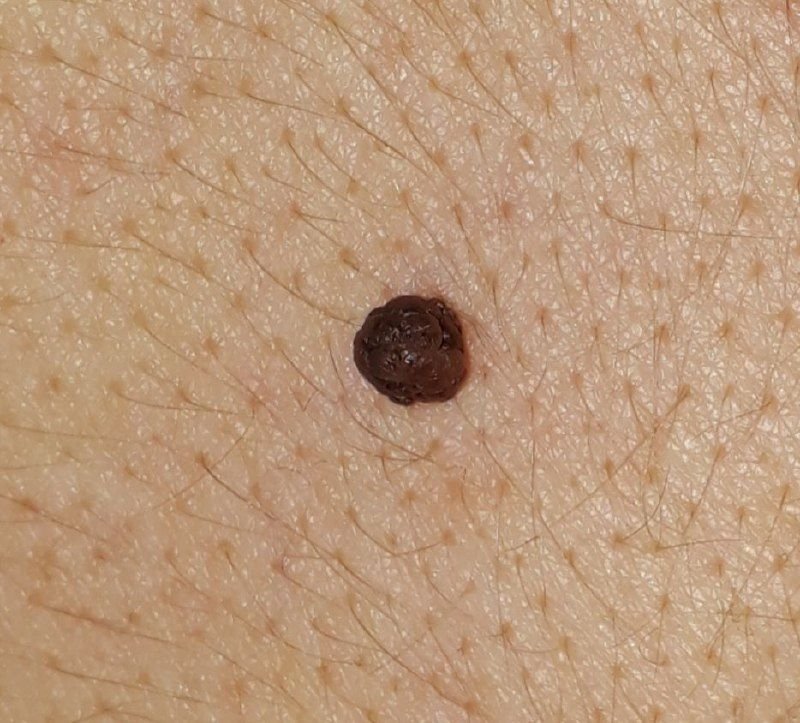
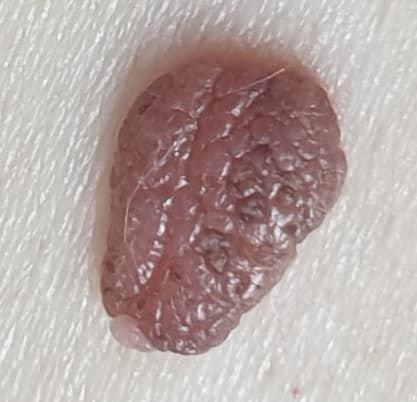
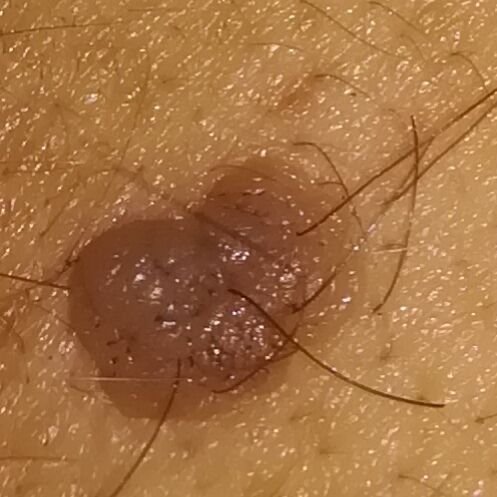
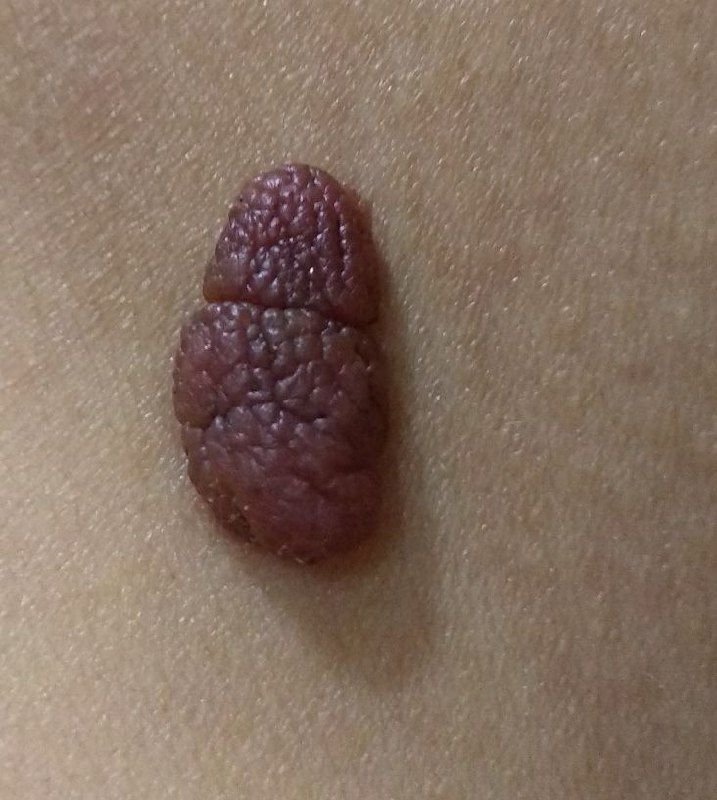
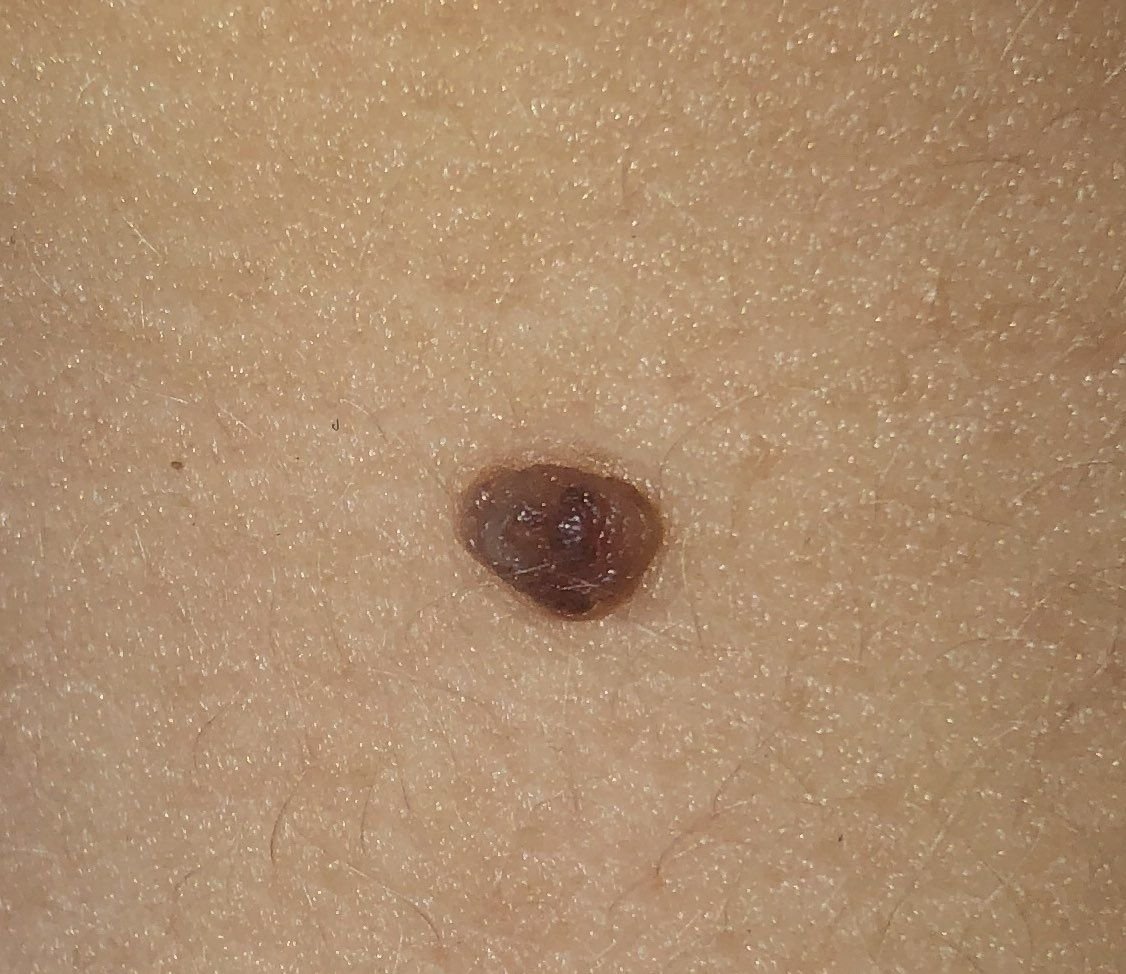
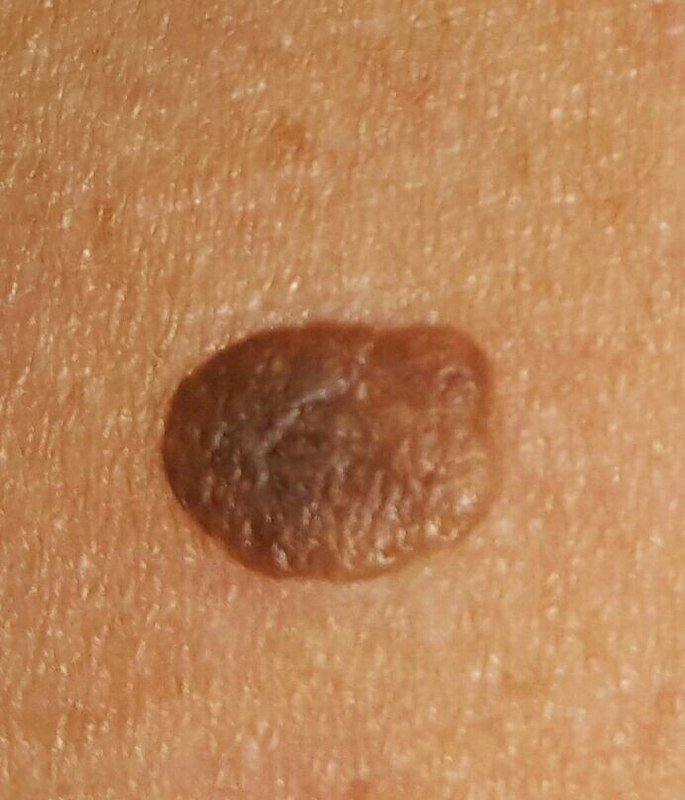
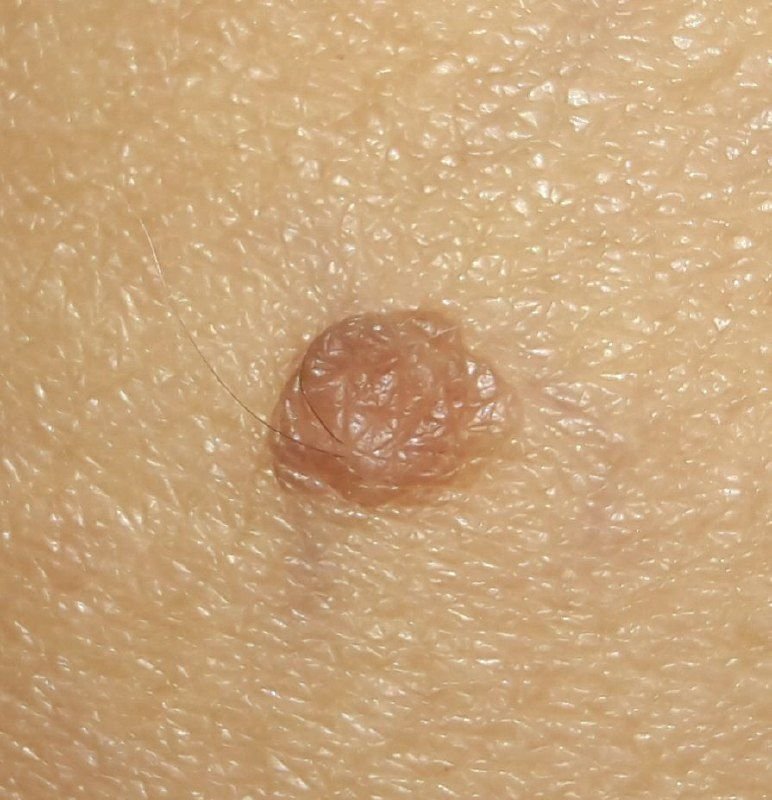
Upon visual examination, a papillomatous nevus typically presents as a hemispherical or slightly elevated growth that rises above the skin on a short, wide stalk (pedicle). The shape of the lesion is most often symmetrical (oval or round), though large nevi may have irregular shapes. The surface of the nevus may vary, with smaller papillomatous nevi exhibiting a smooth texture resembling normal skin, while larger nevi may appear slightly tuberous or even rough. Larger papillomatous nevi (over 8 mm) may have a coarse, warty surface, which is characteristic of verrucous nevi.
The borders of papillomatous nevi are typically clear and even, although larger nevi may have uneven edges. The color of the nevus can range from flesh-colored to tan and dark brown, and the pigment distribution is typically uniform. Occasionally, there is a gradual decrease in color intensity from the center to the periphery or slight variations in shade within the same lesion (which is typical for verrucous nevi).
Hair growth in the area of a papillomatous nevus is typically unaffected. In some cases, coarse bristly hair may develop in the center, especially in congenital papillomas, or downy hair may appear in areas of hypopigmented papillomatous nevi.
The size of papillomatous nevi can vary widely, with most lesions measuring up to 15 mm in diameter. Nevi larger than 15 mm are rare. The height of these nevi above the skin level is usually less than 10 mm. Large papillomatous nevi that resemble cauliflower are quite rare.
On palpation, papillomatous nevi have a consistency similar to that of normal skin, though larger lesions may feel slightly softer. There are typically no subjective symptoms associated with papillomatous nevi, although mild itching may occasionally occur in long-standing forms.
These neoplasms are most commonly located on the face, scalp, neck, and trunk (including the chest and back), though they can occasionally appear on other areas of the body.
Dermatoscopic Description
When examining a papillomatous nevus under dermatoscopy, the following features are typically observed:
- Cobblestone Street Pattern: A network of oval pigment elements forming a cobblestone-like appearance.
- Papillary Structures: Uneven, tuberous structures that appear flattened due to the pressure applied during dermatoscopy.
- Globules: Large hyperpigmented, ring-like structures that are evenly distributed across the nevus or concentrated in the center, sometimes with gray-brown globules characteristic of hyperkeratosis.
- Spots: Hyperpigmented, structureless areas found in the central part of the lesion or along the pigmented lines.
- Diffuse Uniform Staining: The entire lesion may show even pigmentation.
Differential Diagnosis
It is important to differentiate papillomatous nevi from other pigmented or nodular skin lesions, such as:
- Nevus of the sebaceous glands
- Halo nevus
- Spitz nevus
- Blue nevus
- Dysplastic nevus
- Melanoma
Risks
Papillomatous nevi are benign and do not carry an increased risk of melanoma or other malignancies. Papillomatous nevi are typically benign; suspicious changes should be evaluated to exclude other lesions. However, signs of potential malignancy include a change in the appearance of the nevus (such as rapid growth or irregular shape), an increase in its density, and the appearance of subjective sensations like pain or itching.
The primary risk associated with papillomatous nevi is their tendency to become easily injured due to their elongated shape and narrow stalk. When this occurs, the lesion can bleed, become painful, and create an opening for pathogenic microorganisms, leading to infection. Papillomas can also cause psychological discomfort, especially when located in visible areas.
Papillomatous nevi are benign melanocytic lesions and are not caused by HPV; they are distinct from cutaneous warts.
Tactics
A lesion you have not had looked at is a different matter from one a clinician has already identified. Monitoring follows assessment, not the other way round: a pigmented lesion that has not been examined should be shown to a dermatologist. Melanoma can be nodular or papillomatous, and a raised pigmented lesion cannot be classified from its appearance alone.
Once a lesion has been assessed as a papillomatous nevus and is stable, watching it between reviews is reasonable. Go back sooner for asymmetry, variation in colour, bleeding, ulceration, persistent crusting, rapid growth, or a lesion that has begun to look unlike your others.
The healthcare provider will determine whether dynamic monitoring is sufficient or if removal of the lesion is recommended. Nevi that are subject to constant or chronic trauma, such as from clothing, jewelry, or professional activities, should be removed to prevent further injury. Additionally, some individuals may wish to remove papillomatous nevi for cosmetic or psychological reasons.
For dynamic observation, it is useful to take photographs of the nevi to monitor any changes over time. How often a person should be examined is not fixed by the calendar: it depends on the characteristics of their lesions and on their overall melanoma risk. What does warrant assessment is a specific change — asymmetry, a lesion that is evolving, bleeding, or one that simply looks unlike the person’s other moles.
Treatment
A papillomatous nevus is a melanocytic lesion, and that governs how it is treated. Where the diagnosis is in any doubt, the lesion is removed completely and sent for histopathology. Laser, cryotherapy, radiofrequency and electrocoagulation destroy the tissue, leaving nothing for the pathologist to examine, so they are not interchangeable alternatives to excision and must not be used on a lesion that has not been assessed.
A nevus that is clearly benign and simply protrudes may be removed because clothing catches it, because it is repeatedly irritated, or for cosmetic reasons. In that situation the method is chosen for the individual lesion:
- Laser Removal: Used for benign protruding lesions of varying shapes and sizes.
- Cryodestruction: Liquid nitrogen is used on small, superficial lesions, although this method carries a risk of scarring.
- Radio Wave Scalpel Removal: A radiofrequency scalpel allows precise, minimally invasive removal.
- Electrocoagulation: This technique uses electrical currents to remove the lesion.
Self-removal of papillomatous nevi is strongly discouraged due to the risk of complications, such as bleeding, infection, and misdiagnosis of the lesion’s nature. If a papilloma is removed surgically, careful monitoring is necessary to ensure the area heals properly and to detect any recurrence.
Prevention
The prevention of papillomatous nevi involves proper care of the skin and addressing underlying health factors:
- Avoiding excessive ultraviolet radiation, including tanning beds and prolonged sun exposure.
- Using sunscreen and protective clothing during periods of high sun exposure.
- Minimizing chronic skin trauma to areas with existing nevi.
- Maintaining good personal hygiene and being vigilant for changes in skin health.
Regularly inspecting papillomatous nevi, consulting a healthcare professional if any changes occur, and removing potentially dangerous lesions are essential for maintaining skin health.