Papilloma (ICD-10: B07) 💚
Skin Papilloma
Skin papilloma is a benign growth that rises above the surface of the skin. The term is a broad one, and the names often used alongside it are not interchangeable. A filiform wart is a verruca caused by the human papillomavirus. A benign papillomatous skin lesion, by contrast, may have no viral cause at all. Because the treatment and the significance differ, it matters which of these a particular lesion is — and that is a question for examination, not for the name. These lesions typically begin to appear during adolescence and become more numerous with age.
Predisposing Factors
Many cutaneous papillomas and warts are associated with the human papillomavirus (HPV), though some benign papillomatous lesions are non-viral, which is generally associated with a low oncogenic risk. However, given that nearly 90% of the population carries the HPV virus but not everyone develops papillomas, it is evident that other factors contribute to the occurrence of these lesions on the skin. The following factors are known to increase the likelihood of developing papillomas:
- Immunodeficiency States: Weakened immune systems, whether due to conditions like HIV or immunosuppressive treatments, can predispose individuals to develop papillomas.
- Exposure to HPV: For warts, contact with the virus is what matters — skin-to-skin contact, or shared surfaces and objects. This is relevant to HPV-associated lesions and not to papillomatous lesions of other origin.
Diagnostics
The diagnosis of papillomas is based on a clinical examination, which includes a routine visual inspection of the lesions followed by dermatoscopy to examine the structure of the growths. Laboratory testing for HPV is not part of this: it is not required for an ordinary cutaneous wart or papillomatous lesion and does not establish the diagnosis. Where the diagnosis is uncertain, or where malignancy is a possibility, a biopsy is the appropriate step.
Symptoms
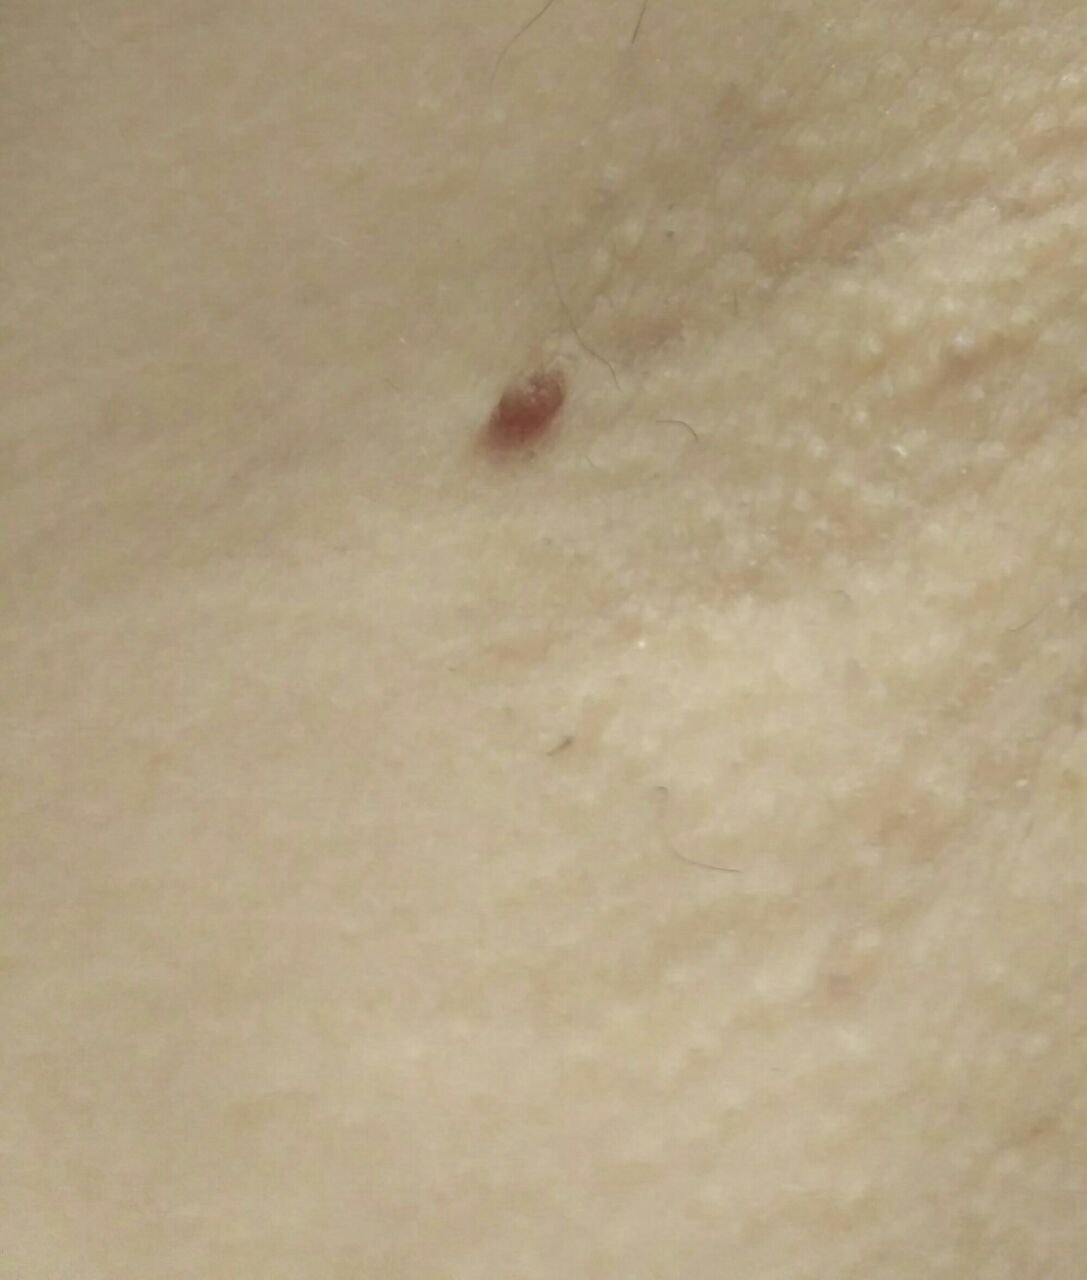
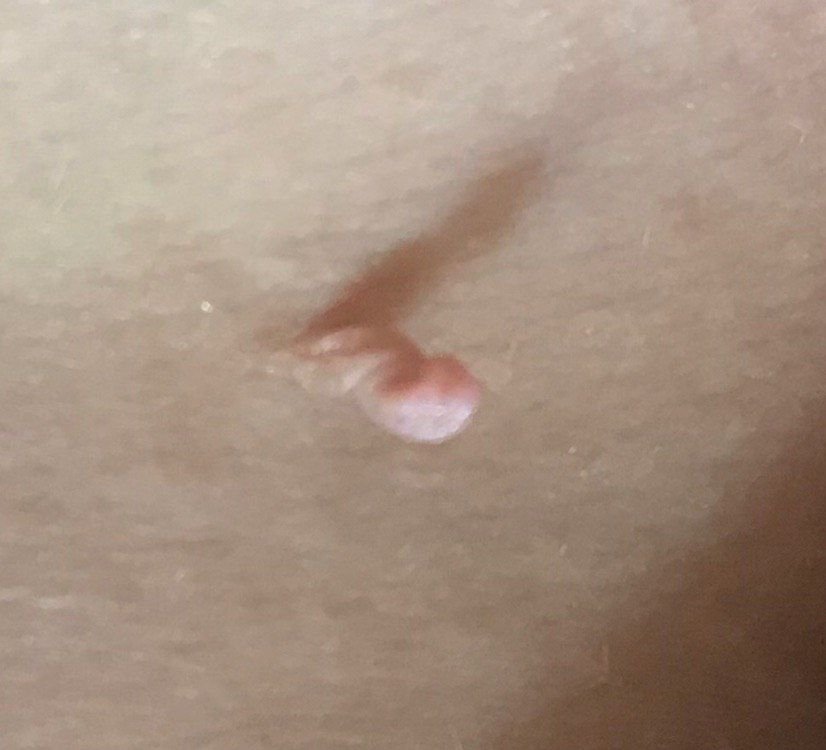
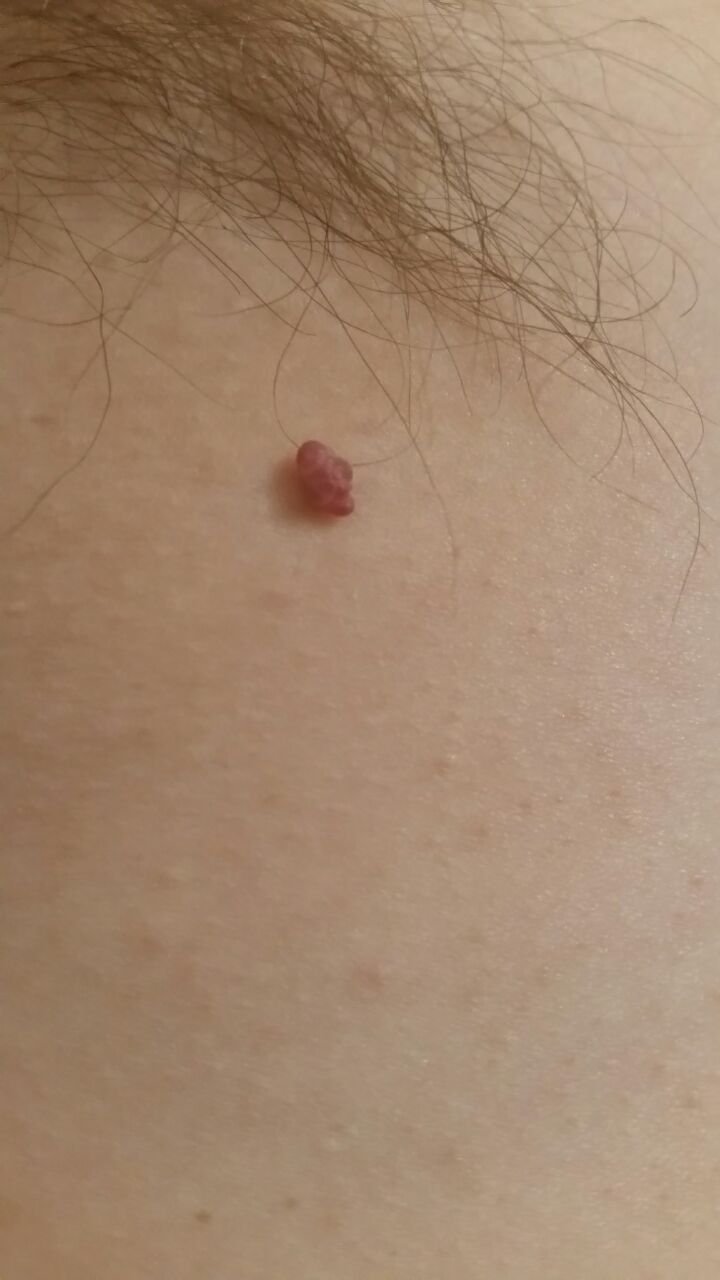
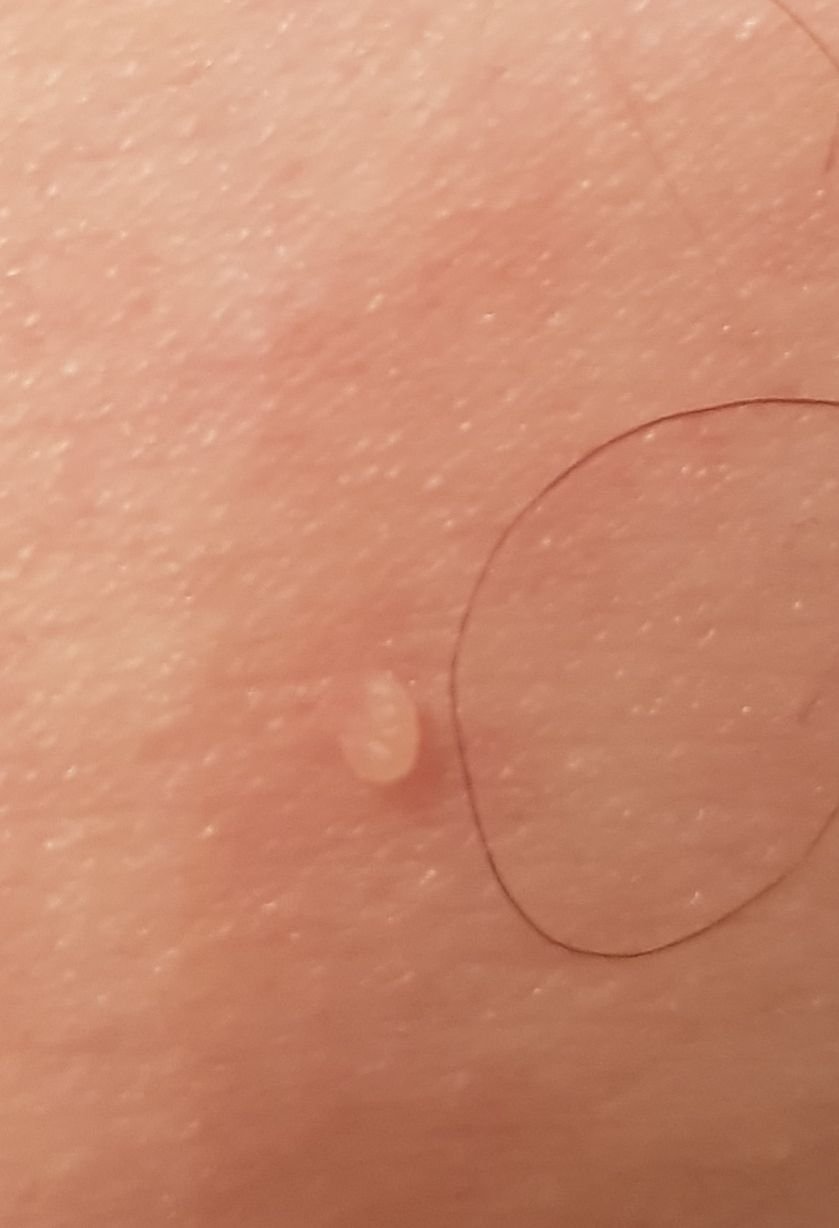
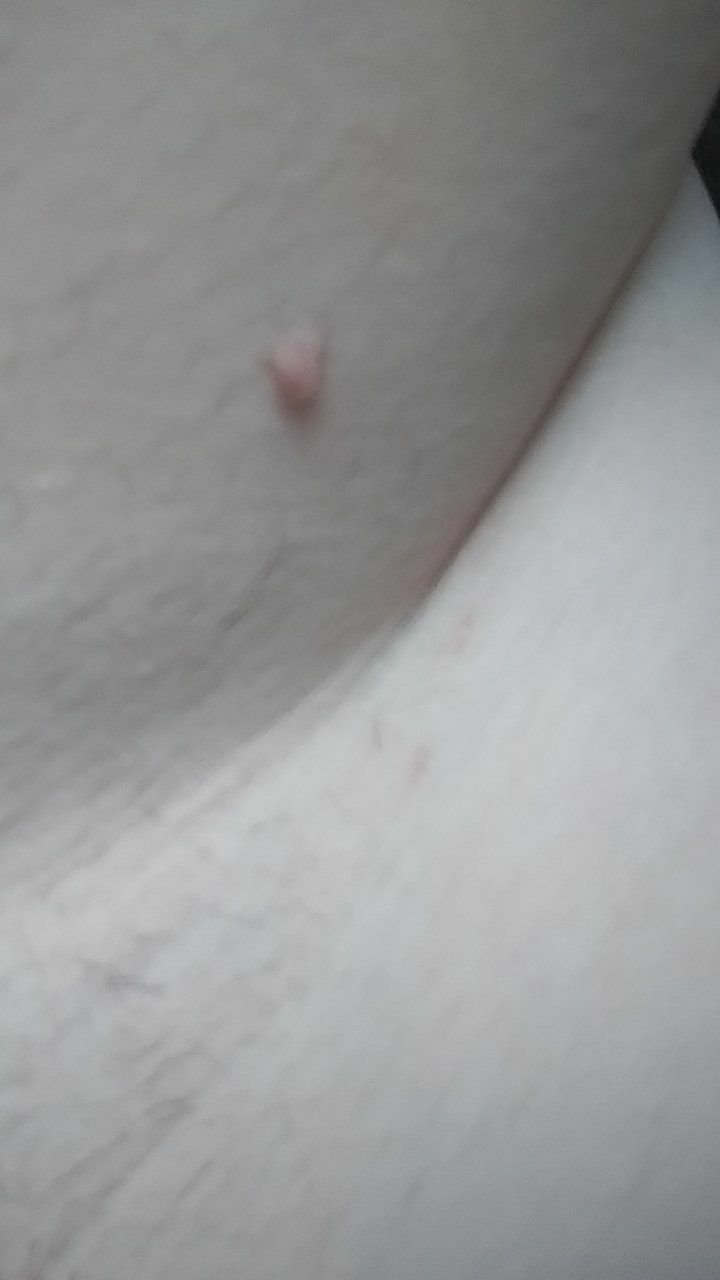
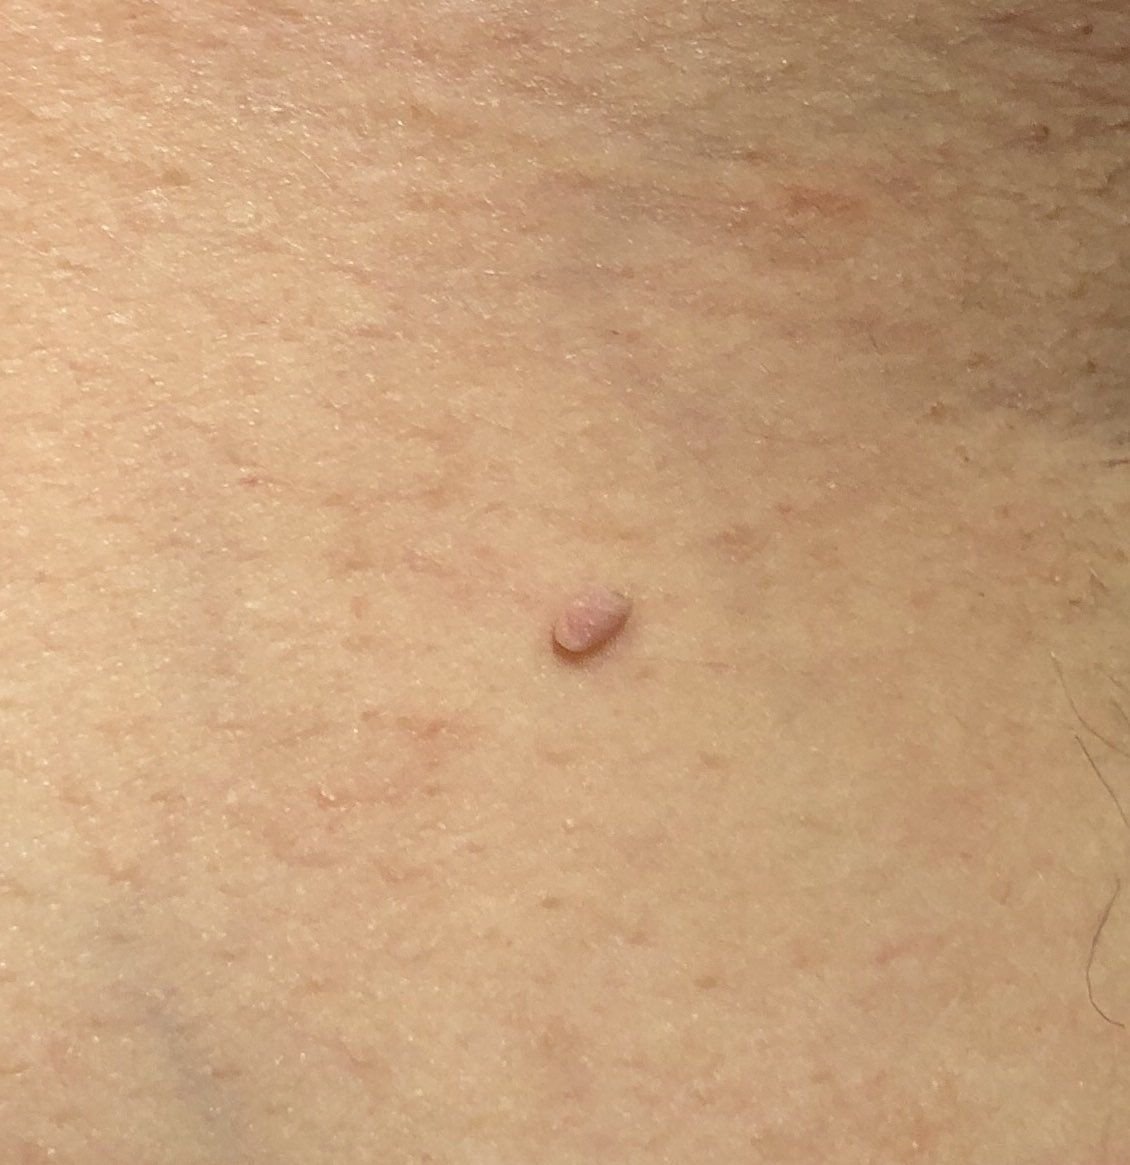
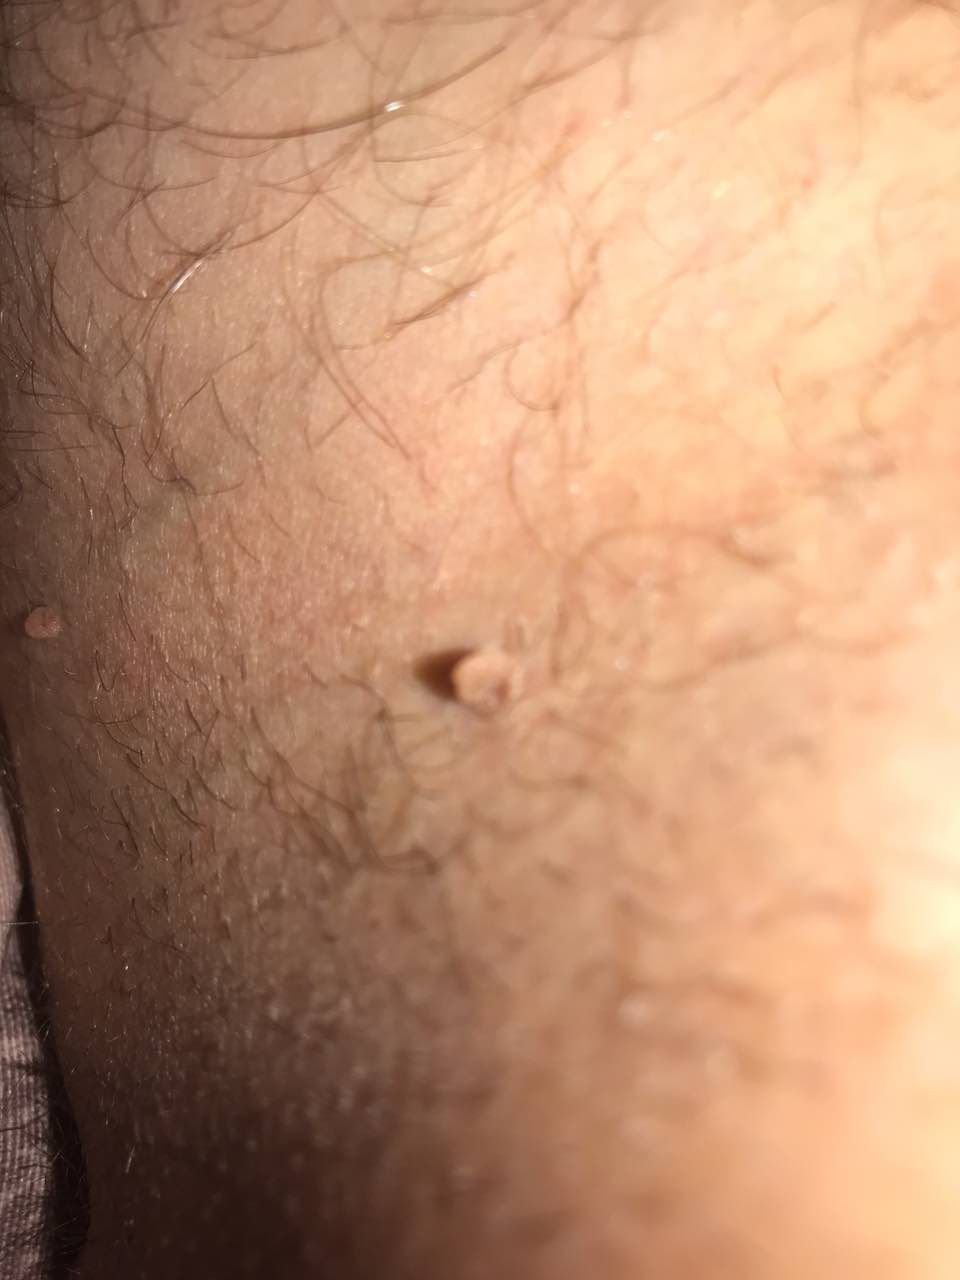
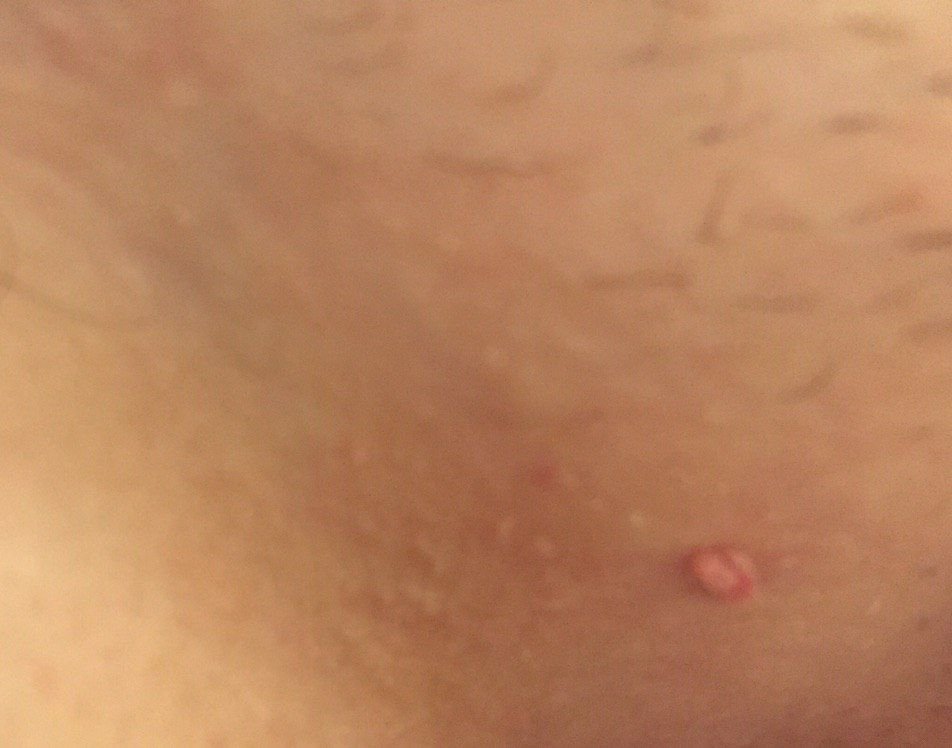
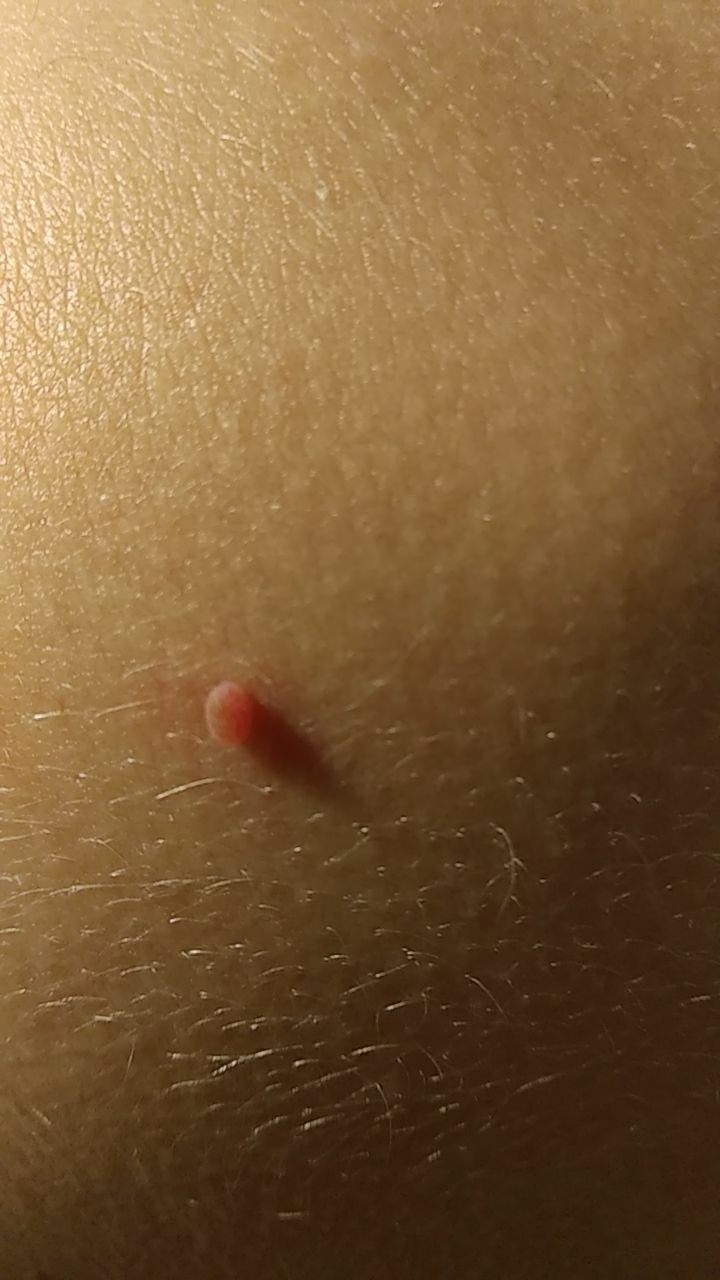
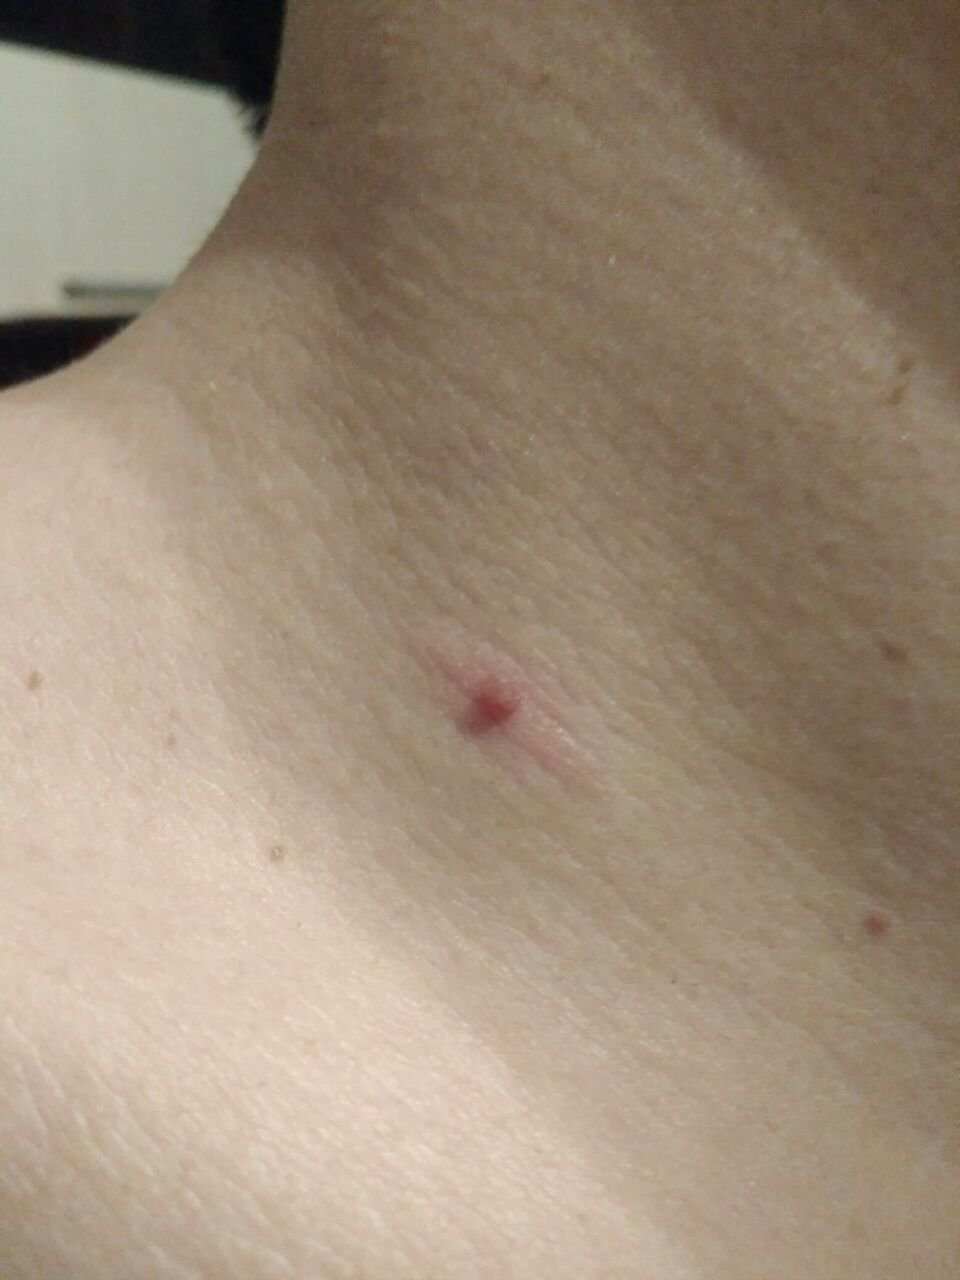
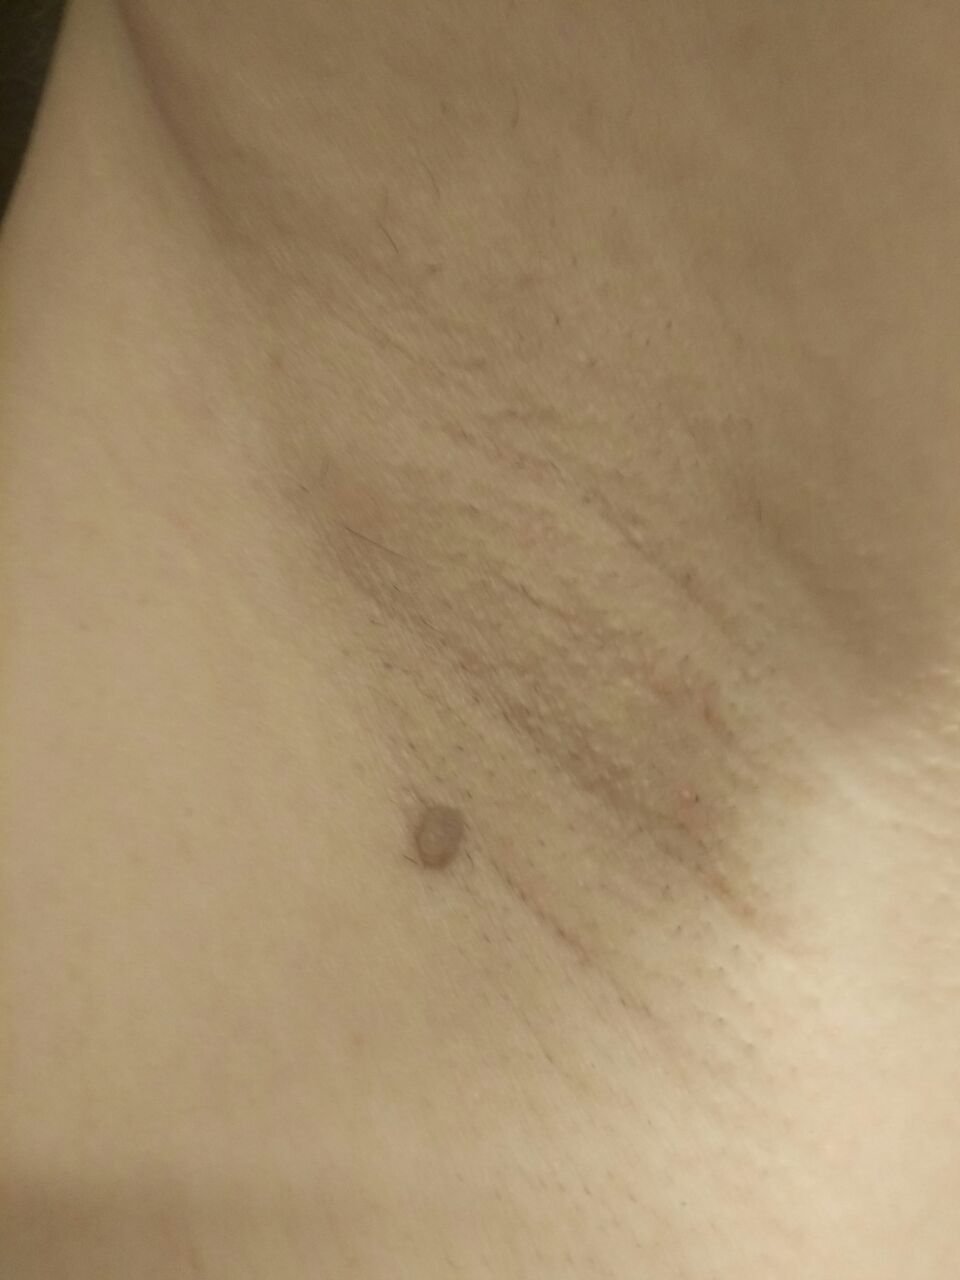
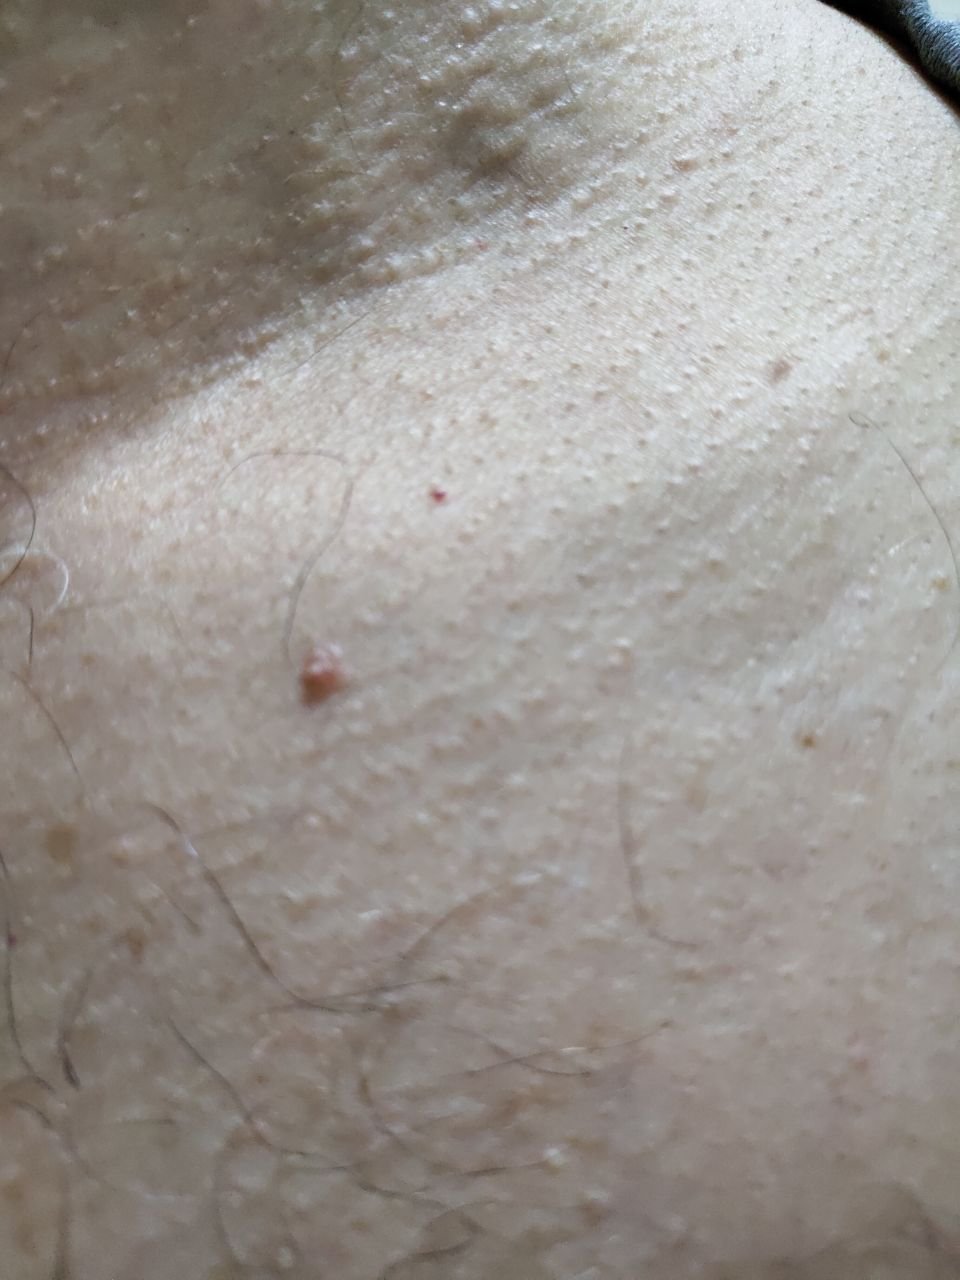
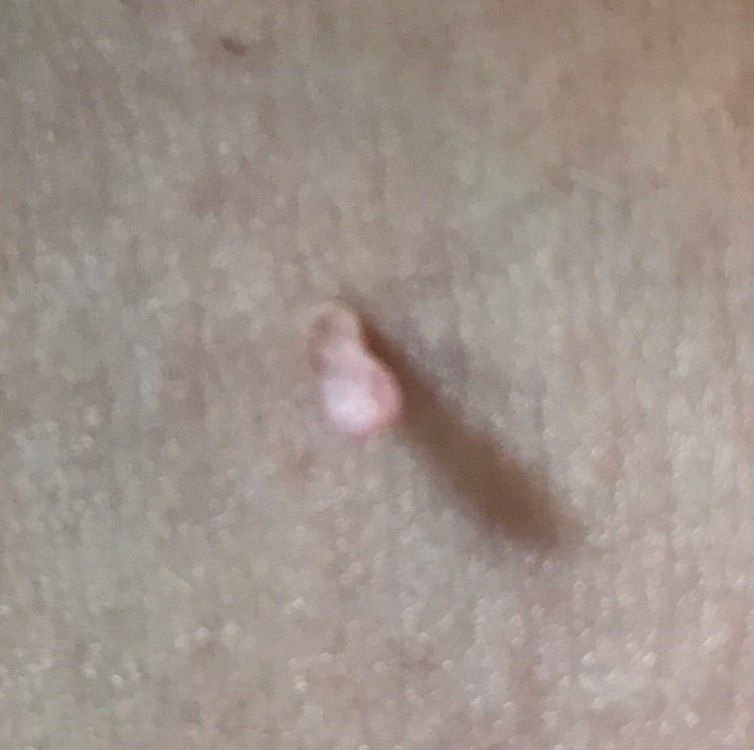
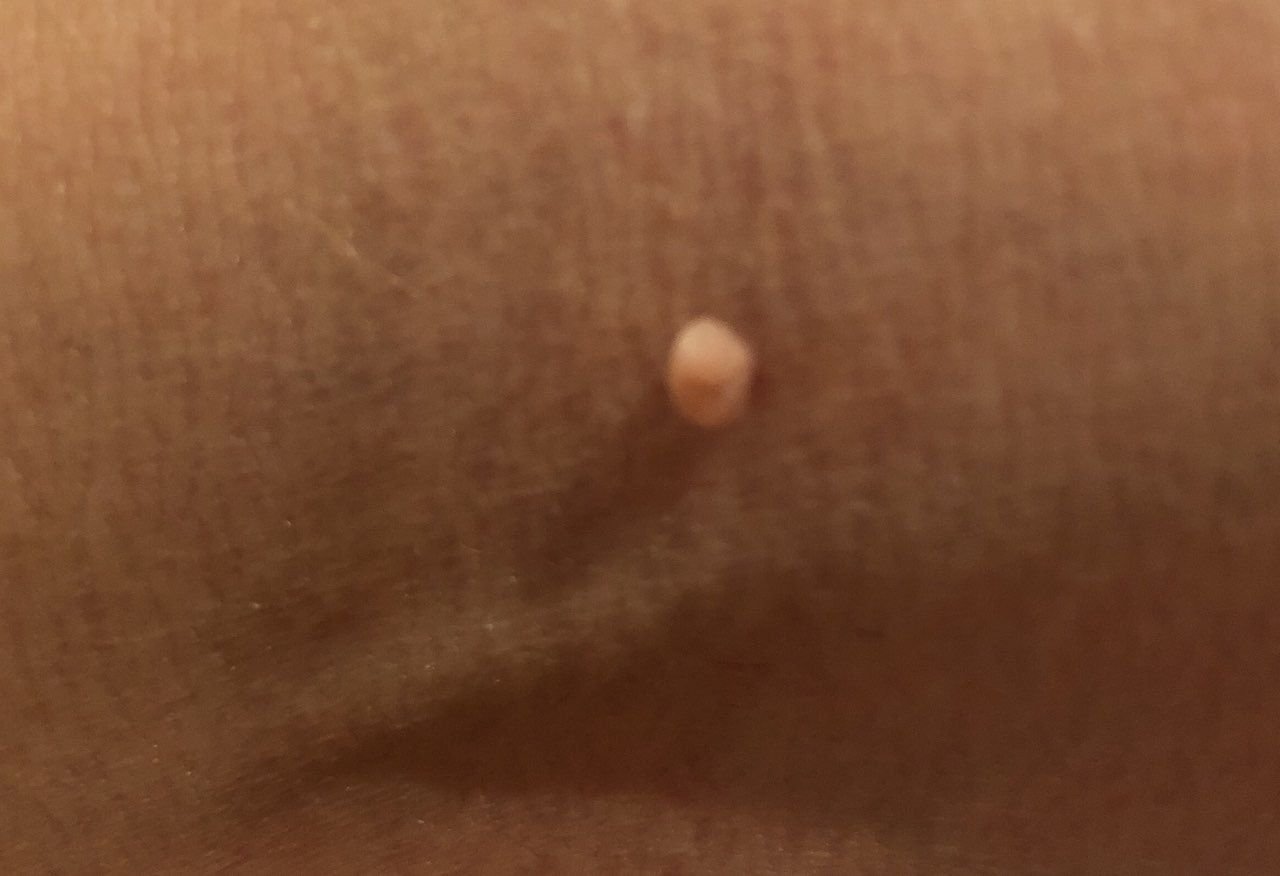
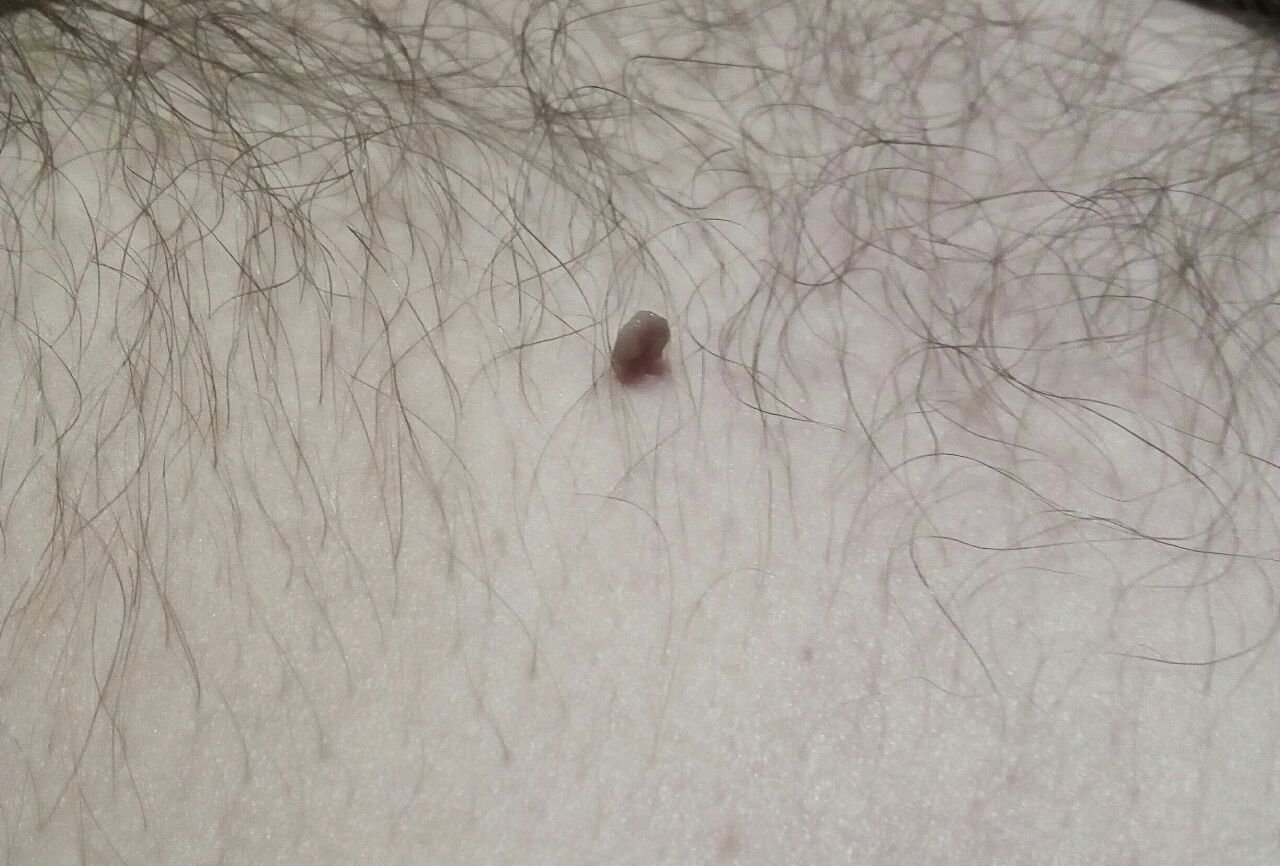
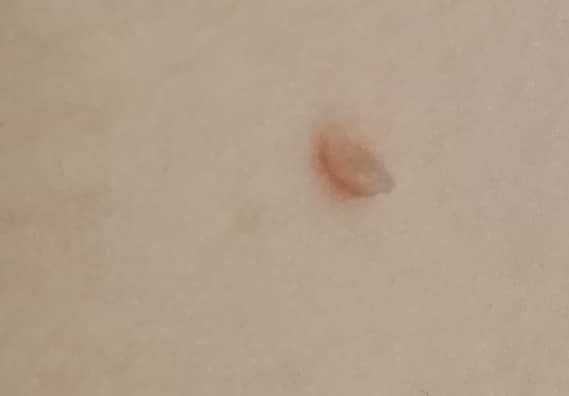
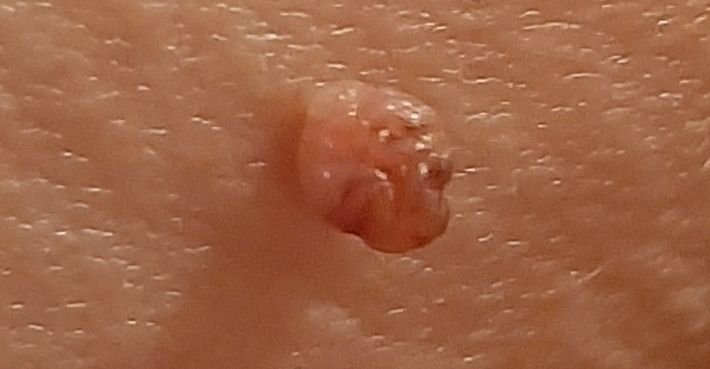
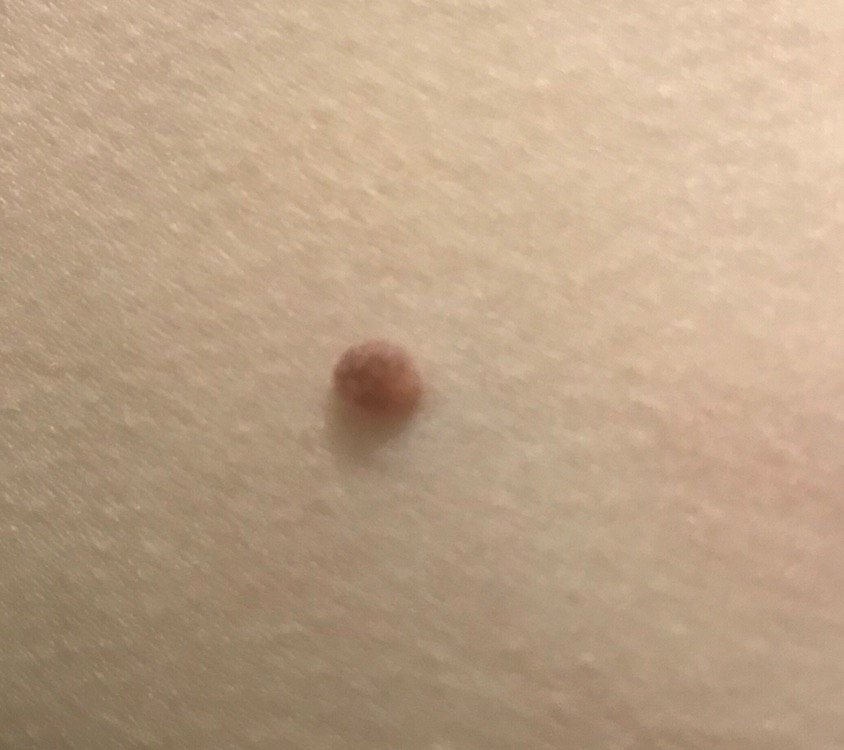
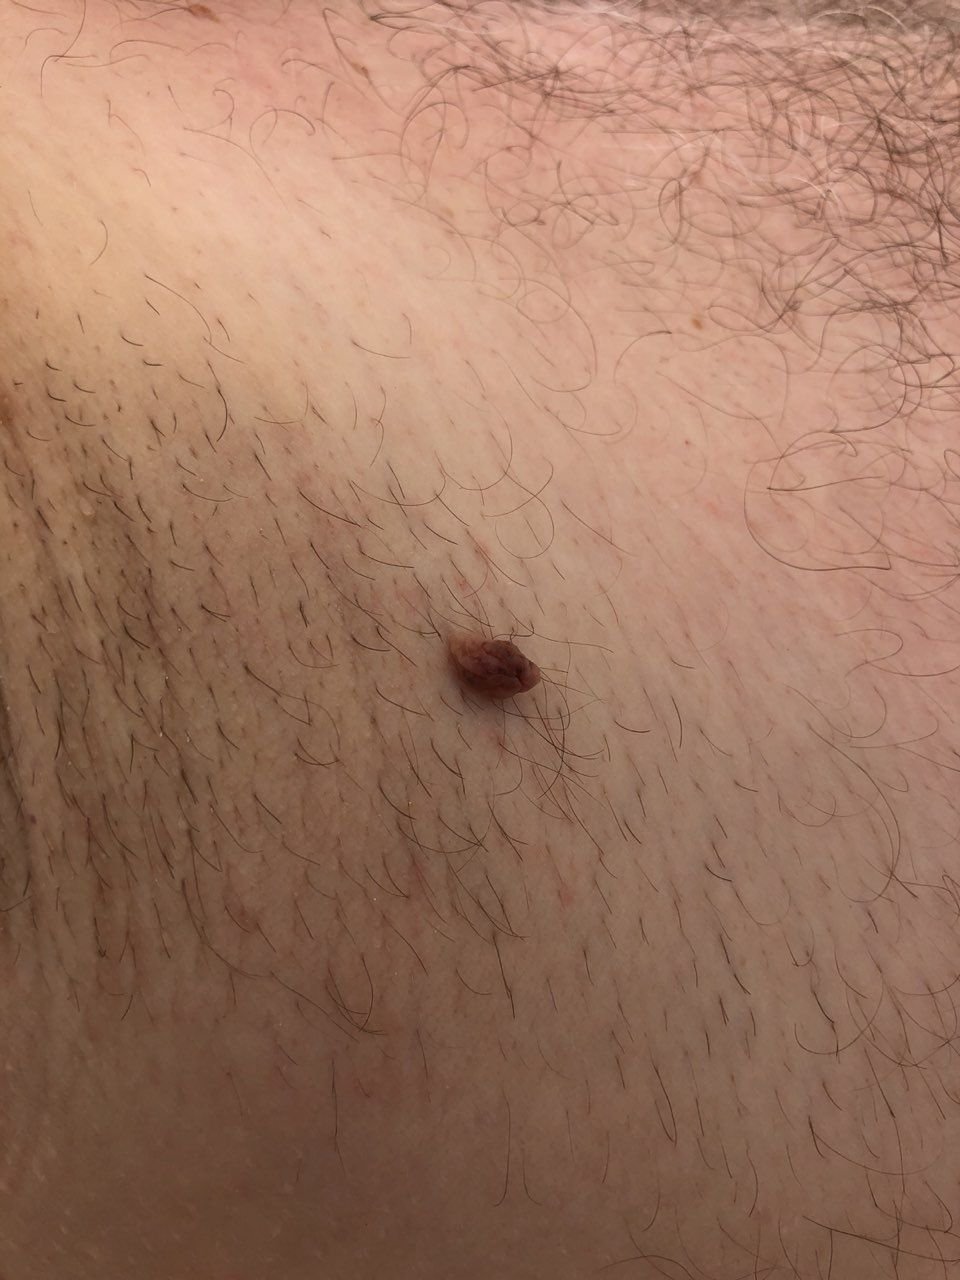
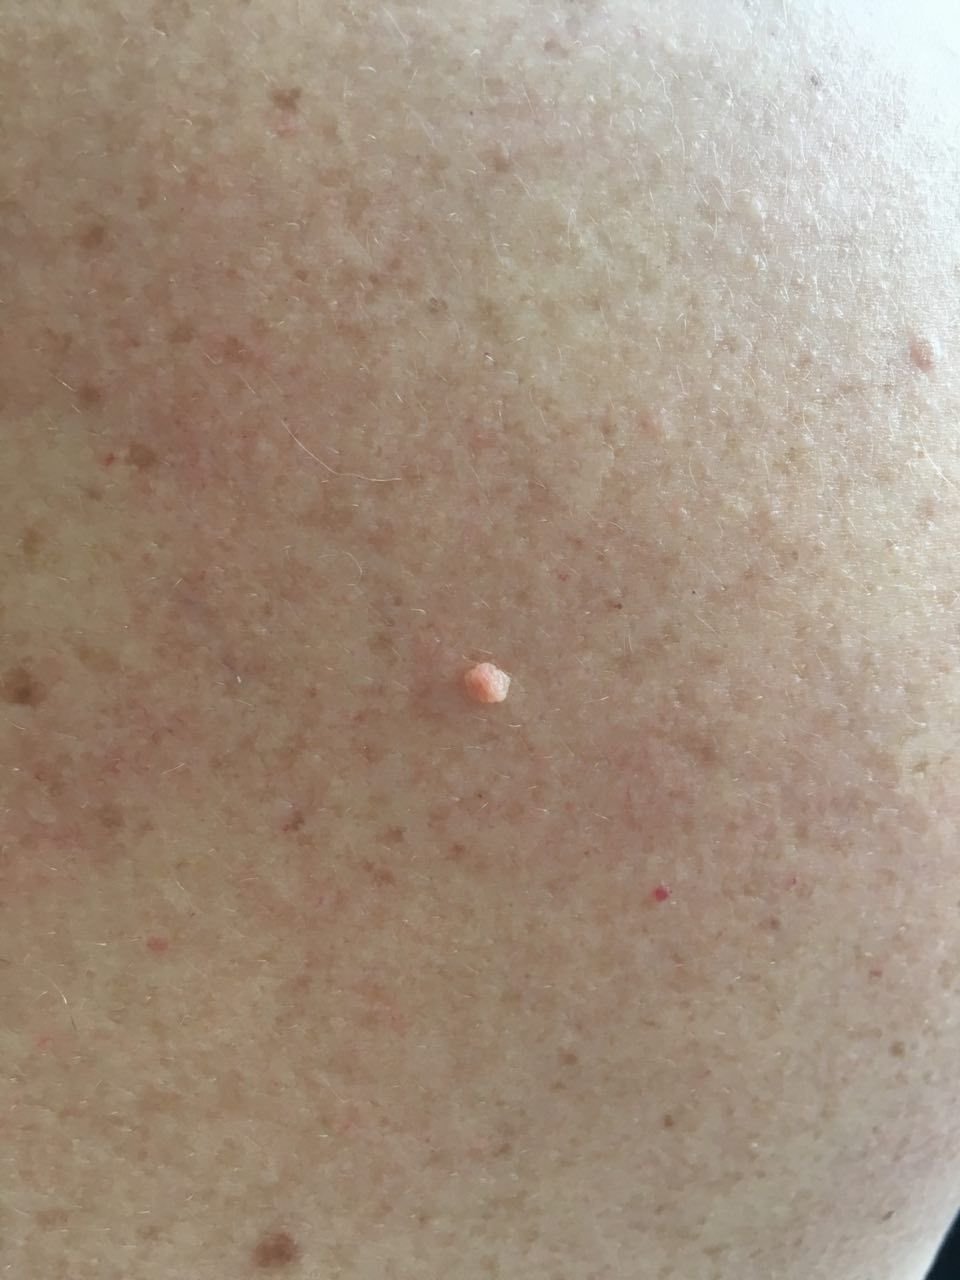
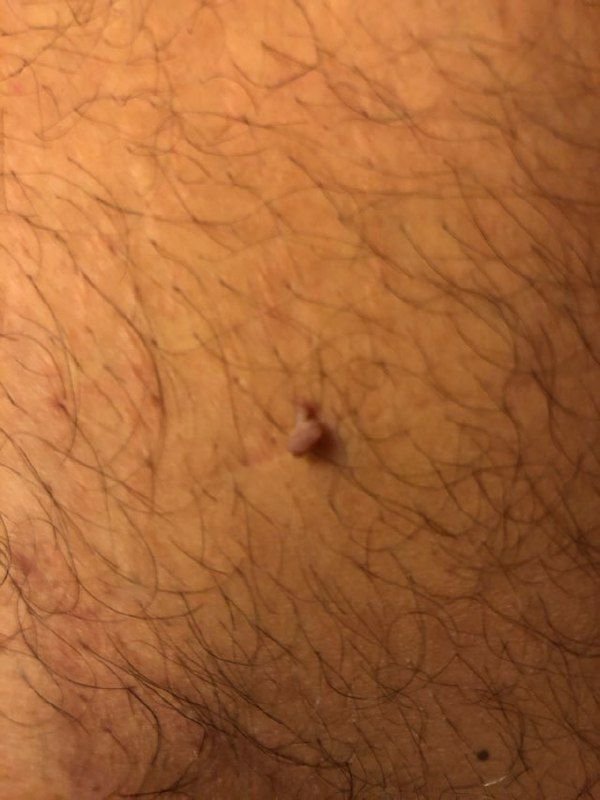
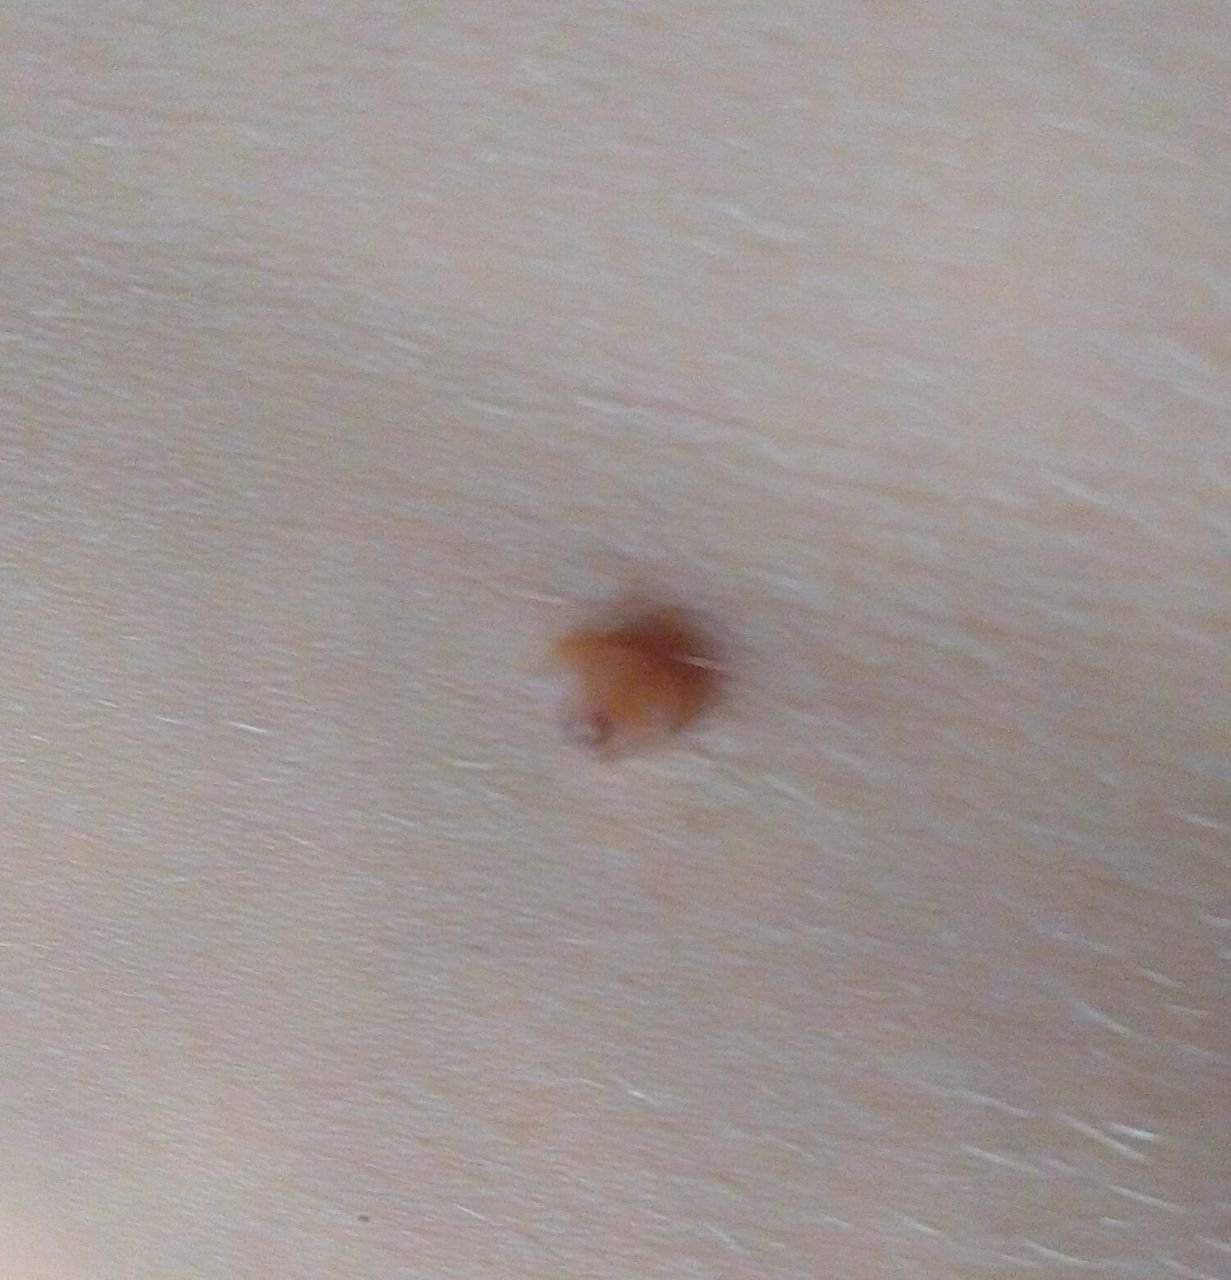
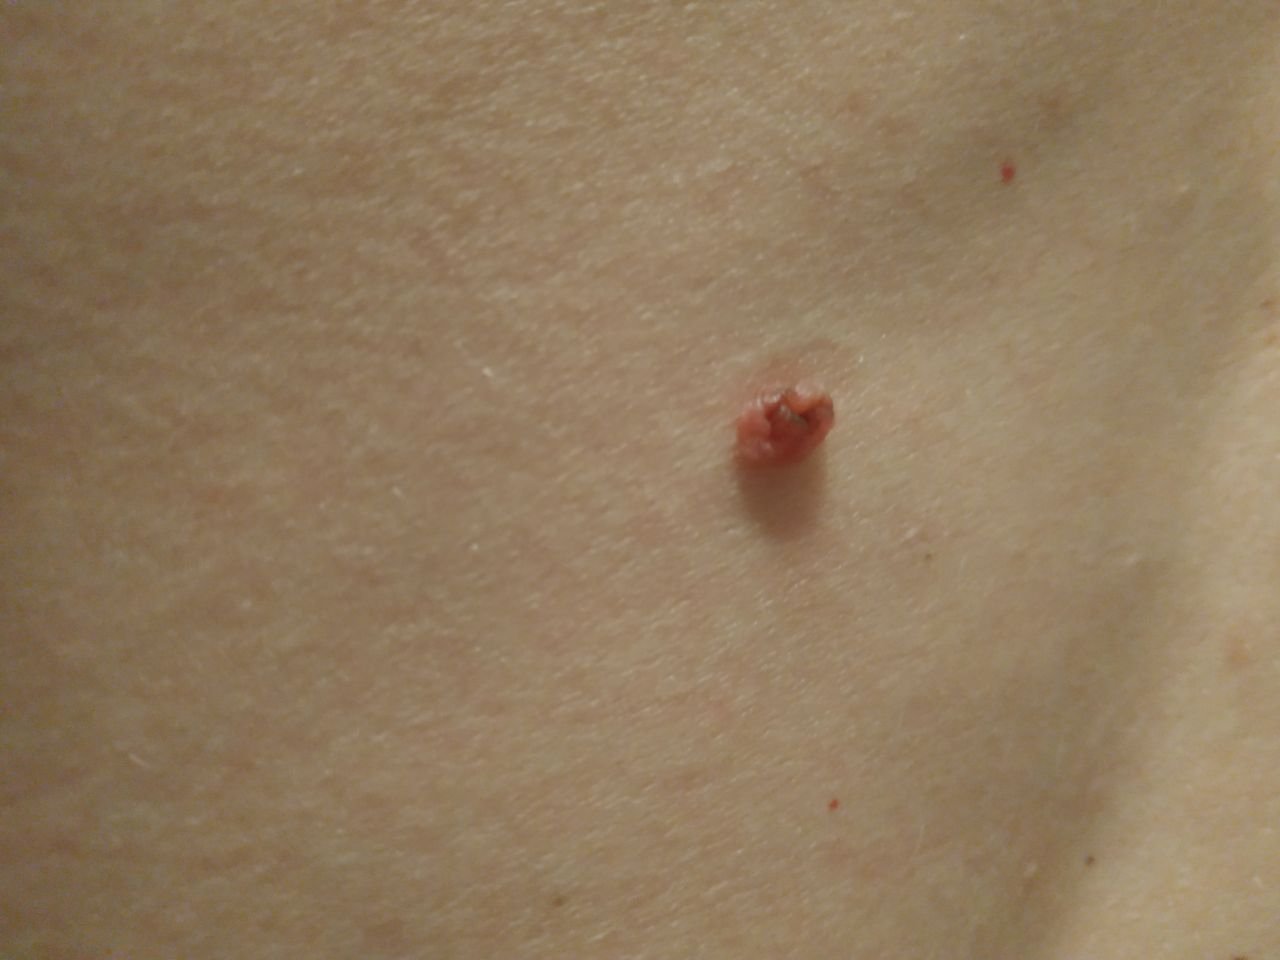
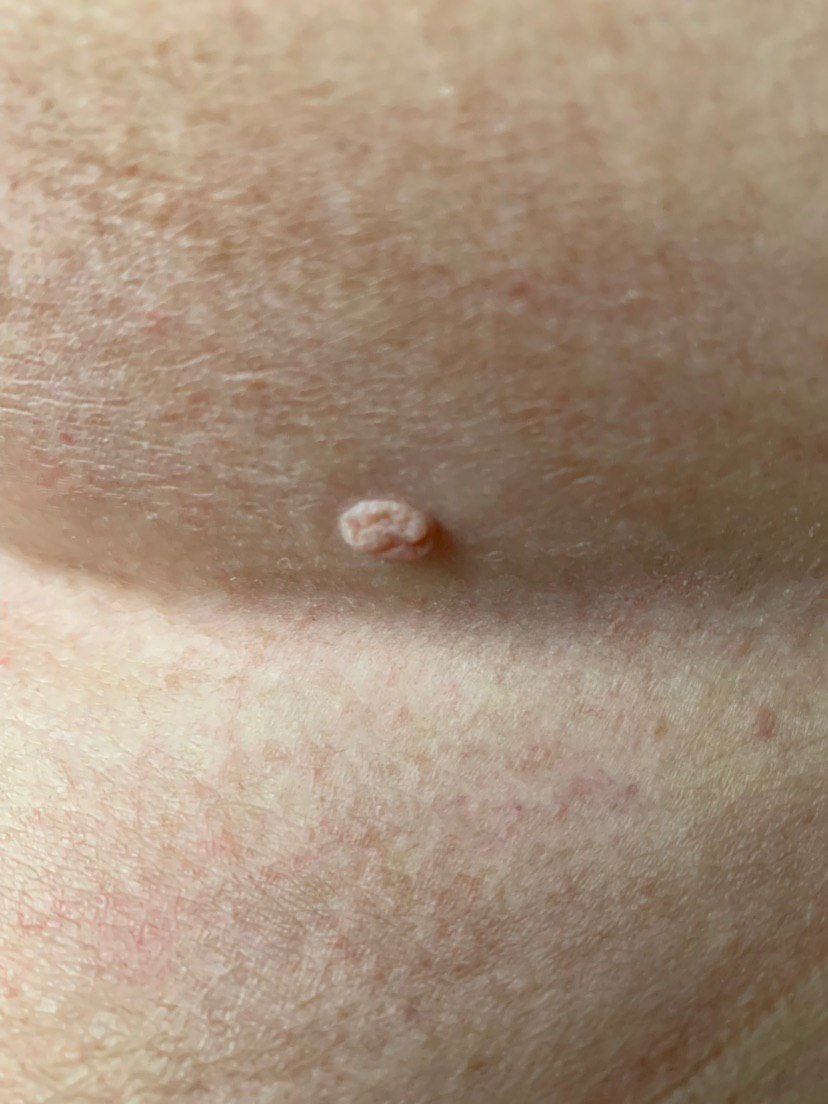
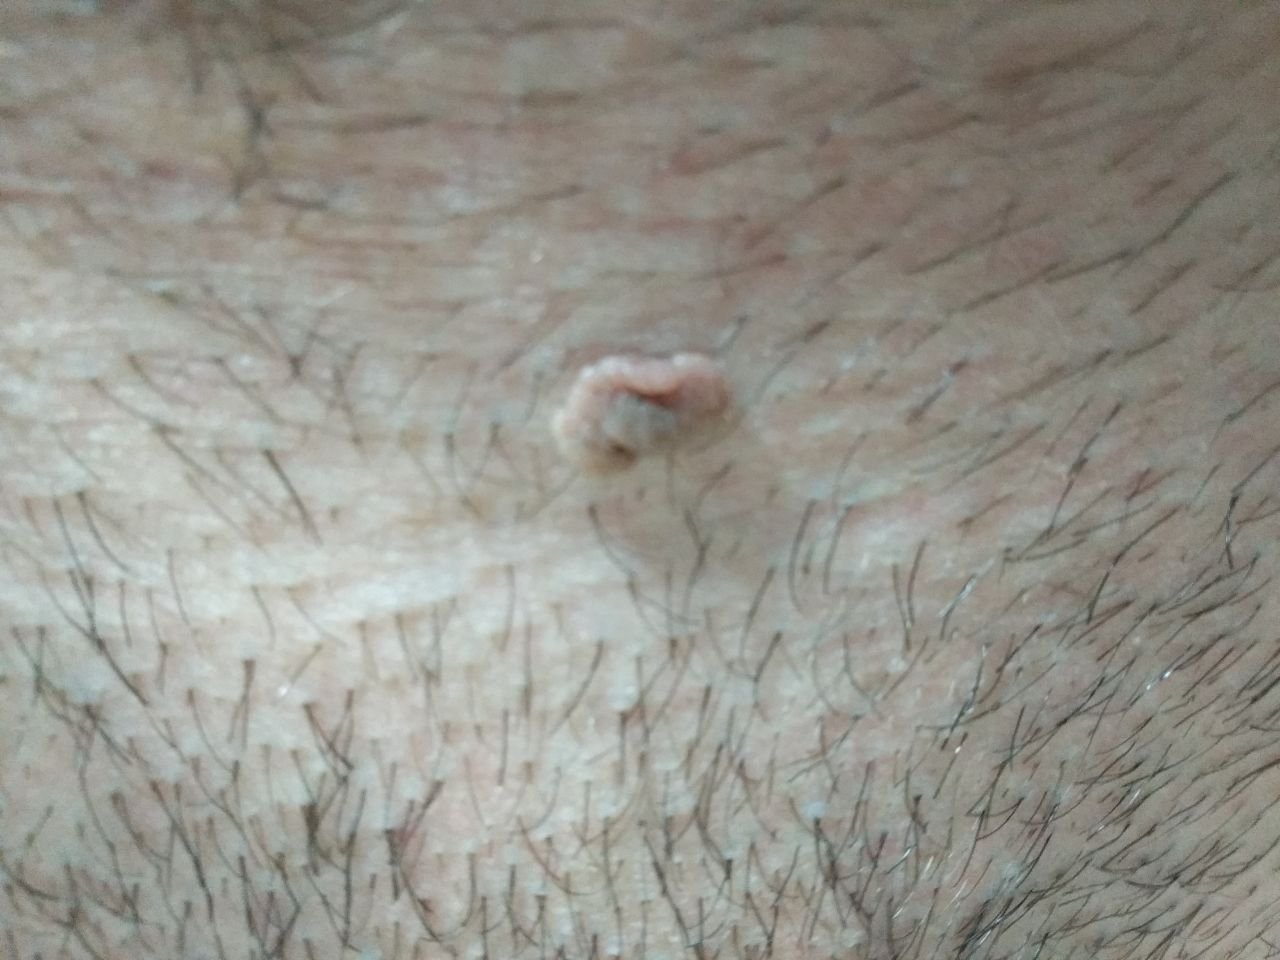
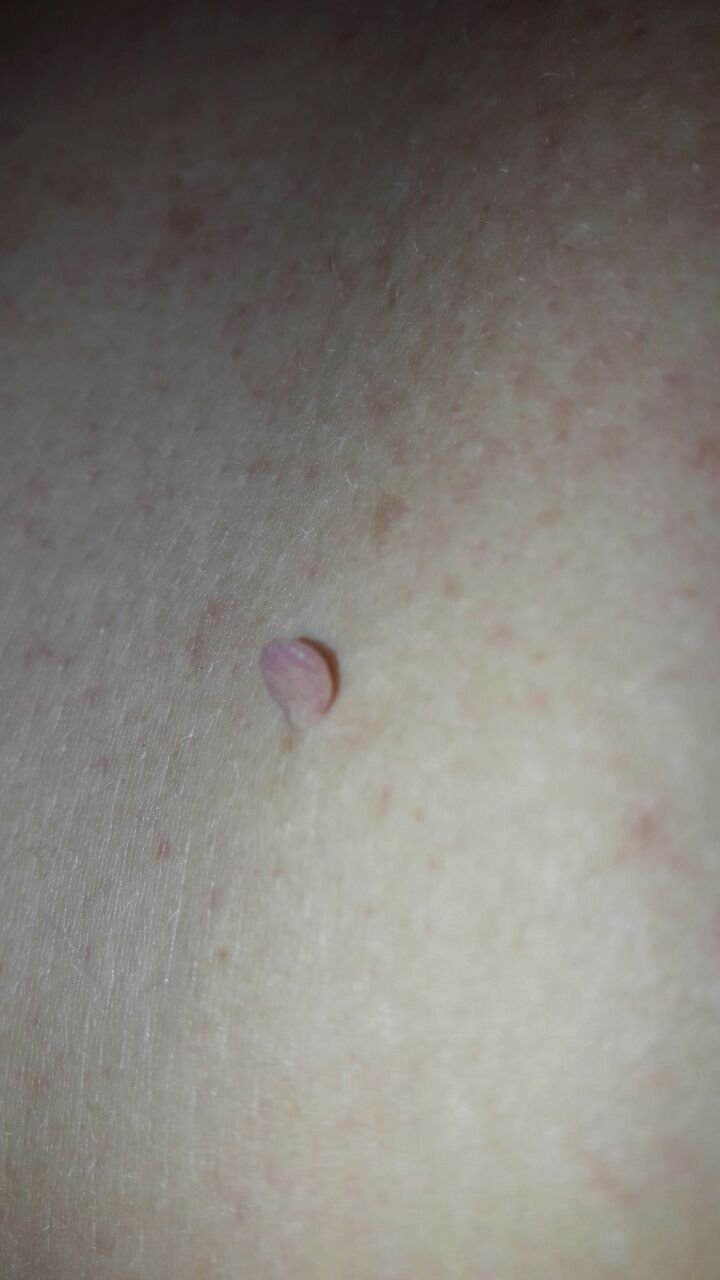
Upon visual inspection, a papilloma is recognized as an elongated formation that rises above the skin on a stem (pedicle). The stem can be as wide as the diameter of the papilloma or slightly narrower. The surface texture of the papilloma typically resembles that of normal skin, but larger papillomas may have a rough, warty surface with a “ragged” appearance.
The borders of the papilloma are generally clear, although they can be uneven, especially in larger lesions. The color of the papilloma usually varies from flesh-colored (most common) to light brown. Darker colors are rare in these lesions. Papillomas do not typically affect hair growth. In some cases, coarse bristly or fluffy hairs may be observed growing in the central part of the lesion.
The size of papillomas is usually small, with typical dimensions being up to 2-3 mm in width and 3-5 mm in height above the skin’s surface. Larger papillomas are uncommon. On palpation, the papilloma feels similar to normal skin or slightly softer, particularly in the central portion. There are no subjective sensations associated with the papilloma, although mild itching can sometimes occur in long-standing cases.
Papillomas are most commonly found on the neck, axillary regions, inguinal regions, and the trunk (chest and back), though they can also appear on mucous membranes. These lesions are less frequently found on other parts of the body.
Dermatoscopic Description
During dermatoscopy, the following features of skin papillomas can be observed:
- Papillary Structure: The characteristic flattened elements of the papilloma, often visible due to the pressure applied during dermatoscopy.
- Diffuse Uniform Staining: The entire papilloma may appear uniformly pigmented under dermatoscopy.
Differential Diagnosis
When diagnosing papillomas, they must be differentiated from other similar skin lesions, including:
- Papillomatous nevus
- Nevus of the sebaceous glands
- Halo nevus
- Dermatofibroma
- Viral wart
- Molluscum contagiosum
- Nodular basal cell carcinoma
- Pigmentless melanoma
Risks
Typical HPV-related warts are benign. A lesion that grows rapidly, becomes indurated, ulcerates, bleeds, or otherwise changes should not be read as a papilloma turning malignant; it should be reassessed, because it may be a different diagnosis altogether, malignancy among them.
Papillomas are more dangerous due to their tendency to become easily injured because of their elongated shape and narrow stalk. This can result in bleeding, pain, and the potential for infection, making the wound an entry point for harmful microorganisms. In addition, papillomas can cause cosmetic and psychological discomfort, especially if they are located in visible areas.
Many people carry HPV without ever developing a lesion, and that in itself is not a reason for oncological surveillance.
Tactics
A lesion you have not had looked at is a different matter from one a clinician has already identified. Monitoring follows assessment, not the other way round: a lesion that has not been examined should be shown to a dermatologist. “Papilloma” covers several different things, and a firm, pigmented or ulcerated growth may be something else entirely.
Once a lesion has been identified and is stable, watching it between reviews is reasonable. Go back sooner if it grows quickly, becomes firm or indurated, ulcerates, bleeds, or fails to heal.
The healthcare provider will assess whether ongoing monitoring or surgical removal of the papilloma is needed. Papillomas that experience constant trauma from clothing, jewelry, or from professional activities should be considered for removal to prevent further injury. In some cases, papillomas can be removed at the patient’s request, especially if they cause cosmetic concerns or psychological discomfort.
For dynamic observation, it is helpful to take photographs of the papillomas, as this allows for the detection of even minor changes over time. How often a person needs to be examined depends on their lesions rather than on the time of year. Keeping a map of skin neoplasms can simplify the monitoring process and help identify new or changing lesions.
Treatment
For the treatment of papillomas, less invasive methods are typically preferred:
- Laser Removal: Used for lesions of varying shapes, sizes and locations.
- Cryodestruction: Liquid nitrogen can be used to treat small, superficial papillomas, although there is a risk of scarring.
- Radio Wave Scalpel Removal: This method uses radio waves to remove the papilloma with minimal tissue damage.
- Electrocoagulation: This technique uses an electrical current to burn off the papilloma.
Which of these suits a given lesion depends on the lesion and on the diagnosis; none of them is the best method in general. They are appropriate for a lesion already identified as an ordinary wart. Where the diagnosis is uncertain or the lesion looks suspicious, it should be biopsied or excised so that the tissue can be examined — not destroyed by a method that leaves nothing to examine.
Self-removal of papillomas is not recommended due to the risk of complications such as bleeding, infection, and misdiagnosis of the lesion’s nature.
Because many cutaneous papillomas are HPV-related, recurrence is possible after removal. New papillomas may appear in the same or adjacent areas after removal. Preventative measures help reduce the likelihood of relapse.
Prevention
Preventing the appearance of papillomas involves a careful and proactive approach to skincare and overall health:
- Limit exposure to ultraviolet radiation, such as from tanning beds or prolonged sun exposure.
- Use sunscreen and protective clothing during periods of intense sunlight.
- Avoid chronic skin trauma that can lead to injury and create an entry point for HPV.
- Follow safety protocols when handling skin-damaging chemicals or substances.
- Maintain good personal hygiene and stay vigilant for any changes in skin health.
It is also important to regularly inspect papillomas, seek timely consultation with a healthcare professional if any changes are observed, and remove potentially dangerous lesions to prevent complications.